
A case of Dengue Virus & Ricketssia co-infection














Description: A case of Dengue Virus Ricketssia co-infection Department of Microbiology Dr. Prachi C. Bhide Case A 55 year old male patient came to Medicine OPD with complaints of Fever since 8 days. (kco Dengue fever; Dengue IgM antibody: positive-
Related Topics
Download Presentation
"A case of Dengue Virus & Ricketssia co-infection" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. A case of Dengue Virus & Ricketssia co-infection Department of Microbiology
Dr. Prachi C. Bhide<br>
slide2. Case A 55 year old male patient came to Medicine OPD with complaints of
Fever since 8 days.
(k/c/o Dengue fever; Dengue IgM antibody: positive- diagnosed at outside laboratory),
Platelet count: 1.5lakh/cumm
Breathlessness since 3 days
Increase in fever spikes since 1 day
k/c/o Hypertension
No h/o chest pain, vomiting, diarrhea<br>
slide3. On examination:
Conscious, oriented
Temp- 1020F
Pulse: 96/min
BP: 130/80 mm Hg<br>
slide4. On further investigations;
Patient was diagnosed to have Diabetes Mellitus(DM)
His HRCT revealed bilateral lower zone consolidation
There were 2-3 spikes of fever everyday
Hence patient was admitted to MICU with diagnosis of LRTI because of ? Bacterial pneumonia with Acute kidney injury(AKI).<br>
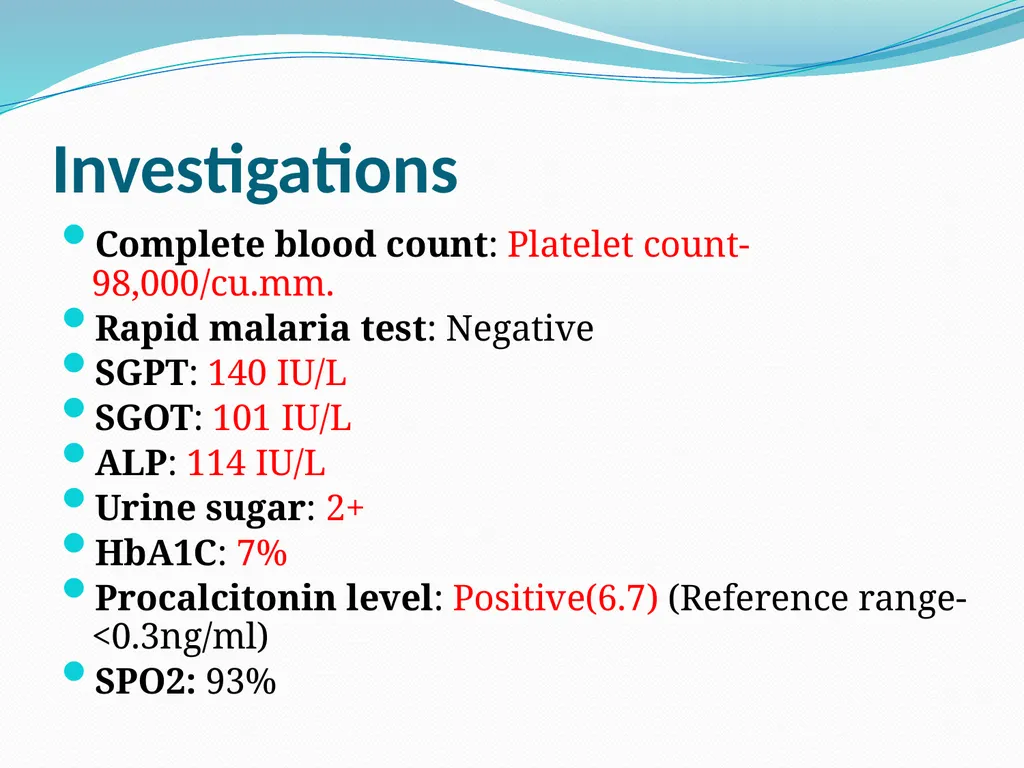
slide5. Investigations Complete blood count: Platelet count- 98,000/cu.mm.
Rapid malaria test: Negative
SGPT: 140 IU/L
SGOT: 101 IU/L
ALP: 114 IU/L
Urine sugar: 2+
HbA1C: 7%
Procalcitonin level: Positive(6.7) (Reference range- <0.3ng/ml)
SPO2: 93%<br>
slide6. Quantitative CRP: 67.8mg/L (Reference range- 0-6 mg/L)
To rule out H1N1 flu: Throat swab was sent to National Institute of Virology(NIV): Report was negative for Influenza A(H1N1) & other seasonal Influenza report
Dengue IgM by ELISA: Positive
Leptospira: Negative
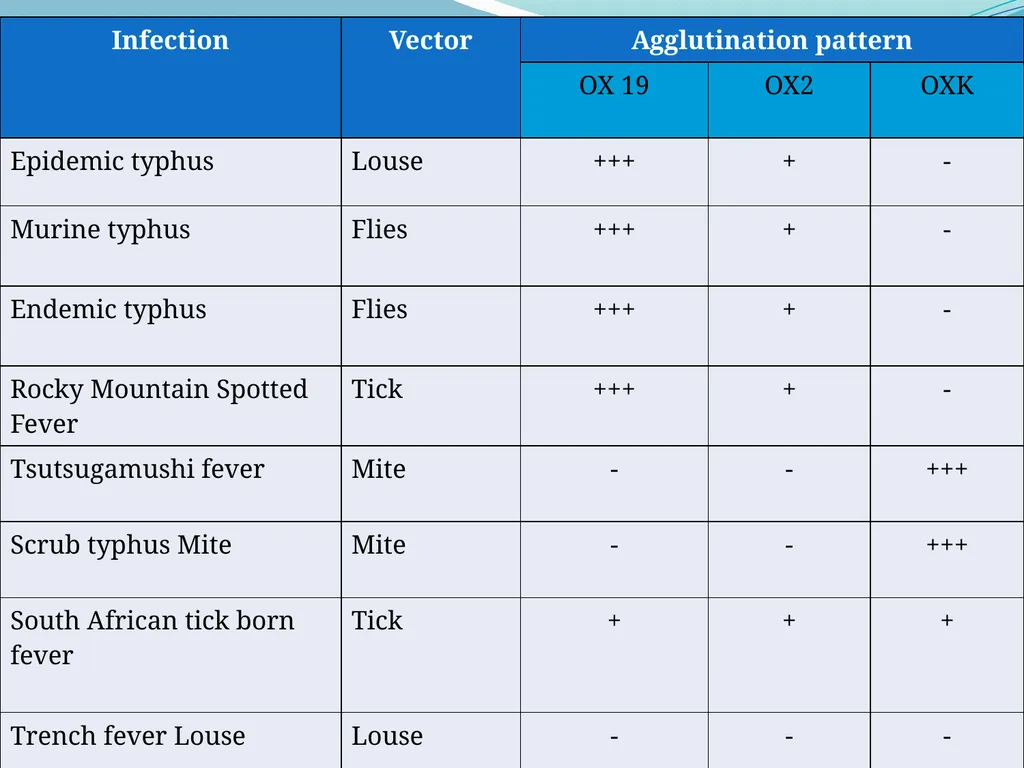
Weil-Felix test: Positive
Titre: OX 2- 1: 640
OX K- Negative
OX 19- 1:1280<br>
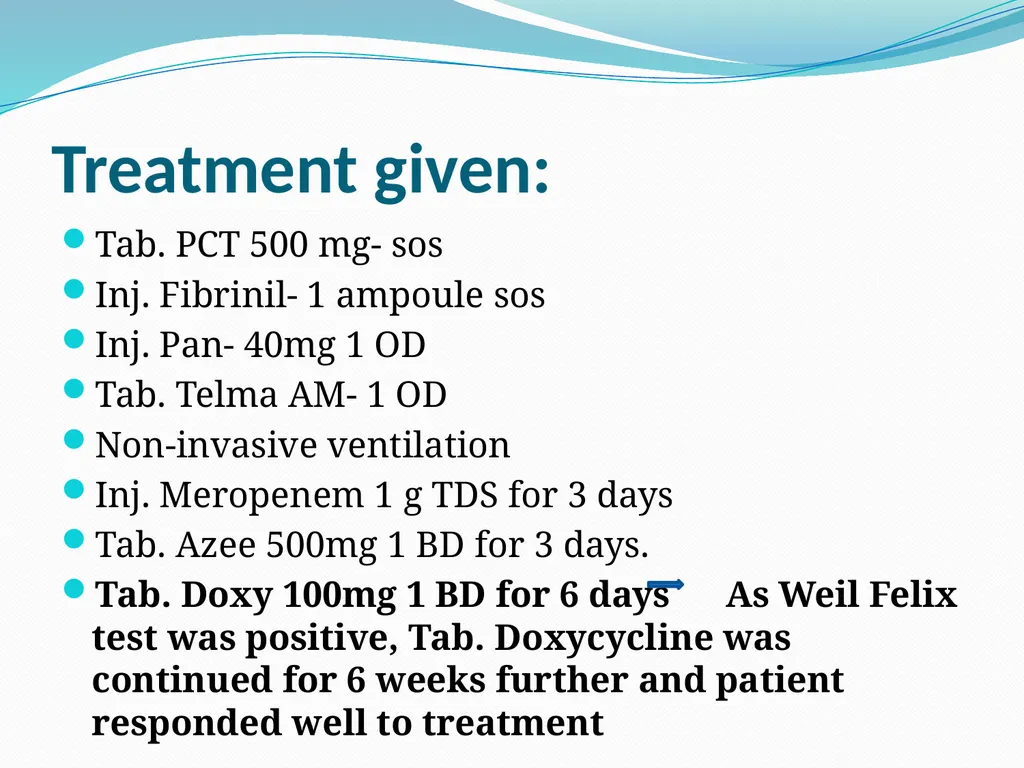
slide8. Treatment given: Tab. PCT 500 mg- sos
Inj. Fibrinil- 1 ampoule sos
Inj. Pan- 40mg 1 OD
Tab. Telma AM- 1 OD
Non-invasive ventilation
Inj. Meropenem 1 g TDS for 3 days
Tab. Azee 500mg 1 BD for 3 days.
Tab. Doxy 100mg 1 BD for 6 days As Weil Felix test was positive, Tab. Doxycycline was continued for 6 weeks further and patient responded well to treatment<br>
slide9. Patient got discharged on request after 3 days of admission.
He got admitted to another tertiary care hospital for further management.
After further follow up with patient by telephonic conversation; it was confirmed that patient responded well to
6 weeks Tab Doxycycline treatment(100 mg BD)
Symtomatic treatment for Dengue fever<br>
slide10. Dengue & co-infection in tropics Acute febrile illness is a common clinical syndrome among patients seeking hospital care in India.
Concurrent infection with two agents can result in an illness having overlapping symptoms creating a diagnostic dilemma for the treating physician.
Common co-infection with Dengue virus in India
Salmonella Typhi
Chikungunya virus
Plasmodium spp.
Leptospira
Influenza A virus
Ricketssia
JE virus<br>
slide11. Discussion: Dengue- a mosquito-borne viral infection
Ricketssial infections- caused by Ricketssiae which are diverse group of organisms transmitted by arthropod vectors(lice, fleas, ticks, mites)
In India, Ricketssial infections are reported from Maharashtra, Tamil nadu, Karnataka, Kerala, Jammu and Kashmir, Uttaranchal, Himachal Pradesh, Rajasthan, Assam and West Bengal.
Both diseases have several clinical and laboratory features in common, including rash, thrombocytopenia, and hepatic dysfunction. However, concurrent infection with both pathogens is exceedingly rare, primarily due to the different vectors involved.
Concurrent infection with multiple pathogens is common in tropics, posing diagnostic and treatment challenges.<br>
slide12. Data on dengue and ricketssial fever co-infection is distinctly limited.
Dengue-ricketssial fever co-infection may remain under-diagnosed in tropics, particularly confounded during dengue epidemics.
Normal leukocyte counts, early drop in platelets and hypoalbuminemia in dengue patients could be clues to concurrent ricketssial fever infection.
Prompt recognition and treatment of ricketssial infection in such cases may reduce unnecessary hospital stay and cost.<br>
slide13. Similar case reports from India Pondicherry Institute of Medical Sciences, Puducherry- 2010-2014- 6 cases of Dengue fever- Scrub typhus co-infection
I.G. Medical College, Shimla- 2015- 1 case of Dengue fever- Scrub typhus co-infection
Himalayan Institute of Medical Sciences, Dehradun- 2015- Rare Co-infection of Malaria, Scrub Typhus and Dengue virus in an Immunocompetent Patient<br>
slide14. Take Home Message Very limited data on dengue and ricketssial fever co-infection
High index of suspicion about ricketssial fever
Additional tests should be done for accurate diagnosis in a case of un-resolving fever in endemic regions to reduce morbidity & mortality<br>
slide15. References Mediterr J Hematol Infect Dis. 2016; 8(1): e2016028
The Indian Practitioner. Volume 68, Issue 9, September 2015
Int.J.Curr.Microbiol.App.Sci (2015) 4(5): 295-297
Indian peadeatr. 2010 Feb;47(2):157-64.<br>
slide16. Thank you…<br>
Dr. Prachi C. Bhide<br>
slide2. Case A 55 year old male patient came to Medicine OPD with complaints of
Fever since 8 days.
(k/c/o Dengue fever; Dengue IgM antibody: positive- diagnosed at outside laboratory),
Platelet count: 1.5lakh/cumm
Breathlessness since 3 days
Increase in fever spikes since 1 day
k/c/o Hypertension
No h/o chest pain, vomiting, diarrhea<br>
slide3. On examination:
Conscious, oriented
Temp- 1020F
Pulse: 96/min
BP: 130/80 mm Hg<br>
slide4. On further investigations;
Patient was diagnosed to have Diabetes Mellitus(DM)
His HRCT revealed bilateral lower zone consolidation
There were 2-3 spikes of fever everyday
Hence patient was admitted to MICU with diagnosis of LRTI because of ? Bacterial pneumonia with Acute kidney injury(AKI).<br>
slide5. Investigations Complete blood count: Platelet count- 98,000/cu.mm.
Rapid malaria test: Negative
SGPT: 140 IU/L
SGOT: 101 IU/L
ALP: 114 IU/L
Urine sugar: 2+
HbA1C: 7%
Procalcitonin level: Positive(6.7) (Reference range- <0.3ng/ml)
SPO2: 93%<br>
slide6. Quantitative CRP: 67.8mg/L (Reference range- 0-6 mg/L)
To rule out H1N1 flu: Throat swab was sent to National Institute of Virology(NIV): Report was negative for Influenza A(H1N1) & other seasonal Influenza report
Dengue IgM by ELISA: Positive
Leptospira: Negative
Weil-Felix test: Positive
Titre: OX 2- 1: 640
OX K- Negative
OX 19- 1:1280<br>
slide8. Treatment given: Tab. PCT 500 mg- sos
Inj. Fibrinil- 1 ampoule sos
Inj. Pan- 40mg 1 OD
Tab. Telma AM- 1 OD
Non-invasive ventilation
Inj. Meropenem 1 g TDS for 3 days
Tab. Azee 500mg 1 BD for 3 days.
Tab. Doxy 100mg 1 BD for 6 days As Weil Felix test was positive, Tab. Doxycycline was continued for 6 weeks further and patient responded well to treatment<br>
slide9. Patient got discharged on request after 3 days of admission.
He got admitted to another tertiary care hospital for further management.
After further follow up with patient by telephonic conversation; it was confirmed that patient responded well to
6 weeks Tab Doxycycline treatment(100 mg BD)
Symtomatic treatment for Dengue fever<br>
slide10. Dengue & co-infection in tropics Acute febrile illness is a common clinical syndrome among patients seeking hospital care in India.
Concurrent infection with two agents can result in an illness having overlapping symptoms creating a diagnostic dilemma for the treating physician.
Common co-infection with Dengue virus in India
Salmonella Typhi
Chikungunya virus
Plasmodium spp.
Leptospira
Influenza A virus
Ricketssia
JE virus<br>
slide11. Discussion: Dengue- a mosquito-borne viral infection
Ricketssial infections- caused by Ricketssiae which are diverse group of organisms transmitted by arthropod vectors(lice, fleas, ticks, mites)
In India, Ricketssial infections are reported from Maharashtra, Tamil nadu, Karnataka, Kerala, Jammu and Kashmir, Uttaranchal, Himachal Pradesh, Rajasthan, Assam and West Bengal.
Both diseases have several clinical and laboratory features in common, including rash, thrombocytopenia, and hepatic dysfunction. However, concurrent infection with both pathogens is exceedingly rare, primarily due to the different vectors involved.
Concurrent infection with multiple pathogens is common in tropics, posing diagnostic and treatment challenges.<br>
slide12. Data on dengue and ricketssial fever co-infection is distinctly limited.
Dengue-ricketssial fever co-infection may remain under-diagnosed in tropics, particularly confounded during dengue epidemics.
Normal leukocyte counts, early drop in platelets and hypoalbuminemia in dengue patients could be clues to concurrent ricketssial fever infection.
Prompt recognition and treatment of ricketssial infection in such cases may reduce unnecessary hospital stay and cost.<br>
slide13. Similar case reports from India Pondicherry Institute of Medical Sciences, Puducherry- 2010-2014- 6 cases of Dengue fever- Scrub typhus co-infection
I.G. Medical College, Shimla- 2015- 1 case of Dengue fever- Scrub typhus co-infection
Himalayan Institute of Medical Sciences, Dehradun- 2015- Rare Co-infection of Malaria, Scrub Typhus and Dengue virus in an Immunocompetent Patient<br>
slide14. Take Home Message Very limited data on dengue and ricketssial fever co-infection
High index of suspicion about ricketssial fever
Additional tests should be done for accurate diagnosis in a case of un-resolving fever in endemic regions to reduce morbidity & mortality<br>
slide15. References Mediterr J Hematol Infect Dis. 2016; 8(1): e2016028
The Indian Practitioner. Volume 68, Issue 9, September 2015
Int.J.Curr.Microbiol.App.Sci (2015) 4(5): 295-297
Indian peadeatr. 2010 Feb;47(2):157-64.<br>
slide16. Thank you…<br>