
Category |A| Biological Agents Louisiana Office of




























































Description: Category A Biological Agents Louisiana Office of Public Health Center for Community Preparedness Training Objectives Describe the CDCs Category A biological threat agents. Describe the public health considerations involved in the release
Related Topics
Download Presentation
"Category |A| Biological Agents Louisiana Office of" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Category |A| Biological Agents Louisiana Office of Public Health
Center for Community Preparedness<br>
slide2. Training Objectives Describe the CDC’s Category A biological threat agents.
Describe the public health considerations involved in the release of a biological threat agent.
Discuss the recognition of potential bioterrorism events and the formulation of an appropriate response strategy. OPH Center for Community Preparedness<br>
slide3. Biological Weapons Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide4. Biological Weapons Biological warfare (BW), also known as germ warfare, is the deliberate use of disease-causing biological agents such as protozoa, fungi, bacteria, protists, or viruses, to kill or incapacitate humans, other animals, or plants.
Biological weapons (bioweapons) are living organisms or replicating entities (virus) that reproduce or replicate within their host victims. OPH Center for Community Preparedness<br>
slide5. Biological Weapons | Uses Mass casualties
Morbidity
Mortality
Destruction of resources
Agriculture
Drinking water
Societal disruption
Overwhelm local resources
Breakdown of order
Panic and fear
Economic hardship OPH Center for Community Preparedness<br>
slide6. Biological Weapons | Historical Offensive biological warfare (developing and stockpiling bioweapons) was outlawed in 1972 by the Biological Weapons Convention (BWC). As of 2009, 163 nations had ratified the BWC.
The United States’ biological weapons program ran from 1943 to 1969.
Biodefense research is now conducted by the United States Army Medical Research Institute of Infectious Diseases (USAMRIID) at Fort Detrick in Maryland.
The Soviet Union’s biological weapons program began in the 1920’s and was know as Biopreparat after 1973. Program was reportedly ended in 1992.
Both the United Kingdom and Japan have developed advanced bioweapon programs. OPH Center for Community Preparedness<br>
slide7. Biological Agent Categories Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide8. CDC Biological Agent Categories Category A
High-priority agents include organisms that pose a risk to national security because they:
Can be easily disseminated or transmitted from person to person;
Result in high mortality rates and have the potential for major public health impact;
Might cause public panic and social disruption; and
Require special action for public health preparedness. Agents
Anthrax (Bacillus anthracis)
Botulism (Clostridium botulinum toxin)
Plague (Yersinia pestis)
Smallpox (variola major)
Tularemia (Francisella tularensis)
Viral hemorrhagic fevers (Ebola, Marburg, Lassa, Machupo) OPH Center for Community Preparedness<br>
slide9. CDC Biological Agent Categories Category B
Second highest priority agents include those that
Are moderately easy to disseminate;
Result in moderate morbidity rates and low mortality rates; and
Require specific enhancements of CDC's diagnostic capacity and enhanced disease surveillance. Agents
Brucellosis (Brucella species)
Epsilon toxin of Clostridium perfringens
Food safety threats (e.g., Salmonella species, Escherichia coli O157:H7, Shigella)
Glanders (Burkholderia mallei)
Melioidosis (Burkholderia pseudomallei)
Psittacosis (Chlamydia psittaci)
Q fever (Coxiella burnetii)
Ricin toxin from Ricinus communis (castor beans)
Staphylococcal enterotoxin B
Typhus fever (Rickettsia prowazekii)
Viral encephalitis (alphaviruses [e.g., Venezuelan equine encephalitis, eastern equine encephalitis, western equine encephalitis])
Water safety threats (e.g., Vibrio cholerae, Cryptosporidium parvum) OPH Center for Community Preparedness<br>
slide10. Category C
Third highest priority agents include emerging pathogens that could be engineered for mass dissemination in the future because of:
Availability;
Ease of production and dissemination; and
Potential for high morbidity and mortality rates and major health impact. Agents
Emerging infectious diseases such as Nipah virus (found in fruit bats). OPH Center for Community Preparedness CDC Biological Agent Categories<br>
slide11. Biological Agents | Characteristics As a bioweapon
Effectiveness
Morbidity and Mortality
Transmission
Environmental
Person-to-person
Ease of Use
Special handling
Production complexity
Accessibility
Commonly available
Few legal controls
Prevention As a disease
Symptoms
Diagnosis
Clinical
Laboratory
Transmission
Environmental
Person-to-person
Treatment
Curative
Supportive OPH Center for Community Preparedness<br>
slide12. The Agents Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide13. Anthrax Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide14. Anthrax | Description Anthrax: An infection caused by the spore-forming bacteria Bacillus anthracis. Also called “wool sorter’s disease.”
Types
Inhalational (rare)
Acquired by inhaling anthrax spores. This is the form most likely caused by a biological attack using aerosolized anthrax spores.
Cutaneous (more common)
Acquired when anthrax bacteria enter a break in the skin.
Gastrointestinal (rare)
Acquired by eating food contaminated with anthrax bacteria. OPH Center for Community Preparedness<br>
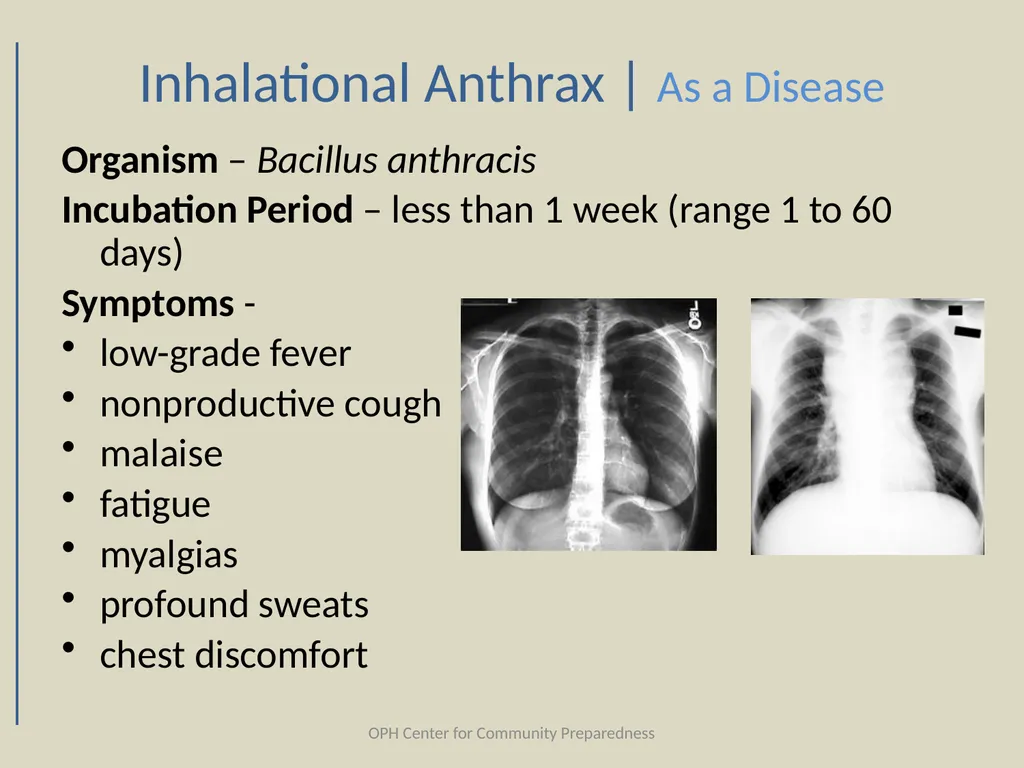
slide15. Inhalational Anthrax | As a Disease Organism – Bacillus anthracis
Incubation Period – less than 1 week (range 1 to 60 days)
Symptoms -
low-grade fever
nonproductive cough
malaise
fatigue
myalgias
profound sweats
chest discomfort OPH Center for Community Preparedness<br>
slide16. Inhalational Anthrax | As a Disease Later Symptoms
1–5 days after onset of initial symptoms .
May be preceded by 1–3 days of improvement.
Abrupt onset of high fever and severe respiratory distress.
Shock, death within 24–36 hours . OPH Center for Community Preparedness<br>
slide17. Inhalational Anthrax | As a Disease Diagnosis
Specific chest X-Ray findings (Ex. widened mediastinum)
Gram-positive bacilli in blood or cerebrospinal fluid.
Aerobic blood culture growth of large, Gram-positive bacilli provides preliminary identification of Bacillus species.
Confirmation by polymerase chain reaction (PCR)
Treatment
Antibiotics (doxycycline, ciprofloxacin)
Survival chances decrease dramatically if not treated within 48 hours of exposure. OPH Center for Community Preparedness<br>
slide18. Effectiveness
In the 20th century, 18 cases of (natural exposure) anthrax in the US had a case-fatality rate of 85%.
In the 2001 anthrax attacks, where the victims received aggressive supportive and antibiotic therapy, the case fatality rate was 45%.
The 2001 anthrax attacks caused widespread panic and fear.
Transmission
No person-to-person transmission.
Spores can survive for decades in the environment.
Weaponized varieties remain suspended in air for substantial periods.
Ease of Use
Multiple distribution methods available. OPH Center for Community Preparedness Inhalational Anthrax | As a Bioweapon<br>
slide19. Accessibility
Occurs naturally in the soil.
Is a common disease in livestock in some parts of the world.
The technology is available on the open market with few controls to purchase.
Prevention
A vaccine is available, but not widely used outside the military.
Detection methods include air-sampling machinery, and indirect methods such as syndromic surveillance and other pattern-recognition methods. These are only useful after an anthrax release has occurred. OPH Center for Community Preparedness Inhalational Anthrax | As a Bioweapon<br>
slide20. Inhalational Anthrax | Public Health Actions Detection
Direct detection of agent
Clinician reports to state health department.
Syndromic detection of illness
Laboratory confirmation
Isolation and quarantine
Not useful for this illness (not person-to-person)
Prophylaxis
Treatment more useful to those not yet exhibiting symptoms.
Delays in treatment greatly increase mortality.
Decontamination
People and clothing can be washed.
Contaminated possessions may need to be incinerated.
Environmental cleaning difficult and expensive. OPH Center for Community Preparedness<br>
slide21. Inhalational Anthrax | Historical Notes Used against Russian forces in Finland in 1916 by Scandinavian freedom fighters (sponsored by Germany).
First extensively developed as a bioweapon by Unit 731 (Japan) in Manchuria in the 1930’s. The USSR later captured the labs used in this project, thus beginning that nation’s bioweapon program.
In 1942 the United Kingdom conducted anthrax bioweapon trials on Gruinard Island in Scotland, making the isle uninhabitable until it was decontaminated in 1990.
Sverdlovsk, Russia – April 2nd 1969, weaponized anthrax spores accidentally released in the city of Sverdlovsk. At least 94 people were infected, and at least 68 died.
In 1990, Iraq deployed two 600 km range missiles loaded with anthrax. OPH Center for Community Preparedness<br>
slide22. Botulism Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide23. Botulism | Description Botulism – a disease caused by the toxin-producing bacteria Clostridium botulinum.
Types
Botulinum Intoxication occurs when a person ingests or inhales a pre-formed toxin that leads to illness within a few hours to days. This toxin is used in the production of biological weapons.
Infant botulism occurs in a small number of susceptible infants each year who harbor C. botulinum in their intestinal tract.
Wound botulism occurs when wounds are infected with C. botulinum that secretes the toxin. OPH Center for Community Preparedness<br>
slide24. Botulism | As a Disease Organism – Clostridium botulinum
Incubation Period – 12 to 36 hours (range 6 hours to 10 days)
Symptoms –
Double vision
Blurred vision
Drooping eyelids
Slurred speech
Dry mouth
Muscle weakness (paralysis) moving down the body
Paralysis of breathing muscles can lead to death OPH Center for Community Preparedness<br>
slide25. Botulism | As a Disease Diagnosis
Based on symptoms
Although this disease resembles Guillain-Barré syndrome, stroke, and myasthenia gravis.
Neurologic tests
Testing for botulinum toxin can be performed at some state health departments and the CDC.
Treatment
Supportive care (such as mechanical breathing assistance).
Antitoxin is available from CDC (at no cost).
Immune globulin for infant botulism is available from California Department of Public Health ($45,300 per dose) OPH Center for Community Preparedness<br>
slide26. Effectiveness
Botulinum toxin is the most poisonous substance known. A single gram of crystalline toxin, evenly dispersed and inhaled, is sufficient to kill more than 1 million people.
Case fatality rate for untreated botulism (toxin) is 60%.
Transmission
Not person-to-person.
Must be ingested or inhaled.
Ease of Use
Distribution accomplished through simple methods.
Direct contamination of food or water.
Spraying of aerosolized toxin. OPH Center for Community Preparedness Botulism | As a Bioweapon<br>
slide27. Accessibility
Bacterium occurs naturally in the soil.
Production methods are relatively unsophisticated for contaminating food and water sources. Aerosolization of the toxin is more difficult.
Prevention
No vaccine available. OPH Center for Community Preparedness Botulism | As a Bioweapon<br>
slide28. Botulism| Public Health Actions Detection
Clinician report to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Not useful for this illness (not person-to-person)
Prophylaxis
Effectively none, although antitoxin might be used in some cases as prophylaxis.
No patient-contact prophylaxis necessary.
Decontamination
Destruction of contaminated food.
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide29. Tested as a bioweapon by Unit 731 (Japan) in Manchuria in the 1930’s. C. botulinum cultures were fed to prisoners.
Aerosolized C. botulinum was dispersed on at least three occasions in Japan by Aum Shinrikyō.
Believing that Nazi Germany had developed weaponized botulinum toxin, the US created 1 million doses of botulinum toxoid vaccine to protect Allied soldiers participating in the invasion of Normandy (June 6th 1944).
By 1991, Iraq had produced 19,000 liters of botulinum toxin, 10,000 liters of which were in weapons. This is approximately three times the amount necessary to kill the entire population of the Earth. OPH Center for Community Preparedness Botulism | Historical Notes<br>
slide30. Plague Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide31. Plague | Description A disease caused by the bacterium Yersinia pestis, which is carried by rodents and their fleas.
Bubonic plague occurs when an infected flea bites a person or when materials contaminated with Y. pestis enter through a break in a person's skin. Patients develop swollen, tender lymph glands (called buboes) and fever, headache, chills, and weakness. Bubonic plague does not spread from person to person. An epidemic in 14th century Europe is known as “the Black Death.”
Pneumonic plague occurs when Y. pestis infects the lungs. This type of plague can spread from person-to-person through the air. Pneumonic plague may also occur if a person with bubonic or septicemic plague is untreated and the bacteria spread to the lungs. This form of the illness will be the most likely result of a biological attack involving Y. pestis.
Septicemic plague occurs when plague bacteria multiply in the blood. It can be a complication of pneumonic or bubonic plague or it can occur by itself. Septicemic plague does not spread from person to person. OPH Center for Community Preparedness<br>
slide32. Pneumonic Plague| As a Disease Organism – Yersinia pestis
Incubation Period – 1 to 6 days
Symptoms –
fever
weakness
rapidly developing pneumonia with
shortness of breath
chest pain
cough
sometimes bloody or watery sputum
Nausea, vomiting, and abdominal pain may also occur.
Without early treatment, pneumonic plague usually leads to respiratory failure, shock, and rapid death. OPH Center for Community Preparedness<br>
slide33. Pneumonic Plague| As a Disease Diagnosis
Lab testing of blood, sputum, or lymph node aspirate.
Treatment
Single patient: streptomycin and gentamycin (intravenous).
Mass casualty: doxycycline and ciprofloxacin. OPH Center for Community Preparedness<br>
slide34. Effectiveness
The mortality rate for untreated pneumonic plague is almost 100%.
Treatment started more than 24 hours after exposure has reduced effectiveness.
Transmission
Person-to-person (mainly respiratory secretions).
Ease of Use
Aerosolized Y. pestis persists in the air for up to 1 hour after release.
High lethality of the agent requires extreme care in handling. OPH Center for Community Preparedness Pneumonic Plague| As a Bioweapon<br>
slide35. Accessibility
Available commercially.
Infects many types of rodents.
Endemic in many areas of the world, including the Southwestern U.S. (prairie dogs).
Prevention
An approved vaccine exists, but is no longer commercially available. OPH Center for Community Preparedness Pneumonic Plague| As a Bioweapon<br>
slide36. Pneumonic Plague | Public Health Actions Detection
Clinician report to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Federally mandated isolation and quarantine disease.
Can be as simple as wearing a proper mask.
May require isolation in a hospital negative pressure room .
Prophylaxis
Antibiotic treatment of close contacts.
Decontamination
Y. pestis is susceptible to sunlight and drying.
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide37. In ancient China and medieval Europe, infected carcasses were used to contaminate enemy water supplies.
Mongol invasion of Caffa - the bodies of plague victims were launched by catapult into the city during the siege.
Plague of Justinian – in the 6th and 7th centuries is the first recorded plague outbreak. It is estimated that one half of Europe's population died.
Black Death – 1348 to 1350. This epidemic killed between 75 million to 100 million people.
After World War II, both the US and USSR developed techniques for weaponizing plague.
In 1994, an outbreak of suspected pneumonic plague occurred in India, resulting in 52 deaths and large internal migrations. OPH Center for Community Preparedness Plague| Historical Notes<br>
slide38. Smallpox Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide39. Smallpox | Description A disease caused by the virus variola major. Smallpox as a naturally occurring disease was eradicated in 1979.
Types
Ordinary: the most frequent type, accounting for 90% or more of cases.
Modified: mild and occurring in previously vaccinated persons.
Flat: rare and very severe. Occurs more often in children. Usually lethal.
Hemorrhagic: rare and very severe. More common in immuno-deficient individuals. Usually lethal. OPH Center for Community Preparedness<br>
slide40. Smallpox| As a Disease Organism – variola major (a virus)
Incubation Period – 7 to 17 days (not contagious)
Symptoms – by phase.
Prodrome: 2 to 4 days duration (possibly contagious)
Fever (101 to 104 °F)
malaise
head and body aches
sometimes vomiting
During this phase, people are generally too sick to carry on daily activities. OPH Center for Community Preparedness<br>
slide41. Smallpox| As a Disease Early rash: 4 days duration (most contagious phase)
Small red spots develop on the tongue and in the mouth, which break open and release the virus
At this time, a rash appears on the body, concentrated on the arms and legs, but spreading everywhere within 24 hours.
By the third day, the spots become raised bumps.
By the fourth day, the bumps fill with a thick, opaque fluid and often have a depression in the center that looks like a bellybutton.
Fever usually returns at this point and remains until the bumps scab over.
Pustular rash: 5 days duration (contagious)
Bumps become pustules (sharply raised, round, and firm to the touch).
Pustule feels as though something like a small ball bearing is embedded in it. OPH Center for Community Preparedness<br>
slide42. Smallpox| As a Disease Pustules and scabs: 5 days duration (contagious)
The pustules begin to form a crust and then scab.
By the end of the second week after the rash appears, most of the sores have scabbed over.
Resolving scabs: ~ 6 days duration (contagious)
Scabs begin to fall off. The resulting marks on the skin will eventually become pitted scars.
Most scabs will have fallen off three weeks after the rash first appeared.
The person is contagious until all of the scabs have fallen off.
Scabs resolved (not contagious) OPH Center for Community Preparedness<br>
slide43. Smallpox| As a Disease Diagnosis
Clinical diagnosis: acute onset of fever >101°F (38.3°C) followed by a rash characterized by firm, deep seated vesicles or pustules in the same stage of development without other apparent cause.
Laboratory confirmation: Polymerase chain reaction (PCR).
Treatment
No proven treatment available, though antivirals may be useful in some cases.
Supportive care.
Vaccination can reduce the severity of disease if given within 2 to 3 days of exposure or decreases the symptoms if given within one week of exposure. OPH Center for Community Preparedness<br>
slide44. Effectiveness
In unvaccinated individuals, smallpox is fatal in 30% of cases.
Causes severe illness (most patients are effectively incapacitated).
Transmission rates are high – in past outbreaks, it is estimated that each infected person infected 10 others.
Transmission
Person-to-person transmission (mainly respiratory secretions).
Large portions of the global population have no immunity.
Ease of Use
Working with smallpox requires highly sophisticated equipment and advanced knowledge. OPH Center for Community Preparedness Smallpox| As a Bioweapon<br>
slide45. Accessibility
Variola major is not naturally occurring. It was wiped out as a natural disease in 1979 after a long-standing global vaccination campaign.
Viral stocks are maintained by only (reportedly) two nations: the United States and the Russian Federation.
Prevention
A vaccine is available, but its use in the general public was discontinued in 1976.
In response to concerns of bioterrorism in the US, a vaccination campaign to immunize medical personnel and first responders was conducted in 2002 - 2003. OPH Center for Community Preparedness Smallpox| As a Bioweapon<br>
slide46. Smallpox| Public Health Actions Detection
Clinician reports to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Federally mandated isolation and quarantine disease.
Severity of illness makes isolation at home impractical.
Prophylaxis
Vaccination soon after exposure reduces severity of illness.
Decontamination
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide47. In the 18th century, smallpox killed approximately 400,000 Europeans.
In 1763, during the French and Indian War, a local trader (and British sympathizer) gave a French-allied Native American tribe (the Delawares) two blankets and a handkerchief from a smallpox hospital.
During World War II, extensive research on the weaponization of smallpox was conducted by the United States, United Kingdom, and Japan.
In 1992, Soviet defector and Biopreparat scientist Ken Alibek revealed that the USSR had stockpiled at least 20 tons of weaponized smallpox, which may have been engineered to reduce the effectiveness of the vaccine. OPH Center for Community Preparedness Smallpox| Historical Notes<br>
slide48. Tularemia Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide49. Tularemia | Description A disease caused by the bacterium Francisella tularensis. Also known as “rabbit fever.”
There are approximately 200 reported cases of tularemia in the US each year.
The bacterium is commonly found in rodents, rabbits, and hares.
Routes of infection include:
Hunters being exposed while handling game carcasses.
Being bitten by an infected tick, deerfly, or other insect.
Consuming contaminated food and water.
Inhaling the bacteria. OPH Center for Community Preparedness<br>
slide50. Tularemia| As a Disease Organism – Francisella tularensis
Incubation Period – 3 to 5 days after exposure (range 1 to 14 days).
Symptoms
Sudden fever
Chills
Headaches
Diarrhea
Muscle aches
Joint pain
Dry cough
Progressive weakness
Pneumonia with chest pain and bloody sputum OPH Center for Community Preparedness<br>
slide51. Tularemia| As a Disease Diagnosis
Symptoms are non-specific.
Laboratory testing: F. tularensis can be identified in certain body fluids by microscopy in properly equipped labs. Growth of the bacterium in culture is considered a confirmed diagnosis.
Treatment
Antibiotics
Single patient: streptomycin and gentamycin (intravenous).
Mass casualty: doxycycline and ciprofloxacin. OPH Center for Community Preparedness<br>
slide52. Effectiveness
F. tularensis is one of the most infectious pathogenic bacteria known.
Fewer than 50 organisms can cause disease. Compare to salmonella species which require 103 to 106 organisms to cause disease.
Transmission
Not person-to-person
F. tularensis can survive in soil and water for several weeks.
Ease of Use
Aerosolization of the bacteria would be the most likely scenario for use as a bioweapon. This would require substantial technical expertise to accomplish. OPH Center for Community Preparedness Tularemia| As a Bioweapon<br>
slide53. Accessibility
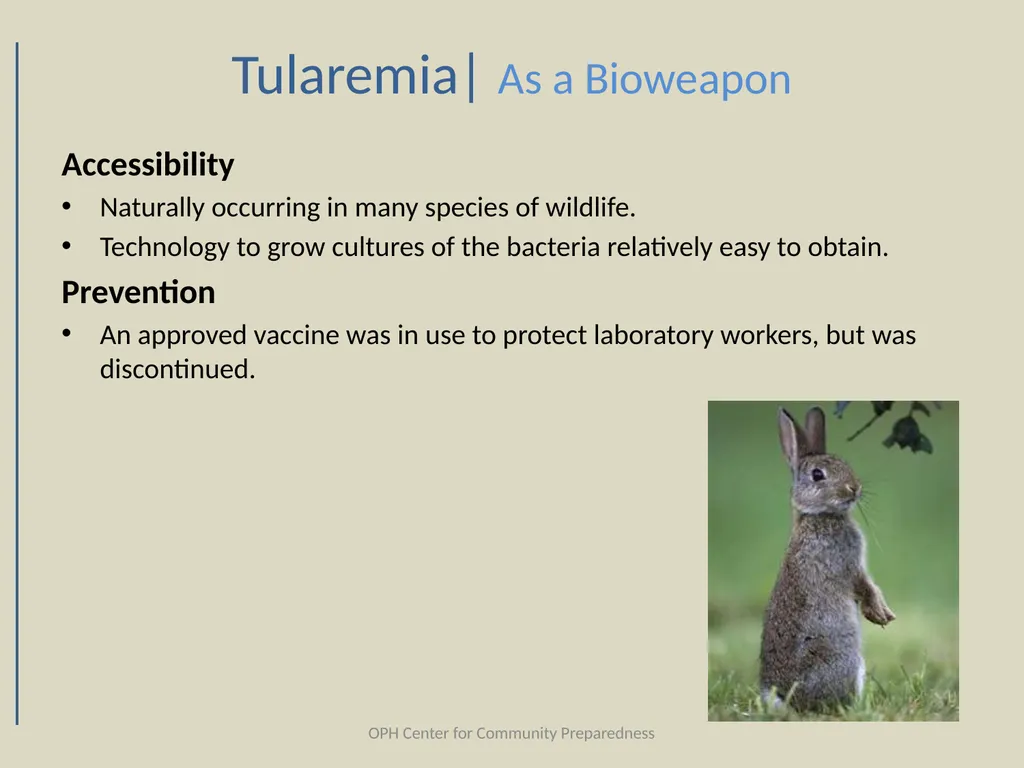
Naturally occurring in many species of wildlife.
Technology to grow cultures of the bacteria relatively easy to obtain.
Prevention
An approved vaccine was in use to protect laboratory workers, but was discontinued. OPH Center for Community Preparedness Tularemia| As a Bioweapon<br>
slide54. Tularemia| Public Health Actions Detection
Clinician reports to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Not useful for this illness (not person-to-person)
Prophylaxis
Antibiotics useful in reducing risk of severe illness in exposed persons.
No patient-contact prophylaxis necessary.
Decontamination
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide55. Named after Tulare County in California.
First isolated in 1912 in a US Public Health Service laboratory.
Researched as a bioweapon by several countries as a more desirable alternative to anthrax.
In the US, development of F. tularensis as a bioweapon was done at the Pine Bluff Arsenal in Arkansas.
In September 2005, six air sampling devices around the Mall in Washington DC detected F. tularensis. This occurred during a well-attended anti-war rally on September 24th 2005. 100,000 to 300,000 people were present. No illnesses were reported and it was declared a natural occurrence. OPH Center for Community Preparedness Tularemia| Historical Notes<br>
slide56. Viral Hemorrhagic Fever Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide57. Viral Hemorrhagic Fevers | Description “Viral hemorrhagic fever“ (VHF) is used to describe a severe syndrome affecting multiple organ systems that is caused by a variety of viruses.
A common symptom of all types is hemorrhage (bleeding).
Some of these diseases are found in rodents and can transmitted to humans:
by insects that have fed on infected rodents.
through contact with the urine, feces, or saliva of infected animals.
through contact with the body fluids of an infected person.
Viral families
Arenaviruses (Laasa fever, Crimean-Congo Hemorrhagic Fever)
Filoviruses (Hantavirus, Rift Valley Fever)
Bunyaviruses (Ebola, Marburg)
Flaviviruses (Omsk Hemorrhagic fever, tick-borne encephalitis) OPH Center for Community Preparedness<br>
slide58. Viral Hemorrhagic Fevers | Examples Laasa Fever
Named after the town in Nigeria where it was first identified.
100,000 to 300,00 cases per year; 5000 deaths per year.
In epidemics, case fatality can reach 50%.
Hantavirus Pulmonary Syndrome
First recognized in 1993 in the southwest US. In that outbreak, half of the patients declined rapidly and died.
Acquired by breathing air contaminated with the feces and urine of infected mice.
Ebola Hemorrhagic Fever
First recognized in 1976; named after a river in the Democratic Republic of Congo.
The reservoir (host) animal for Ebola is unknown. OPH Center for Community Preparedness<br>
slide59. Viral Hemorrhagic Fevers | As a Disease Organism – viruses in the families arenaviridae, filoviridae, bunyaviridae, and flaviviridae.
Incubation Period – varies by organism, but usually one to three weeks.
Symptoms – vary by disease.
General
fever, fatigue, dizziness, muscle aches, loss of strength, and exhaustion.
Severe cases
Bleeding under the skin, in internal organs, or from body orifices like the mouth, eyes, or ears.
Shock, nervous system malfunction, coma, delirium, and seizures. OPH Center for Community Preparedness<br>
slide60. Viral Hemorrhagic Fevers | As a Disease Diagnosis
Early stages of some fevers are non-specific (such as a rash or breathing difficulty).
The most severe forms of the illness are easily recognized, though identification of the specific virus generally requires laboratory analysis.
Treatment
For most diseases in this category, there is no specific treatment, other than supportive care. In many cases, patients will require ventilator support or other advanced forms of care. OPH Center for Community Preparedness<br>
slide61. Effectiveness
Mortality varies by type, but most VHF agents cause severe illness and some diseases are fatal without aggressive medical treatment.
Transmission
Insect bites.
Contact with infected animals.
Contact with body fluids of infected people (person-to-person).
Ease of Use
The highly lethal nature of these agents requires extreme caution when handling.
Distribution of the agent is relatively easy (low tech) for small scale operations (which may be sufficient for causing panic and disruption). OPH Center for Community Preparedness Viral Hemorrhagic Fevers | As a Bioweapon<br>
slide62. Accessibility
Each disease agent is geographically limited, only occurring where the host animals live. For some viruses (Ebola and Marburg) the host animals are unknown.
Laboratory stocks are tightly controlled in bio-safety level 4 containment facilities.
Prevention
With the exception of one disease (Argentine HF), no vaccine is available for viral hemorrhagic fevers.
For naturally occurring disease, the only prevention is avoidance of host animals and insect vector control. OPH Center for Community Preparedness Viral Hemorrhagic Fevers | As a Bioweapon<br>
slide63. Viral Hemorrhagic Fevers | Public Health Actions Detection
Because of the unusual presentation, this syndrome will be rapidly identified.
Isolation and quarantine
Federally mandated isolation and quarantine disease.
The only truly effective method of containment.
Most cases will require hospitalization.
Prophylaxis
None
Decontamination
Standard healthcare sanitization of surfaces and durable equipment .
Standard healthcare sanitization of bedding and clothing.
Incineration of non-reusable equipment. OPH Center for Community Preparedness<br>
slide64. Some researchers claim that the Black Death was actually a VHF and not plague.
No confirmed attempt to weaponize VHF-causing viruses is known.
Some former Soviet scientists have claimed that Biopreparat attempted to engineer other bioweapons to include characteristics of the Ebola virus. OPH Center for Community Preparedness Viral Hemorrhagic Fevers | Historical Notes<br>
slide65. Learning More Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide66. Additional Information The Centers for Disease Control website has extensive information on biological threat agents.
General information
Clinical guidance
Emergency preparedness planning
Links to many other sources of information
CDC Bioterrorism Preparedness
http://emergency.cdc.gov/bioterrorism OPH Center for Community Preparedness<br>
slide67. Other Resources World Health Organization
http://www.who.int/en/
Responder Knowledge Base (FEMA)
http://www.rkb.gov
National Library of Medicine – PubMed
http://www.ncbi.nlm.nih.gov/pubmed/
Louisiana Office of Public Health
http://www.dhh.louisiana.gov/offices/?ID=79 OPH Center for Community Preparedness<br>
slide68. Questions? Category |A| Biological Agents OPH Center for Community Preparedness<br>
Center for Community Preparedness<br>
slide2. Training Objectives Describe the CDC’s Category A biological threat agents.
Describe the public health considerations involved in the release of a biological threat agent.
Discuss the recognition of potential bioterrorism events and the formulation of an appropriate response strategy. OPH Center for Community Preparedness<br>
slide3. Biological Weapons Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide4. Biological Weapons Biological warfare (BW), also known as germ warfare, is the deliberate use of disease-causing biological agents such as protozoa, fungi, bacteria, protists, or viruses, to kill or incapacitate humans, other animals, or plants.
Biological weapons (bioweapons) are living organisms or replicating entities (virus) that reproduce or replicate within their host victims. OPH Center for Community Preparedness<br>
slide5. Biological Weapons | Uses Mass casualties
Morbidity
Mortality
Destruction of resources
Agriculture
Drinking water
Societal disruption
Overwhelm local resources
Breakdown of order
Panic and fear
Economic hardship OPH Center for Community Preparedness<br>
slide6. Biological Weapons | Historical Offensive biological warfare (developing and stockpiling bioweapons) was outlawed in 1972 by the Biological Weapons Convention (BWC). As of 2009, 163 nations had ratified the BWC.
The United States’ biological weapons program ran from 1943 to 1969.
Biodefense research is now conducted by the United States Army Medical Research Institute of Infectious Diseases (USAMRIID) at Fort Detrick in Maryland.
The Soviet Union’s biological weapons program began in the 1920’s and was know as Biopreparat after 1973. Program was reportedly ended in 1992.
Both the United Kingdom and Japan have developed advanced bioweapon programs. OPH Center for Community Preparedness<br>
slide7. Biological Agent Categories Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide8. CDC Biological Agent Categories Category A
High-priority agents include organisms that pose a risk to national security because they:
Can be easily disseminated or transmitted from person to person;
Result in high mortality rates and have the potential for major public health impact;
Might cause public panic and social disruption; and
Require special action for public health preparedness. Agents
Anthrax (Bacillus anthracis)
Botulism (Clostridium botulinum toxin)
Plague (Yersinia pestis)
Smallpox (variola major)
Tularemia (Francisella tularensis)
Viral hemorrhagic fevers (Ebola, Marburg, Lassa, Machupo) OPH Center for Community Preparedness<br>
slide9. CDC Biological Agent Categories Category B
Second highest priority agents include those that
Are moderately easy to disseminate;
Result in moderate morbidity rates and low mortality rates; and
Require specific enhancements of CDC's diagnostic capacity and enhanced disease surveillance. Agents
Brucellosis (Brucella species)
Epsilon toxin of Clostridium perfringens
Food safety threats (e.g., Salmonella species, Escherichia coli O157:H7, Shigella)
Glanders (Burkholderia mallei)
Melioidosis (Burkholderia pseudomallei)
Psittacosis (Chlamydia psittaci)
Q fever (Coxiella burnetii)
Ricin toxin from Ricinus communis (castor beans)
Staphylococcal enterotoxin B
Typhus fever (Rickettsia prowazekii)
Viral encephalitis (alphaviruses [e.g., Venezuelan equine encephalitis, eastern equine encephalitis, western equine encephalitis])
Water safety threats (e.g., Vibrio cholerae, Cryptosporidium parvum) OPH Center for Community Preparedness<br>
slide10. Category C
Third highest priority agents include emerging pathogens that could be engineered for mass dissemination in the future because of:
Availability;
Ease of production and dissemination; and
Potential for high morbidity and mortality rates and major health impact. Agents
Emerging infectious diseases such as Nipah virus (found in fruit bats). OPH Center for Community Preparedness CDC Biological Agent Categories<br>
slide11. Biological Agents | Characteristics As a bioweapon
Effectiveness
Morbidity and Mortality
Transmission
Environmental
Person-to-person
Ease of Use
Special handling
Production complexity
Accessibility
Commonly available
Few legal controls
Prevention As a disease
Symptoms
Diagnosis
Clinical
Laboratory
Transmission
Environmental
Person-to-person
Treatment
Curative
Supportive OPH Center for Community Preparedness<br>
slide12. The Agents Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide13. Anthrax Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide14. Anthrax | Description Anthrax: An infection caused by the spore-forming bacteria Bacillus anthracis. Also called “wool sorter’s disease.”
Types
Inhalational (rare)
Acquired by inhaling anthrax spores. This is the form most likely caused by a biological attack using aerosolized anthrax spores.
Cutaneous (more common)
Acquired when anthrax bacteria enter a break in the skin.
Gastrointestinal (rare)
Acquired by eating food contaminated with anthrax bacteria. OPH Center for Community Preparedness<br>
slide15. Inhalational Anthrax | As a Disease Organism – Bacillus anthracis
Incubation Period – less than 1 week (range 1 to 60 days)
Symptoms -
low-grade fever
nonproductive cough
malaise
fatigue
myalgias
profound sweats
chest discomfort OPH Center for Community Preparedness<br>
slide16. Inhalational Anthrax | As a Disease Later Symptoms
1–5 days after onset of initial symptoms .
May be preceded by 1–3 days of improvement.
Abrupt onset of high fever and severe respiratory distress.
Shock, death within 24–36 hours . OPH Center for Community Preparedness<br>
slide17. Inhalational Anthrax | As a Disease Diagnosis
Specific chest X-Ray findings (Ex. widened mediastinum)
Gram-positive bacilli in blood or cerebrospinal fluid.
Aerobic blood culture growth of large, Gram-positive bacilli provides preliminary identification of Bacillus species.
Confirmation by polymerase chain reaction (PCR)
Treatment
Antibiotics (doxycycline, ciprofloxacin)
Survival chances decrease dramatically if not treated within 48 hours of exposure. OPH Center for Community Preparedness<br>
slide18. Effectiveness
In the 20th century, 18 cases of (natural exposure) anthrax in the US had a case-fatality rate of 85%.
In the 2001 anthrax attacks, where the victims received aggressive supportive and antibiotic therapy, the case fatality rate was 45%.
The 2001 anthrax attacks caused widespread panic and fear.
Transmission
No person-to-person transmission.
Spores can survive for decades in the environment.
Weaponized varieties remain suspended in air for substantial periods.
Ease of Use
Multiple distribution methods available. OPH Center for Community Preparedness Inhalational Anthrax | As a Bioweapon<br>
slide19. Accessibility
Occurs naturally in the soil.
Is a common disease in livestock in some parts of the world.
The technology is available on the open market with few controls to purchase.
Prevention
A vaccine is available, but not widely used outside the military.
Detection methods include air-sampling machinery, and indirect methods such as syndromic surveillance and other pattern-recognition methods. These are only useful after an anthrax release has occurred. OPH Center for Community Preparedness Inhalational Anthrax | As a Bioweapon<br>
slide20. Inhalational Anthrax | Public Health Actions Detection
Direct detection of agent
Clinician reports to state health department.
Syndromic detection of illness
Laboratory confirmation
Isolation and quarantine
Not useful for this illness (not person-to-person)
Prophylaxis
Treatment more useful to those not yet exhibiting symptoms.
Delays in treatment greatly increase mortality.
Decontamination
People and clothing can be washed.
Contaminated possessions may need to be incinerated.
Environmental cleaning difficult and expensive. OPH Center for Community Preparedness<br>
slide21. Inhalational Anthrax | Historical Notes Used against Russian forces in Finland in 1916 by Scandinavian freedom fighters (sponsored by Germany).
First extensively developed as a bioweapon by Unit 731 (Japan) in Manchuria in the 1930’s. The USSR later captured the labs used in this project, thus beginning that nation’s bioweapon program.
In 1942 the United Kingdom conducted anthrax bioweapon trials on Gruinard Island in Scotland, making the isle uninhabitable until it was decontaminated in 1990.
Sverdlovsk, Russia – April 2nd 1969, weaponized anthrax spores accidentally released in the city of Sverdlovsk. At least 94 people were infected, and at least 68 died.
In 1990, Iraq deployed two 600 km range missiles loaded with anthrax. OPH Center for Community Preparedness<br>
slide22. Botulism Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide23. Botulism | Description Botulism – a disease caused by the toxin-producing bacteria Clostridium botulinum.
Types
Botulinum Intoxication occurs when a person ingests or inhales a pre-formed toxin that leads to illness within a few hours to days. This toxin is used in the production of biological weapons.
Infant botulism occurs in a small number of susceptible infants each year who harbor C. botulinum in their intestinal tract.
Wound botulism occurs when wounds are infected with C. botulinum that secretes the toxin. OPH Center for Community Preparedness<br>
slide24. Botulism | As a Disease Organism – Clostridium botulinum
Incubation Period – 12 to 36 hours (range 6 hours to 10 days)
Symptoms –
Double vision
Blurred vision
Drooping eyelids
Slurred speech
Dry mouth
Muscle weakness (paralysis) moving down the body
Paralysis of breathing muscles can lead to death OPH Center for Community Preparedness<br>
slide25. Botulism | As a Disease Diagnosis
Based on symptoms
Although this disease resembles Guillain-Barré syndrome, stroke, and myasthenia gravis.
Neurologic tests
Testing for botulinum toxin can be performed at some state health departments and the CDC.
Treatment
Supportive care (such as mechanical breathing assistance).
Antitoxin is available from CDC (at no cost).
Immune globulin for infant botulism is available from California Department of Public Health ($45,300 per dose) OPH Center for Community Preparedness<br>
slide26. Effectiveness
Botulinum toxin is the most poisonous substance known. A single gram of crystalline toxin, evenly dispersed and inhaled, is sufficient to kill more than 1 million people.
Case fatality rate for untreated botulism (toxin) is 60%.
Transmission
Not person-to-person.
Must be ingested or inhaled.
Ease of Use
Distribution accomplished through simple methods.
Direct contamination of food or water.
Spraying of aerosolized toxin. OPH Center for Community Preparedness Botulism | As a Bioweapon<br>
slide27. Accessibility
Bacterium occurs naturally in the soil.
Production methods are relatively unsophisticated for contaminating food and water sources. Aerosolization of the toxin is more difficult.
Prevention
No vaccine available. OPH Center for Community Preparedness Botulism | As a Bioweapon<br>
slide28. Botulism| Public Health Actions Detection
Clinician report to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Not useful for this illness (not person-to-person)
Prophylaxis
Effectively none, although antitoxin might be used in some cases as prophylaxis.
No patient-contact prophylaxis necessary.
Decontamination
Destruction of contaminated food.
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide29. Tested as a bioweapon by Unit 731 (Japan) in Manchuria in the 1930’s. C. botulinum cultures were fed to prisoners.
Aerosolized C. botulinum was dispersed on at least three occasions in Japan by Aum Shinrikyō.
Believing that Nazi Germany had developed weaponized botulinum toxin, the US created 1 million doses of botulinum toxoid vaccine to protect Allied soldiers participating in the invasion of Normandy (June 6th 1944).
By 1991, Iraq had produced 19,000 liters of botulinum toxin, 10,000 liters of which were in weapons. This is approximately three times the amount necessary to kill the entire population of the Earth. OPH Center for Community Preparedness Botulism | Historical Notes<br>
slide30. Plague Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide31. Plague | Description A disease caused by the bacterium Yersinia pestis, which is carried by rodents and their fleas.
Bubonic plague occurs when an infected flea bites a person or when materials contaminated with Y. pestis enter through a break in a person's skin. Patients develop swollen, tender lymph glands (called buboes) and fever, headache, chills, and weakness. Bubonic plague does not spread from person to person. An epidemic in 14th century Europe is known as “the Black Death.”
Pneumonic plague occurs when Y. pestis infects the lungs. This type of plague can spread from person-to-person through the air. Pneumonic plague may also occur if a person with bubonic or septicemic plague is untreated and the bacteria spread to the lungs. This form of the illness will be the most likely result of a biological attack involving Y. pestis.
Septicemic plague occurs when plague bacteria multiply in the blood. It can be a complication of pneumonic or bubonic plague or it can occur by itself. Septicemic plague does not spread from person to person. OPH Center for Community Preparedness<br>
slide32. Pneumonic Plague| As a Disease Organism – Yersinia pestis
Incubation Period – 1 to 6 days
Symptoms –
fever
weakness
rapidly developing pneumonia with
shortness of breath
chest pain
cough
sometimes bloody or watery sputum
Nausea, vomiting, and abdominal pain may also occur.
Without early treatment, pneumonic plague usually leads to respiratory failure, shock, and rapid death. OPH Center for Community Preparedness<br>
slide33. Pneumonic Plague| As a Disease Diagnosis
Lab testing of blood, sputum, or lymph node aspirate.
Treatment
Single patient: streptomycin and gentamycin (intravenous).
Mass casualty: doxycycline and ciprofloxacin. OPH Center for Community Preparedness<br>
slide34. Effectiveness
The mortality rate for untreated pneumonic plague is almost 100%.
Treatment started more than 24 hours after exposure has reduced effectiveness.
Transmission
Person-to-person (mainly respiratory secretions).
Ease of Use
Aerosolized Y. pestis persists in the air for up to 1 hour after release.
High lethality of the agent requires extreme care in handling. OPH Center for Community Preparedness Pneumonic Plague| As a Bioweapon<br>
slide35. Accessibility
Available commercially.
Infects many types of rodents.
Endemic in many areas of the world, including the Southwestern U.S. (prairie dogs).
Prevention
An approved vaccine exists, but is no longer commercially available. OPH Center for Community Preparedness Pneumonic Plague| As a Bioweapon<br>
slide36. Pneumonic Plague | Public Health Actions Detection
Clinician report to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Federally mandated isolation and quarantine disease.
Can be as simple as wearing a proper mask.
May require isolation in a hospital negative pressure room .
Prophylaxis
Antibiotic treatment of close contacts.
Decontamination
Y. pestis is susceptible to sunlight and drying.
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide37. In ancient China and medieval Europe, infected carcasses were used to contaminate enemy water supplies.
Mongol invasion of Caffa - the bodies of plague victims were launched by catapult into the city during the siege.
Plague of Justinian – in the 6th and 7th centuries is the first recorded plague outbreak. It is estimated that one half of Europe's population died.
Black Death – 1348 to 1350. This epidemic killed between 75 million to 100 million people.
After World War II, both the US and USSR developed techniques for weaponizing plague.
In 1994, an outbreak of suspected pneumonic plague occurred in India, resulting in 52 deaths and large internal migrations. OPH Center for Community Preparedness Plague| Historical Notes<br>
slide38. Smallpox Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide39. Smallpox | Description A disease caused by the virus variola major. Smallpox as a naturally occurring disease was eradicated in 1979.
Types
Ordinary: the most frequent type, accounting for 90% or more of cases.
Modified: mild and occurring in previously vaccinated persons.
Flat: rare and very severe. Occurs more often in children. Usually lethal.
Hemorrhagic: rare and very severe. More common in immuno-deficient individuals. Usually lethal. OPH Center for Community Preparedness<br>
slide40. Smallpox| As a Disease Organism – variola major (a virus)
Incubation Period – 7 to 17 days (not contagious)
Symptoms – by phase.
Prodrome: 2 to 4 days duration (possibly contagious)
Fever (101 to 104 °F)
malaise
head and body aches
sometimes vomiting
During this phase, people are generally too sick to carry on daily activities. OPH Center for Community Preparedness<br>
slide41. Smallpox| As a Disease Early rash: 4 days duration (most contagious phase)
Small red spots develop on the tongue and in the mouth, which break open and release the virus
At this time, a rash appears on the body, concentrated on the arms and legs, but spreading everywhere within 24 hours.
By the third day, the spots become raised bumps.
By the fourth day, the bumps fill with a thick, opaque fluid and often have a depression in the center that looks like a bellybutton.
Fever usually returns at this point and remains until the bumps scab over.
Pustular rash: 5 days duration (contagious)
Bumps become pustules (sharply raised, round, and firm to the touch).
Pustule feels as though something like a small ball bearing is embedded in it. OPH Center for Community Preparedness<br>
slide42. Smallpox| As a Disease Pustules and scabs: 5 days duration (contagious)
The pustules begin to form a crust and then scab.
By the end of the second week after the rash appears, most of the sores have scabbed over.
Resolving scabs: ~ 6 days duration (contagious)
Scabs begin to fall off. The resulting marks on the skin will eventually become pitted scars.
Most scabs will have fallen off three weeks after the rash first appeared.
The person is contagious until all of the scabs have fallen off.
Scabs resolved (not contagious) OPH Center for Community Preparedness<br>
slide43. Smallpox| As a Disease Diagnosis
Clinical diagnosis: acute onset of fever >101°F (38.3°C) followed by a rash characterized by firm, deep seated vesicles or pustules in the same stage of development without other apparent cause.
Laboratory confirmation: Polymerase chain reaction (PCR).
Treatment
No proven treatment available, though antivirals may be useful in some cases.
Supportive care.
Vaccination can reduce the severity of disease if given within 2 to 3 days of exposure or decreases the symptoms if given within one week of exposure. OPH Center for Community Preparedness<br>
slide44. Effectiveness
In unvaccinated individuals, smallpox is fatal in 30% of cases.
Causes severe illness (most patients are effectively incapacitated).
Transmission rates are high – in past outbreaks, it is estimated that each infected person infected 10 others.
Transmission
Person-to-person transmission (mainly respiratory secretions).
Large portions of the global population have no immunity.
Ease of Use
Working with smallpox requires highly sophisticated equipment and advanced knowledge. OPH Center for Community Preparedness Smallpox| As a Bioweapon<br>
slide45. Accessibility
Variola major is not naturally occurring. It was wiped out as a natural disease in 1979 after a long-standing global vaccination campaign.
Viral stocks are maintained by only (reportedly) two nations: the United States and the Russian Federation.
Prevention
A vaccine is available, but its use in the general public was discontinued in 1976.
In response to concerns of bioterrorism in the US, a vaccination campaign to immunize medical personnel and first responders was conducted in 2002 - 2003. OPH Center for Community Preparedness Smallpox| As a Bioweapon<br>
slide46. Smallpox| Public Health Actions Detection
Clinician reports to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Federally mandated isolation and quarantine disease.
Severity of illness makes isolation at home impractical.
Prophylaxis
Vaccination soon after exposure reduces severity of illness.
Decontamination
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide47. In the 18th century, smallpox killed approximately 400,000 Europeans.
In 1763, during the French and Indian War, a local trader (and British sympathizer) gave a French-allied Native American tribe (the Delawares) two blankets and a handkerchief from a smallpox hospital.
During World War II, extensive research on the weaponization of smallpox was conducted by the United States, United Kingdom, and Japan.
In 1992, Soviet defector and Biopreparat scientist Ken Alibek revealed that the USSR had stockpiled at least 20 tons of weaponized smallpox, which may have been engineered to reduce the effectiveness of the vaccine. OPH Center for Community Preparedness Smallpox| Historical Notes<br>
slide48. Tularemia Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide49. Tularemia | Description A disease caused by the bacterium Francisella tularensis. Also known as “rabbit fever.”
There are approximately 200 reported cases of tularemia in the US each year.
The bacterium is commonly found in rodents, rabbits, and hares.
Routes of infection include:
Hunters being exposed while handling game carcasses.
Being bitten by an infected tick, deerfly, or other insect.
Consuming contaminated food and water.
Inhaling the bacteria. OPH Center for Community Preparedness<br>
slide50. Tularemia| As a Disease Organism – Francisella tularensis
Incubation Period – 3 to 5 days after exposure (range 1 to 14 days).
Symptoms
Sudden fever
Chills
Headaches
Diarrhea
Muscle aches
Joint pain
Dry cough
Progressive weakness
Pneumonia with chest pain and bloody sputum OPH Center for Community Preparedness<br>
slide51. Tularemia| As a Disease Diagnosis
Symptoms are non-specific.
Laboratory testing: F. tularensis can be identified in certain body fluids by microscopy in properly equipped labs. Growth of the bacterium in culture is considered a confirmed diagnosis.
Treatment
Antibiotics
Single patient: streptomycin and gentamycin (intravenous).
Mass casualty: doxycycline and ciprofloxacin. OPH Center for Community Preparedness<br>
slide52. Effectiveness
F. tularensis is one of the most infectious pathogenic bacteria known.
Fewer than 50 organisms can cause disease. Compare to salmonella species which require 103 to 106 organisms to cause disease.
Transmission
Not person-to-person
F. tularensis can survive in soil and water for several weeks.
Ease of Use
Aerosolization of the bacteria would be the most likely scenario for use as a bioweapon. This would require substantial technical expertise to accomplish. OPH Center for Community Preparedness Tularemia| As a Bioweapon<br>
slide53. Accessibility
Naturally occurring in many species of wildlife.
Technology to grow cultures of the bacteria relatively easy to obtain.
Prevention
An approved vaccine was in use to protect laboratory workers, but was discontinued. OPH Center for Community Preparedness Tularemia| As a Bioweapon<br>
slide54. Tularemia| Public Health Actions Detection
Clinician reports to state health department.
Syndromic detection of illness.
Laboratory confirmation.
Isolation and quarantine
Not useful for this illness (not person-to-person)
Prophylaxis
Antibiotics useful in reducing risk of severe illness in exposed persons.
No patient-contact prophylaxis necessary.
Decontamination
Standard healthcare sanitization of surfaces and durable equipment.
Standard healthcare sanitization of bedding and clothing. OPH Center for Community Preparedness<br>
slide55. Named after Tulare County in California.
First isolated in 1912 in a US Public Health Service laboratory.
Researched as a bioweapon by several countries as a more desirable alternative to anthrax.
In the US, development of F. tularensis as a bioweapon was done at the Pine Bluff Arsenal in Arkansas.
In September 2005, six air sampling devices around the Mall in Washington DC detected F. tularensis. This occurred during a well-attended anti-war rally on September 24th 2005. 100,000 to 300,000 people were present. No illnesses were reported and it was declared a natural occurrence. OPH Center for Community Preparedness Tularemia| Historical Notes<br>
slide56. Viral Hemorrhagic Fever Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide57. Viral Hemorrhagic Fevers | Description “Viral hemorrhagic fever“ (VHF) is used to describe a severe syndrome affecting multiple organ systems that is caused by a variety of viruses.
A common symptom of all types is hemorrhage (bleeding).
Some of these diseases are found in rodents and can transmitted to humans:
by insects that have fed on infected rodents.
through contact with the urine, feces, or saliva of infected animals.
through contact with the body fluids of an infected person.
Viral families
Arenaviruses (Laasa fever, Crimean-Congo Hemorrhagic Fever)
Filoviruses (Hantavirus, Rift Valley Fever)
Bunyaviruses (Ebola, Marburg)
Flaviviruses (Omsk Hemorrhagic fever, tick-borne encephalitis) OPH Center for Community Preparedness<br>
slide58. Viral Hemorrhagic Fevers | Examples Laasa Fever
Named after the town in Nigeria where it was first identified.
100,000 to 300,00 cases per year; 5000 deaths per year.
In epidemics, case fatality can reach 50%.
Hantavirus Pulmonary Syndrome
First recognized in 1993 in the southwest US. In that outbreak, half of the patients declined rapidly and died.
Acquired by breathing air contaminated with the feces and urine of infected mice.
Ebola Hemorrhagic Fever
First recognized in 1976; named after a river in the Democratic Republic of Congo.
The reservoir (host) animal for Ebola is unknown. OPH Center for Community Preparedness<br>
slide59. Viral Hemorrhagic Fevers | As a Disease Organism – viruses in the families arenaviridae, filoviridae, bunyaviridae, and flaviviridae.
Incubation Period – varies by organism, but usually one to three weeks.
Symptoms – vary by disease.
General
fever, fatigue, dizziness, muscle aches, loss of strength, and exhaustion.
Severe cases
Bleeding under the skin, in internal organs, or from body orifices like the mouth, eyes, or ears.
Shock, nervous system malfunction, coma, delirium, and seizures. OPH Center for Community Preparedness<br>
slide60. Viral Hemorrhagic Fevers | As a Disease Diagnosis
Early stages of some fevers are non-specific (such as a rash or breathing difficulty).
The most severe forms of the illness are easily recognized, though identification of the specific virus generally requires laboratory analysis.
Treatment
For most diseases in this category, there is no specific treatment, other than supportive care. In many cases, patients will require ventilator support or other advanced forms of care. OPH Center for Community Preparedness<br>
slide61. Effectiveness
Mortality varies by type, but most VHF agents cause severe illness and some diseases are fatal without aggressive medical treatment.
Transmission
Insect bites.
Contact with infected animals.
Contact with body fluids of infected people (person-to-person).
Ease of Use
The highly lethal nature of these agents requires extreme caution when handling.
Distribution of the agent is relatively easy (low tech) for small scale operations (which may be sufficient for causing panic and disruption). OPH Center for Community Preparedness Viral Hemorrhagic Fevers | As a Bioweapon<br>
slide62. Accessibility
Each disease agent is geographically limited, only occurring where the host animals live. For some viruses (Ebola and Marburg) the host animals are unknown.
Laboratory stocks are tightly controlled in bio-safety level 4 containment facilities.
Prevention
With the exception of one disease (Argentine HF), no vaccine is available for viral hemorrhagic fevers.
For naturally occurring disease, the only prevention is avoidance of host animals and insect vector control. OPH Center for Community Preparedness Viral Hemorrhagic Fevers | As a Bioweapon<br>
slide63. Viral Hemorrhagic Fevers | Public Health Actions Detection
Because of the unusual presentation, this syndrome will be rapidly identified.
Isolation and quarantine
Federally mandated isolation and quarantine disease.
The only truly effective method of containment.
Most cases will require hospitalization.
Prophylaxis
None
Decontamination
Standard healthcare sanitization of surfaces and durable equipment .
Standard healthcare sanitization of bedding and clothing.
Incineration of non-reusable equipment. OPH Center for Community Preparedness<br>
slide64. Some researchers claim that the Black Death was actually a VHF and not plague.
No confirmed attempt to weaponize VHF-causing viruses is known.
Some former Soviet scientists have claimed that Biopreparat attempted to engineer other bioweapons to include characteristics of the Ebola virus. OPH Center for Community Preparedness Viral Hemorrhagic Fevers | Historical Notes<br>
slide65. Learning More Category |A| Biological Agents OPH Center for Community Preparedness<br>
slide66. Additional Information The Centers for Disease Control website has extensive information on biological threat agents.
General information
Clinical guidance
Emergency preparedness planning
Links to many other sources of information
CDC Bioterrorism Preparedness
http://emergency.cdc.gov/bioterrorism OPH Center for Community Preparedness<br>
slide67. Other Resources World Health Organization
http://www.who.int/en/
Responder Knowledge Base (FEMA)
http://www.rkb.gov
National Library of Medicine – PubMed
http://www.ncbi.nlm.nih.gov/pubmed/
Louisiana Office of Public Health
http://www.dhh.louisiana.gov/offices/?ID=79 OPH Center for Community Preparedness<br>
slide68. Questions? Category |A| Biological Agents OPH Center for Community Preparedness<br>