
CYTOMEGALOVIRUS Largest virus in herpes viridae












Description: CYTOMEGALOVIRUS Largest virus in herpes viridae family. Named because it causes massive enlargement of infected host cells. CYTOMEGALOVIRUS Properties of CMV are similar to any other herpesvirus described earlier with some minor
Related Topics
Download Presentation
"CYTOMEGALOVIRUS Largest virus in herpes viridae" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. CYTOMEGALOVIRUS Largest virus in herpes viridae family.
Named because it causes massive enlargement of infected host cells.<br>
slide2. CYTOMEGALOVIRUS Properties of CMV are similar to any other herpesvirus described earlier with some minor differences.
CMV belongs to β-subfamily
dsDNA is the largest among herpesviruses.
Cytomegaloviruses are strictly species-specific.
Cell type specificity-
In vivo, CMV infects kidney and salivary glands; where it undergoes latency.
In vitro, CMV replicates only in human fibroblast cell line &produces a characteristic cytopathic effect (CPE) described as Owl’s eye appearance
Cell–to-cell spread<br>
slide3. Clinical Manifestations CMV causes an array of clinical syndromes:
Congenital
Perinatal infections
Infections in immunocompetent
Infection in immunocompromised & transplant recipients<br>
slide4. Congenital CMV Infection Most common intrauterine infection associated with congenital defects.
About 1% of infants born are infected with CMV.
Cytomegalic inclusion disease develops in about 5% of the infected fetus.
5–25% of them may develop significant psychomotor, hearing, ocular, or dental defects within 2 years.<br>
slide5. Clinical Manifestations Congenital defects include-
Most common defects arepetechiae, hepatosplenomegaly, and jaundice (60–80% of cases).
Less common defects include-microcephaly, cerebral calcifications, intrauterine growth retardation, and prematurity (30–50% of cases).
Risk is maximum if the infection occurs in early pregnancy and if the mother is primarily infected during pregnancy (one third of the primarily infected mothers transmit the virus to fetus in contrast to 1% of reactivated mothers)<br>
slide6. Perinatal CMV Infection- Transmission to the new-born occurs either during
delivery-through infected birth canal or
post natal- through infected breast milk / secretions from mother.
Mostly asymptomatic, but shed virus in urine from 8-12 weeks of age, up to several years.
Few infants, especially premature babies develop interstitial pneumonitis.<br>
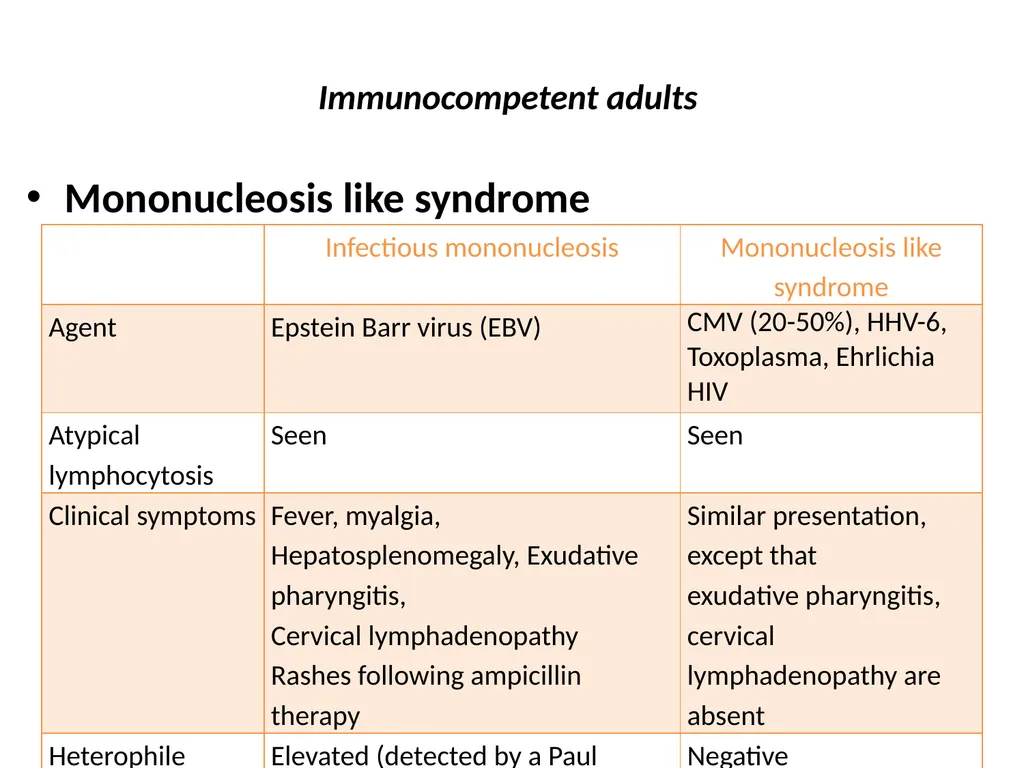
slide7. Immunocompetent adults Mononucleosis like syndrome<br>
slide8. immunocompromised host (most of which are due to reactivation) In untreated AIDS patients (CD4 count <50/µL) - CMV may cause chorioretinitis, gastroenteritis, dementia and other disseminated CMV infection.
Organ transplant recipients- Most common viral infection (1 to 4 months post transplantation)
Bilateral interstitial pneumonia is the most common form seen in 15-20% of bone marrow transplant recipients;
Febrile leukopenia is seen among solid organ transplants recipients
Obliterative bronchiolitis in lung transplants
Graft atherosclerosis in heart transplants
Rejection of renal allografts<br>
slide9. Epidemiology Transmission-
Oral and respiratory spread is the predominant mode
Transplacental route ( transmission from mother to fetus)
Blood transfusion- Risk of transmission is about 0.1-10% per blood unit transfused
Organ transplantation
Sexual contact ( in young adults)<br>
slide10. Epidemiology Reservoir- Humans are the only known host for CMV.
Source- Virus may be shed in urine, saliva, semen, breast milk, and cervical secretions, and is carried in circulating white blood cells
CMV is endemic worldwide, present throughout the year without any seasonal variation.
Risk factors such as low socioeconomic status and poor personal hygiene facilitate the infection.
Prevalence is high in under developed nations with 90% of people being seropositive in contrast to 40–70% seropositivity in developed nations.<br>
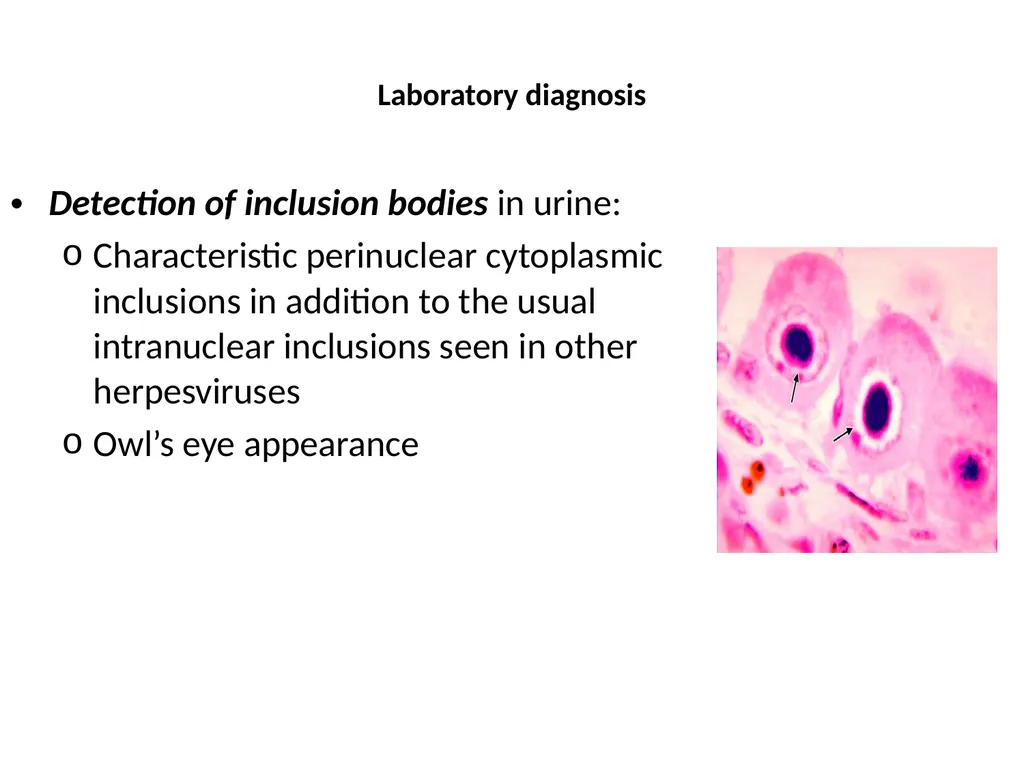
slide11. Laboratory diagnosis Detection of inclusion bodies in urine:
Characteristic perinuclear cytoplasmic inclusions in addition to the usual intranuclear inclusions seen in other herpesviruses
Owl’s eye appearance<br>
slide12. Laboratory diagnosis (cont..) Virus Isolation- From throat washings and urine.
Human fibroblasts are the most ideal cell lines.
Cytopathic effect-After2–3 weeks of incubation, the following CPE may be observed-
Typical CMV inclusions,
Multinucleated giant cells are seen.
Enlargement of infected host cells<br>
slide13. Laboratory diagnosis (cont..) Shell vial technique - very useful in CMV mononucleosis where viral load is low and CPE takes several weeks to appear.<br>
slide14. Antibody Detection ELISA has been available for detecting serum antibodies against various antigens such as:
Matrix phosphoproteins pp150 and pp65
Glycoproteins gB and gH
Major DNA binding protein (pp52)<br>
slide15. Antibody Detection (cont..) CMV IgM antibodies appear in 1–2 weeks after infection and indicates recent or on-going infection.
Drops to below detectable levels within several months after infection.
IgM detection in pregnancy indicates congenital infection, thus guiding initiation of appropriate treatment<br>
slide16. Antibody Detection (cont..) CMV IgG antibodies are produced few days after IgM and persist life-long.
Indicates either a recent or past infection; which can be differentiated by performing IgG avidity test.
Low IgG avidity indicates recent infection (<3 weeks).
IgG avidity test is also useful in diagnosing congenital infection
Antibody detection cannot distinguish strain differences among the clinical isolates.<br>
slide17. Antigen Detection CMV-specific pp65 antigen (a major matrix phosphoprotein) can be detected in peripheral-blood leukocytes by indirect immunofluorescence test using specific monoclonal antibody.
Test has been in use since long; but is less preferred as it is time-consuming and technically demanding.<br>
slide18. Molecular Methods PCR - To detect specific CMV DNA in blood or body fluids such as CSF.
Various genes targeted are glycoprotein B (UL55), DNA polymerase (UL54) and pp65 (UL83)
PCR assays are rapid, highly sensitive, specific and have replaced the gold standard culture technique in most laboratories
Real time PCR can quantitate the viral load, hence, it is the method of choice to monitor the treatment response.<br>
slide19. Treatment CMV does not respond to acyclovir.
The following drugs are used for treatment of CMV infections.
Ganciclovir
Valganciclovir
Foscarnet
Cidofovir
CMV immunoglobulin<br>
slide20. Treatment Antiviral resistance can occur rarely due to mutations in target genes.
For example, UL97 mutation confers resistance to ganciclovir, while UL54 mutation leads to resistance to ganciclovir, cidofovir, and foscarnet)<br>
slide21. Prophylaxis Both ganciclovir and valgancyclovir have been used successfully for prophylaxis and preemptive therapy in transplant recipients.
CMV immunoglobulin has shown to be effective in preventing congenital infection when given to mother during pregnancy<br>
slide22. REFRENCES Text Book Of Medical Microbiology by Ananth
Narayan Paniker
Text Book Of Medical Microbiology by D R Arora
Text Book Of Medical Microbiology by A S Sastry
Text Book Of Medical Microbiology by Baweja
Text Book Of Medical Microbiology by Satish Gupte<br>
Named because it causes massive enlargement of infected host cells.<br>
slide2. CYTOMEGALOVIRUS Properties of CMV are similar to any other herpesvirus described earlier with some minor differences.
CMV belongs to β-subfamily
dsDNA is the largest among herpesviruses.
Cytomegaloviruses are strictly species-specific.
Cell type specificity-
In vivo, CMV infects kidney and salivary glands; where it undergoes latency.
In vitro, CMV replicates only in human fibroblast cell line &produces a characteristic cytopathic effect (CPE) described as Owl’s eye appearance
Cell–to-cell spread<br>
slide3. Clinical Manifestations CMV causes an array of clinical syndromes:
Congenital
Perinatal infections
Infections in immunocompetent
Infection in immunocompromised & transplant recipients<br>
slide4. Congenital CMV Infection Most common intrauterine infection associated with congenital defects.
About 1% of infants born are infected with CMV.
Cytomegalic inclusion disease develops in about 5% of the infected fetus.
5–25% of them may develop significant psychomotor, hearing, ocular, or dental defects within 2 years.<br>
slide5. Clinical Manifestations Congenital defects include-
Most common defects arepetechiae, hepatosplenomegaly, and jaundice (60–80% of cases).
Less common defects include-microcephaly, cerebral calcifications, intrauterine growth retardation, and prematurity (30–50% of cases).
Risk is maximum if the infection occurs in early pregnancy and if the mother is primarily infected during pregnancy (one third of the primarily infected mothers transmit the virus to fetus in contrast to 1% of reactivated mothers)<br>
slide6. Perinatal CMV Infection- Transmission to the new-born occurs either during
delivery-through infected birth canal or
post natal- through infected breast milk / secretions from mother.
Mostly asymptomatic, but shed virus in urine from 8-12 weeks of age, up to several years.
Few infants, especially premature babies develop interstitial pneumonitis.<br>
slide7. Immunocompetent adults Mononucleosis like syndrome<br>
slide8. immunocompromised host (most of which are due to reactivation) In untreated AIDS patients (CD4 count <50/µL) - CMV may cause chorioretinitis, gastroenteritis, dementia and other disseminated CMV infection.
Organ transplant recipients- Most common viral infection (1 to 4 months post transplantation)
Bilateral interstitial pneumonia is the most common form seen in 15-20% of bone marrow transplant recipients;
Febrile leukopenia is seen among solid organ transplants recipients
Obliterative bronchiolitis in lung transplants
Graft atherosclerosis in heart transplants
Rejection of renal allografts<br>
slide9. Epidemiology Transmission-
Oral and respiratory spread is the predominant mode
Transplacental route ( transmission from mother to fetus)
Blood transfusion- Risk of transmission is about 0.1-10% per blood unit transfused
Organ transplantation
Sexual contact ( in young adults)<br>
slide10. Epidemiology Reservoir- Humans are the only known host for CMV.
Source- Virus may be shed in urine, saliva, semen, breast milk, and cervical secretions, and is carried in circulating white blood cells
CMV is endemic worldwide, present throughout the year without any seasonal variation.
Risk factors such as low socioeconomic status and poor personal hygiene facilitate the infection.
Prevalence is high in under developed nations with 90% of people being seropositive in contrast to 40–70% seropositivity in developed nations.<br>
slide11. Laboratory diagnosis Detection of inclusion bodies in urine:
Characteristic perinuclear cytoplasmic inclusions in addition to the usual intranuclear inclusions seen in other herpesviruses
Owl’s eye appearance<br>
slide12. Laboratory diagnosis (cont..) Virus Isolation- From throat washings and urine.
Human fibroblasts are the most ideal cell lines.
Cytopathic effect-After2–3 weeks of incubation, the following CPE may be observed-
Typical CMV inclusions,
Multinucleated giant cells are seen.
Enlargement of infected host cells<br>
slide13. Laboratory diagnosis (cont..) Shell vial technique - very useful in CMV mononucleosis where viral load is low and CPE takes several weeks to appear.<br>
slide14. Antibody Detection ELISA has been available for detecting serum antibodies against various antigens such as:
Matrix phosphoproteins pp150 and pp65
Glycoproteins gB and gH
Major DNA binding protein (pp52)<br>
slide15. Antibody Detection (cont..) CMV IgM antibodies appear in 1–2 weeks after infection and indicates recent or on-going infection.
Drops to below detectable levels within several months after infection.
IgM detection in pregnancy indicates congenital infection, thus guiding initiation of appropriate treatment<br>
slide16. Antibody Detection (cont..) CMV IgG antibodies are produced few days after IgM and persist life-long.
Indicates either a recent or past infection; which can be differentiated by performing IgG avidity test.
Low IgG avidity indicates recent infection (<3 weeks).
IgG avidity test is also useful in diagnosing congenital infection
Antibody detection cannot distinguish strain differences among the clinical isolates.<br>
slide17. Antigen Detection CMV-specific pp65 antigen (a major matrix phosphoprotein) can be detected in peripheral-blood leukocytes by indirect immunofluorescence test using specific monoclonal antibody.
Test has been in use since long; but is less preferred as it is time-consuming and technically demanding.<br>
slide18. Molecular Methods PCR - To detect specific CMV DNA in blood or body fluids such as CSF.
Various genes targeted are glycoprotein B (UL55), DNA polymerase (UL54) and pp65 (UL83)
PCR assays are rapid, highly sensitive, specific and have replaced the gold standard culture technique in most laboratories
Real time PCR can quantitate the viral load, hence, it is the method of choice to monitor the treatment response.<br>
slide19. Treatment CMV does not respond to acyclovir.
The following drugs are used for treatment of CMV infections.
Ganciclovir
Valganciclovir
Foscarnet
Cidofovir
CMV immunoglobulin<br>
slide20. Treatment Antiviral resistance can occur rarely due to mutations in target genes.
For example, UL97 mutation confers resistance to ganciclovir, while UL54 mutation leads to resistance to ganciclovir, cidofovir, and foscarnet)<br>
slide21. Prophylaxis Both ganciclovir and valgancyclovir have been used successfully for prophylaxis and preemptive therapy in transplant recipients.
CMV immunoglobulin has shown to be effective in preventing congenital infection when given to mother during pregnancy<br>
slide22. REFRENCES Text Book Of Medical Microbiology by Ananth
Narayan Paniker
Text Book Of Medical Microbiology by D R Arora
Text Book Of Medical Microbiology by A S Sastry
Text Book Of Medical Microbiology by Baweja
Text Book Of Medical Microbiology by Satish Gupte<br>