
Diabetes 101: Myths and Facts Lauren Golden MD















Description: Diabetes 101: Myths and Facts Lauren Golden MD Assistant Professor Clinical Medicine Naomi Berrie Diabetes Center Columbia University Medical Center New York, NY lhg2109columbia.edu www.nbdiabetes.org How Do We Diagnose Diabetes? Criteria
Related Topics
Download Presentation
"Diabetes 101: Myths and Facts Lauren Golden MD" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Diabetes 101: Myths and Facts Lauren Golden MD
Assistant Professor Clinical Medicine Naomi Berrie Diabetes Center Columbia University Medical Center New York, NY
lhg2109@columbia.edu
www.nbdiabetes.org<br>
slide2. How Do We Diagnose Diabetes?<br>
slide3. Criteria For Diagnosis of Diabetes Fasting blood sugar >126 mg/dL
2 Hour blood sugar >200 mg/dL after a glucose tolerance test
Random blood sugar >200 mg/dL + symptoms
HbA1c ≥ 6.5%, confirmed ADA. V. Diabetes Care. Diabetes Care 2013;36(suppl 1):S17.<br>
slide4. Criteria for Diagnosis: Pre-Diabetes Fasting blood sugar 100-125 mg/dL
2 Hour blood sugar 140-199 mg/dL
HbA1c 5.7-6.4% ADA. V. Diabetes Care. Diabetes Care 2013;36(suppl 1):S17.<br>
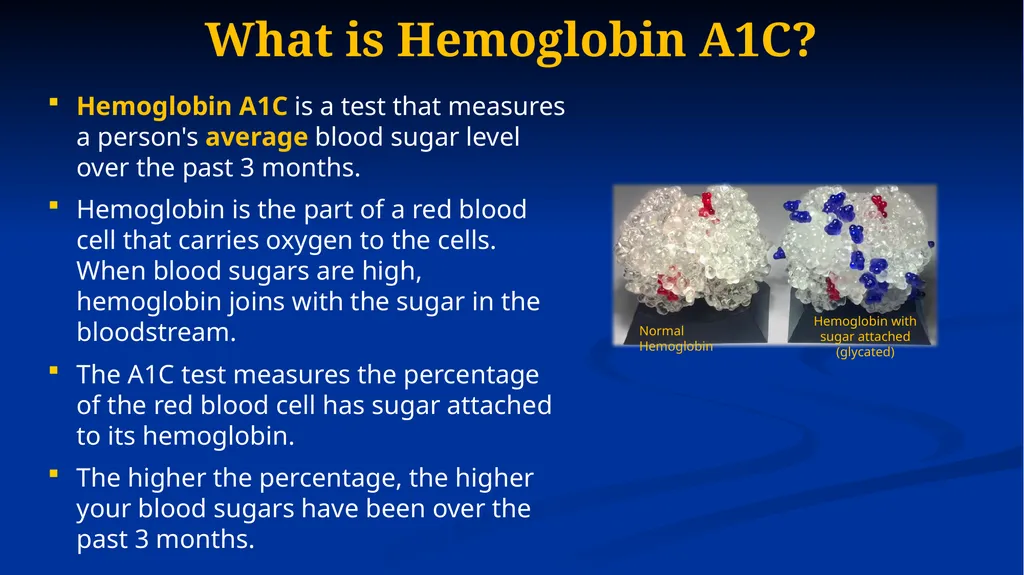
slide5. Normal Hemoglobin Hemoglobin with sugar attached (glycated) What is Hemoglobin A1C? Hemoglobin A1C is a test that measures a person's average blood sugar level over the past 3 months.
Hemoglobin is the part of a red blood cell that carries oxygen to the cells. When blood sugars are high, hemoglobin joins with the sugar in the bloodstream.
The A1C test measures the percentage of the red blood cell has sugar attached to its hemoglobin.
The higher the percentage, the higher your blood sugars have been over the past 3 months.<br>
slide6. Myth #1: Diabetes is caused by eating too much sugar Fact: Type 2 diabetes is caused by an inability of the pancreas to make enough insulin or if there is a problem with how the insulin is used by the cells. It is NOT from eating too much sugar. However, a more balanced diet can help to manage blood sugars.
So, if diabetes is not caused by eating to much sugar, why do some people get diabetes?<br>
slide7. Who Gets Type 2 Diabetes? People inherit genes that contribute to insulin resistance in liver, muscle and fat
This means that insulin does not work as effectively in these tissues and sugar cannot get as easily into cells
Beta cells, the cells that produce insulin, initially compensate by increasing insulin production to overcome the resistance
Overtime, beta cells fail, insulin levels fall, blood sugars rise, and people are diagnosed with diabetes<br>
slide8. Age
Ethnic background (African American, Latino, Native American, Asian American, Pacific Islander)
Family members with diabetes: mother, father, sister, brother
Previous diagnosis of gestational diabetes (diabetes during pregnancy)
Weight status: overweight and obesity
Physical Activity Status
Those with pre-diabetes Risk Factors for Type 2 Diabetes<br>
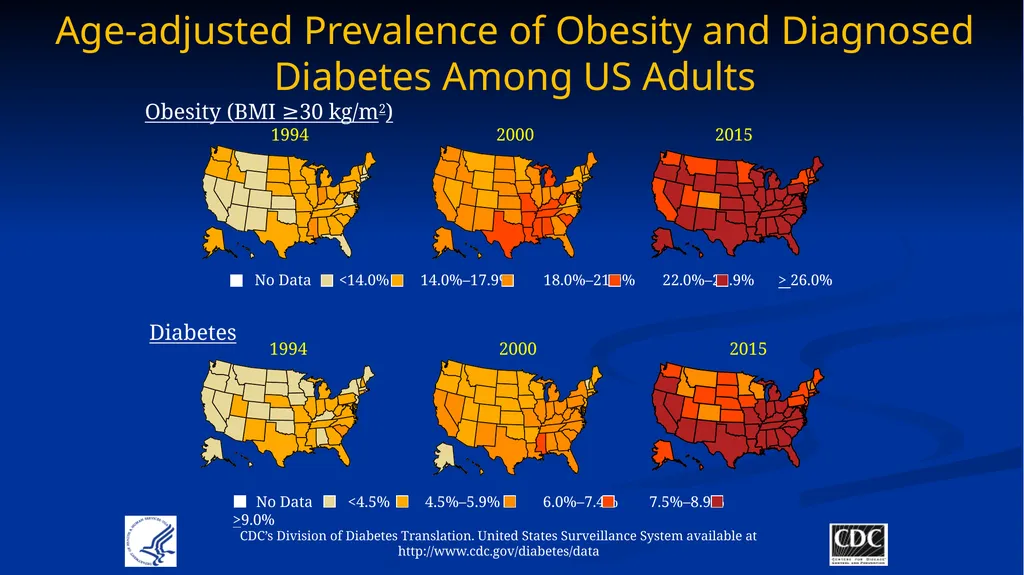
slide9. Age-adjusted Prevalence of Obesity and Diagnosed Diabetes Among US Adults Obesity (BMI ≥30 kg/m2) Diabetes CDC’s Division of Diabetes Translation. United States Surveillance System available at http://www.cdc.gov/diabetes/data 2015 2015<br>
slide10. Myth #2: If you are at risk for diabetes, there is nothing you can do to prevent it Fact: healthy lifestyle changes, including diet and exercise, can delay the onset of diabetes in those at risk
This includes people with pre-diabetes<br>
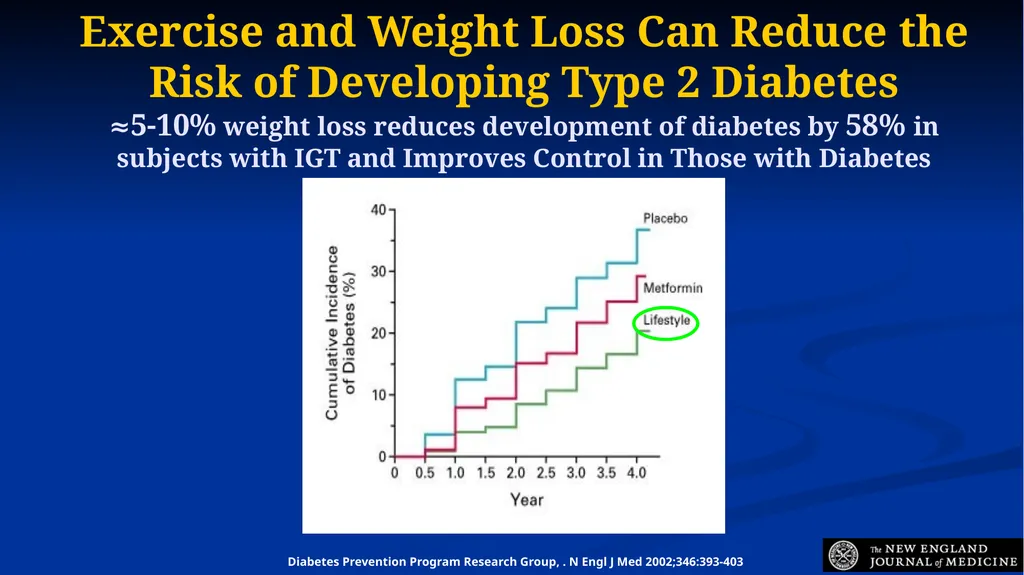
slide11. Diabetes Prevention Program Research Group, . N Engl J Med 2002;346:393-403 Exercise and Weight Loss Can Reduce the Risk of Developing Type 2 Diabetes
≈5-10% weight loss reduces development of diabetes by 58% in subjects with IGT and Improves Control in Those with Diabetes<br>
slide12. Myth #3: If you have diabetes, you cannot eat any carbohydrates ever again Fact: People with diabetes typically should be eating the same diet as anyone else –high in vegetables, fruits, fiber, whole grain, lean meats, and heart healthy fats. Moderate in sodium and low in saturated fat.
The key is to have small portions and to choose complex carbohydrates when eaten with meals
Try to save more processed carbohydrates (baked goods etc) for special occasions so the focus can be on balanced meals most of the time.<br>
slide13. If you have diabetes, is it better to check blood sugars fasting or after eating? Your provider may ask you to start by checking an occasional fasting blood sugar at home using a glucose meter
This shows how you body is doing when you have not eaten for many hours
A normal fasting blood sugar is <100mg/dL
Acceptable for diabetes is <135mg/dL, and as close to 100mg/dL as possible<br>
slide14. When would I check a blood sugar after eating? Sometimes you may want to see the effect of certain foods on your blood sugar
For example, a starchy meal would be expected to raise your blood sugar
By two hours after eating, a normal blood sugar would be <140mg/dL
Acceptable for diabetes is up to 150-180mg/dL
If your blood sugar is higher than that, your body had difficulty handling the food you ate for that meal<br>
slide15. Myth #4: It is inevitable that you will have to take insulin for diabetes, and this means that you have failed to take care of your diabetes properly Fact: Diabetes changes over time. Some people, particularly early in the course of their diabetes, may be able to manage their diabetes by eating more balanced meals and increasing their activity levels.
Over time (generally 5-10 years), many people with diabetes will require some sort of medication by mouth.
As time goes on (generally >10 years or more since diagnosis), and the body’s insulin production declines, many people will eventually require insulin.<br>
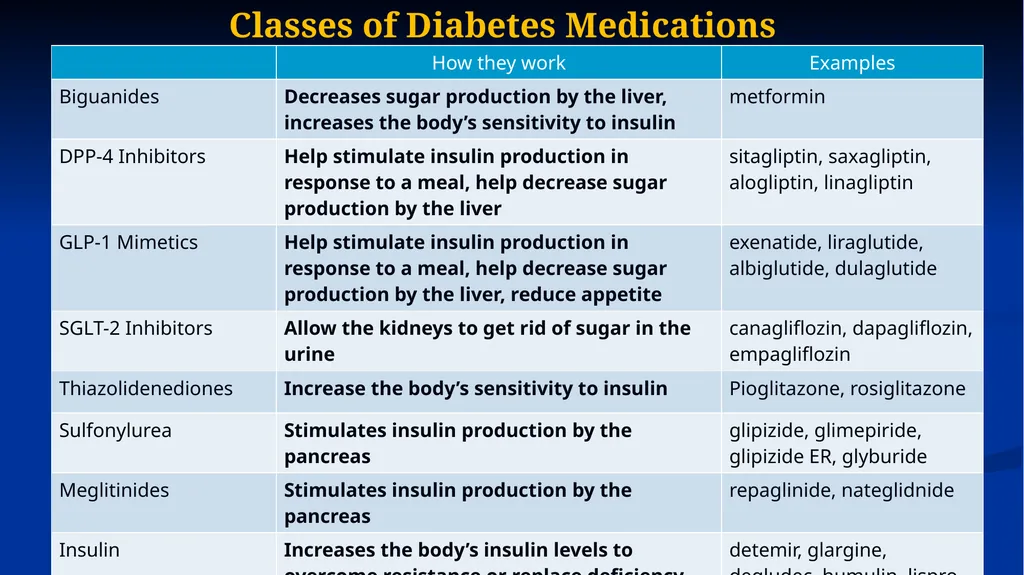
slide16. Classes of Diabetes Medications<br>
slide17. Myth #5: The way my provider decides what medication to prescribe me is totally random. Fact: If diet and exercise are not enough, your provider may recommend medical therapy for your diabetes, based on national guidelines and individual characteristics.
metformin is the preferred initial drug for treatment of type 2 diabetes, as long as there are no medical reasons why you should not take it
If a second drug is needed to control the blood sugars, the decision about what drug to add next depends on the presence or absence of heart disease Diabetes Care 2018 Jan; 41 (Supplement 1): S1-S159<br>
slide18. Medical Management of Type 2 Diabetes In patients with type 2 diabetes and atherosclerotic heart disease, the provider should next consider adding a diabetes medication that also reduces cardiovascular events and death from cardiovascular disease (empagliflozin and liraglutide; consider canagliflozin)
In patients without atherosclerotic heart disease, the provider should consider the importance of weight loss/weight gain, the risk of low blood sugars, oral vs injectable therapy, and the side effect profile of individual drugs. Diabetes Care 2018 Jan; 41 (Supplement 1): S1-S159<br>
Assistant Professor Clinical Medicine Naomi Berrie Diabetes Center Columbia University Medical Center New York, NY
lhg2109@columbia.edu
www.nbdiabetes.org<br>
slide2. How Do We Diagnose Diabetes?<br>
slide3. Criteria For Diagnosis of Diabetes Fasting blood sugar >126 mg/dL
2 Hour blood sugar >200 mg/dL after a glucose tolerance test
Random blood sugar >200 mg/dL + symptoms
HbA1c ≥ 6.5%, confirmed ADA. V. Diabetes Care. Diabetes Care 2013;36(suppl 1):S17.<br>
slide4. Criteria for Diagnosis: Pre-Diabetes Fasting blood sugar 100-125 mg/dL
2 Hour blood sugar 140-199 mg/dL
HbA1c 5.7-6.4% ADA. V. Diabetes Care. Diabetes Care 2013;36(suppl 1):S17.<br>
slide5. Normal Hemoglobin Hemoglobin with sugar attached (glycated) What is Hemoglobin A1C? Hemoglobin A1C is a test that measures a person's average blood sugar level over the past 3 months.
Hemoglobin is the part of a red blood cell that carries oxygen to the cells. When blood sugars are high, hemoglobin joins with the sugar in the bloodstream.
The A1C test measures the percentage of the red blood cell has sugar attached to its hemoglobin.
The higher the percentage, the higher your blood sugars have been over the past 3 months.<br>
slide6. Myth #1: Diabetes is caused by eating too much sugar Fact: Type 2 diabetes is caused by an inability of the pancreas to make enough insulin or if there is a problem with how the insulin is used by the cells. It is NOT from eating too much sugar. However, a more balanced diet can help to manage blood sugars.
So, if diabetes is not caused by eating to much sugar, why do some people get diabetes?<br>
slide7. Who Gets Type 2 Diabetes? People inherit genes that contribute to insulin resistance in liver, muscle and fat
This means that insulin does not work as effectively in these tissues and sugar cannot get as easily into cells
Beta cells, the cells that produce insulin, initially compensate by increasing insulin production to overcome the resistance
Overtime, beta cells fail, insulin levels fall, blood sugars rise, and people are diagnosed with diabetes<br>
slide8. Age
Ethnic background (African American, Latino, Native American, Asian American, Pacific Islander)
Family members with diabetes: mother, father, sister, brother
Previous diagnosis of gestational diabetes (diabetes during pregnancy)
Weight status: overweight and obesity
Physical Activity Status
Those with pre-diabetes Risk Factors for Type 2 Diabetes<br>
slide9. Age-adjusted Prevalence of Obesity and Diagnosed Diabetes Among US Adults Obesity (BMI ≥30 kg/m2) Diabetes CDC’s Division of Diabetes Translation. United States Surveillance System available at http://www.cdc.gov/diabetes/data 2015 2015<br>
slide10. Myth #2: If you are at risk for diabetes, there is nothing you can do to prevent it Fact: healthy lifestyle changes, including diet and exercise, can delay the onset of diabetes in those at risk
This includes people with pre-diabetes<br>
slide11. Diabetes Prevention Program Research Group, . N Engl J Med 2002;346:393-403 Exercise and Weight Loss Can Reduce the Risk of Developing Type 2 Diabetes
≈5-10% weight loss reduces development of diabetes by 58% in subjects with IGT and Improves Control in Those with Diabetes<br>
slide12. Myth #3: If you have diabetes, you cannot eat any carbohydrates ever again Fact: People with diabetes typically should be eating the same diet as anyone else –high in vegetables, fruits, fiber, whole grain, lean meats, and heart healthy fats. Moderate in sodium and low in saturated fat.
The key is to have small portions and to choose complex carbohydrates when eaten with meals
Try to save more processed carbohydrates (baked goods etc) for special occasions so the focus can be on balanced meals most of the time.<br>
slide13. If you have diabetes, is it better to check blood sugars fasting or after eating? Your provider may ask you to start by checking an occasional fasting blood sugar at home using a glucose meter
This shows how you body is doing when you have not eaten for many hours
A normal fasting blood sugar is <100mg/dL
Acceptable for diabetes is <135mg/dL, and as close to 100mg/dL as possible<br>
slide14. When would I check a blood sugar after eating? Sometimes you may want to see the effect of certain foods on your blood sugar
For example, a starchy meal would be expected to raise your blood sugar
By two hours after eating, a normal blood sugar would be <140mg/dL
Acceptable for diabetes is up to 150-180mg/dL
If your blood sugar is higher than that, your body had difficulty handling the food you ate for that meal<br>
slide15. Myth #4: It is inevitable that you will have to take insulin for diabetes, and this means that you have failed to take care of your diabetes properly Fact: Diabetes changes over time. Some people, particularly early in the course of their diabetes, may be able to manage their diabetes by eating more balanced meals and increasing their activity levels.
Over time (generally 5-10 years), many people with diabetes will require some sort of medication by mouth.
As time goes on (generally >10 years or more since diagnosis), and the body’s insulin production declines, many people will eventually require insulin.<br>
slide16. Classes of Diabetes Medications<br>
slide17. Myth #5: The way my provider decides what medication to prescribe me is totally random. Fact: If diet and exercise are not enough, your provider may recommend medical therapy for your diabetes, based on national guidelines and individual characteristics.
metformin is the preferred initial drug for treatment of type 2 diabetes, as long as there are no medical reasons why you should not take it
If a second drug is needed to control the blood sugars, the decision about what drug to add next depends on the presence or absence of heart disease Diabetes Care 2018 Jan; 41 (Supplement 1): S1-S159<br>
slide18. Medical Management of Type 2 Diabetes In patients with type 2 diabetes and atherosclerotic heart disease, the provider should next consider adding a diabetes medication that also reduces cardiovascular events and death from cardiovascular disease (empagliflozin and liraglutide; consider canagliflozin)
In patients without atherosclerotic heart disease, the provider should consider the importance of weight loss/weight gain, the risk of low blood sugars, oral vs injectable therapy, and the side effect profile of individual drugs. Diabetes Care 2018 Jan; 41 (Supplement 1): S1-S159<br>