
Drug-induced liver injury Clinical Practice













Description: Drug-induced liver injury Clinical Practice Guidelines About these slides These slides give a comprehensive overview of the EASL clinical practice guidelines on the management of drug-induced liver injury The guidelines were first presented
Related Topics
Download Presentation
"Drug-induced liver injury Clinical Practice" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Drug-induced liver injury Clinical Practice Guidelines<br>
slide2. About these slides These slides give a comprehensive overview of the EASL clinical practice guidelines on the management of drug-induced liver injury
The guidelines were first presented at the International Liver Congress 2018 and are published in the Journal of Hepatology
The full publication can be downloaded from the Clinical Practice Guidelines section of the EASL website
Please feel free to use, adapt, and share these slides for your own personal use; however, please acknowledge EASL as the source<br>
slide3. About these slides Definitions of all abbreviations shown in these slides are provided within the slide notes
When you see a home symbol like this one: , you can click on this to return to the outline or topics pages, depending on which section you are in
Please send any feedback to: slidedeck_feedback@easloffice.eu These slides are intended for use as an educational resource and should not be used in isolation to make patient management decisions. All information included should be verified before treating patients or using any therapies described in these materials<br>
slide4. Guideline panel EASL CPG DILI. J Hepatol 2019;70:122261. Chair
Raul J Andrade
Panel members
Guruprasad P Aithal, Einar S Björnsson, Neil Kaplowitz, Gerd A Kullak-Ublick, Dominique Larrey; Tom Hemming Karlsen (EASL Governing Board Representative)
Reviewers
EASL Governing Board, Didier Samuel, Tom Lüdde, Naga Chalasani<br>
slide5. Outline EASL CPG DILI. J Hepatol 2019;70:122261.<br>
slide6. Methods Grading evidence and recommendations<br>
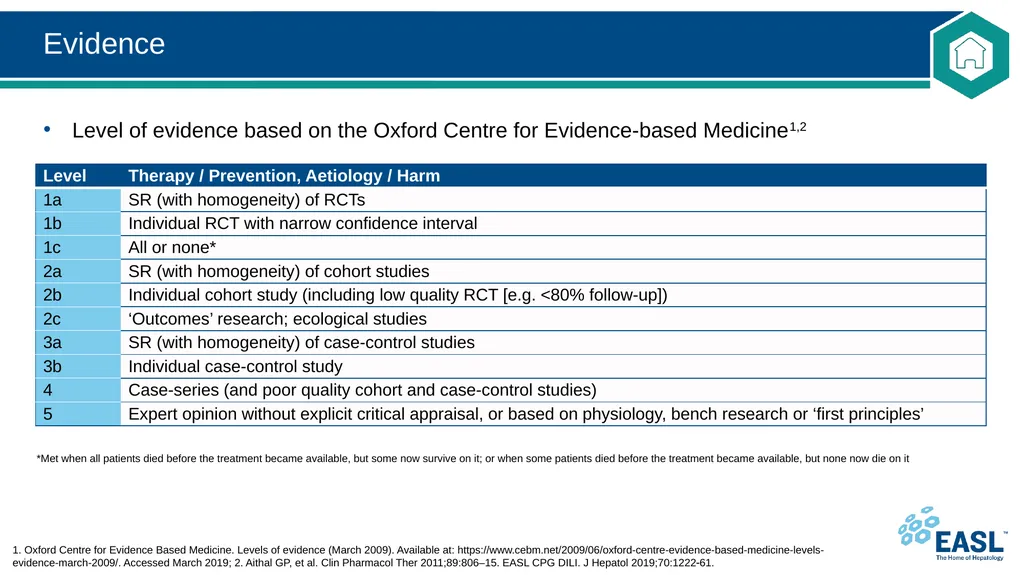
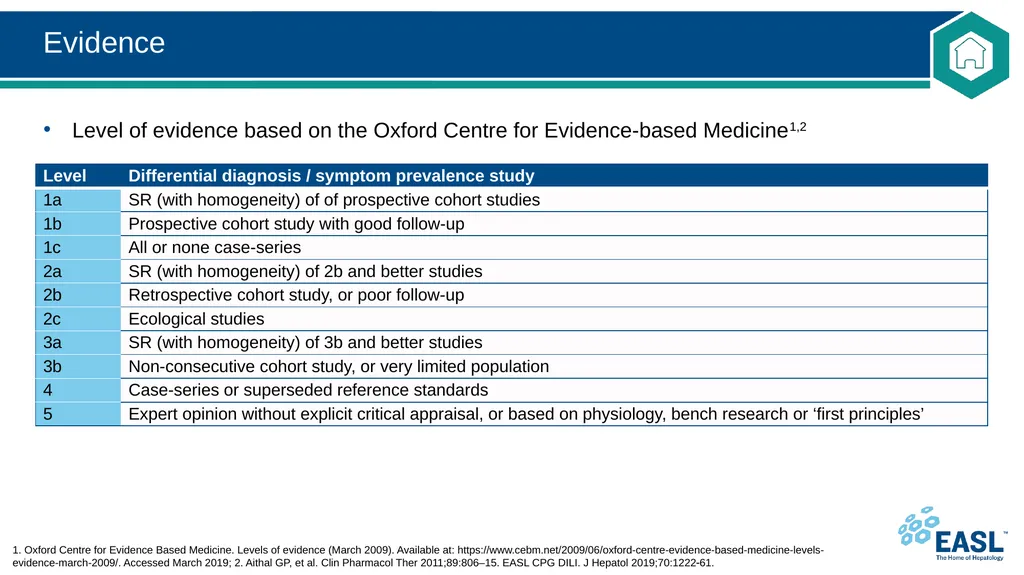
slide7. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2 *Met when all patients died before the treatment became available, but some now survive on it; or when some patients died before the treatment became available, but none now die on it<br>
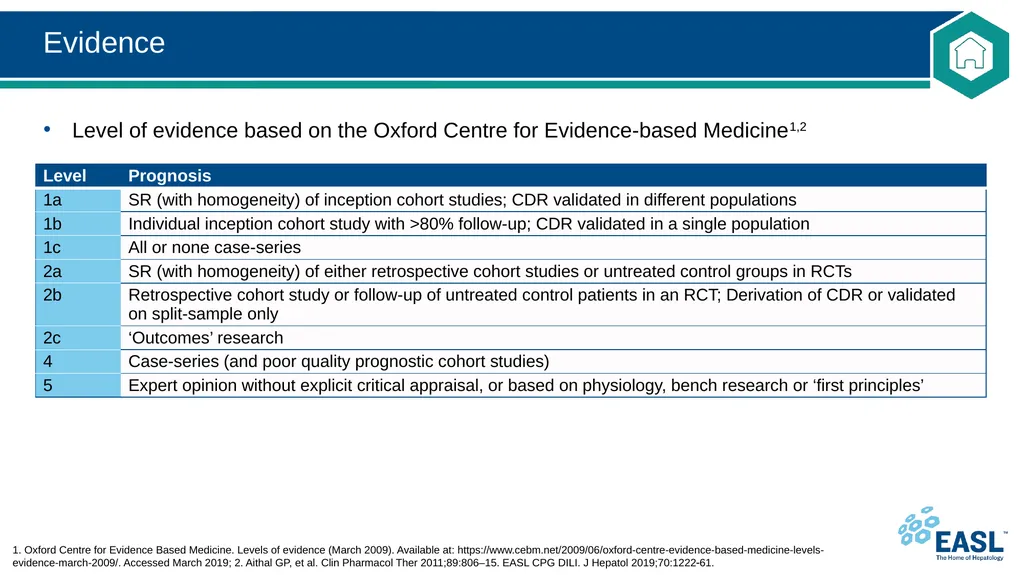
slide8. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2<br>
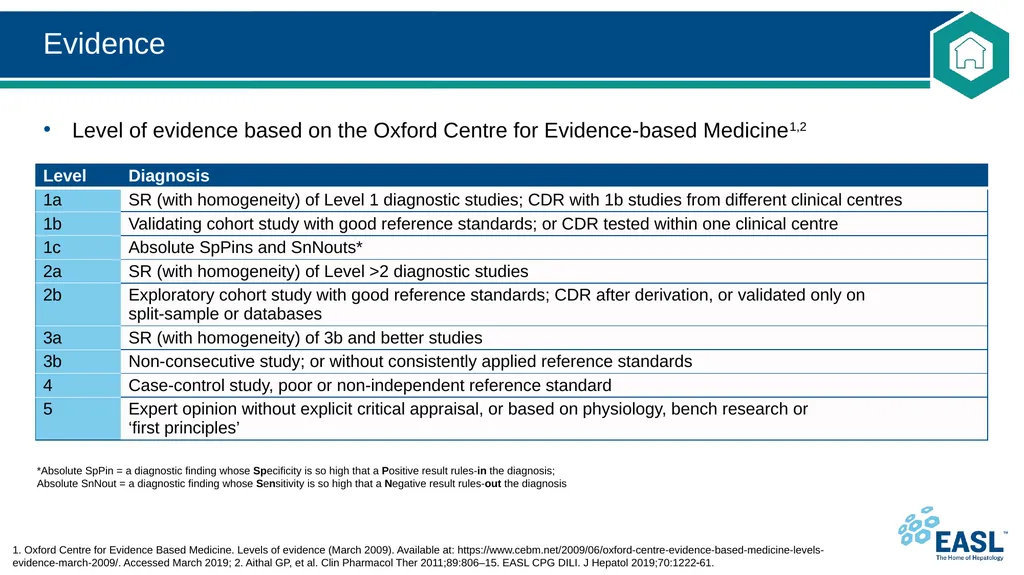
slide9. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2 *Absolute SpPin = a diagnostic finding whose Specificity is so high that a Positive result rules-in the diagnosis; Absolute SnNout = a diagnostic finding whose Sensitivity is so high that a Negative result rules-out the diagnosis<br>
slide10. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2<br>
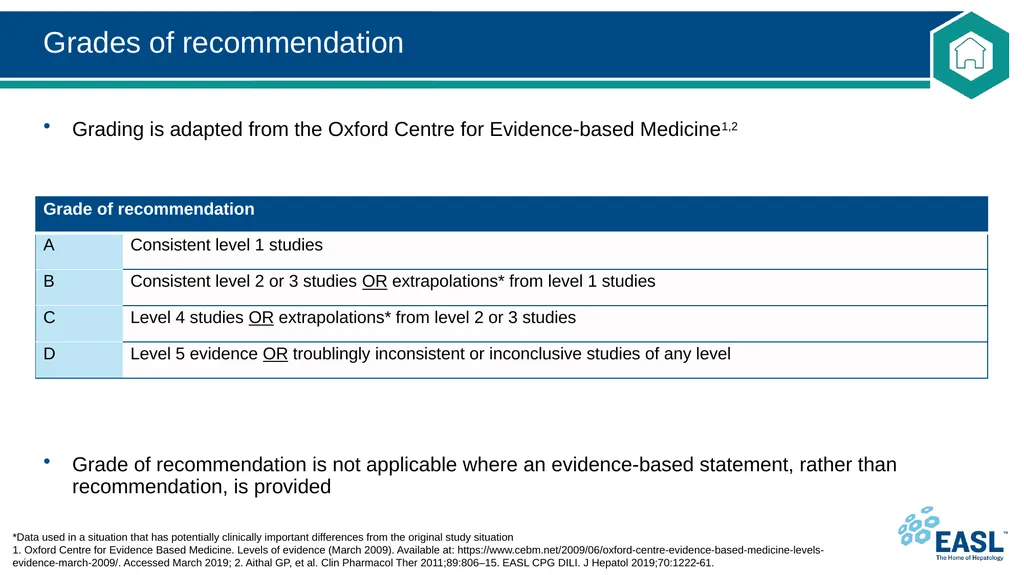
slide11. Grades of recommendation *Data used in a situation that has potentially clinically important differences from the original study situation
1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Grading is adapted from the Oxford Centre for Evidence-based Medicine1,2
Grade of recommendation is not applicable where an evidence-based statement, rather than recommendation, is provided<br>
slide12. Background General concepts
Epidemiology<br>
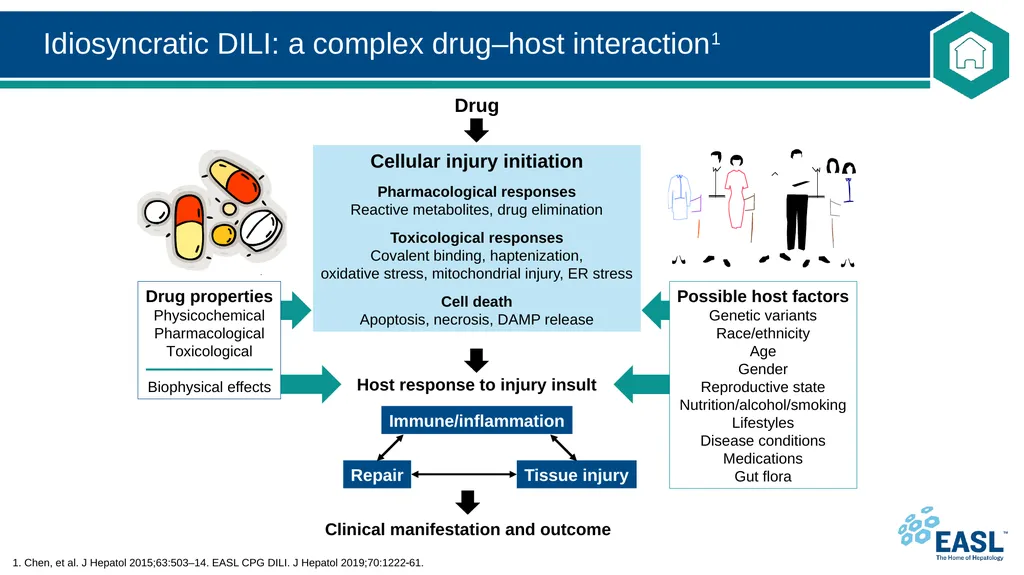
slide13. Idiosyncratic DILI: a complex drug–host interaction1 1. Chen, et al. J Hepatol 2015;63:503–14. EASL CPG DILI. J Hepatol 2019;70:122261. Possible host factors
Genetic variants
Race/ethnicity
Age
Gender
Reproductive state
Nutrition/alcohol/smoking
Lifestyles
Disease conditions
Medications
Gut flora Cellular injury initiation
Pharmacological responses
Reactive metabolites, drug elimination
Toxicological responses
Covalent binding, haptenization, oxidative stress, mitochondrial injury, ER stress
Cell death Apoptosis, necrosis, DAMP release Host response to injury insult Clinical manifestation and outcome Drug Drug properties
Physicochemical
Pharmacological
Toxicological
Biophysical effects<br>
slide14. Epidemiology *Lower incidence may be due to: use of higher liver enzyme cut-offs vs. previous prospective studies; limitation of surveillance to subspecialists.
1. Sgro C, et al. Hepatology 2002;36:451–5; 2. Björnsson ES, et al. Gastroenterology 2013;144:1419–25.e3;
3. Suk KT, et al. Am J Gastroenterol 2012;107:1380–7; 4. Vega M, et al. Drug Saf 2017;40:783–87; 5. Andrade RJ, et al. Gastroenterology 2005;129:512–21; 6. Chalasani N, et al. Gastroenterology 2015;148:1340–52.e7; 7. Bessone F, et al. Int J Mol Sci 2016;17:313. EASL CPG DILI. J Hepatol 2019;70:122261. The incidence of DILI in the general population is not well known
Population-based studies:
France: 14 cases per 100,000 inhabitants per year1
Iceland: 19 cases per 100,000 inhabitants per year2
Korea: 12 cases of hospitalization per 100,000 inhabitants per year3
USA: 2.7 cases per 100,000 adults attending gastroenterology practices*4
Prospective registries: recruit bona fide cases, a bias for more severe hospitalized DILI
Spanish DILI Registry5
DILIN6
LATINDILIN7<br>
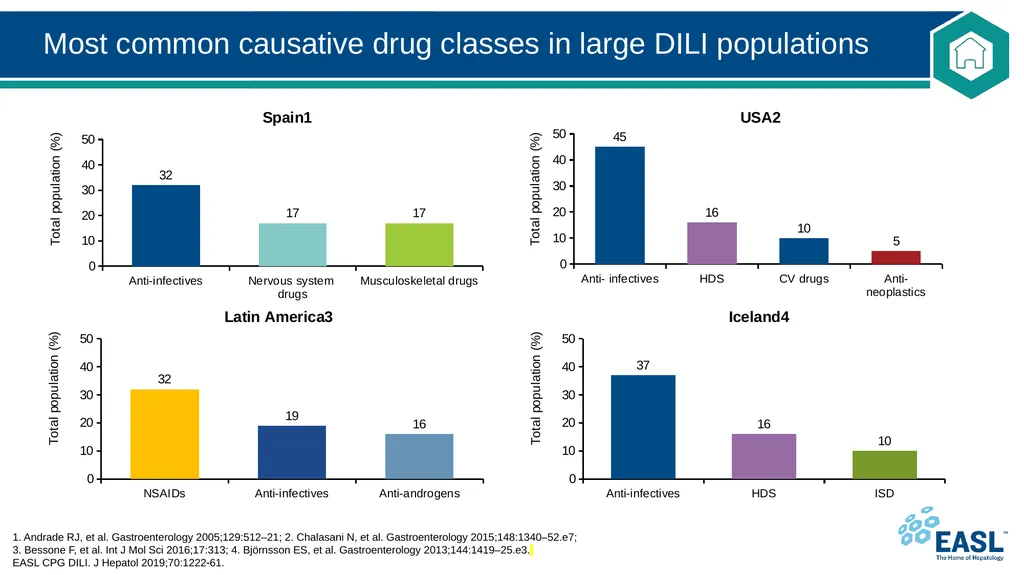
slide15. Most common causative drug classes in large DILI populations 1. Andrade RJ, et al. Gastroenterology 2005;129:512–21; 2. Chalasani N, et al. Gastroenterology 2015;148:1340–52.e7; 3. Bessone F, et al. Int J Mol Sci 2016;17:313; 4. Björnsson ES, et al. Gastroenterology 2013;144:1419–25.e3. EASL CPG DILI. J Hepatol 2019;70:122261.<br>
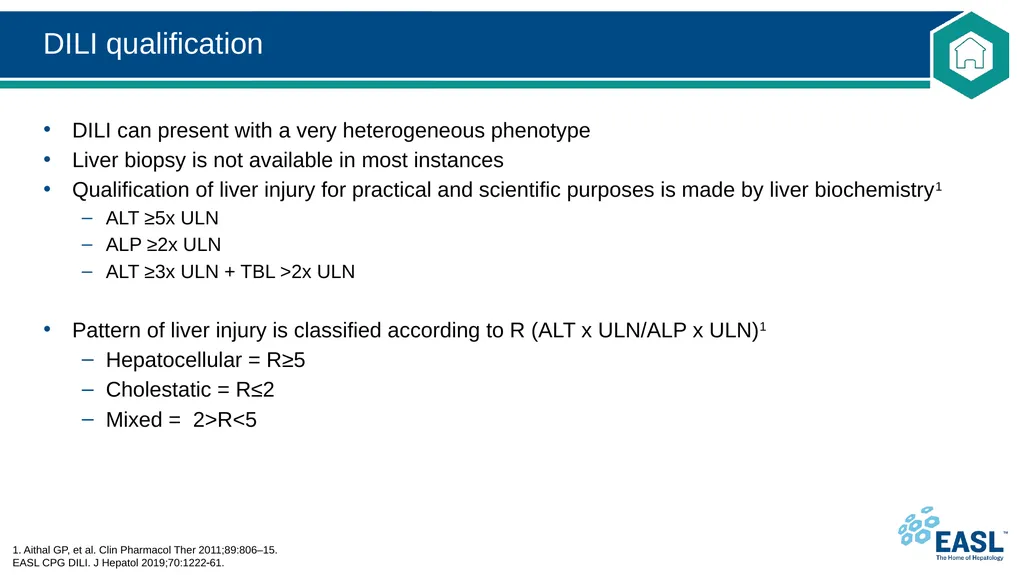
slide16. DILI qualification 1. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15.
EASL CPG DILI. J Hepatol 2019;70:122261. DILI can present with a very heterogeneous phenotype
Liver biopsy is not available in most instances
Qualification of liver injury for practical and scientific purposes is made by liver biochemistry1
ALT ≥5x ULN
ALP ≥2x ULN
ALT ≥3x ULN + TBL >2x ULN
Pattern of liver injury is classified according to R (ALT x ULN/ALP x ULN)1
Hepatocellular = R≥5
Cholestatic = R≤2
Mixed = 2>R<5<br>
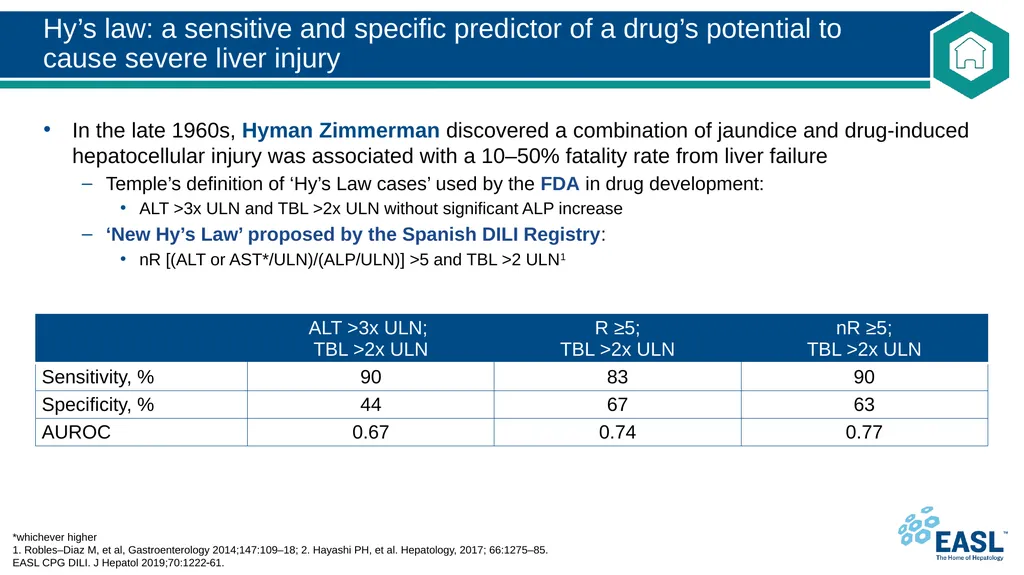
slide17. Hy’s law: a sensitive and specific predictor of a drug’s potential to cause severe liver injury *whichever higher 1. Robles–Diaz M, et al, Gastroenterology 2014;147:109–18; 2. Hayashi PH, et al. Hepatology, 2017; 66:1275–85.
EASL CPG DILI. J Hepatol 2019;70:122261. In the late 1960s, Hyman Zimmerman discovered a combination of jaundice and drug-induced hepatocellular injury was associated with a 10–50% fatality rate from liver failure
Temple’s definition of ‘Hy’s Law cases’ used by the FDA in drug development:
ALT >3x ULN and TBL >2x ULN without significant ALP increase
‘New Hy’s Law’ proposed by the Spanish DILI Registry:
nR [(ALT or AST*/ULN)/(ALP/ULN)] >5 and TBL >2 ULN1<br>
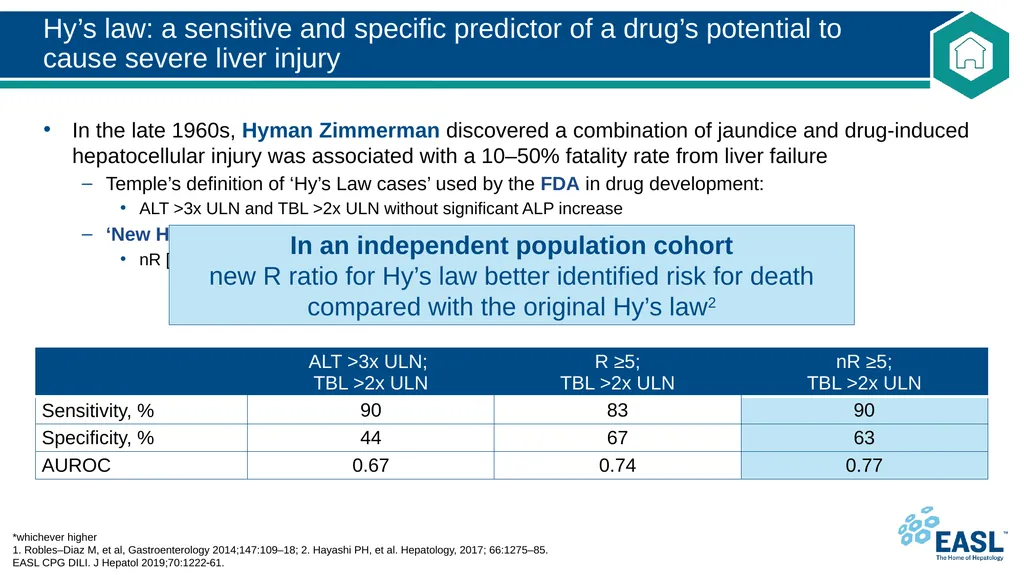
slide18. Hy’s law: a sensitive and specific predictor of a drug’s potential to cause severe liver injury *whichever higher 1. Robles–Diaz M, et al, Gastroenterology 2014;147:109–18; 2. Hayashi PH, et al. Hepatology, 2017; 66:1275–85.
EASL CPG DILI. J Hepatol 2019;70:122261. In the late 1960s, Hyman Zimmerman discovered a combination of jaundice and drug-induced hepatocellular injury was associated with a 10–50% fatality rate from liver failure
Temple’s definition of ‘Hy’s Law cases’ used by the FDA in drug development:
ALT >3x ULN and TBL >2x ULN without significant ALP increase
‘New Hy’s Law’ proposed by the Spanish DILI Registry:
nR [(ALT or AST*/ULN)/(ALP/ULN)] >5 and TBL>2 ULN1 In an independent population cohort
new R ratio for Hy’s law better identified risk for death compared with the original Hy’s law2<br>
slide19. Guidelines Key recommendations<br>
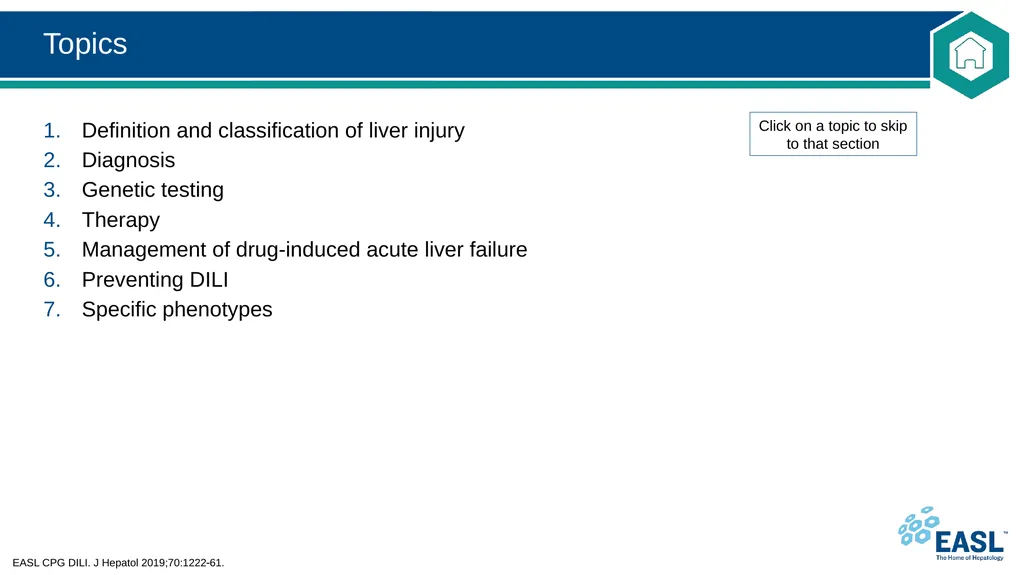
slide20. Topics EASL CPG DILI. J Hepatol 2019;70:122261. Definition and classification of liver injury
Diagnosis
Genetic testing
Therapy
Management of drug-induced acute liver failure
Preventing DILI
Specific phenotypes Click on a topic to skip to that section<br>
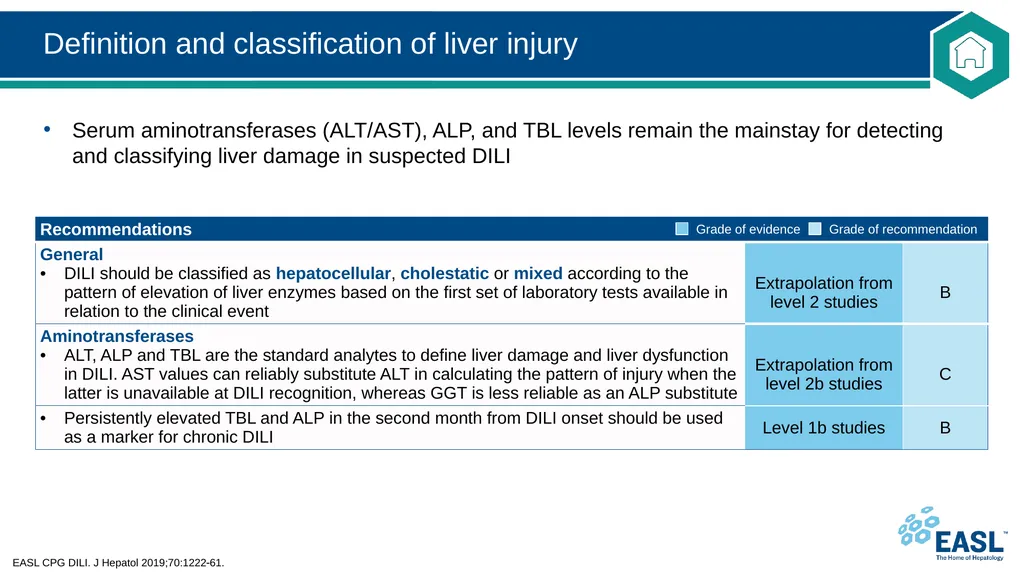
slide21. Definition and classification of liver injury EASL CPG DILI. J Hepatol 2019;70:122261. Serum aminotransferases (ALT/AST), ALP, and TBL levels remain the mainstay for detecting and classifying liver damage in suspected DILI<br>
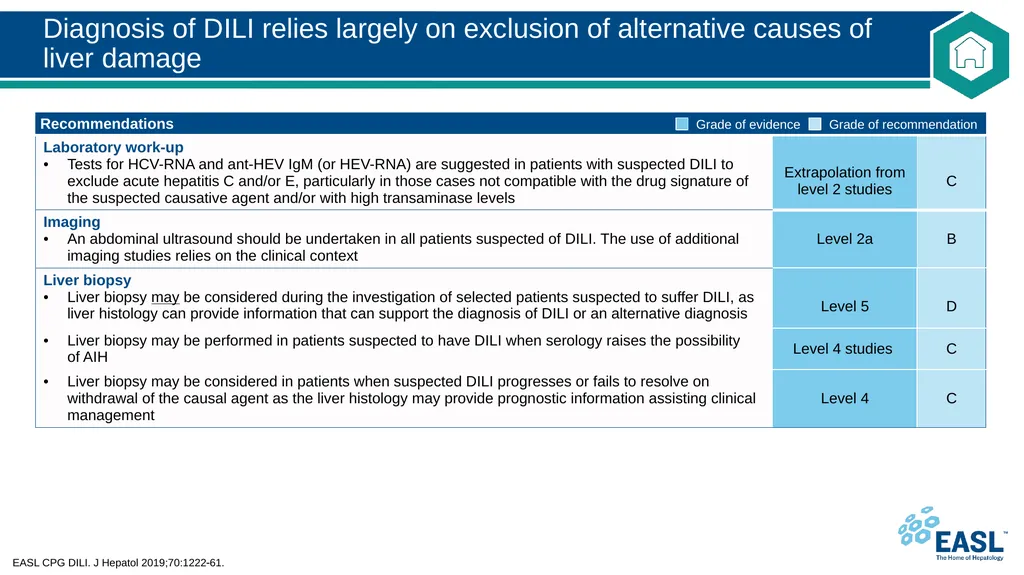
slide22. Diagnosis of DILI relies largely on exclusion of alternative causes of liver damage EASL CPG DILI. J Hepatol 2019;70:122261.<br>
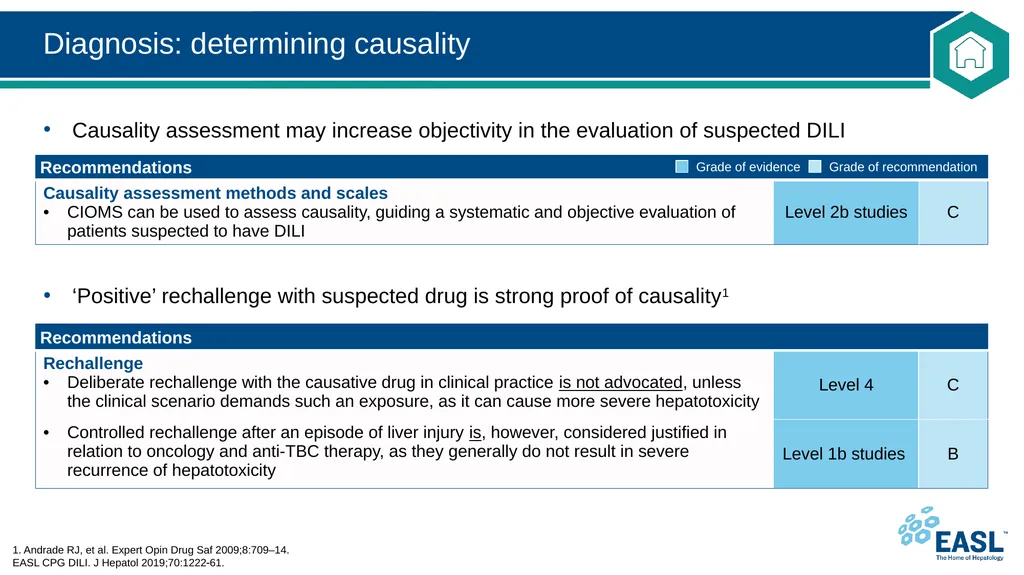
slide23. Diagnosis: determining causality 1. Andrade RJ, et al. Expert Opin Drug Saf 2009;8:709–14.
EASL CPG DILI. J Hepatol 2019;70:122261. Causality assessment may increase objectivity in the evaluation of suspected DILI
‘Positive’ rechallenge with suspected drug is strong proof of causality1<br>
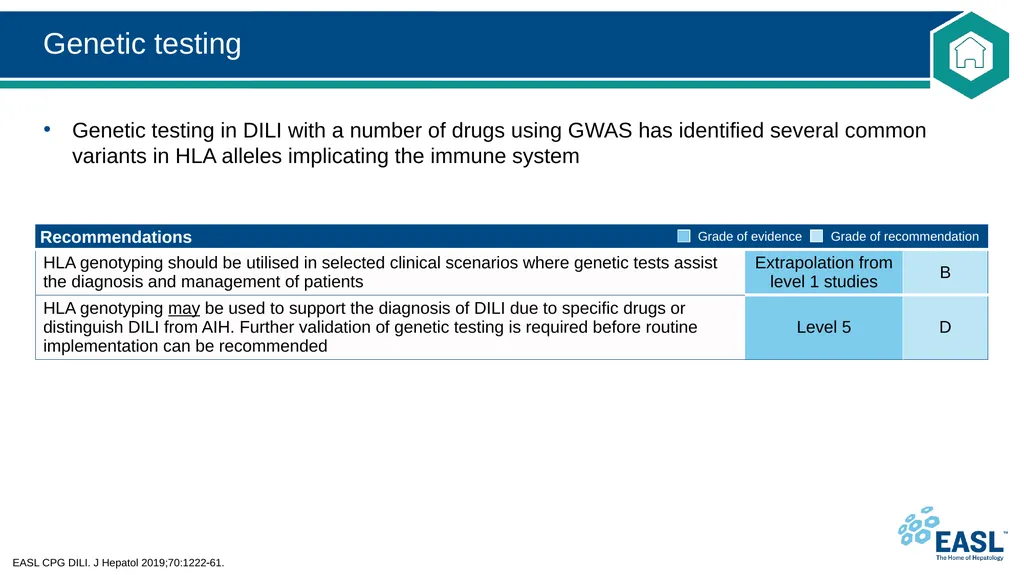
slide24. Genetic testing EASL CPG DILI. J Hepatol 2019;70:122261. Genetic testing in DILI with a number of drugs using GWAS has identified several common variants in HLA alleles implicating the immune system<br>
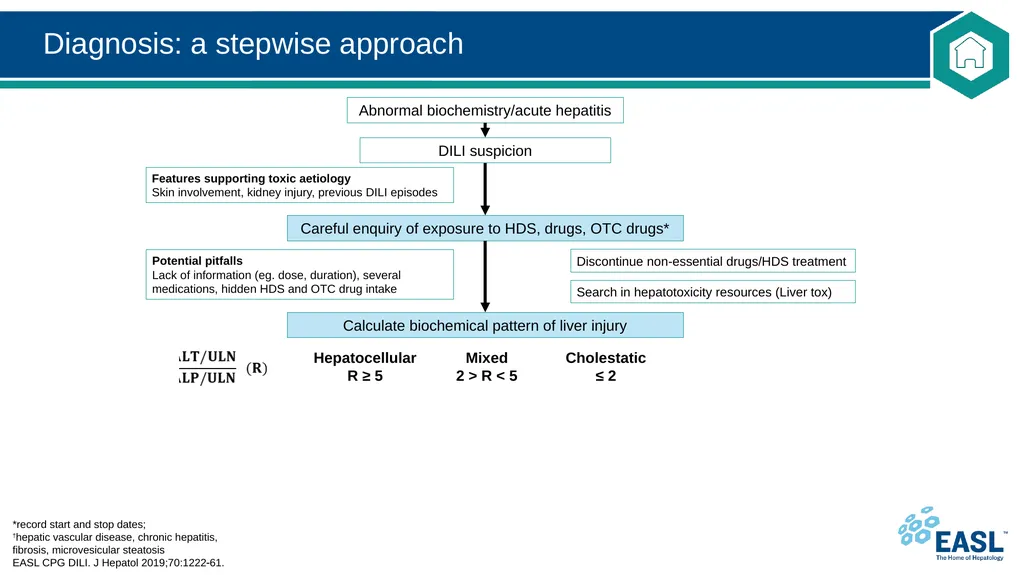
slide25. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
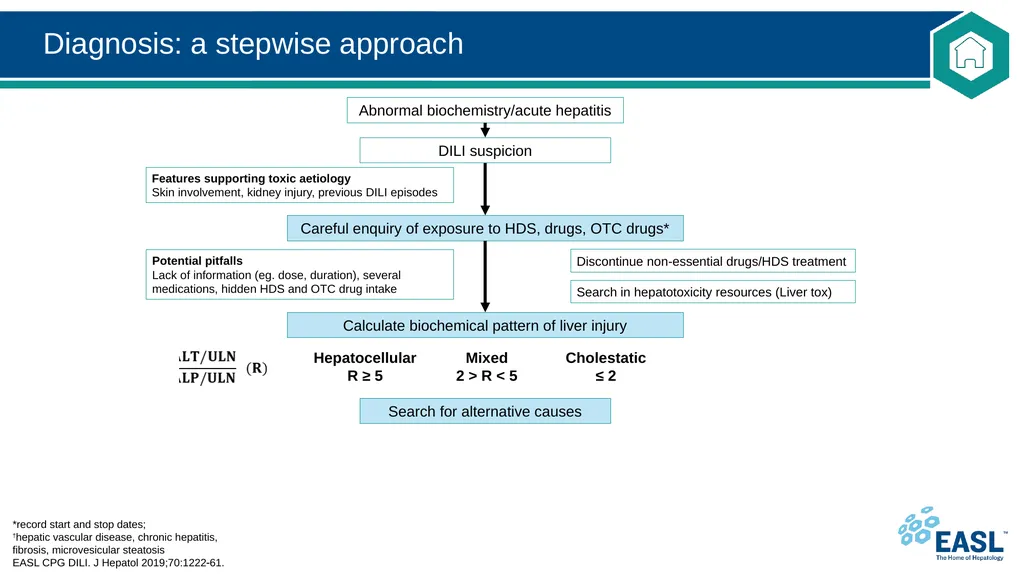
slide26. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
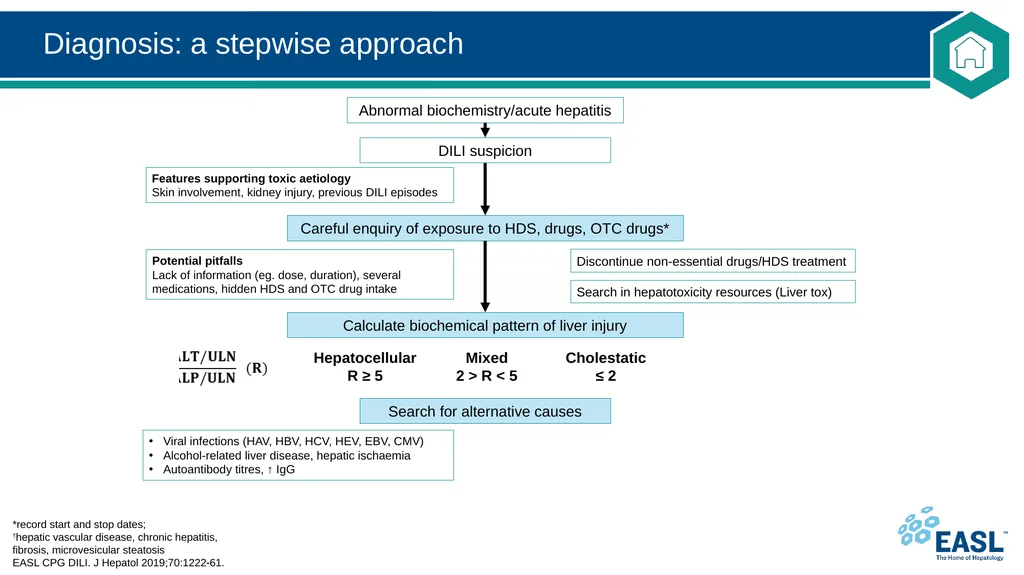
slide27. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Viral infections (HAV, HBV, HCV, HEV, EBV, CMV)
Alcohol-related liver disease, hepatic ischaemia
Autoantibody titres, ↑ IgG Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
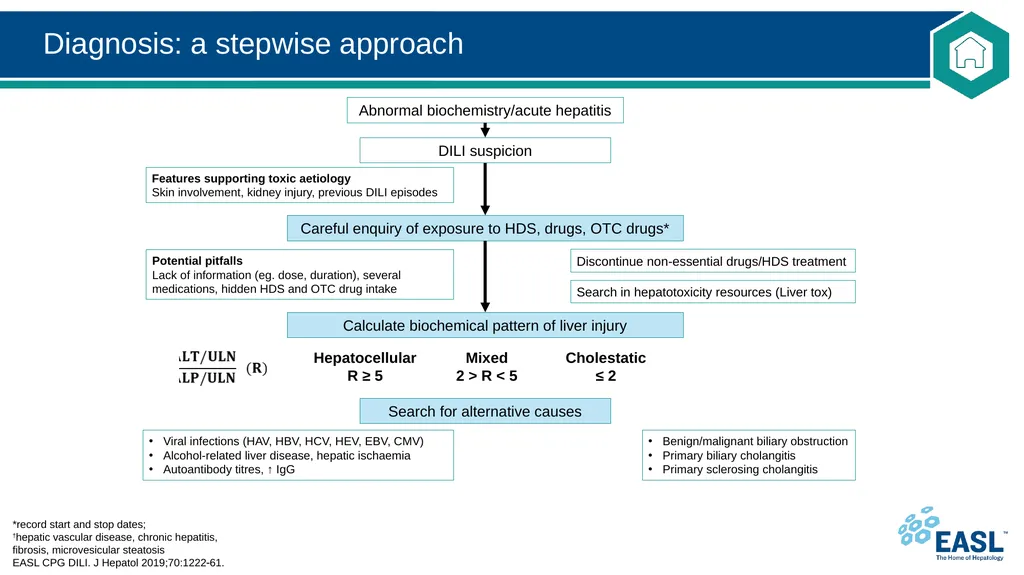
slide28. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Viral infections (HAV, HBV, HCV, HEV, EBV, CMV)
Alcohol-related liver disease, hepatic ischaemia
Autoantibody titres, ↑ IgG Benign/malignant biliary obstruction
Primary biliary cholangitis
Primary sclerosing cholangitis Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Hepatocellular
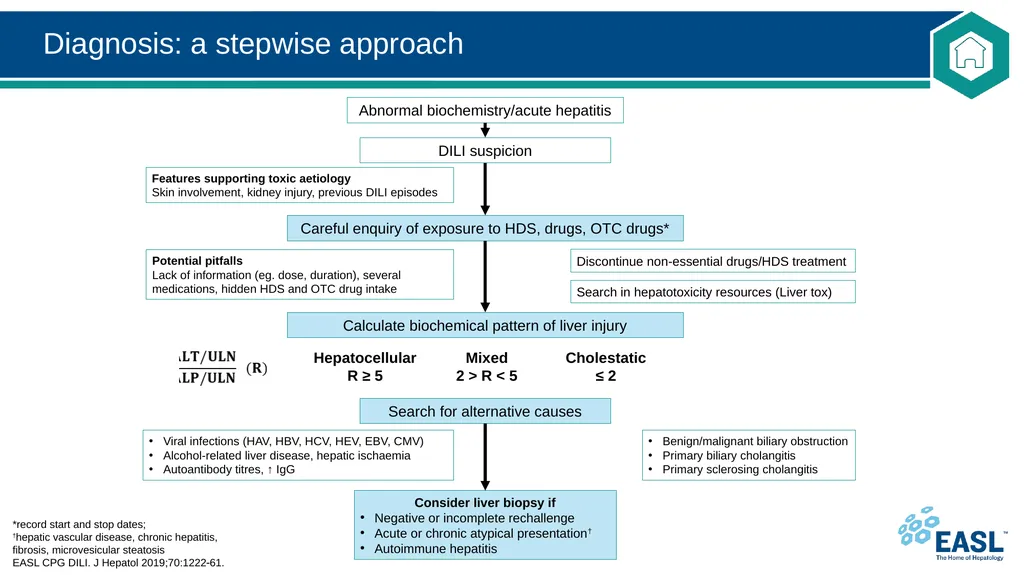
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
slide29. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Viral infections (HAV, HBV, HCV, HEV, EBV, CMV)
Alcohol-related liver disease, hepatic ischaemia
Autoantibody titres, ↑ IgG Benign/malignant biliary obstruction
Primary biliary cholangitis
Primary sclerosing cholangitis Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Consider liver biopsy if
Negative or incomplete rechallenge
Acute or chronic atypical presentation†
Autoimmune hepatitis Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
slide30. Therapy EASL CPG DILI. J Hepatol 2019;70:122261. Toxic liver damage is still an orphan hepatic disease with respect to therapy
Most important initial step in terms of management of suspected DILI is to discontinue the implicated agent<br>
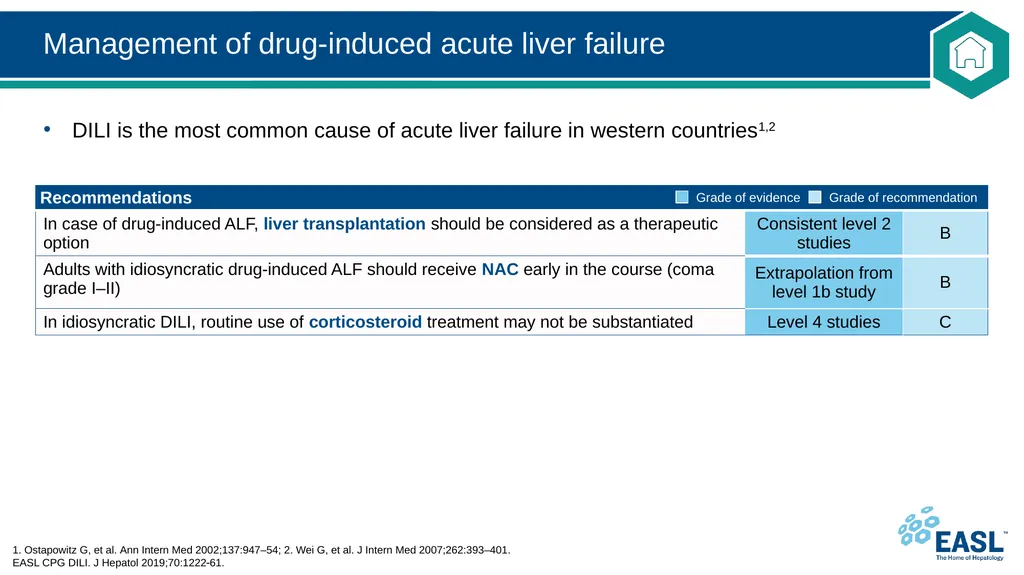
slide31. Management of drug-induced acute liver failure 1. Ostapowitz G, et al. Ann Intern Med 2002;137:947–54; 2. Wei G, et al. J Intern Med 2007;262:393–401. EASL CPG DILI. J Hepatol 2019;70:122261. DILI is the most common cause of acute liver failure in western countries1,2<br>
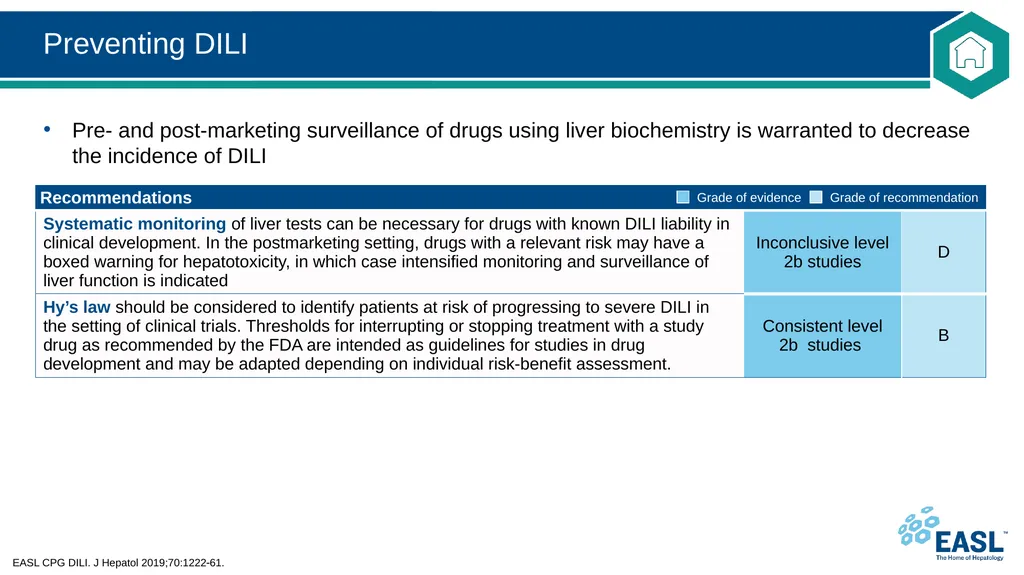
slide32. Preventing DILI EASL CPG DILI. J Hepatol 2019;70:122261. Pre- and post-marketing surveillance of drugs using liver biochemistry is warranted to decrease the incidence of DILI<br>
slide33. Specific phenotypes: AIH EASL CPG DILI. J Hepatol 2019;70:122261. A number of drugs have been associated with drug-induced AIH
A syndrome that shares many features of idiopathic AIH
In cohorts of cases with the diagnosis of AIH, 29% were considered to be drug-induced
Conversely, drug-induced AIH accounts for 9% of all DILI<br>
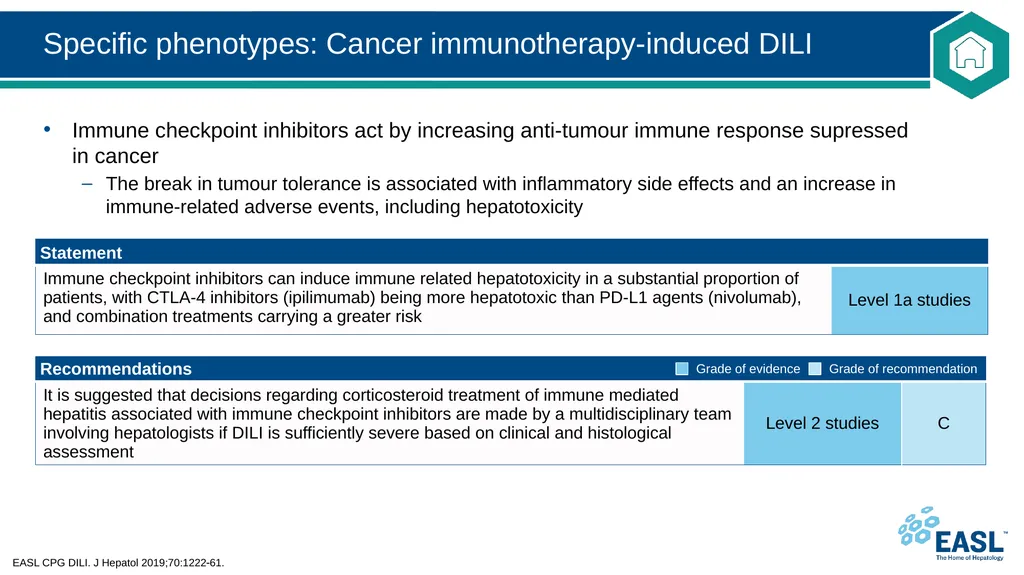
slide34. Specific phenotypes: Cancer immunotherapy-induced DILI EASL CPG DILI. J Hepatol 2019;70:122261. Immune checkpoint inhibitors act by increasing anti-tumour immune response supressed in cancer
The break in tumour tolerance is associated with inflammatory side effects and an increase in immune-related adverse events, including hepatotoxicity<br>
slide35. Specific phenotypes: Secondary sclerosing cholangitis 1. Gudnason HO, et al. Dig Liver Dis 2015;47:502–7.
EASL CPG DILI. J Hepatol 2019;70:122261. Strictures of the bile tract may result from ischaemia or drug toxicity1<br>
slide36. Specific phenotypes: Granulomatous hepatitis 1. Drebber U, et al. Liver Int 2008;28:828–34.
EASL CPG DILI. J Hepatol 2019;70:122261. Hepatic granulomas are reported in 2–15% of liver biopsies1
Of those with granulomatous hepatitis, 2.5% are considered drug-related<br>
slide37. Specific phenotypes: Acute fatty liver EASL CPG DILI. J Hepatol 2019;70:122261. Rare form of acute hepatotoxicity related to microvesicular steatosis
Manifested with hypoglycaemia, lactic acidosis, hyperammonaemia and cerebral oedema
Dramatically rapid development of organ failure precedes clinical syndrome
With an acute rise in liver enzymes and jaundice
An index of suspicion is crucial in identifying the drug aetiology when approaching a patient with ‘anicteric hepatic encephalopathy’<br>
slide38. Specific phenotypes: Drug-associated fatty liver disease (DAFLD) EASL CPG DILI. J Hepatol 2019;70:122261. NAFLD is associated with accumulation of fat in >5% of hepatocytes
With or without inflammation and fibrosis
In those with moderate or lower alcohol consumption
<21 units in men and <14 units in women, per week
Certain drugs may be one of the aetiologies behind a proportion of ‘secondary’ NAFLD
Cases not associated with characteristic features of metabolic syndrome
Where no risk factors are obvious<br>
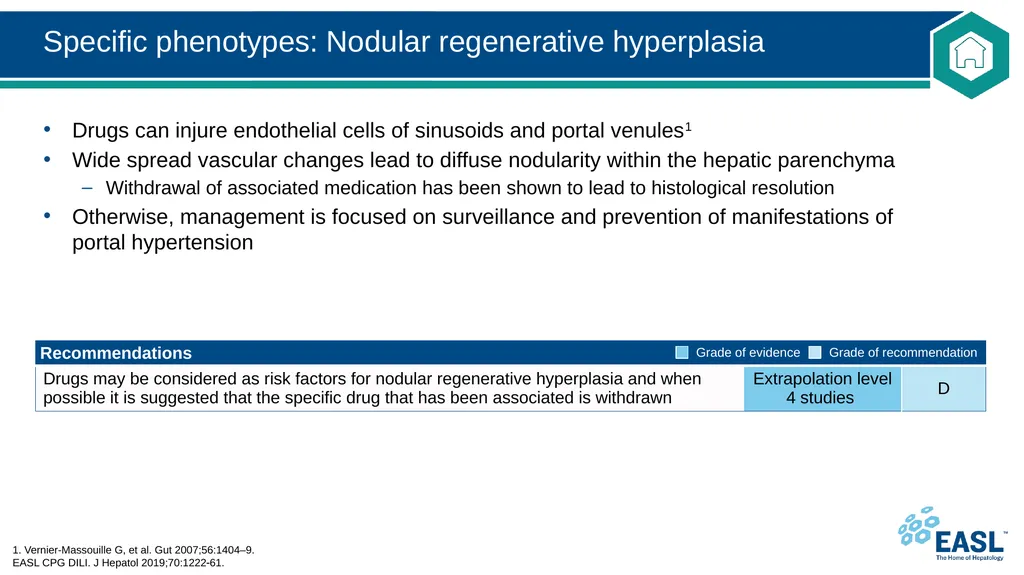
slide39. Specific phenotypes: Nodular regenerative hyperplasia 1. Vernier-Massouille G, et al. Gut 2007;56:1404–9. EASL CPG DILI. J Hepatol 2019;70:122261. Drugs can injure endothelial cells of sinusoids and portal venules1
Wide spread vascular changes lead to diffuse nodularity within the hepatic parenchyma
Withdrawal of associated medication has been shown to lead to histological resolution
Otherwise, management is focused on surveillance and prevention of manifestations of portal hypertension<br>
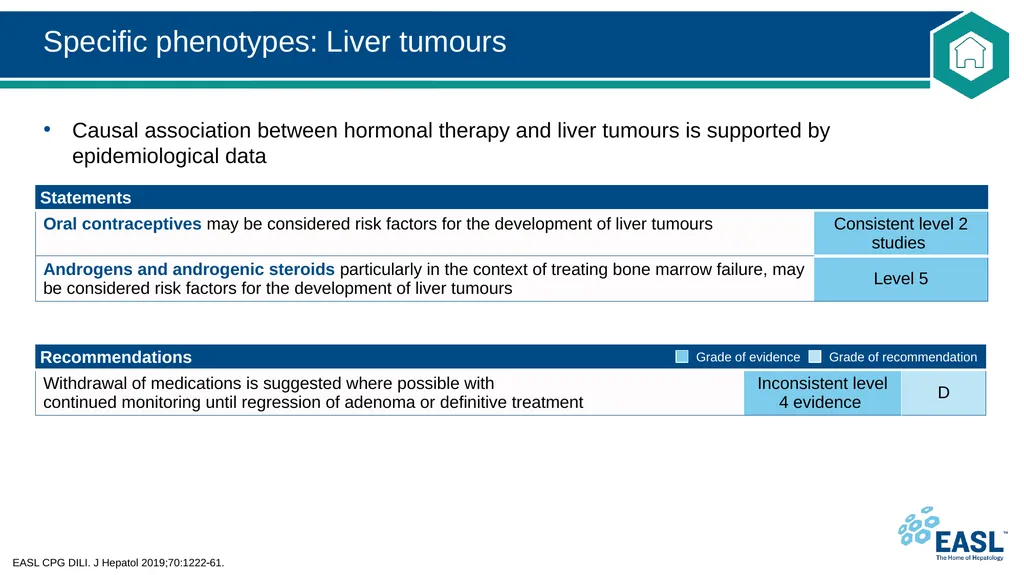
slide40. Specific phenotypes: Liver tumours EASL CPG DILI. J Hepatol 2019;70:122261. Causal association between hormonal therapy and liver tumours is supported by epidemiological data<br>
slide41. Future prospects New biomarkers
Unresolved issues
Unmet needs<br>
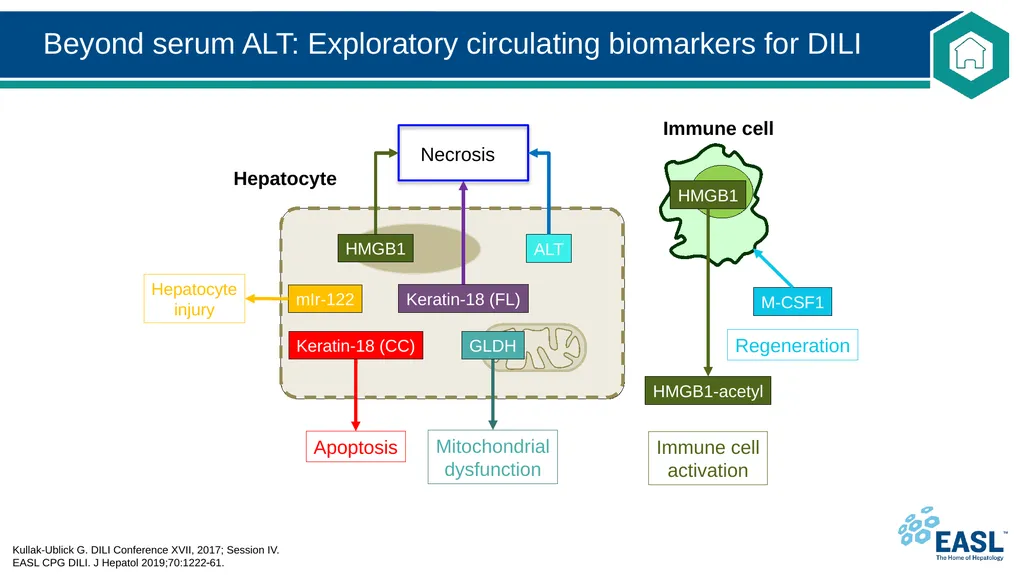
slide42. Beyond serum ALT: Exploratory circulating biomarkers for DILI Kullak-Ublick G. DILI Conference XVII, 2017; Session IV. EASL CPG DILI. J Hepatol 2019;70:122261. Hepatocyte Immune cell Necrosis Keratin-18 (CC) Apoptosis GLDH Mitochondrial dysfunction mIr-122 Hepatocyte injury Keratin-18 (FL) HMGB1 ALT HMGB1 HMGB1-acetyl Immune cell activation M-CSF1 Regeneration<br>
slide43. SAFE-T’s new liver safety biomarkers Kullak-Ublick G. DILI Conference XVII, 2017; Session IV. EASL CPG DILI. J Hepatol 2019;70:122261. Nine new liver safety biomarkers supported by the EMA and/or FDA for exploratory use in clinical drug development:<br>
slide44. Unresolved issues and unmet needs EASL CPG DILI. J Hepatol 2019;70:122261. Epidemiology
Big data analysis
Estimates of socioeconomic burden of DILI and its impact on quality of life
Robust case-control or population-based cohort studies to evaluate the risk of HDS- related liver injury, botanical identification and chemical analysis
Pathogenesis
Identify the factors that unmask or prevent liver injury as well as the determinants of severity of DILI in subjects otherwise genetically predisposed
Diagnosis and outcome
Discovery, evaluation and validation of biomarkers, which can distinguish self-resolving elevation of liver enzymes related to drugs from those with a potential to evolve into symptomatic DILI
Better prediction of DILI subjects at risk of ALF, including prognostic biomarkers
Therapy
Randomized controlled trials to evaluate the effect of specific interventions on the clinical outcomes of DILI
Prediction
Algorithms that reliably predict the DILI liability considering drug–host factors<br>
slide2. About these slides These slides give a comprehensive overview of the EASL clinical practice guidelines on the management of drug-induced liver injury
The guidelines were first presented at the International Liver Congress 2018 and are published in the Journal of Hepatology
The full publication can be downloaded from the Clinical Practice Guidelines section of the EASL website
Please feel free to use, adapt, and share these slides for your own personal use; however, please acknowledge EASL as the source<br>
slide3. About these slides Definitions of all abbreviations shown in these slides are provided within the slide notes
When you see a home symbol like this one: , you can click on this to return to the outline or topics pages, depending on which section you are in
Please send any feedback to: slidedeck_feedback@easloffice.eu These slides are intended for use as an educational resource and should not be used in isolation to make patient management decisions. All information included should be verified before treating patients or using any therapies described in these materials<br>
slide4. Guideline panel EASL CPG DILI. J Hepatol 2019;70:122261. Chair
Raul J Andrade
Panel members
Guruprasad P Aithal, Einar S Björnsson, Neil Kaplowitz, Gerd A Kullak-Ublick, Dominique Larrey; Tom Hemming Karlsen (EASL Governing Board Representative)
Reviewers
EASL Governing Board, Didier Samuel, Tom Lüdde, Naga Chalasani<br>
slide5. Outline EASL CPG DILI. J Hepatol 2019;70:122261.<br>
slide6. Methods Grading evidence and recommendations<br>
slide7. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2 *Met when all patients died before the treatment became available, but some now survive on it; or when some patients died before the treatment became available, but none now die on it<br>
slide8. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2<br>
slide9. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2 *Absolute SpPin = a diagnostic finding whose Specificity is so high that a Positive result rules-in the diagnosis; Absolute SnNout = a diagnostic finding whose Sensitivity is so high that a Negative result rules-out the diagnosis<br>
slide10. Evidence 1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Level of evidence based on the Oxford Centre for Evidence-based Medicine1,2<br>
slide11. Grades of recommendation *Data used in a situation that has potentially clinically important differences from the original study situation
1. Oxford Centre for Evidence Based Medicine. Levels of evidence (March 2009). Available at: https://www.cebm.net/2009/06/oxford-centre-evidence-based-medicine-levels-evidence-march-2009/. Accessed March 2019; 2. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15. EASL CPG DILI. J Hepatol 2019;70:122261. Grading is adapted from the Oxford Centre for Evidence-based Medicine1,2
Grade of recommendation is not applicable where an evidence-based statement, rather than recommendation, is provided<br>
slide12. Background General concepts
Epidemiology<br>
slide13. Idiosyncratic DILI: a complex drug–host interaction1 1. Chen, et al. J Hepatol 2015;63:503–14. EASL CPG DILI. J Hepatol 2019;70:122261. Possible host factors
Genetic variants
Race/ethnicity
Age
Gender
Reproductive state
Nutrition/alcohol/smoking
Lifestyles
Disease conditions
Medications
Gut flora Cellular injury initiation
Pharmacological responses
Reactive metabolites, drug elimination
Toxicological responses
Covalent binding, haptenization, oxidative stress, mitochondrial injury, ER stress
Cell death Apoptosis, necrosis, DAMP release Host response to injury insult Clinical manifestation and outcome Drug Drug properties
Physicochemical
Pharmacological
Toxicological
Biophysical effects<br>
slide14. Epidemiology *Lower incidence may be due to: use of higher liver enzyme cut-offs vs. previous prospective studies; limitation of surveillance to subspecialists.
1. Sgro C, et al. Hepatology 2002;36:451–5; 2. Björnsson ES, et al. Gastroenterology 2013;144:1419–25.e3;
3. Suk KT, et al. Am J Gastroenterol 2012;107:1380–7; 4. Vega M, et al. Drug Saf 2017;40:783–87; 5. Andrade RJ, et al. Gastroenterology 2005;129:512–21; 6. Chalasani N, et al. Gastroenterology 2015;148:1340–52.e7; 7. Bessone F, et al. Int J Mol Sci 2016;17:313. EASL CPG DILI. J Hepatol 2019;70:122261. The incidence of DILI in the general population is not well known
Population-based studies:
France: 14 cases per 100,000 inhabitants per year1
Iceland: 19 cases per 100,000 inhabitants per year2
Korea: 12 cases of hospitalization per 100,000 inhabitants per year3
USA: 2.7 cases per 100,000 adults attending gastroenterology practices*4
Prospective registries: recruit bona fide cases, a bias for more severe hospitalized DILI
Spanish DILI Registry5
DILIN6
LATINDILIN7<br>
slide15. Most common causative drug classes in large DILI populations 1. Andrade RJ, et al. Gastroenterology 2005;129:512–21; 2. Chalasani N, et al. Gastroenterology 2015;148:1340–52.e7; 3. Bessone F, et al. Int J Mol Sci 2016;17:313; 4. Björnsson ES, et al. Gastroenterology 2013;144:1419–25.e3. EASL CPG DILI. J Hepatol 2019;70:122261.<br>
slide16. DILI qualification 1. Aithal GP, et al. Clin Pharmacol Ther 2011;89:806–15.
EASL CPG DILI. J Hepatol 2019;70:122261. DILI can present with a very heterogeneous phenotype
Liver biopsy is not available in most instances
Qualification of liver injury for practical and scientific purposes is made by liver biochemistry1
ALT ≥5x ULN
ALP ≥2x ULN
ALT ≥3x ULN + TBL >2x ULN
Pattern of liver injury is classified according to R (ALT x ULN/ALP x ULN)1
Hepatocellular = R≥5
Cholestatic = R≤2
Mixed = 2>R<5<br>
slide17. Hy’s law: a sensitive and specific predictor of a drug’s potential to cause severe liver injury *whichever higher 1. Robles–Diaz M, et al, Gastroenterology 2014;147:109–18; 2. Hayashi PH, et al. Hepatology, 2017; 66:1275–85.
EASL CPG DILI. J Hepatol 2019;70:122261. In the late 1960s, Hyman Zimmerman discovered a combination of jaundice and drug-induced hepatocellular injury was associated with a 10–50% fatality rate from liver failure
Temple’s definition of ‘Hy’s Law cases’ used by the FDA in drug development:
ALT >3x ULN and TBL >2x ULN without significant ALP increase
‘New Hy’s Law’ proposed by the Spanish DILI Registry:
nR [(ALT or AST*/ULN)/(ALP/ULN)] >5 and TBL >2 ULN1<br>
slide18. Hy’s law: a sensitive and specific predictor of a drug’s potential to cause severe liver injury *whichever higher 1. Robles–Diaz M, et al, Gastroenterology 2014;147:109–18; 2. Hayashi PH, et al. Hepatology, 2017; 66:1275–85.
EASL CPG DILI. J Hepatol 2019;70:122261. In the late 1960s, Hyman Zimmerman discovered a combination of jaundice and drug-induced hepatocellular injury was associated with a 10–50% fatality rate from liver failure
Temple’s definition of ‘Hy’s Law cases’ used by the FDA in drug development:
ALT >3x ULN and TBL >2x ULN without significant ALP increase
‘New Hy’s Law’ proposed by the Spanish DILI Registry:
nR [(ALT or AST*/ULN)/(ALP/ULN)] >5 and TBL>2 ULN1 In an independent population cohort
new R ratio for Hy’s law better identified risk for death compared with the original Hy’s law2<br>
slide19. Guidelines Key recommendations<br>
slide20. Topics EASL CPG DILI. J Hepatol 2019;70:122261. Definition and classification of liver injury
Diagnosis
Genetic testing
Therapy
Management of drug-induced acute liver failure
Preventing DILI
Specific phenotypes Click on a topic to skip to that section<br>
slide21. Definition and classification of liver injury EASL CPG DILI. J Hepatol 2019;70:122261. Serum aminotransferases (ALT/AST), ALP, and TBL levels remain the mainstay for detecting and classifying liver damage in suspected DILI<br>
slide22. Diagnosis of DILI relies largely on exclusion of alternative causes of liver damage EASL CPG DILI. J Hepatol 2019;70:122261.<br>
slide23. Diagnosis: determining causality 1. Andrade RJ, et al. Expert Opin Drug Saf 2009;8:709–14.
EASL CPG DILI. J Hepatol 2019;70:122261. Causality assessment may increase objectivity in the evaluation of suspected DILI
‘Positive’ rechallenge with suspected drug is strong proof of causality1<br>
slide24. Genetic testing EASL CPG DILI. J Hepatol 2019;70:122261. Genetic testing in DILI with a number of drugs using GWAS has identified several common variants in HLA alleles implicating the immune system<br>
slide25. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
slide26. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
slide27. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Viral infections (HAV, HBV, HCV, HEV, EBV, CMV)
Alcohol-related liver disease, hepatic ischaemia
Autoantibody titres, ↑ IgG Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
slide28. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Viral infections (HAV, HBV, HCV, HEV, EBV, CMV)
Alcohol-related liver disease, hepatic ischaemia
Autoantibody titres, ↑ IgG Benign/malignant biliary obstruction
Primary biliary cholangitis
Primary sclerosing cholangitis Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
slide29. Diagnosis: a stepwise approach *record start and stop dates; †hepatic vascular disease, chronic hepatitis, fibrosis, microvesicular steatosis EASL CPG DILI. J Hepatol 2019;70:122261. Discontinue non-essential drugs/HDS treatment Features supporting toxic aetiology
Skin involvement, kidney injury, previous DILI episodes Potential pitfalls
Lack of information (eg. dose, duration), several medications, hidden HDS and OTC drug intake Viral infections (HAV, HBV, HCV, HEV, EBV, CMV)
Alcohol-related liver disease, hepatic ischaemia
Autoantibody titres, ↑ IgG Benign/malignant biliary obstruction
Primary biliary cholangitis
Primary sclerosing cholangitis Abnormal biochemistry/acute hepatitis DILI suspicion Careful enquiry of exposure to HDS, drugs, OTC drugs* Calculate biochemical pattern of liver injury Search for alternative causes Consider liver biopsy if
Negative or incomplete rechallenge
Acute or chronic atypical presentation†
Autoimmune hepatitis Hepatocellular
R ≥ 5 Mixed
2 > R < 5 Cholestatic
≤ 2 Search in hepatotoxicity resources (Liver tox)<br>
slide30. Therapy EASL CPG DILI. J Hepatol 2019;70:122261. Toxic liver damage is still an orphan hepatic disease with respect to therapy
Most important initial step in terms of management of suspected DILI is to discontinue the implicated agent<br>
slide31. Management of drug-induced acute liver failure 1. Ostapowitz G, et al. Ann Intern Med 2002;137:947–54; 2. Wei G, et al. J Intern Med 2007;262:393–401. EASL CPG DILI. J Hepatol 2019;70:122261. DILI is the most common cause of acute liver failure in western countries1,2<br>
slide32. Preventing DILI EASL CPG DILI. J Hepatol 2019;70:122261. Pre- and post-marketing surveillance of drugs using liver biochemistry is warranted to decrease the incidence of DILI<br>
slide33. Specific phenotypes: AIH EASL CPG DILI. J Hepatol 2019;70:122261. A number of drugs have been associated with drug-induced AIH
A syndrome that shares many features of idiopathic AIH
In cohorts of cases with the diagnosis of AIH, 29% were considered to be drug-induced
Conversely, drug-induced AIH accounts for 9% of all DILI<br>
slide34. Specific phenotypes: Cancer immunotherapy-induced DILI EASL CPG DILI. J Hepatol 2019;70:122261. Immune checkpoint inhibitors act by increasing anti-tumour immune response supressed in cancer
The break in tumour tolerance is associated with inflammatory side effects and an increase in immune-related adverse events, including hepatotoxicity<br>
slide35. Specific phenotypes: Secondary sclerosing cholangitis 1. Gudnason HO, et al. Dig Liver Dis 2015;47:502–7.
EASL CPG DILI. J Hepatol 2019;70:122261. Strictures of the bile tract may result from ischaemia or drug toxicity1<br>
slide36. Specific phenotypes: Granulomatous hepatitis 1. Drebber U, et al. Liver Int 2008;28:828–34.
EASL CPG DILI. J Hepatol 2019;70:122261. Hepatic granulomas are reported in 2–15% of liver biopsies1
Of those with granulomatous hepatitis, 2.5% are considered drug-related<br>
slide37. Specific phenotypes: Acute fatty liver EASL CPG DILI. J Hepatol 2019;70:122261. Rare form of acute hepatotoxicity related to microvesicular steatosis
Manifested with hypoglycaemia, lactic acidosis, hyperammonaemia and cerebral oedema
Dramatically rapid development of organ failure precedes clinical syndrome
With an acute rise in liver enzymes and jaundice
An index of suspicion is crucial in identifying the drug aetiology when approaching a patient with ‘anicteric hepatic encephalopathy’<br>
slide38. Specific phenotypes: Drug-associated fatty liver disease (DAFLD) EASL CPG DILI. J Hepatol 2019;70:122261. NAFLD is associated with accumulation of fat in >5% of hepatocytes
With or without inflammation and fibrosis
In those with moderate or lower alcohol consumption
<21 units in men and <14 units in women, per week
Certain drugs may be one of the aetiologies behind a proportion of ‘secondary’ NAFLD
Cases not associated with characteristic features of metabolic syndrome
Where no risk factors are obvious<br>
slide39. Specific phenotypes: Nodular regenerative hyperplasia 1. Vernier-Massouille G, et al. Gut 2007;56:1404–9. EASL CPG DILI. J Hepatol 2019;70:122261. Drugs can injure endothelial cells of sinusoids and portal venules1
Wide spread vascular changes lead to diffuse nodularity within the hepatic parenchyma
Withdrawal of associated medication has been shown to lead to histological resolution
Otherwise, management is focused on surveillance and prevention of manifestations of portal hypertension<br>
slide40. Specific phenotypes: Liver tumours EASL CPG DILI. J Hepatol 2019;70:122261. Causal association between hormonal therapy and liver tumours is supported by epidemiological data<br>
slide41. Future prospects New biomarkers
Unresolved issues
Unmet needs<br>
slide42. Beyond serum ALT: Exploratory circulating biomarkers for DILI Kullak-Ublick G. DILI Conference XVII, 2017; Session IV. EASL CPG DILI. J Hepatol 2019;70:122261. Hepatocyte Immune cell Necrosis Keratin-18 (CC) Apoptosis GLDH Mitochondrial dysfunction mIr-122 Hepatocyte injury Keratin-18 (FL) HMGB1 ALT HMGB1 HMGB1-acetyl Immune cell activation M-CSF1 Regeneration<br>
slide43. SAFE-T’s new liver safety biomarkers Kullak-Ublick G. DILI Conference XVII, 2017; Session IV. EASL CPG DILI. J Hepatol 2019;70:122261. Nine new liver safety biomarkers supported by the EMA and/or FDA for exploratory use in clinical drug development:<br>
slide44. Unresolved issues and unmet needs EASL CPG DILI. J Hepatol 2019;70:122261. Epidemiology
Big data analysis
Estimates of socioeconomic burden of DILI and its impact on quality of life
Robust case-control or population-based cohort studies to evaluate the risk of HDS- related liver injury, botanical identification and chemical analysis
Pathogenesis
Identify the factors that unmask or prevent liver injury as well as the determinants of severity of DILI in subjects otherwise genetically predisposed
Diagnosis and outcome
Discovery, evaluation and validation of biomarkers, which can distinguish self-resolving elevation of liver enzymes related to drugs from those with a potential to evolve into symptomatic DILI
Better prediction of DILI subjects at risk of ALF, including prognostic biomarkers
Therapy
Randomized controlled trials to evaluate the effect of specific interventions on the clinical outcomes of DILI
Prediction
Algorithms that reliably predict the DILI liability considering drug–host factors<br>