
Eating Disorders 21 November 2013 Krissy Schwerin,










































Description: Eating Disorders 21 November 2013 Krissy Schwerin, MD Child and Adolescent Psychiatrist Canterbury District Health Board South Island Eating Disorders Service Child Adolescent Family Rural Service Overview Anorexia Nervosa (AN) Bulemia
Related Topics
Download Presentation
"Eating Disorders 21 November 2013 Krissy Schwerin," is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Eating Disorders
21 November 2013 Krissy Schwerin, MD
Child and Adolescent Psychiatrist
Canterbury District Health Board
South Island Eating Disorders Service
Child Adolescent & Family Rural Service<br>
slide2. Overview Anorexia Nervosa (AN)
Bulemia Nervosa (BN)
Binge Eating disorder (BED)
Unspecified Feeding or Eating Disorder (UFED)
Other Eating/Feeding problems Diagnosis
Epidemiology
Medical risks
Etiology
Treatment
Prognosis<br>
slide3. Misconceptions Myth: White, upper-middle class females in metropolitan areas of the western world
Eating disorders are increasing in prevalence in males, younger children, older adults, and other ethnic groups.
Our field needs to do a better job screening and treating…<br>
slide4. Case Vignette #1 - Carla Carla is a 13 year-old female who presented to the ER with a grand-mal seizure from hyponatremia. She had been binging on water in order to fend off hunger. Carla had always been a happy child and great student, but had recently become obsessed with her schoolwork and isolated from her friends and close-knit family.
Carla began losing weight after her PMD told her she was overweight. This coincided with a family trip to parents’ country of origin where Carla didn’t like the food. She lost >40 pounds and stopped getting her period<br>
slide5. Anorexia Nervosa (AN) - DSM V Persistent restriction of energy intake leading low weight (lower than minimally expected for age/sex)
Intense fear of gaining weight or becoming fat, or behaviour that interferes with weight gain
Disturbance in body image, undue influence of shape/weight on self-evaluation, lack of recognition of seriousness of low body weight
Restricting sub-type
Binge-eating/purging sub-type **DSM-IV: 1. “refusal” to maintain weight 2. <85 percentile weight
3. amnorrhea was required<br>
slide6. Anorexia Nervosa: chief complaint… Family or school is concerned about eating habits or personality change
Physical symptoms
Other psychological concerns – depression, anxiety, obsessive
“unintentional” weight loss
Amenorrhea
Patient: “I’m fine!”<br>
slide7. Anorexia Nervosa: Risk Factors, Precipitating Factors, & Traits Perfectionism
Early Puberty
Failed attempts to lose weight
Antecedent illness with weight loss
Athletics
Beginning a diet
Family history of eating disorder
Life/family stressors<br>
slide8. Anorexia Nervosa: Epidemiology Lifetime prevalence 0.5-1%
Females:Males 10:1
Usually arises during adolescence or young adulthood
Increased risk in 1st degree biological relatives with AN
1/3 will develop bulimia nervosa
Long-term mortality 10-20%<br>
slide9. Physical Risks Death (suicide, starvation, sudden cardiac death)
Hypometabolic state (bradycardia, hypotension, hypothermia)
Orthostasis
Dehydration
Arrhythmia, heart failure, liver failure
Bone marrow suppression
Malnourishment
Bone loss
Lanugo
Peripheral edema
Stunted growth
Delayed sexual maturity
Hair loss, brittle hair
Cognitive impairment
Water intoxication
Re-feeding syndrome<br>
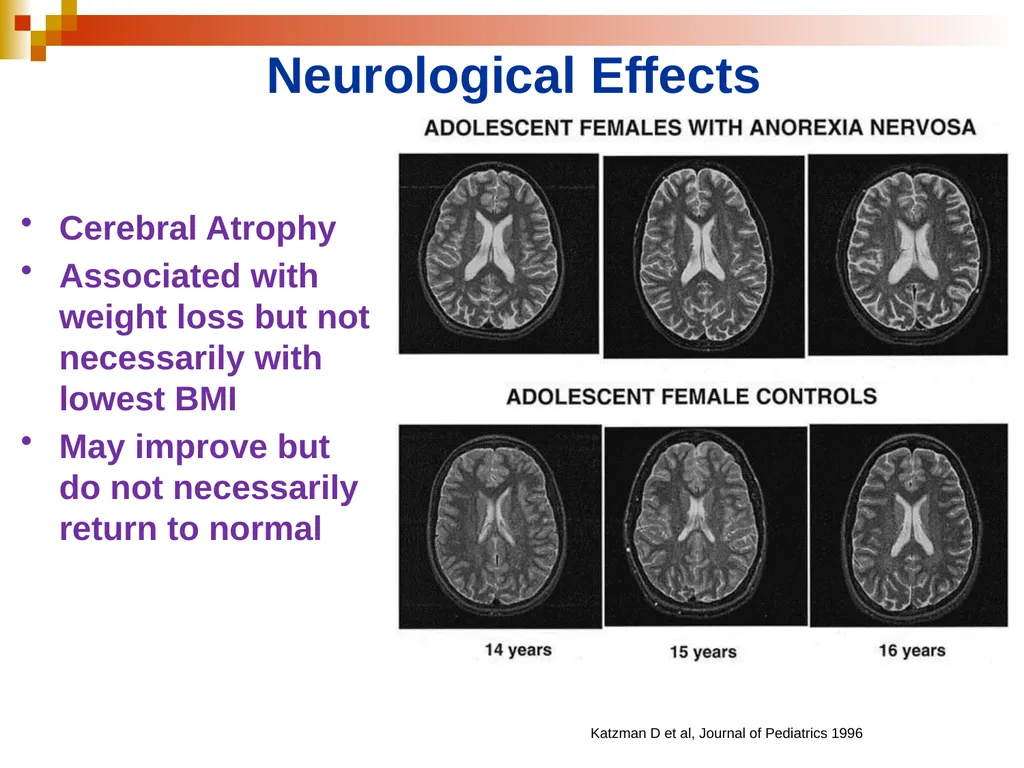
slide10. Neurological Effects Cerebral Atrophy
Associated with weight loss but not necessarily with lowest BMI
May improve but do not necessarily return to normal Katzman D et al, Journal of Pediatrics 1996<br>
slide11. Anorexia Nervosa: Medical Workup Vitals (w/ temperature)
ECG (look for long QTc)
Lytes, CBC, LFTs, ESR, TFTs, CK
β-HCG, LH, FSH, prolactin, estradiol if indicated
Bone density
(don’t be fooled by normal bloods!!!)<br>
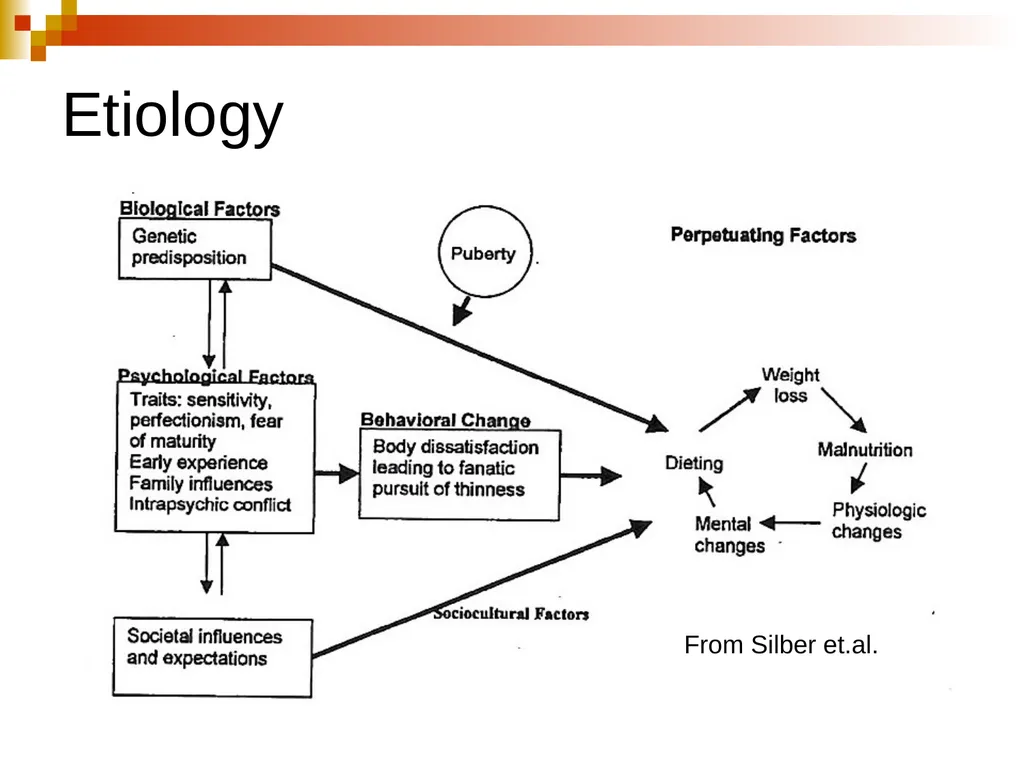
slide12. Etiology From Silber et.al.<br>
slide13. Anorexia Nervosa: Treatment Determine level of care
Inpatient medical stabilization
Inpatient eating disorders service
Outpatient treatment
1st: weight restoration
2nd: psychological
3rd: maintenance (long-term)
Multidisciplinary Team Approach! (psychiatrist, PCP, nurse, psychologist, family therapist, social worker, occupational therapist, dietician)<br>
slide14. Considering Medical Admission <75% ideal body weight
Hypothermia T<35.5 C
Bradycardia HR<50 (peds) or HR <40 (adults)
Orthostasis-drop in sbp >10, increase in HR>35
Dehydration
Potassium < 2.5 or other electrolyte abnormality
Acute medical complication
Delirium
Re-feeding syndrome
Severe depression/suicidality– psychiatric admit<br>
slide15. Anorexia Nervosa: Treatment No evidence-based psychotherapy for Anorexia Nervosa in adults!
No evidence-based pharmacologic treatments in any age!<br>
slide16. Psychological Treatments: Adolescents with AN Family Based Treatment (FBT) (aka “Maudsley Approach”)
no-blame approach, family did not cause anorexia
family is the best resource to help her/him get better
Empower parents to get the young person to eat in order to save his/her life: “intense scene”
Align siblings with the patient for support
“Externalize” the anorexia
Family Meal (Session #2)
Focus on weight restoration first
then explore the family dynamics and psychological issues that may get in the way of maintaining weight<br>
slide17. Psychological Treatments: Adults with AN None are “evidence-based”
We use…
Motivational Interviewing
Cognitive Behavioural Therapy (CBT)
Supportive Psychotherapy
Metacognitive Therapy
Couples or Family Therapy, or family involvement
Psychodynamic Therapy
Interpersonal Therapy (IPT)
Group Therapy<br>
slide18. Anorexia Nervosa: Medications No approved medication treatments for Anorexia Nervosa
Fluoxetine (or other SSRI) for co-morbid depression or anxiety
Growing evidence for low-dose atypical antipsychotics (Olanzapine) for obsessive ruminations and possibly weight gain (still off-label)<br>
slide19. Re-feeding Syndrome Metabolic abnormalities as a result of reinstating nutrition to patients who are malnourished
Potentially fatal
Low phosphate
Edema
Tachycardia
Hypoglycemia (hyperinsulinemic response)
Treatment
admit
replace phosphate
higher protein: carbohydrate ratio<br>
slide20. Anorexia Nervosa: Prognosis 1/3 recover
1/3 continue with milder course
1/3 chronic severe
Young age of onset, short time since onset of illness: very good prognosis
>7 years of illness, very unlikely recovery (but not zero!!!)<br>
slide21. Case Vignette #2: Katie Katie is a 20 year-old University student who had been in therapy for anxiety, self-harm, and a prior trauma that occurred in early adolescence. One session Katie revealed to her therapist that she had an embarrassing secret that she wanted to disclose. She had been bingeing and purging multiple time per week throughout the course of treatment. For years she had gone to great lengths to hide this from roomates/family, going to extents of hiding bags of vomit in the outside rubbish. She finally decided to tell her therapist and ask for help, because after years of being under 130 pounds, her weight has now increased to 134 pounds and she thinks her body is “disgusting”. Current BMI is 22.<br>
slide22. Bulemia Nervosa (BN)– DSM V Recurrent episodes of binge eating (eating larger amounts of food than others would eat in a discrete- 2 hour- period of time, with a sense of lack of control)
recurrent episodes of compensatory behavior (vomiting, laxatives, diuretics, excessive exercise)
Both occur at least 1x/week for 3 months
Self-evaluation is unduly influenced by body shape or weight
Does not occur exclusively during episodes of Anorexia Nervosa **DSM-IV: compensatory episodes had to be 2x/week<br>
slide23. Bulemia Nervosa: Risk Factors, Precipitating Factors, & Traits Often normal weight or overweight (easy to forget to screen for eating disorders!)
Shame and guilt
History of sexual abuse not uncommon
Impulsivity, risk-taking behaviours
Depression/anxiety, emotional dysregulation, self-harm
Less denial compared to AN, but may go to great lengths to keep symptoms secret<br>
slide24. Bulemia Nervosa: Epidemiology Lifetime Prevalence
1.5% women
0.5% men
Prevalence of binge-purge behaviors:
13% girls
7% boys
Slightly older average age of onset compared to Anorexia Nervosa
Purging extremely rare in children<br>
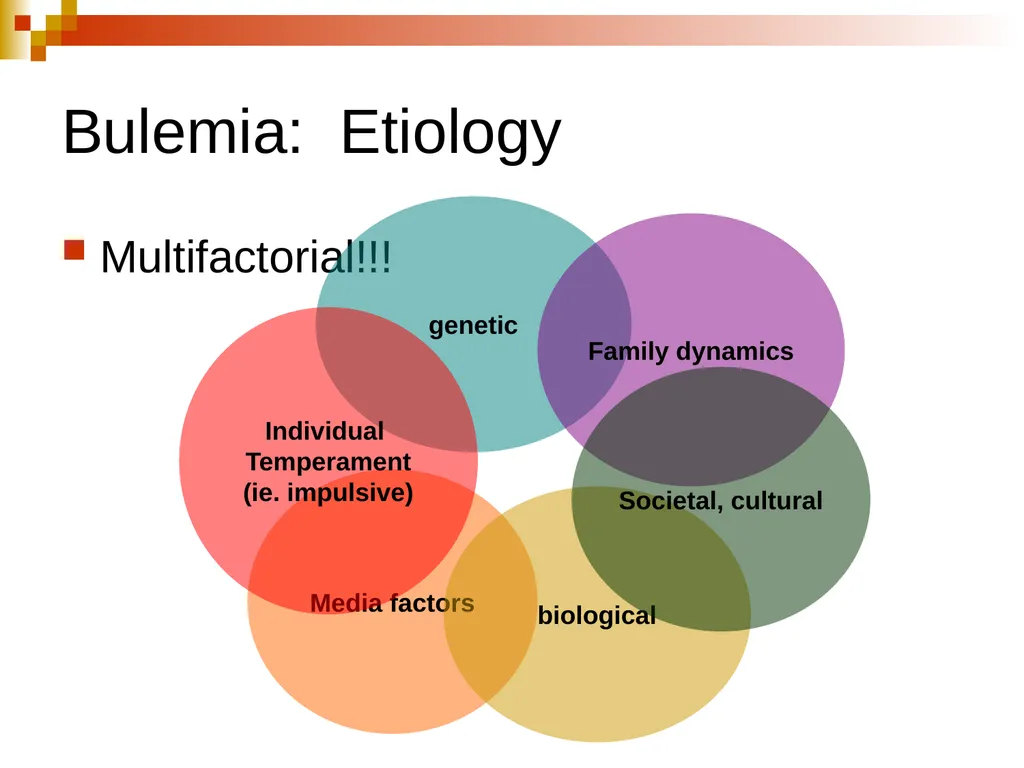
slide25. Bulemia: Etiology Multifactorial!!! Media factors genetic Individual
Temperament
(ie. impulsive) biological Family dynamics Societal, cultural<br>
slide26. Medical Risks Electrolyte abnormalities (hypokalemia, ketosis)
Dental – loss of enamel, chipped teeth, cavities
Parotid hypertrophy
Conjunctival hemorrhages
Calluses on dorsal side of hand (Russell’s sign)
Esophagitis, Mallory-weiss tears, Barrett esophagus
hematemesis
Latxative-dependent: cathartic colon, melena, rectal prolapse
Elevated CK or other injuries (over-exercising)
Poor nutrition (if severe purging)
Edema upon cessation of purging<br>
slide27. Bulemia Nervosa: Treatment Again, multidisciplinary team!!!
Adults:
Best evidence: Cognitive Behavioural Therapy (CBT) + Antidepressant (SSRI)
Adolescents
Evidence for adolescents is sparse; we extrapolate from the evidence for adult treatment
CBT + SSRI
or Family-Based Treatment (FBT) modified for BN (good evidence, but not as good as for AN)<br>
slide28. Bulemia Nervosa: CBT or DBT Best evidence is for CBT or DBT (good outcomes, but outcomes are short-term)
Cognitive Behavioral Therapy (CBT)
Thought Challenging: “I will gain weight if I eat normal amounts of food.”
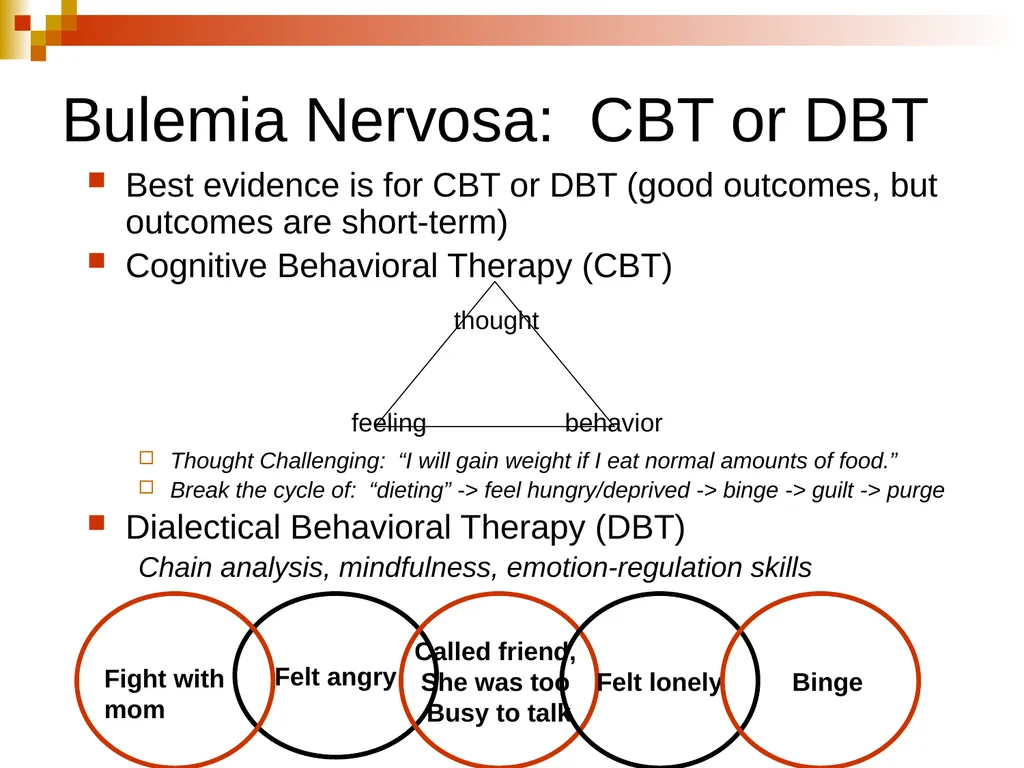
Break the cycle of: “dieting” -> feel hungry/deprived -> binge -> guilt -> purge
Dialectical Behavioral Therapy (DBT)
Chain analysis, mindfulness, emotion-regulation skills Felt angry Called friend,
She was too
Busy to talk Felt lonely Binge Fight with
mom thought feeling behavior<br>
slide29. Bulemia: Other Therapies Family Therapy and/or family involvement
Interpersonal therapy (IPT) (short-term treatment focused on life transitions)
Psychodynamic Psychotherapy (good for long-term results in people with chronic depressive and personality symptoms)
Psychotherapy for comorbidities<br>
slide30. Bulemia Nervosa: Medications High-dose Fluoxetine (SSRI) – very good evidence!
Sertraline (SSRI) – some good evidence
Topiramate (mood stabalizer, promotes weight loss) – some good evidence, but use with caution especially if low-weight
Remember: Buproprion (other antidepressant) is contraindicated! (risk of seizures if history of purging)<br>
slide31. Bulemia: Prognosis 33% remit every year
But another 33% relapse into full criteria
Adolescent-onset better prognosis than adult-onset
Death-rate = 1%<br>
slide32. Case Vignette #3 - Laura Laura is a 47 year-old divorced female in treatment for depression. She has suffered from morbid obesity ever since she stopped using cocaine 13 years ago. When Laura’s teenage son (who is involved in an inner-city gang) does not come home on time, or when she feels empty and lonely about not having a romantic relationship, she eats excessive amounts of food, despite her mindset and efforts throughout the rest of the day to watch her diet. Laura visits multiple different fast-food restaurants in succession and in neighborhoods far from home, so that this behavior will not get noticed by others. Laura one of 7 siblings. She is always identified as the “strong” one in the family who will take care of others who are ailing.<br>
slide33. Binge Eating Disorder (BED) – DSM V Recurrent episodes of binge eating
Eating definitely more than most people would eat in discrete 2-hour period of time
Sense of lack of control during the episode
Three or more of the following:
Eating much more rapidly than normal
Eating until uncomfortably full
Eating large amounts when not physically hungry
Eating alone because embarrassed by how much eating
Feeling disgusted, depressed, or guilty afterwards
Marked distress regarding binge eating
On average at least once a week for 3 months
No compensatory behaviours such as in bulemia nervosa **DSM IV: Binge-eating disorder was only in the appendix, frequency of binge episodes was >2x/week<br>
slide34. Binge Eating Disorder vs. Obesity Binge Eating Disorder: may be overweight, but not required for diagnosis
Binge Eating Disorder: more subjective distress about episodes of over-eating compared to obese non-BED<br>
slide35. Binge Eating Disorder: Epidemiology Most common eating disorder
Lifetime prevalence:
3.5% women
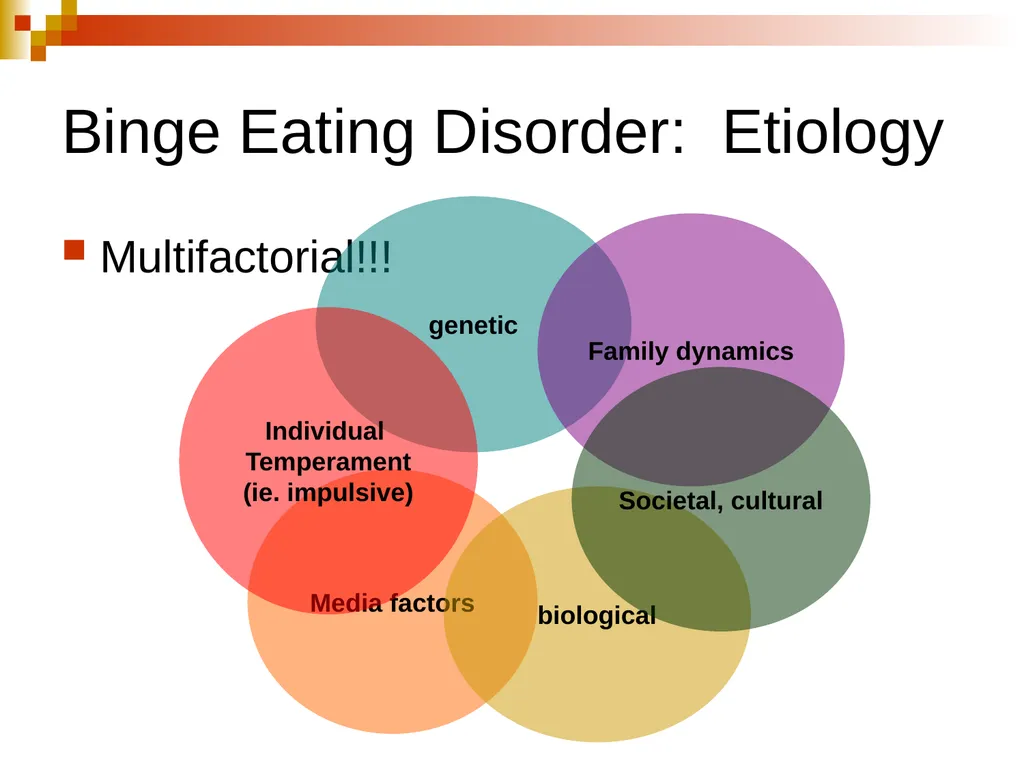
2% men<br>
slide36. Binge Eating Disorder: Etiology Multifactorial!!! Media factors genetic Individual
Temperament
(ie. impulsive) biological Family dynamics Societal, cultural<br>
slide37. Binge Eating Disorder: Treatment (Medication) SSRI
high dose reduces binge behavior short-term
but doesn’t help weight loss
Topiramate, Zonisamide (anticonvulsants, mild mood stabalizer)
Helps binge reduction
Helps weight loss
Caution for adverse effects, high discontinuation rates<br>
slide38. Binge Eating Disorder: Treatment (Therapy) Therapies either prioritize…
Weight loss
Binge-reduction
Neither (ie. relationships, depression etc)
Group psychotherapy
There is little evidence that obese individuals who binge should receive different therapy than obese individuals who do not binge<br>
slide39. Binge Eating Disorder: Psychosocial Support Family may need help with co-dependency
Attachment approach, particularly with youth
Weight loss programs
12-step self-help groups (addressing the problem as an addiction)
Food Addicts in Recovery Anonymous<br>
slide40. Case Vignette #4: Alisa Alisa is an 8 year-old girl who was admitted to the hospital for malnutrition. She had stopped eating due to a subjective sense of stomach pain every time she ate. Nasogastric feedings were initiated, and Alisa underwent a complete GI workup which was negative for a medical cause for her pain. Her parents had difficulty accepting that there may be a psychological component to her illness. Parents were divorced, with a high level of post-divorce conflict. Alisa’s older brother had low-functioning Autistic Spectrum Disorder with behavior/aggression problems, and the family were always impressed with Alisa’s resilience. Alisa denied body image distortion or desire for weight loss.<br>
slide41. Other Eating/Feeding Disorders DSM V Pica- eating non-nutritive substances
Rumination Disorder- chewing/spitting, re-chewing, regurgitating
Avoidant/Restrictive Food Intake Disorder- failure to meet energy/nutritive needs, dependence on enteral feeding or supplements<br>
slide42. Unspecified Feeding or Eating Disorder (UFED) Formerly Eating Disorder NOS (EDNOS) Clinically significant distress/impairment but do not meet criteria for other eating disorders
May be used when not enough clinical information (ie. emergency room settings)
Atypical presentations ** Overall changes in eating disorders are meant to limit the use of this “unspecified” category, which was too large in DSM-IV. (ED-NOS was more common than AN or BN, and actually represented a very “sick” group.)<br>
slide43. Other Feeding Problems in Infancy/Childhood (non-DSM) Selective Eating
Food Phobias
Pervasive Food Refusal
Food Avoidance Emotional Disorder<br>
slide44. Eating Disorders: Take Home Points Great need for provider-awareness (both in mental health and non-mental health)
Very medically risky!!! Need intense psychological AND medical management!
Multifactorial etiology
Multidisciplinary treatment approach
Involve the family in treatment whenever you can
Young patient with new AN cannot afford to wait for FBT
Prevalent in teens, but much less research to guide us in their treatment
Little evidence for medications in EDs: this is why psychiatrists need to be more than med-managers!<br>
slide45. References Hay et.al. “Psychological Treatments for Bulemia Nervosa and Bingeing” The Cochrane Library 2010
Lock, J., “Evaluation of Family Treatment Models for Eating Disorders” Current Opinion in Psychiatry 2011
Lock & LeGrange Treatment Manual for Anorexia Nervosa, Second Edition 2013
Rosen et.al. “Identification and Management of Eating Disorders in Children and Adolescents” Pediatrics 2010
Treasure et.al. “Eating Disorders” Lancet 2010
Vocks et.al. “Meta-Analysis of the Effectiveness of Psychological and Pharmacological Treatments for Binge Eating Disorder” International Journal for Eating Disorders 2010
www.dsm5.org Feeding and Eating Disorders Fact Sheet, American Psychiatric Association 2013<br>
slide46. Any questions? krissy.schwerin@cdhb.health.nz
krissy@schwerno.com<br>
Child and Adolescent Psychiatrist
Canterbury District Health Board
South Island Eating Disorders Service
Child Adolescent & Family Rural Service<br>
slide2. Overview Anorexia Nervosa (AN)
Bulemia Nervosa (BN)
Binge Eating disorder (BED)
Unspecified Feeding or Eating Disorder (UFED)
Other Eating/Feeding problems Diagnosis
Epidemiology
Medical risks
Etiology
Treatment
Prognosis<br>
slide3. Misconceptions Myth: White, upper-middle class females in metropolitan areas of the western world
Eating disorders are increasing in prevalence in males, younger children, older adults, and other ethnic groups.
Our field needs to do a better job screening and treating…<br>
slide4. Case Vignette #1 - Carla Carla is a 13 year-old female who presented to the ER with a grand-mal seizure from hyponatremia. She had been binging on water in order to fend off hunger. Carla had always been a happy child and great student, but had recently become obsessed with her schoolwork and isolated from her friends and close-knit family.
Carla began losing weight after her PMD told her she was overweight. This coincided with a family trip to parents’ country of origin where Carla didn’t like the food. She lost >40 pounds and stopped getting her period<br>
slide5. Anorexia Nervosa (AN) - DSM V Persistent restriction of energy intake leading low weight (lower than minimally expected for age/sex)
Intense fear of gaining weight or becoming fat, or behaviour that interferes with weight gain
Disturbance in body image, undue influence of shape/weight on self-evaluation, lack of recognition of seriousness of low body weight
Restricting sub-type
Binge-eating/purging sub-type **DSM-IV: 1. “refusal” to maintain weight 2. <85 percentile weight
3. amnorrhea was required<br>
slide6. Anorexia Nervosa: chief complaint… Family or school is concerned about eating habits or personality change
Physical symptoms
Other psychological concerns – depression, anxiety, obsessive
“unintentional” weight loss
Amenorrhea
Patient: “I’m fine!”<br>
slide7. Anorexia Nervosa: Risk Factors, Precipitating Factors, & Traits Perfectionism
Early Puberty
Failed attempts to lose weight
Antecedent illness with weight loss
Athletics
Beginning a diet
Family history of eating disorder
Life/family stressors<br>
slide8. Anorexia Nervosa: Epidemiology Lifetime prevalence 0.5-1%
Females:Males 10:1
Usually arises during adolescence or young adulthood
Increased risk in 1st degree biological relatives with AN
1/3 will develop bulimia nervosa
Long-term mortality 10-20%<br>
slide9. Physical Risks Death (suicide, starvation, sudden cardiac death)
Hypometabolic state (bradycardia, hypotension, hypothermia)
Orthostasis
Dehydration
Arrhythmia, heart failure, liver failure
Bone marrow suppression
Malnourishment
Bone loss
Lanugo
Peripheral edema
Stunted growth
Delayed sexual maturity
Hair loss, brittle hair
Cognitive impairment
Water intoxication
Re-feeding syndrome<br>
slide10. Neurological Effects Cerebral Atrophy
Associated with weight loss but not necessarily with lowest BMI
May improve but do not necessarily return to normal Katzman D et al, Journal of Pediatrics 1996<br>
slide11. Anorexia Nervosa: Medical Workup Vitals (w/ temperature)
ECG (look for long QTc)
Lytes, CBC, LFTs, ESR, TFTs, CK
β-HCG, LH, FSH, prolactin, estradiol if indicated
Bone density
(don’t be fooled by normal bloods!!!)<br>
slide12. Etiology From Silber et.al.<br>
slide13. Anorexia Nervosa: Treatment Determine level of care
Inpatient medical stabilization
Inpatient eating disorders service
Outpatient treatment
1st: weight restoration
2nd: psychological
3rd: maintenance (long-term)
Multidisciplinary Team Approach! (psychiatrist, PCP, nurse, psychologist, family therapist, social worker, occupational therapist, dietician)<br>
slide14. Considering Medical Admission <75% ideal body weight
Hypothermia T<35.5 C
Bradycardia HR<50 (peds) or HR <40 (adults)
Orthostasis-drop in sbp >10, increase in HR>35
Dehydration
Potassium < 2.5 or other electrolyte abnormality
Acute medical complication
Delirium
Re-feeding syndrome
Severe depression/suicidality– psychiatric admit<br>
slide15. Anorexia Nervosa: Treatment No evidence-based psychotherapy for Anorexia Nervosa in adults!
No evidence-based pharmacologic treatments in any age!<br>
slide16. Psychological Treatments: Adolescents with AN Family Based Treatment (FBT) (aka “Maudsley Approach”)
no-blame approach, family did not cause anorexia
family is the best resource to help her/him get better
Empower parents to get the young person to eat in order to save his/her life: “intense scene”
Align siblings with the patient for support
“Externalize” the anorexia
Family Meal (Session #2)
Focus on weight restoration first
then explore the family dynamics and psychological issues that may get in the way of maintaining weight<br>
slide17. Psychological Treatments: Adults with AN None are “evidence-based”
We use…
Motivational Interviewing
Cognitive Behavioural Therapy (CBT)
Supportive Psychotherapy
Metacognitive Therapy
Couples or Family Therapy, or family involvement
Psychodynamic Therapy
Interpersonal Therapy (IPT)
Group Therapy<br>
slide18. Anorexia Nervosa: Medications No approved medication treatments for Anorexia Nervosa
Fluoxetine (or other SSRI) for co-morbid depression or anxiety
Growing evidence for low-dose atypical antipsychotics (Olanzapine) for obsessive ruminations and possibly weight gain (still off-label)<br>
slide19. Re-feeding Syndrome Metabolic abnormalities as a result of reinstating nutrition to patients who are malnourished
Potentially fatal
Low phosphate
Edema
Tachycardia
Hypoglycemia (hyperinsulinemic response)
Treatment
admit
replace phosphate
higher protein: carbohydrate ratio<br>
slide20. Anorexia Nervosa: Prognosis 1/3 recover
1/3 continue with milder course
1/3 chronic severe
Young age of onset, short time since onset of illness: very good prognosis
>7 years of illness, very unlikely recovery (but not zero!!!)<br>
slide21. Case Vignette #2: Katie Katie is a 20 year-old University student who had been in therapy for anxiety, self-harm, and a prior trauma that occurred in early adolescence. One session Katie revealed to her therapist that she had an embarrassing secret that she wanted to disclose. She had been bingeing and purging multiple time per week throughout the course of treatment. For years she had gone to great lengths to hide this from roomates/family, going to extents of hiding bags of vomit in the outside rubbish. She finally decided to tell her therapist and ask for help, because after years of being under 130 pounds, her weight has now increased to 134 pounds and she thinks her body is “disgusting”. Current BMI is 22.<br>
slide22. Bulemia Nervosa (BN)– DSM V Recurrent episodes of binge eating (eating larger amounts of food than others would eat in a discrete- 2 hour- period of time, with a sense of lack of control)
recurrent episodes of compensatory behavior (vomiting, laxatives, diuretics, excessive exercise)
Both occur at least 1x/week for 3 months
Self-evaluation is unduly influenced by body shape or weight
Does not occur exclusively during episodes of Anorexia Nervosa **DSM-IV: compensatory episodes had to be 2x/week<br>
slide23. Bulemia Nervosa: Risk Factors, Precipitating Factors, & Traits Often normal weight or overweight (easy to forget to screen for eating disorders!)
Shame and guilt
History of sexual abuse not uncommon
Impulsivity, risk-taking behaviours
Depression/anxiety, emotional dysregulation, self-harm
Less denial compared to AN, but may go to great lengths to keep symptoms secret<br>
slide24. Bulemia Nervosa: Epidemiology Lifetime Prevalence
1.5% women
0.5% men
Prevalence of binge-purge behaviors:
13% girls
7% boys
Slightly older average age of onset compared to Anorexia Nervosa
Purging extremely rare in children<br>
slide25. Bulemia: Etiology Multifactorial!!! Media factors genetic Individual
Temperament
(ie. impulsive) biological Family dynamics Societal, cultural<br>
slide26. Medical Risks Electrolyte abnormalities (hypokalemia, ketosis)
Dental – loss of enamel, chipped teeth, cavities
Parotid hypertrophy
Conjunctival hemorrhages
Calluses on dorsal side of hand (Russell’s sign)
Esophagitis, Mallory-weiss tears, Barrett esophagus
hematemesis
Latxative-dependent: cathartic colon, melena, rectal prolapse
Elevated CK or other injuries (over-exercising)
Poor nutrition (if severe purging)
Edema upon cessation of purging<br>
slide27. Bulemia Nervosa: Treatment Again, multidisciplinary team!!!
Adults:
Best evidence: Cognitive Behavioural Therapy (CBT) + Antidepressant (SSRI)
Adolescents
Evidence for adolescents is sparse; we extrapolate from the evidence for adult treatment
CBT + SSRI
or Family-Based Treatment (FBT) modified for BN (good evidence, but not as good as for AN)<br>
slide28. Bulemia Nervosa: CBT or DBT Best evidence is for CBT or DBT (good outcomes, but outcomes are short-term)
Cognitive Behavioral Therapy (CBT)
Thought Challenging: “I will gain weight if I eat normal amounts of food.”
Break the cycle of: “dieting” -> feel hungry/deprived -> binge -> guilt -> purge
Dialectical Behavioral Therapy (DBT)
Chain analysis, mindfulness, emotion-regulation skills Felt angry Called friend,
She was too
Busy to talk Felt lonely Binge Fight with
mom thought feeling behavior<br>
slide29. Bulemia: Other Therapies Family Therapy and/or family involvement
Interpersonal therapy (IPT) (short-term treatment focused on life transitions)
Psychodynamic Psychotherapy (good for long-term results in people with chronic depressive and personality symptoms)
Psychotherapy for comorbidities<br>
slide30. Bulemia Nervosa: Medications High-dose Fluoxetine (SSRI) – very good evidence!
Sertraline (SSRI) – some good evidence
Topiramate (mood stabalizer, promotes weight loss) – some good evidence, but use with caution especially if low-weight
Remember: Buproprion (other antidepressant) is contraindicated! (risk of seizures if history of purging)<br>
slide31. Bulemia: Prognosis 33% remit every year
But another 33% relapse into full criteria
Adolescent-onset better prognosis than adult-onset
Death-rate = 1%<br>
slide32. Case Vignette #3 - Laura Laura is a 47 year-old divorced female in treatment for depression. She has suffered from morbid obesity ever since she stopped using cocaine 13 years ago. When Laura’s teenage son (who is involved in an inner-city gang) does not come home on time, or when she feels empty and lonely about not having a romantic relationship, she eats excessive amounts of food, despite her mindset and efforts throughout the rest of the day to watch her diet. Laura visits multiple different fast-food restaurants in succession and in neighborhoods far from home, so that this behavior will not get noticed by others. Laura one of 7 siblings. She is always identified as the “strong” one in the family who will take care of others who are ailing.<br>
slide33. Binge Eating Disorder (BED) – DSM V Recurrent episodes of binge eating
Eating definitely more than most people would eat in discrete 2-hour period of time
Sense of lack of control during the episode
Three or more of the following:
Eating much more rapidly than normal
Eating until uncomfortably full
Eating large amounts when not physically hungry
Eating alone because embarrassed by how much eating
Feeling disgusted, depressed, or guilty afterwards
Marked distress regarding binge eating
On average at least once a week for 3 months
No compensatory behaviours such as in bulemia nervosa **DSM IV: Binge-eating disorder was only in the appendix, frequency of binge episodes was >2x/week<br>
slide34. Binge Eating Disorder vs. Obesity Binge Eating Disorder: may be overweight, but not required for diagnosis
Binge Eating Disorder: more subjective distress about episodes of over-eating compared to obese non-BED<br>
slide35. Binge Eating Disorder: Epidemiology Most common eating disorder
Lifetime prevalence:
3.5% women
2% men<br>
slide36. Binge Eating Disorder: Etiology Multifactorial!!! Media factors genetic Individual
Temperament
(ie. impulsive) biological Family dynamics Societal, cultural<br>
slide37. Binge Eating Disorder: Treatment (Medication) SSRI
high dose reduces binge behavior short-term
but doesn’t help weight loss
Topiramate, Zonisamide (anticonvulsants, mild mood stabalizer)
Helps binge reduction
Helps weight loss
Caution for adverse effects, high discontinuation rates<br>
slide38. Binge Eating Disorder: Treatment (Therapy) Therapies either prioritize…
Weight loss
Binge-reduction
Neither (ie. relationships, depression etc)
Group psychotherapy
There is little evidence that obese individuals who binge should receive different therapy than obese individuals who do not binge<br>
slide39. Binge Eating Disorder: Psychosocial Support Family may need help with co-dependency
Attachment approach, particularly with youth
Weight loss programs
12-step self-help groups (addressing the problem as an addiction)
Food Addicts in Recovery Anonymous<br>
slide40. Case Vignette #4: Alisa Alisa is an 8 year-old girl who was admitted to the hospital for malnutrition. She had stopped eating due to a subjective sense of stomach pain every time she ate. Nasogastric feedings were initiated, and Alisa underwent a complete GI workup which was negative for a medical cause for her pain. Her parents had difficulty accepting that there may be a psychological component to her illness. Parents were divorced, with a high level of post-divorce conflict. Alisa’s older brother had low-functioning Autistic Spectrum Disorder with behavior/aggression problems, and the family were always impressed with Alisa’s resilience. Alisa denied body image distortion or desire for weight loss.<br>
slide41. Other Eating/Feeding Disorders DSM V Pica- eating non-nutritive substances
Rumination Disorder- chewing/spitting, re-chewing, regurgitating
Avoidant/Restrictive Food Intake Disorder- failure to meet energy/nutritive needs, dependence on enteral feeding or supplements<br>
slide42. Unspecified Feeding or Eating Disorder (UFED) Formerly Eating Disorder NOS (EDNOS) Clinically significant distress/impairment but do not meet criteria for other eating disorders
May be used when not enough clinical information (ie. emergency room settings)
Atypical presentations ** Overall changes in eating disorders are meant to limit the use of this “unspecified” category, which was too large in DSM-IV. (ED-NOS was more common than AN or BN, and actually represented a very “sick” group.)<br>
slide43. Other Feeding Problems in Infancy/Childhood (non-DSM) Selective Eating
Food Phobias
Pervasive Food Refusal
Food Avoidance Emotional Disorder<br>
slide44. Eating Disorders: Take Home Points Great need for provider-awareness (both in mental health and non-mental health)
Very medically risky!!! Need intense psychological AND medical management!
Multifactorial etiology
Multidisciplinary treatment approach
Involve the family in treatment whenever you can
Young patient with new AN cannot afford to wait for FBT
Prevalent in teens, but much less research to guide us in their treatment
Little evidence for medications in EDs: this is why psychiatrists need to be more than med-managers!<br>
slide45. References Hay et.al. “Psychological Treatments for Bulemia Nervosa and Bingeing” The Cochrane Library 2010
Lock, J., “Evaluation of Family Treatment Models for Eating Disorders” Current Opinion in Psychiatry 2011
Lock & LeGrange Treatment Manual for Anorexia Nervosa, Second Edition 2013
Rosen et.al. “Identification and Management of Eating Disorders in Children and Adolescents” Pediatrics 2010
Treasure et.al. “Eating Disorders” Lancet 2010
Vocks et.al. “Meta-Analysis of the Effectiveness of Psychological and Pharmacological Treatments for Binge Eating Disorder” International Journal for Eating Disorders 2010
www.dsm5.org Feeding and Eating Disorders Fact Sheet, American Psychiatric Association 2013<br>
slide46. Any questions? krissy.schwerin@cdhb.health.nz
krissy@schwerno.com<br>