
G BLICK1, E CERRETA-DIAL1, G MANCINI1, A COSENZA1,
DJ
Published · 22 slides · 0 views

1 / 1







Description
G BLICK1, E CERRETA-DIAL1, G MANCINI1, A COSENZA1, L. FANG2 1Health Care Advocates International, Stratford CT USA 2Pharstat, Raleigh, NC USA SSOAX0903LB No Confirmed Virological Failures (CVF) for 144 Weeks When Switching 2-3-4-Drug ART
Related Topics
Share
Embed code
Download this presentation From Below
"G BLICK1, E CERRETA-DIAL1, G MANCINI1, A COSENZA1," is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
01
G BLICK1, E CERRETA-DIAL1, G MANCINI1, A COSENZA1, L. FANG2
1Health Care Advocates International, Stratford CT USA
2Pharstat, Raleigh, NC USA SSOAX0903LB No Confirmed Virological Failures (CVF) for 144 Weeks When Switching 2-/3-/4-Drug ART to DTG/3TC in Heavily Treatment-Experienced PLWHA with Prior M184V/I and Multiple Virological Failures in the Prospective SOLAR-3D Study<br>
02
SUMMARY 2 MAIN QUESTION:
Can you safely and effectively switch adult PLWHA “OFF-LABEL” to a 2DR STR DTG/3TC regimen in the setting of prior virologic failures and history of prior M184V/I? MAIN IMPORTANCE OF FINDINGS?
Why use 3- or 4-drug ART if 2DR does not sacrifice virologic efficacy?
“Less is better”: 2DR does not add short-term safety issues. ?Long-term impact of stopping ABC, TDF, or TAF?
Global financial impact: cost savings of 2DR is enormous in resource-limited and resource-wealthy nations MAIN FINDING:
Neither Prior or Current M184V/I nor history of prior ART virological failures impact the efficacy of switching virologically suppressed adult PLWHA to DTG/3TC through 144 weeks. MAIN IMPORTANCE OF FINDINGS:
Why use 3- or 4-drug ART if 2DR does not sacrifice virologic efficacy?
2DR does not add short-term safety issues. ?Positive long-term metabolic impact of stopping ABC, TDF, or TAF?
Global financial and health impacts: cost savings and potential human morbidity and mortality benefits of 2DR would be enormous in economically developed and developing nations Blick et al. IAS 2024, #SSOAX0903LB<br>
03
BACKGROUND 3 1van Wyk J, et al. TANGO Study. Clin Infect Dis. 2020;71(8):1920-1929. 2Guidelines for the Use of Antiretroviral Agents in Adults and Adolescents with HIV. DHHS. Available at https://clinicalinfo.hiv.gov/sites/default/files/ guidelines/documents/ AdultandAdolescentGL.pdf. Accessed Oct 3, 2021, I31. 3European AIDS Clinical Society. EACS Guidelines Version 10.1, October 2020. Available online: https://www.eacsociety.org/files/guidelines-10.1_30032021_1.pdf. Accessed Oct 3, 2021. 4Rial-Crestelo, et al. J Antimicrob Chemother. 2021 Feb 11;76(3):738-742. 5Madhusudan K, et al. Open Forum Inf Dis. 2023 Nov 10(11), ofad526. 6Blick G et al. IAS2023, OAB0202. 7De Miguel Buckley R, et al. EACS 2023, eP.A.097. 8De Miguel R, et l. CROI 2024, 693.
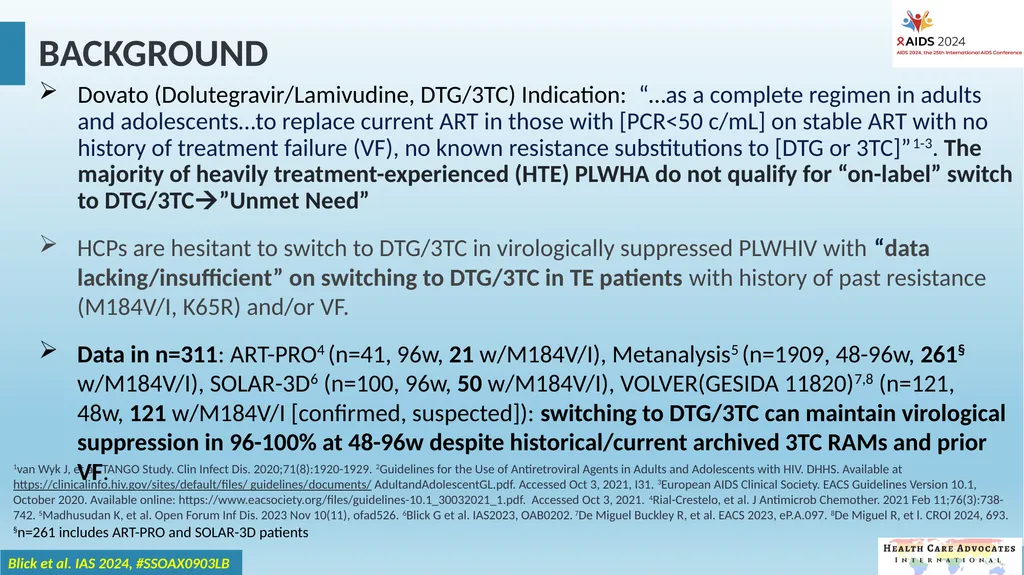
§n=261 includes ART-PRO and SOLAR-3D patients Blick et al. IAS 2024, #SSOAX0903LB Dovato (Dolutegravir/Lamivudine, DTG/3TC) Indication: “…as a complete regimen in adults and adolescents…to replace current ART in those with [PCR<50 c/mL] on stable ART with no history of treatment failure (VF), no known resistance substitutions to [DTG or 3TC]”1-3. The majority of heavily treatment-experienced (HTE) PLWHA do not qualify for “on-label” switch to DTG/3TC”Unmet Need”
HCPs are hesitant to switch to DTG/3TC in virologically suppressed PLWHIV with “data lacking/insufficient” on switching to DTG/3TC in TE patients with history of past resistance (M184V/I, K65R) and/or VF.
Data in n=311: ART-PRO4 (n=41, 96w, 21 w/M184V/I), Metanalysis5 (n=1909, 48-96w, 261§ w/M184V/I), SOLAR-3D6 (n=100, 96w, 50 w/M184V/I), VOLVER(GESIDA 11820)7,8 (n=121, 48w, 121 w/M184V/I [confirmed, suspected]): switching to DTG/3TC can maintain virological suppression in 96-100% at 48-96w despite historical/current archived 3TC RAMs and prior VF.<br>
04
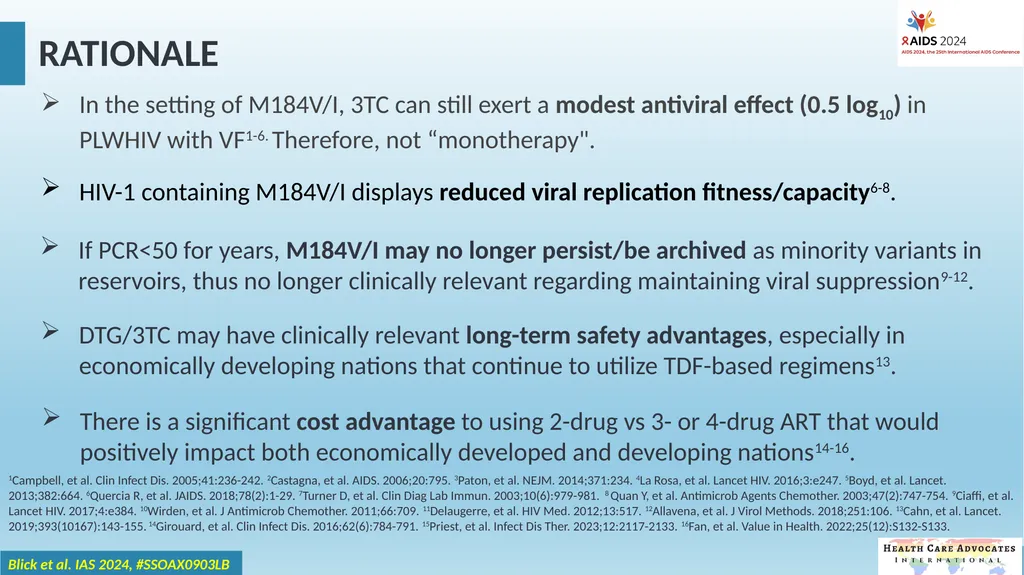
4 RATIONALE If PCR<50 for years, M184V/I may no longer persist/be archived as minority variants in reservoirs, thus no longer clinically relevant regarding maintaining viral suppression9-12. There is a significant cost advantage to using 2-drug vs 3- or 4-drug ART that would positively impact both economically developed and developing nations14-16. DTG/3TC may have clinically relevant long-term safety advantages, especially in economically developing nations that continue to utilize TDF-based regimens13. 1Campbell, et al. Clin Infect Dis. 2005;41:236-242. 2Castagna, et al. AIDS. 2006;20:795. 3Paton, et al. NEJM. 2014;371:234. 4La Rosa, et al. Lancet HIV. 2016;3:e247. 5Boyd, et al. Lancet. 2013;382:664. 6Quercia R, et al. JAIDS. 2018;78(2):1-29. 7Turner D, et al. Clin Diag Lab Immun. 2003;10(6):979-981. 8 Quan Y, et al. Antimicrob Agents Chemother. 2003;47(2):747-754. 9Ciaffi, et al. Lancet HIV. 2017;4:e384. 10Wirden, et al. J Antimicrob Chemother. 2011;66:709. 11Delaugerre, et al. HIV Med. 2012;13:517. 12Allavena, et al. J Virol Methods. 2018;251:106. 13Cahn, et al. Lancet. 2019;393(10167):143-155. 14Girouard, et al. Clin Infect Dis. 2016;62(6):784-791. 15Priest, et al. Infect Dis Ther. 2023;12:2117-2133. 16Fan, et al. Value in Health. 2022;25(12):S132-S133. HIV-1 containing M184V/I displays reduced viral replication fitness/capacity6-8. In the setting of M184V/I, 3TC can still exert a modest antiviral effect (0.5 log10) in PLWHIV with VF1-6. Therefore, not “monotherapy". Blick et al. IAS 2024, #SSOAX0903LB<br>
05
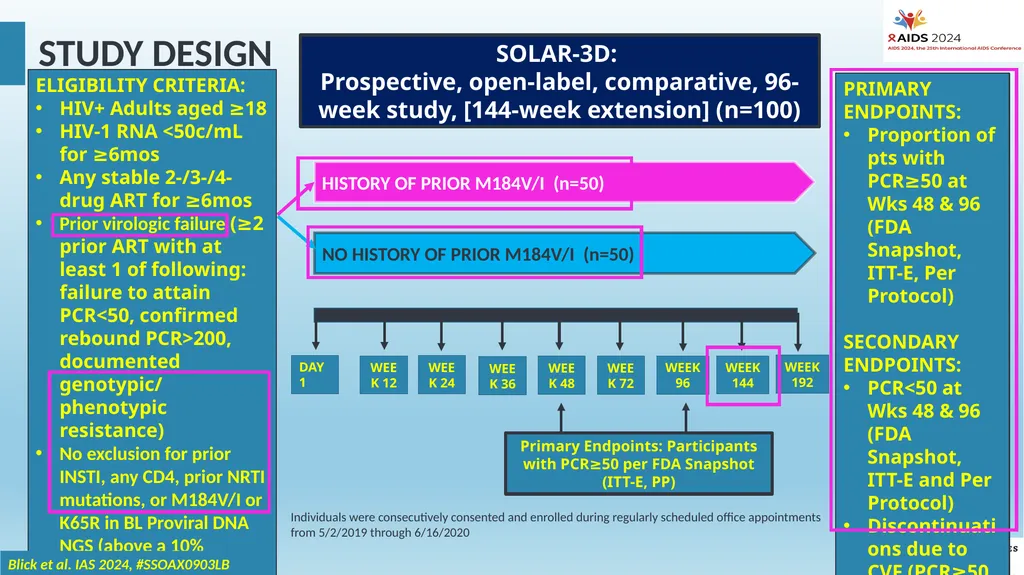
STUDY DESIGN 5 ELIGIBILITY CRITERIA:
HIV+ Adults aged ≥18
HIV-1 RNA <50c/mL for ≥6mos
Any stable 2-/3-/4-drug ART for ≥6mos
Prior virologic failure (≥2 prior ART with at least 1 of following: failure to attain PCR<50, confirmed rebound PCR>200, documented genotypic/ phenotypic resistance)
No exclusion for prior INSTI, any CD4, prior NRTI mutations, or M184V/I or K65R in BL Proviral DNA NGS (above a 10% threshold)
COVID Window +/- 1mo. SOLAR-3D:
Prospective, open-label, comparative, 96-week study, [144-week extension] (n=100) HISTORY OF PRIOR M184V/I (n=50) NO HISTORY OF PRIOR M184V/I (n=50) PRIMARY ENDPOINTS:
Proportion of pts with PCR≥50 at Wks 48 & 96 (FDA Snapshot, ITT-E, Per Protocol)
SECONDARY ENDPOINTS:
PCR<50 at Wks 48 & 96 (FDA Snapshot, ITT-E and Per Protocol)
Discontinuations due to CVF (PCR≥50 followed by PCR>200) DAY 1 WEEK 12 WEEK 24 Primary Endpoints: Participants with PCR≥50 per FDA Snapshot (ITT-E, PP) WEEK 36 WEEK 48 WEEK 72 WEEK 96 WEEK 144 Individuals were consecutively consented and enrolled during regularly scheduled office appointments from 5/2/2019 through 6/16/2020 Blick et al. IAS 2024, #SSOAX0903LB WEEK 192<br>
06
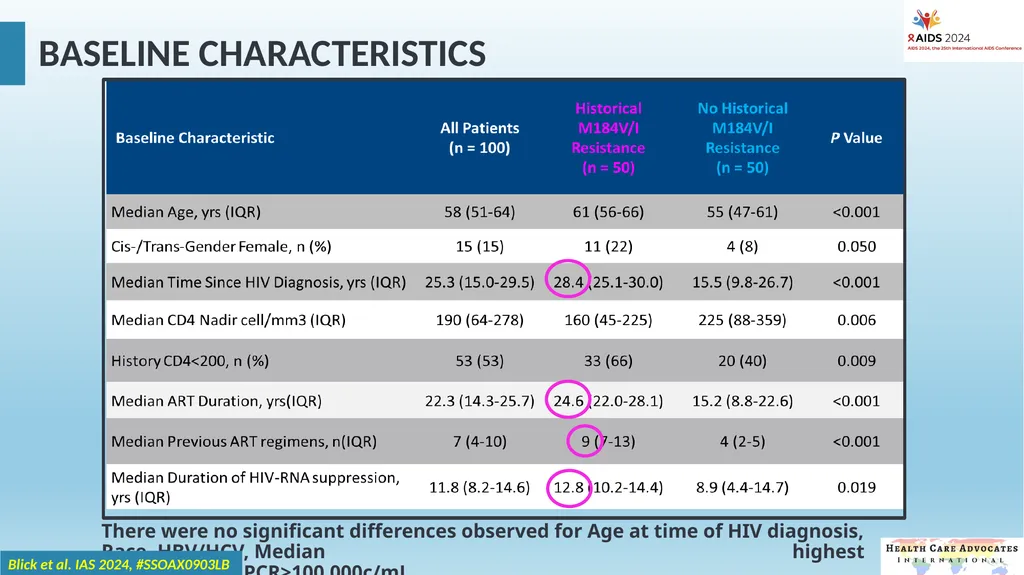
BASELINE CHARACTERISTICS 6 There were no significant differences observed for Age at time of HIV diagnosis, Race, HBV/HCV, Median highest PCR or History PCR>100,000c/mL Blick et al. IAS 2024, #SSOAX0903LB<br>
07
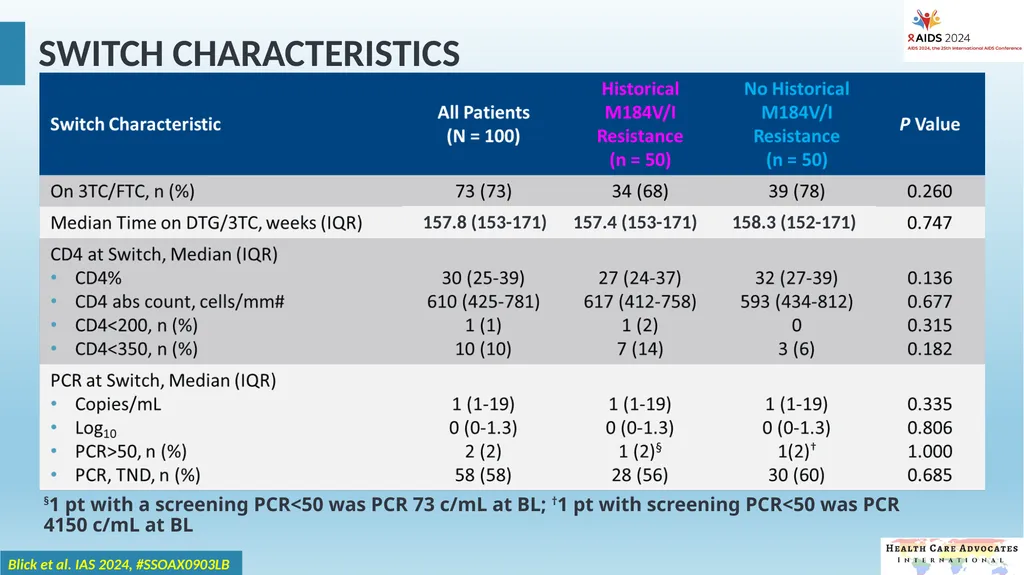
SWITCH CHARACTERISTICS 7 §1 pt with a screening PCR<50 was PCR 73 c/mL at BL; †1 pt with screening PCR<50 was PCR 4150 c/mL at BL 157.8 (153-171) 157.4 (153-171) 158.3 (152-171) Blick et al. IAS 2024, #SSOAX0903LB<br>
08
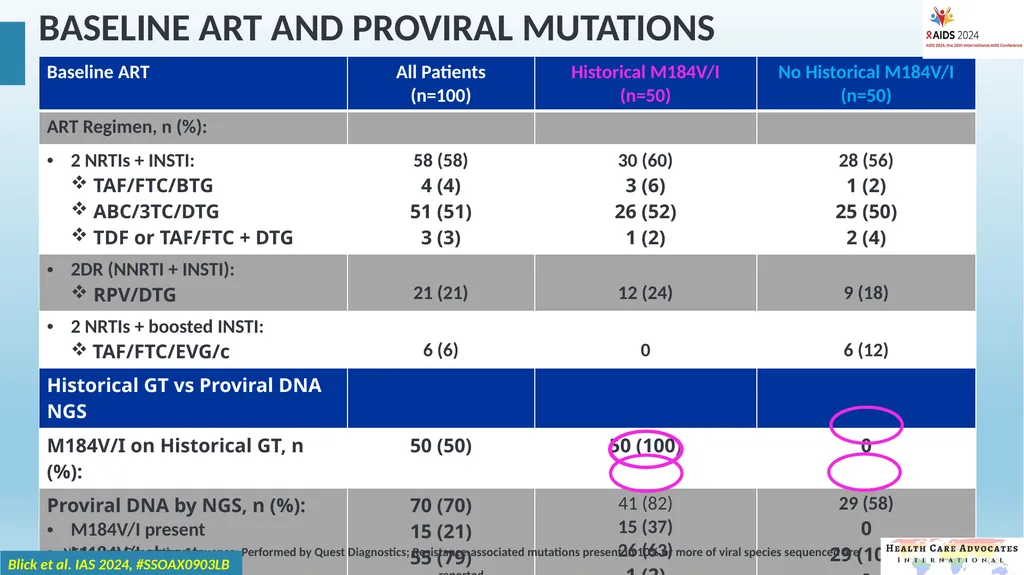
BASELINE ART AND PROVIRAL MUTATIONS 8 NGS = Next-Generation Sequence; Performed by Quest Diagnostics; Resistance-associated mutations present in 10% or more of viral species sequenced are reported Blick et al. IAS 2024, #SSOAX0903LB<br>
09
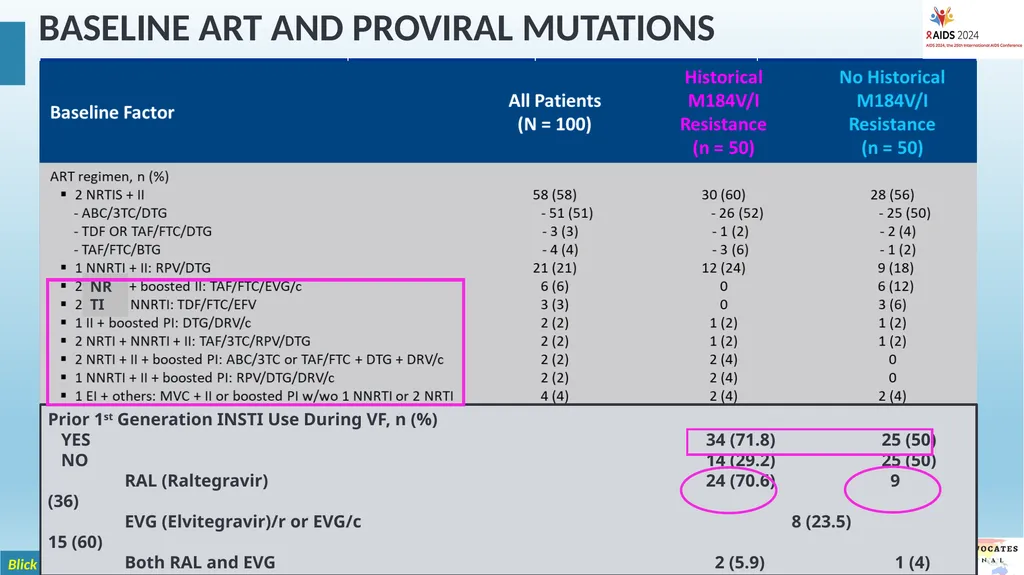
BASELINE ART AND PROVIRAL MUTATIONS 9 NGS = Next-Generation Sequence; Performed by Quest Diagnostics; Resistance-associated mutations present in 10% or more of viral species sequenced are reported Blick et al. IAS 2024, #SSOAX0903LB Prior 1st Generation INSTI Use During VF, n (%)
YES 34 (71.8) 25 (50)
NO 14 (29.2) 25 (50)
RAL (Raltegravir) 24 (70.6) 9 (36)
EVG (Elvitegravir)/r or EVG/c 8 (23.5) 15 (60)
Both RAL and EVG 2 (5.9) 1 (4) NRTI<br>
YES 34 (71.8) 25 (50)
NO 14 (29.2) 25 (50)
RAL (Raltegravir) 24 (70.6) 9 (36)
EVG (Elvitegravir)/r or EVG/c 8 (23.5) 15 (60)
Both RAL and EVG 2 (5.9) 1 (4) NRTI<br>
10
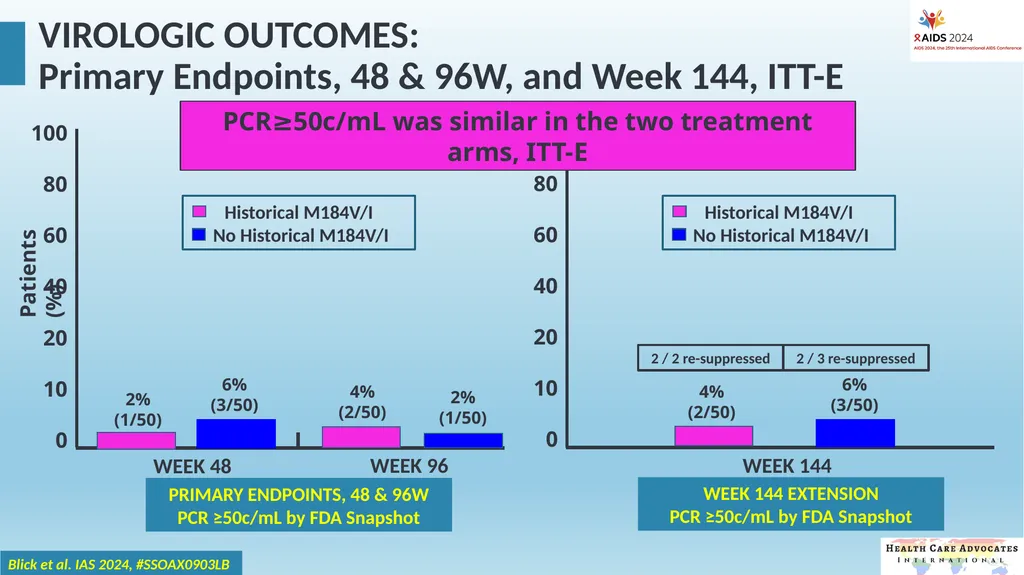
10 VIROLOGIC OUTCOMES:
Primary Endpoints, 48 & 96W, and Week 144, ITT-E 100
80
60
40
20
10
0 WEEK 48 WEEK 96 PRIMARY ENDPOINTS, 48 & 96W
PCR ≥50c/mL by FDA Snapshot Patients (%) 2%
(1/50) 6%
(3/50) 4%
(2/50) 2%
(1/50) Historical M184V/I
No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB 100
80
60
40
20
10
0 WEEK 144 Historical M184V/I
No Historical M184V/I WEEK 144 EXTENSION
PCR ≥50c/mL by FDA Snapshot 4%
(2/50) 6%
(3/50) 2 / 2 re-suppressed 2 / 3 re-suppressed PCR≥50c/mL was similar in the two treatment arms, ITT-E<br>
80
60
40
20
10
0 WEEK 48 WEEK 96 PRIMARY ENDPOINTS, 48 & 96W
PCR ≥50c/mL by FDA Snapshot Patients (%) 2%
(1/50) 6%
(3/50) 4%
(2/50) 2%
(1/50) Historical M184V/I
No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB 100
80
60
40
20
10
0 WEEK 144 Historical M184V/I
No Historical M184V/I WEEK 144 EXTENSION
PCR ≥50c/mL by FDA Snapshot 4%
(2/50) 6%
(3/50) 2 / 2 re-suppressed 2 / 3 re-suppressed PCR≥50c/mL was similar in the two treatment arms, ITT-E<br>
11
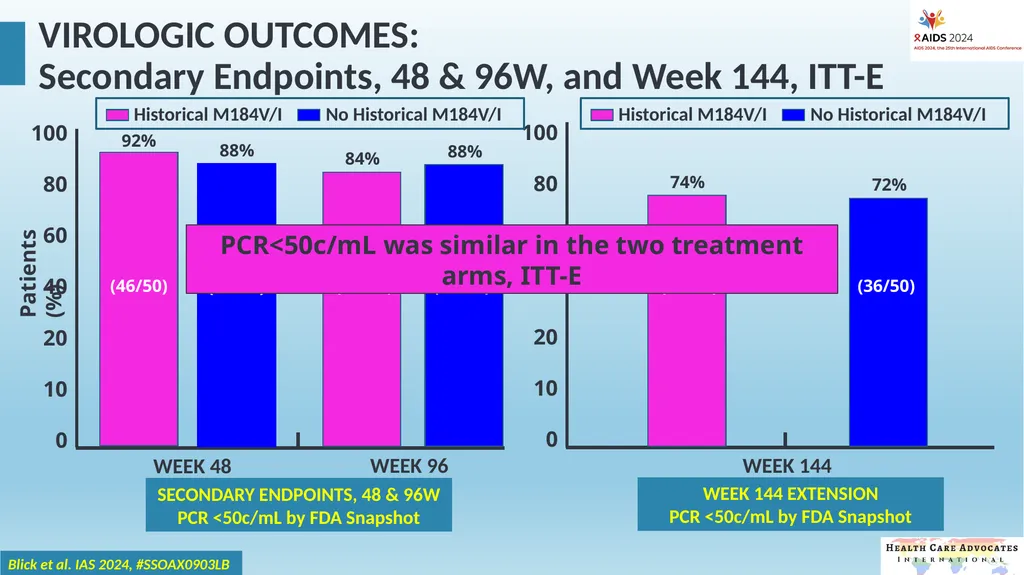
11 VIROLOGIC OUTCOMES:
Secondary Endpoints, 48 & 96W, and Week 144, ITT-E 100
80
60
40
20
10
0 100
80
60
40
20
10
0 WEEK 48 WEEK 96 SECONDARY ENDPOINTS, 48 & 96W
PCR <50c/mL by FDA Snapshot WEEK 144 EXTENSION
PCR <50c/mL by FDA Snapshot Patients (%) 92% 88% (46/50) (44/50) 84% 88% (42/50) (44/50) Historical M184V/I No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB Historical M184V/I No Historical M184V/I 74% (37/50) 72% (36/50) WEEK 144 PCR<50c/mL was similar in the two treatment arms, ITT-E<br>
80
60
40
20
10
0 100
80
60
40
20
10
0 WEEK 48 WEEK 96 SECONDARY ENDPOINTS, 48 & 96W
PCR <50c/mL by FDA Snapshot WEEK 144 EXTENSION
PCR <50c/mL by FDA Snapshot Patients (%) 92% 88% (46/50) (44/50) 84% 88% (42/50) (44/50) Historical M184V/I No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB Historical M184V/I No Historical M184V/I 74% (37/50) 72% (36/50) WEEK 144 PCR<50c/mL was similar in the two treatment arms, ITT-E<br>
12
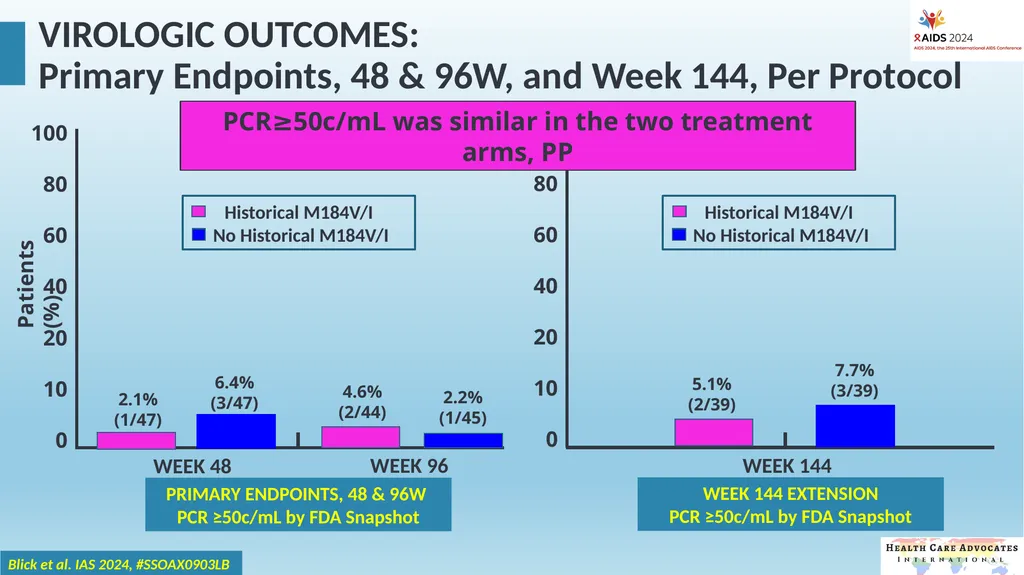
12 VIROLOGIC OUTCOMES:
Primary Endpoints, 48 & 96W, and Week 144, Per Protocol 100
80
60
40
20
10
0 100
80
60
40
20
10
0 WEEK 48 WEEK 96 PRIMARY ENDPOINTS, 48 & 96W
PCR ≥50c/mL by FDA Snapshot WEEK 144 EXTENSION
PCR ≥50c/mL by FDA Snapshot Patients (%) 2.1%
(1/47) 6.4%
(3/47) 4.6%
(2/44) 2.2%
(1/45) Historical M184V/I
No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB WEEK 144 Historical M184V/I
No Historical M184V/I 5.1%
(2/39) 7.7%
(3/39) PCR≥50c/mL was similar in the two treatment arms, PP<br>
80
60
40
20
10
0 100
80
60
40
20
10
0 WEEK 48 WEEK 96 PRIMARY ENDPOINTS, 48 & 96W
PCR ≥50c/mL by FDA Snapshot WEEK 144 EXTENSION
PCR ≥50c/mL by FDA Snapshot Patients (%) 2.1%
(1/47) 6.4%
(3/47) 4.6%
(2/44) 2.2%
(1/45) Historical M184V/I
No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB WEEK 144 Historical M184V/I
No Historical M184V/I 5.1%
(2/39) 7.7%
(3/39) PCR≥50c/mL was similar in the two treatment arms, PP<br>
13
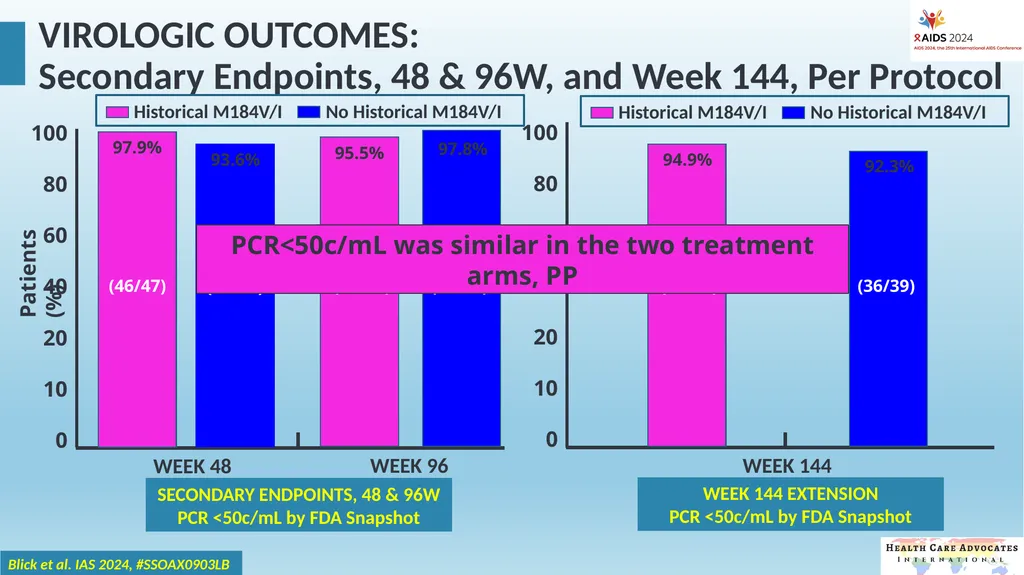
13 VIROLOGIC OUTCOMES:
Secondary Endpoints, 48 & 96W, and Week 144, Per Protocol 100
80
60
40
20
10
0 100
80
60
40
20
10
0 WEEK 48 WEEK 96 SECONDARY ENDPOINTS, 48 & 96W
PCR <50c/mL by FDA Snapshot WEEK 144 EXTENSION
PCR <50c/mL by FDA Snapshot Patients (%) Historical M184V/I No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB Historical M184V/I No Historical M184V/I 94.9% (37/39) 92.3% (36/39) WEEK 144 97.9% 93.6% (46/47) (44/47) 95.5% 97.8% (42/44) (44/45) PCR<50c/mL was similar in the two treatment arms, PP<br>
80
60
40
20
10
0 100
80
60
40
20
10
0 WEEK 48 WEEK 96 SECONDARY ENDPOINTS, 48 & 96W
PCR <50c/mL by FDA Snapshot WEEK 144 EXTENSION
PCR <50c/mL by FDA Snapshot Patients (%) Historical M184V/I No Historical M184V/I Blick et al. IAS 2024, #SSOAX0903LB Historical M184V/I No Historical M184V/I 94.9% (37/39) 92.3% (36/39) WEEK 144 97.9% 93.6% (46/47) (44/47) 95.5% 97.8% (42/44) (44/45) PCR<50c/mL was similar in the two treatment arms, PP<br>
14
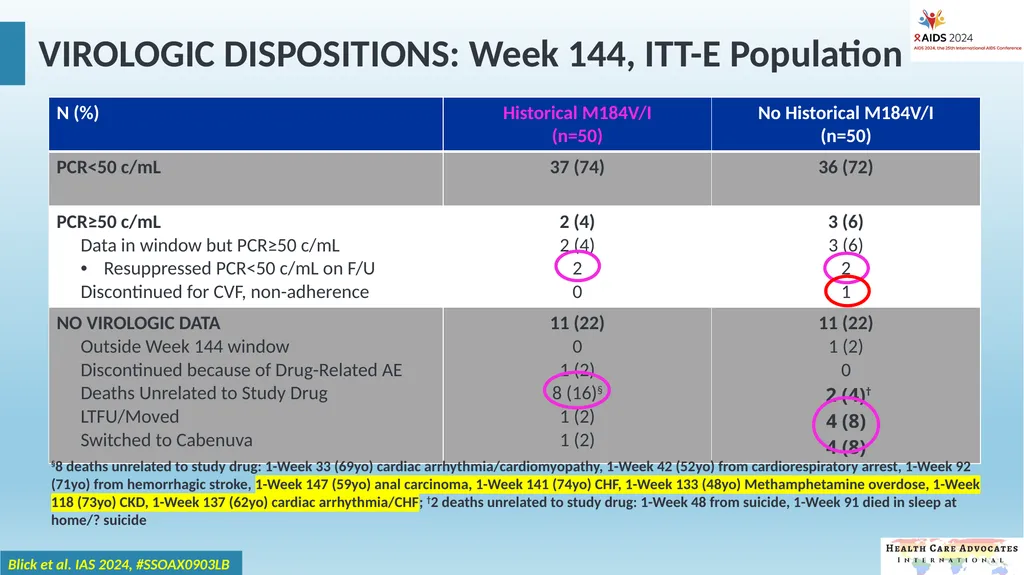
14 VIROLOGIC DISPOSITIONS: Week 144, ITT-E Population §8 deaths unrelated to study drug: 1-Week 33 (69yo) cardiac arrhythmia/cardiomyopathy, 1-Week 42 (52yo) from cardiorespiratory arrest, 1-Week 92 (71yo) from hemorrhagic stroke, 1-Week 147 (59yo) anal carcinoma, 1-Week 141 (74yo) CHF, 1-Week 133 (48yo) Methamphetamine overdose, 1-Week 118 (73yo) CKD, 1-Week 137 (62yo) cardiac arrhythmia/CHF; †2 deaths unrelated to study drug: 1-Week 48 from suicide, 1-Week 91 died in sleep at home/? suicide Blick et al. IAS 2024, #SSOAX0903LB<br>
15
VIROLOGIC FAILURES: Secondary Endpoint, Week 144 15 There were no cases of Confirmed Virologic Failure (CVF)§ in Historical M184VI treatment arm
1 CVF in No Historical M184V/I treatment arm through Week 144, due to non-adherence
There were no cases of Treatment-Emergent Resistance across treatment arms through Week 144 §Confirmed Virologic Failure (CVF) is defined as a PCR≥50 followed by a second consecutive PCR>200 Blick et al. IAS 2024, #SSOAX0903LB<br>
16
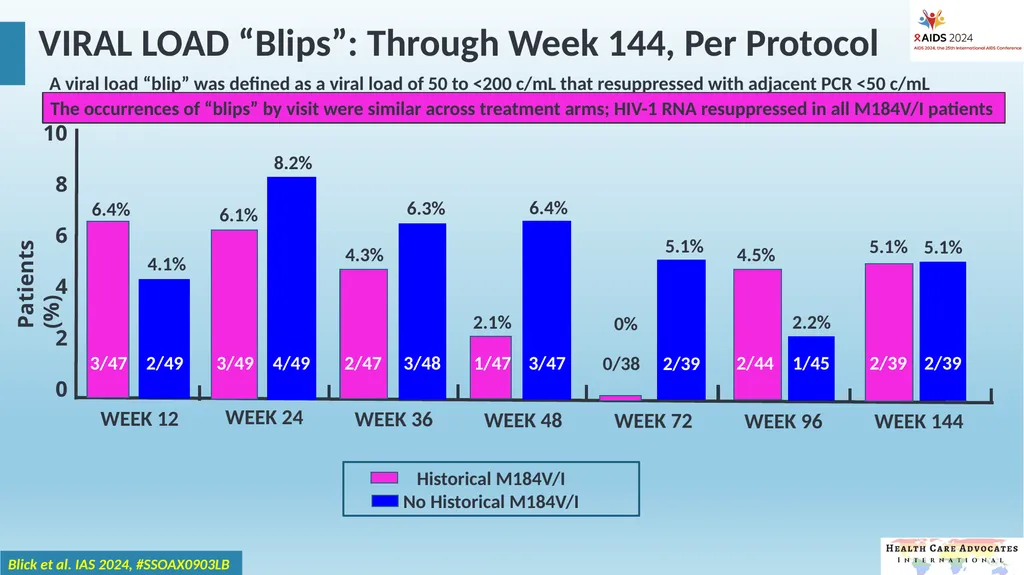
16 VIRAL LOAD “Blips”: Through Week 144, Per Protocol 10
8
6
4
2
0 Patients (%) WEEK 12 WEEK 24 WEEK 36 WEEK 48 WEEK 72 WEEK 96 6.4% 4.1% 6.1% 8.2% 4.3% 6.3% 2.1% 6.4% 0% 4.5% 5.1% 2.2% 3/47 2/49 3/49 4/49 2/47 3/48 1/47 2/44 1/45 2/39 0/38 Historical M184V/I
No Historical M184V/I A viral load “blip” was defined as a viral load of 50 to <200 c/mL that resuppressed with adjacent PCR <50 c/mL Blick et al. IAS 2024, #SSOAX0903LB 3/47 WEEK 144 5.1% 5.1% 2/39 2/39 The occurrences of “blips” by visit were similar across treatment arms; HIV-1 RNA resuppressed in all M184V/I patients<br>
17
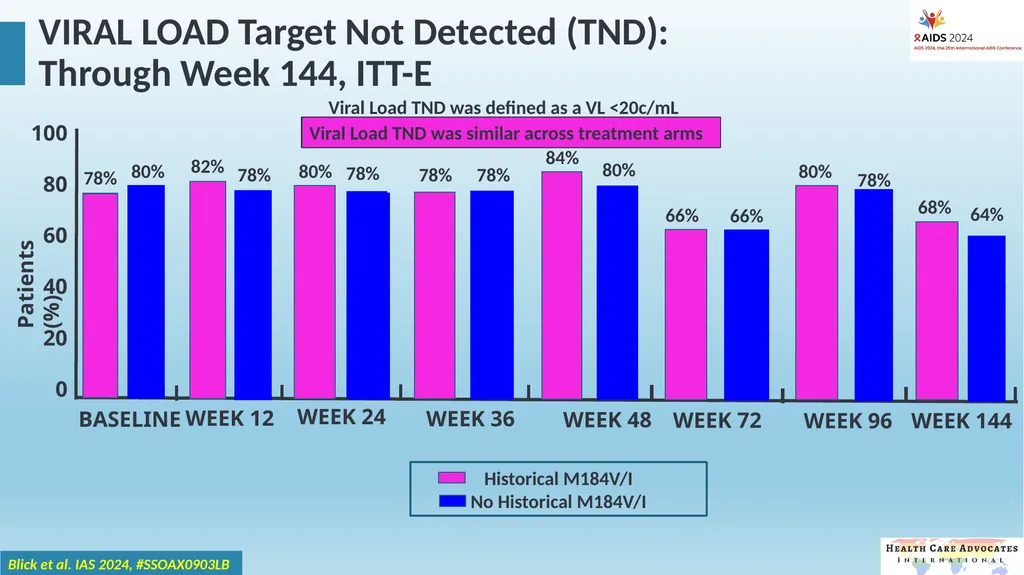
17 VIRAL LOAD Target Not Detected (TND):
Through Week 144, ITT-E 100
80
60
40
20
0 Patients (%) WEEK 12 WEEK 24 WEEK 36 WEEK 48 WEEK 72 WEEK 96 78% 80% 82% 78% 80% 78% 78% 78% 84% 66% 80% 66% Historical M184V/I
No Historical M184V/I Viral Load TND was defined as a VL <20c/mL BASELINE 78% 80% Blick et al. IAS 2024, #SSOAX0903LB 64% 68% WEEK 144 Viral Load TND was similar across treatment arms<br>
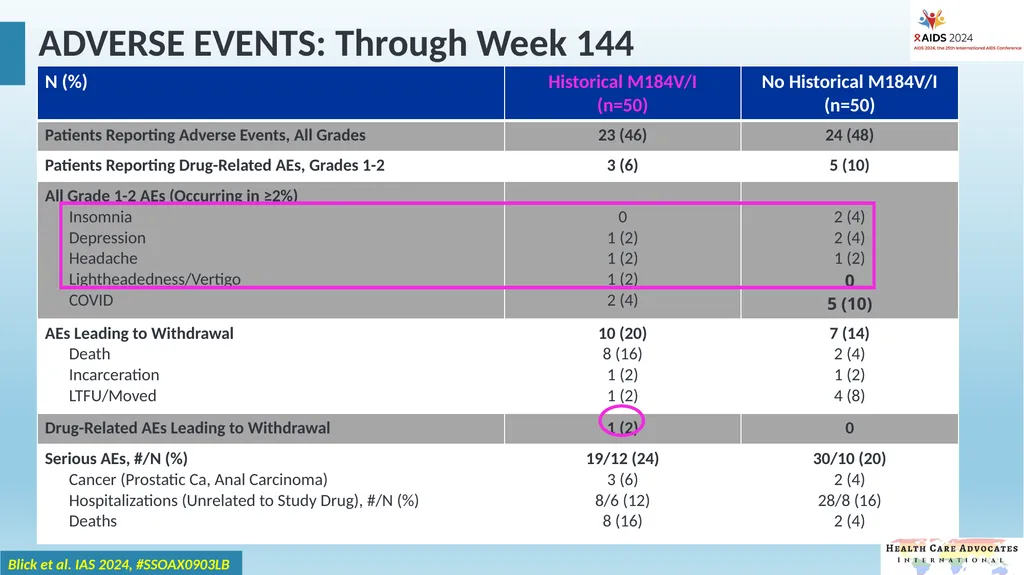
18
18 ADVERSE EVENTS: Through Week 144 Blick et al. IAS 2024, #SSOAX0903LB<br>
19
CONCLUSION SOLAR-3D is the largest prospective, comparative trial with longest follow-up to-date to demonstrate that neither prior/current M184V/I nor multiple prior VFs impact the efficacy and durability of switching virologically suppressed PLWHA to DTG/3TC through 144-weeks. 19 Blick et al. IAS 2024, #SSOAX0903LB<br>
20
LAST THOUGHT 20 Blick et al. IAS 2024, #SSOAX0903LB Switching to STR DTG/3TC must be explored in economically-developing countries in individuals with M184V/I and/or K65R, without DTG-associated RAMs, where economic/safety advantages of discontinuing TDF could be consequential<br>
21
ACKNOWLEDGEMENTS (1) 21 Blick et al. IAS 2024, #SSOAX0903LB In Loving Memory of
Mark Wainberg, PhD
Past President, International AIDS Society (1998-2000),
Internationally Renown HIV/AIDS Researcher, HIV Activist, Global Health, Public Health, Health Promotion & Advocacy, Patient Care, Infectious Disease, Allergy & Immunity, Mentor and Friend Born: April 21, 1945 Died: April 11, 2017 First to identify the antiviral capabilities of 3TC in 1989 and test the drug in patients
Advocate of the impaired viral fitness (VRC) of 3TC-resistant HIV in the setting of M184V/I
“Resistance to 3TC is not really resistance at all”
“3TC can be the key component to a successful 2-drug therapy, even in the presence of M184V/I”<br>
22
ACKNOWLEDGEMENTS (2) To all of our devoted HIV/AIDS patients who consented to take the unknown risk presented by SOLAR-3D design to further our knowledge base in off-label suppressed switch to DTG/3TC
To Health Care Advocates International, LLC for funding SOLAR-3D and investigators and staff for helping to close this research gap
To Lei Fang of Pharstat for his statistical prowess
To Hubby for his assistance and for tolerating 4 years of my OCD conducting SOLAR-3D Blick et al. IAS 2024, #SSOAX0903LB<br>