
INDEX CASE OF GERIATRICS Name of investigator Date













































Description: INDEX CASE OF GERIATRICS Name of investigator Date of investigation GENERAL INFORMATION Name SO Resident of Sex Age Religion with caste Marital status Occupation Family income Social class Education PERSONAL HABITS Dietary habits (a)
Related Topics
Download Presentation
"INDEX CASE OF GERIATRICS Name of investigator Date" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. INDEX CASE OF GERIATRICS<br>
slide2. Name of investigator
Date of investigation<br>
slide3. GENERAL INFORMATION
Name
S/O
Resident of
Sex
Age
Religion with caste
Marital status
Occupation
Family income
Social class
Education<br>
slide4. PERSONAL HABITS Dietary habits (a) Vegetarian (b) Non-vegetarian (c) Lact-ovo-veg.
Smoking (a) No (b) Yes (c) occasional (d) Regular
Type of smoking (e.g. Bidi, Cigarette, Tobacco, Kaini etc.)
Frequency of smoking
Since when smoking (age/duration)
Alcoholic drinks (a) No (b) Yes (c) occasional (d) Regular
Type of drinks
Frequency of drinks
Since when drinking (age/duration)<br>
slide5. 4. Betel chewing (a) No (b) yes (c) occasional (d) Regular
1. with tobacco
2. without tobacco
3. Since when chewing tobacco
4. Frequency of Betel chewing
5. Monthly expenses on
(a) Smoking
(b) Alcoholic drinks
(c) Betel chewing<br>
slide6. C. HISTORY OF PAST ILLNESS (DURING LAST YEAR)
1. Nature of illness 2. Duration 3. Treatment taken at
D. HISTORY OF PRESENT ILLNESS
1.Nature of complaints 2. Duration<br>
slide7. E. FAMILY CONTACTS
1. Name of family member 2. Sex 3. Age 4. Relationship with patient
F. HISTORY OF CONTACT WITH A PATIENT OF SIMILAR ILLNESS BEFORE ONSET OF ILLNESS
1. Family contact
2. Work place contact
3. Neighbourhood contact
4. School contact
5. Village locality contact
6. No history of any contact
7. Any other<br>
slide8. G. HISTORY OF ONSET OF ILLNESS IN HIS CONTACT (DESCRIBE THE NATURE OF CONTACT AND NATURE OF COMPLAINTS IN HIM)<br>
slide9. H. GENERAL EXAMINATION
SYSTEMIC EXAMINATION
Specially abdomen is to be examined for period of gestation and foetal heart sound heard
J. INVESTIGATION DONE<br>
slide10. K. DIAGNOSIS AND MANAGEMENT
(a) Effects of illness on the family (in terms of money and social impact)
(b) Role of physical, Biological & psychological environment in the causation of this illness.
(c) Level of prevention failed in this case.<br>
slide11. L. SUGGEST RECOMMENDATION AT
1. Individual level
2. Family level
3. Community level<br>
slide12. M. SOCIAL THERAPY AND REHABILITATION
1. What should be done for rehabilitation?
2. What can be done to provide
a. Hospital and home treatment
b. Financial assistance
c. Food supplements
d. Housing
e. Vocational training
f. Shelter jobs
g. Better family relation
h. Any other assistance<br>
slide13. CONCLUSION
Source of illness
Circumstances which led to disease
If the disease was preventable
Likely results of the disease
If there any danger of spread of disease to contacts and neighbours.<br>
slide14. INTRODUCTION “Progressive process associated with declines in structure and function, impaired maintenance and repair systems, increased susceptibility to disease and death and reduced reproductive capacity”
GERIATRICS- “branch which deals with health care of aging people.
GERONTOLOGY- Study of physical, biological, psychological and sociological changes which are incident to old age.
SENILITY- Physical and mental weakness associated with old age
SENESCENCE- Process of growing old.<br>
slide15. UNO defines old age as “person who is more than 60 years of age”
1999 Jan. “ National policy on older persons” GOI adopted “Senior Citizen” or “elderly”as a person who is 60 years of age or above.
60-74- “Young old”
75-84 – “ Middle old”
Above 85- “oldest old” or “infirm”<br>
slide16. COMMON GERIATRIC HEALTH PROBLEMS Normal aging- no symptoms.
Abrupt decline in function-pathological not due to aging.
Multi-factorial process depends upon amount of care, consumed diet, environmental factors, personal habits, genetic factors and neglect of body in previous years.<br>
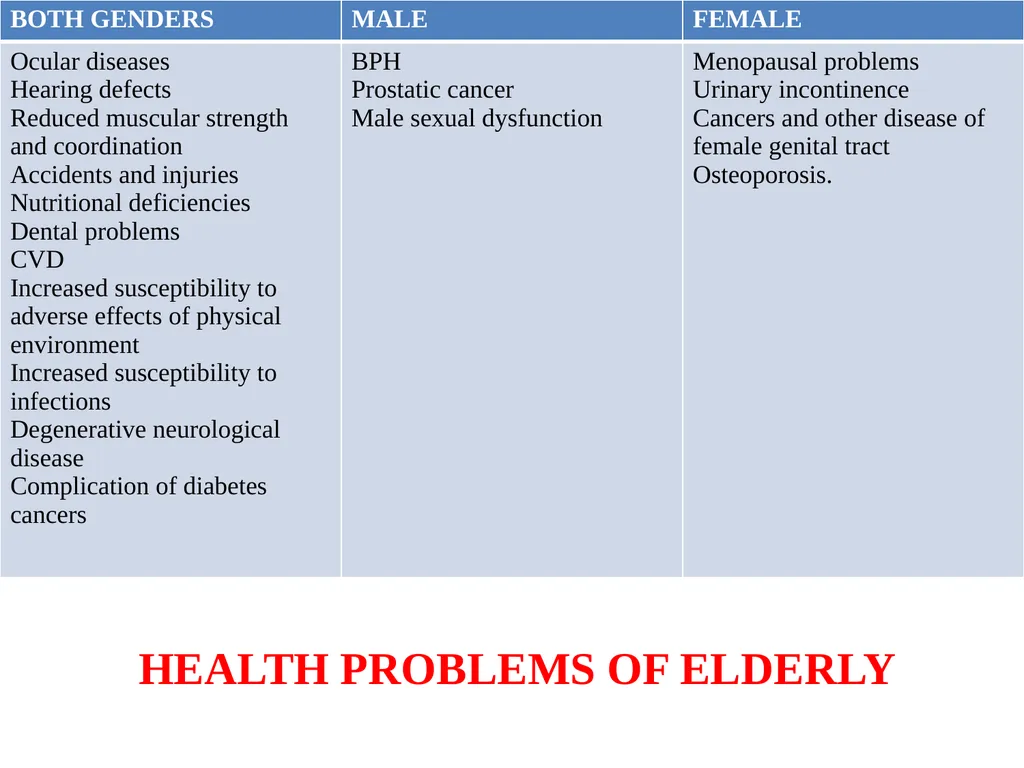
slide17. HEALTH PROBLEMS OF ELDERLY<br>
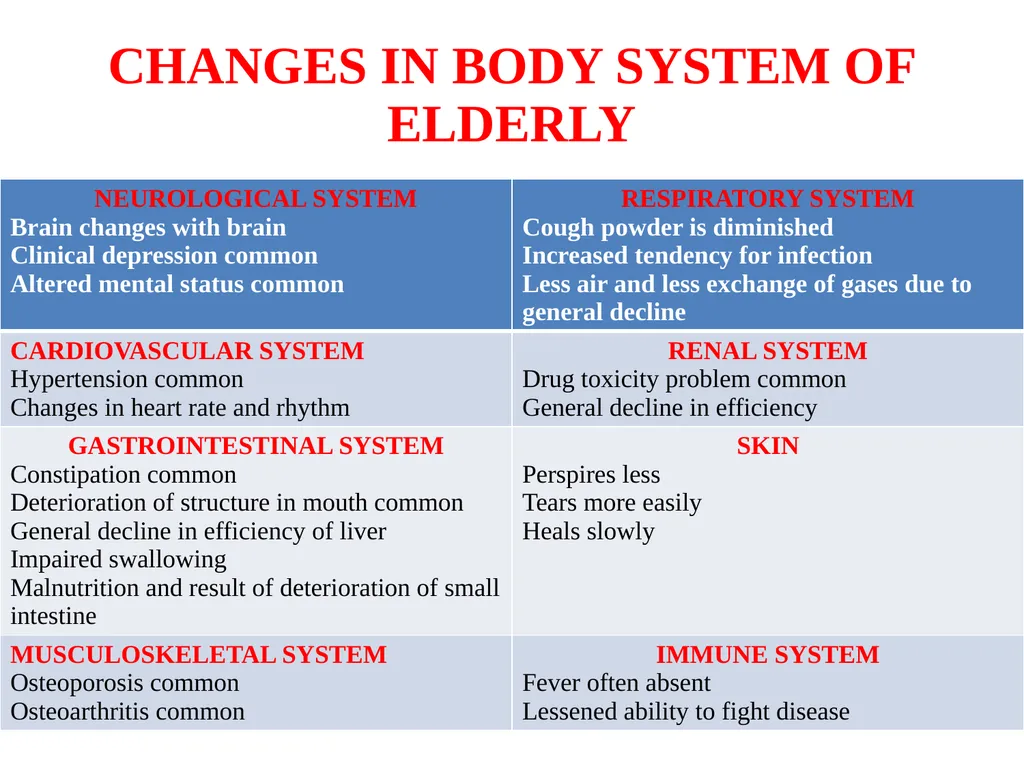
slide18. CHANGES IN BODY SYSTEM OF ELDERLY<br>
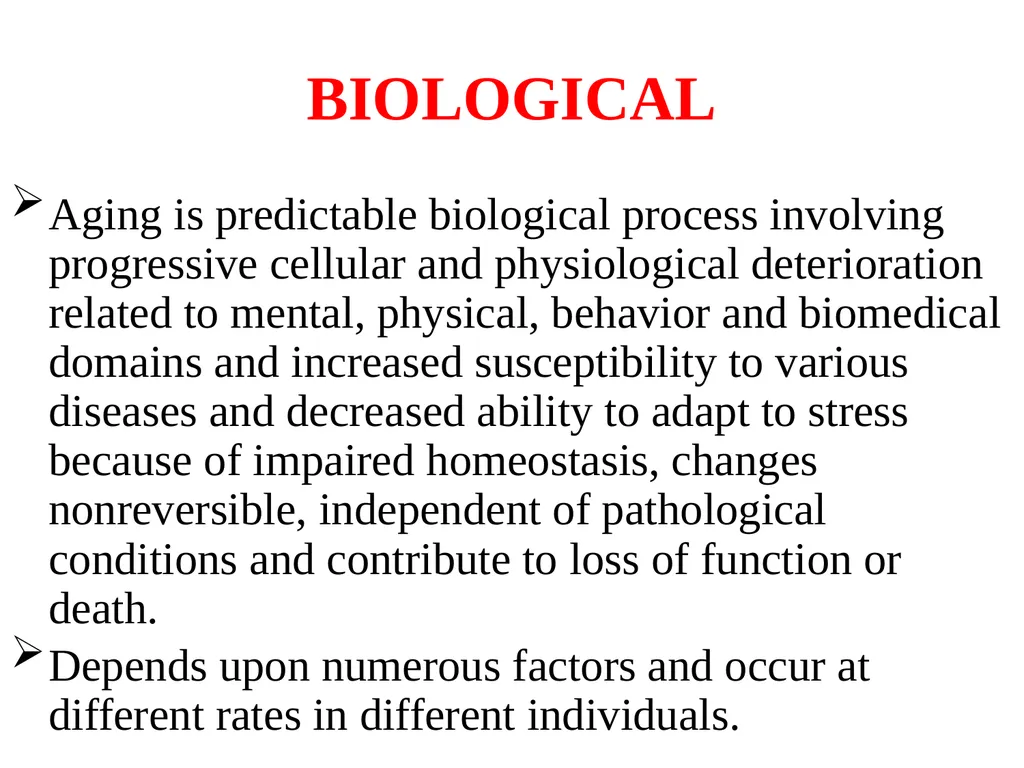
slide19. BIOLOGICAL Aging is predictable biological process involving progressive cellular and physiological deterioration related to mental, physical, behavior and biomedical domains and increased susceptibility to various diseases and decreased ability to adapt to stress because of impaired homeostasis, changes nonreversible, independent of pathological conditions and contribute to loss of function or death.
Depends upon numerous factors and occur at different rates in different individuals.<br>
slide20. PSYCHOLOGICAL Physical, physiological, psychological conditions, social prestige, financial status, personal lifestyle, family support system-influences health of elders.
Period of critical changes in body, mind and spirit.
Loneliness, boredom, depression, dejection, grief and worrying about the future alter the normal physiological process.
Loss of memory, loss of confidence, sense of hopelessness, senile dementia, Alzheimer’s disease and other mental disorders.<br>
slide21. General attitude towards old age, degradation of status in community, problems of isolation, loneliness and generation gap-socio-psychological frustration among elderly
Elder abuse-psychological abuse in term of verbal assaults, threats and fear of isolation, physical violence and financial exploitation.
More women than men-maltreatment in both physical and verbal abuse.
Old persons with high educational background and sufficient income-abuse.<br>
slide22. SOCIAL Reduction in income, social status, authority, power, respect a after retirement.
After loss of spouse, friends and colleagues-social isolation.
Loss of decision power by those surrendered property in favor of younger's members.
Ageism is accusing them as inefficient and discriminating against elderly people on basis of their age.<br>
slide23. PREVENTIVE AND COMMUNITY GERIATRICS Art and science of preventing diseases in geriatric population and promoting their health and efficacy.
Process of aging should be smooth and physiological rather than pathological-mainly primary prevention.<br>
slide24. PRINCIPAL OF GERITRIC HEALTHCARE Individual become more heterogeneous or dissimilar as they age.
Aging does not produce an abrupt decline in organ function but disease always does.
Aging process is accentuated by disease and attenuated by modification of risk factors such as smoking, sedentary lifestyle and obesity.
Investigation is essential tool for diagnosis but under or over investigation are to be avoided.<br>
slide25. HEALTH PROMOTION: HEALTHY AGING WHO- “Healthy aging is process of developing and maintaining the functional ability that enables well-being in older age”
Functional ability-the health related attributes that enables people to be and to do what they have reasons to value.
Healthy aging starts at birth so care of old age begins with childhood.<br>
slide26. Adoption of healthy lifestyle and promotive measures undertaken during childhood to ensure healthy aging.
Supportive “age friendly” environments allows older people to live fuller lives and maximize the contribution they make.
Older persons have small appetite, small frequent, nutrient dense foods should be included, both quality and quantity.
Nourishing, digestible, easy to chew and easy to swallow foods beverages.
4-5 serving of fruits and vegetables and cut down on fried foods with saturated and trans fats.<br>
slide27. EARLY DIAGNOSIS AND TREATMENT Early detection and treatment of disease developing in young age- D.M., hypertension or early stage of cancer-decreased morbidity and mortality in geriatric age group.<br>
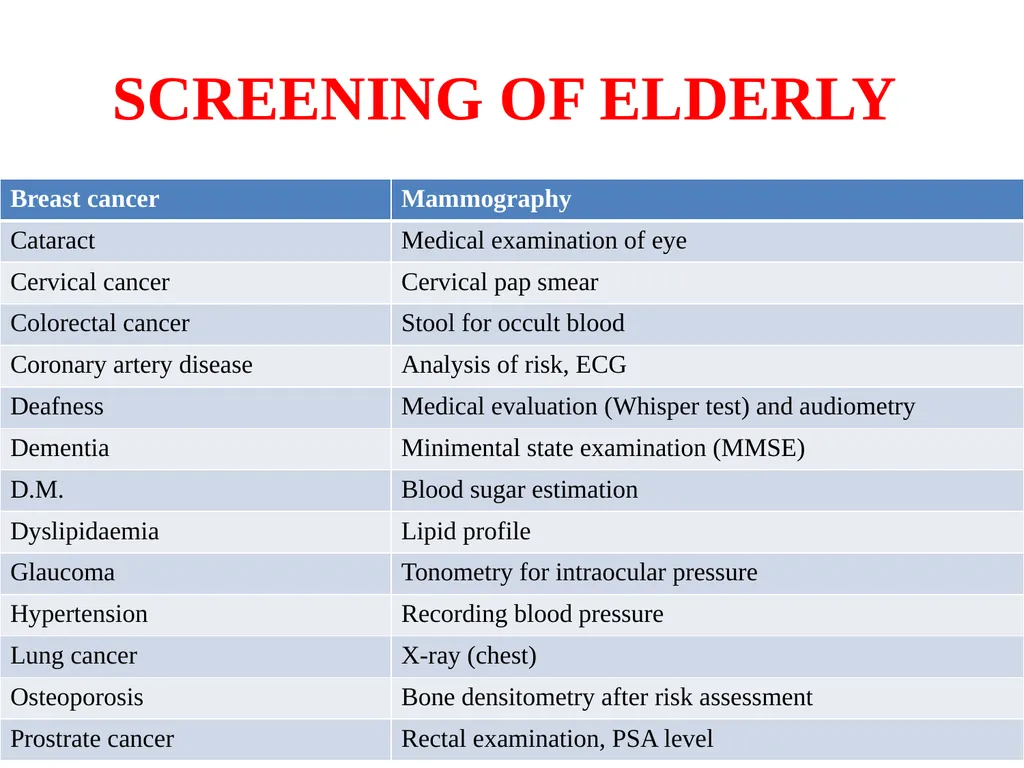
slide28. SCREENING Screening camps-hypertension, D.M.by simple diagnostic procedure and identification of “early warning signs” for cancer training women about breast self examination for presence of lump in breast and exfoliative cytology of vaginal smear.
By conducting health assessment of elderly and collecting information related to vision, joints, hearing, chest, BP, blood sugar etc. and data updated and maintained on subsequent visits.<br>
slide29. SCREENING OF ELDERLY<br>
slide30. PERIODIC HEALTH CHEK-UP Elderly person’s needs are multidisciplinary require medical, social, environmental and mental support.
Annual health check-up includes vision, hearing and laboratory examination of blood test, stool for occult blood and ECG.
Adequate advise on chronic morbidities like COPD, arthritis, D.M., hypertension etc. including lifestyle modification and dietary recommendations.<br>
slide31. COMPONENTS OF COMPREHENSIVE GERIATRIC ASSESSMENT physical
Functional
Psychological: Cognitive, affective
Socioeconomic: Financial status, Social Support and care facility
environment<br>
slide32. REHABILITATION Detection and treatment of debilitating chronic conditions with aim of minimizing residual disability and rehabilitation.
Rehabilitation done by enabling person to acquire skills that is needed to live independent life.
Preventive geriatric focuses on prevention and reduction of disability and improvement of quality of life of old age people.
Spectacles, dentures, sun glasses and hearing aids-free to needy aged person.<br>
slide33. GERIATRIC HEALTHCARE CENTERS At dispensary or a general hospital.
Package of geriatric services at different levels under National Program for Health Care of Elderly(NPHCE)-at subcenter, PHC, CHC, district hospital and regional geriatric center (RGC) level.<br>
slide34. CURRENT APPROACHES GLOBAL APPROACH
Approach changes from curative and rehabilitative to prevention and promotion.
WHO (2002) Based on report on “the world report on aging 2015” changed healthy aging 2015-2030.
HEALTHY AGING (WHO) – “ process of developing and maintaining the functional ability that enables well-being in older age”
FUNCTIONAL ABILITY- “Abilities which enable all elderly to meet their basic needs and to learn, grow and make decisions, remain mobile to build and maintain relationships and to effectively contribute to society”<br>
slide35. October 1st as International Day of Older Persons.
June 15th as World Elder Abuse Day-various types of abuse faced by elderly.
World Health Assembly adopted “The Global Strategy and Action Plan for Aging and Health (GSAP).
May 2016-objective of this strategy- “framework to achieve healthy aging for all”
WHO(2020-2030)- “Decade of elderly”<br>
slide36. GLOBAL STRATEGY AND ACTION PLAN FOR AGING AND HEALTH<br>
slide37. NATIONAL APPROACH Ministry of Social Justice and Empowerment (MoSJE)-social issue of elderly.
MoHFW-health concern.
National Policy on Older Persons (NPOP) 1999,2011
Maintenance and Welfare of Parents and Senior Citizen Act 2007
National Program for Health Care of Elderly -2010<br>
slide38. NATIONAL POLICY ON OLDER PERSONS Financial security
Healthcare and nutrition
Shelter, education, welfare
Protection of life and property
Involvement of NGOs
Training of manpower
Establishment of a National C ouncil for Senior Citizen<br>
slide39. MAINTENANCE OF SENIOR CITZEN ACT 2007 Legal compulsion for children and successors to offer maintenance to senior citizen and parents by monthly allowance.
Provide simple, immediate and economical instrument for protection of life and property of older persons
Senior citizen not capable of maintain himself from own earning or out of property owned by him, entitle to get relief under this act.
If not maintained than get relief from Tribunal constituted under act.<br>
slide40. NATIONAL PROGRAM FOR HEALTH CARE OF ELDERLY 2010-11
Objective-distinct, specialized and comprehensive healthcare to the elderlies at various healthcare delivery system level including services through outreach approach.
Funder and enactment supervised by MoHFW, GOI, after initial implement program run by State Govt.
Initially in 100 selected district, presently 600 district out of 716 in 36 States and UTs<br>
slide41. VISION OF NPHCE To provide accessible, affordable and high quality long-term comprehensive and dedicated care services to aging populations.
Creating new “architecture” for aging.
To build a framework tro create an enabling environment for “a society for all ages”
To provide concept of active and healthy aging.
Convergence with NRHM, AYUSH and other departments like MoSJE<br>
slide42. COMPONENTS OF PROGRAM Dedicated primary care through district hospital, CHC, PHC, SC.
Secondary and tertiary care through RGCs at selected medical colleges.
Centers of excellence- National Centers for Aging-AIMS Delhi and Madras Medical College, Chennai.<br>
slide43. STRATEGIES OF NPHCE PREVENTIVE AND PROMOTIVE CARE
Regular physical exercise, balanced diet, stress management, avoidance of smoking or tobacco products, prevention of fall etc. are provided by expending access to health practices through domiciliary visits by trained health workers.
Health education to elderly and caregivers.
Weekly clinic at PHCs – monitoring and assessment for infirmity.<br>
slide44. MANAGEMENT OF ILLNESS Dedicated outdoor and indoor services at PHCs, CHCs, District hospitals and RGCs for management of chronic and disabling diseases by providing central assistance to State Governments.<br>
slide45. HEALTH MANPOWER DEVELOPMENT In service training through specific modules developed for training of M.O., nurses, community-based workers-conducted.
PG course MD( geriatric medicine) imparted through 4 medical colleges (2 private and 2 government).<br>
slide46. MEDICAL REHABILITATION AND THRAPEUTIC INTERVENTIONS Arranging therapeutic modalities-therapeutic exercises, training in activities of daily life (ADL) and treatment of pain and inflammation through physiotherapy unit at CHC, District Hospital and RGC levels.<br>
slide47. INFORMATION, EDUCATION AND COMMUNICATION(IEC) Health education program through mass media, folk media and other communication channels for promoting concept of healthy aging, importance of physical exercise, healthy habits and reduction of stress.
IEC activities promoted at regular camps.<br>
slide48. LONGITUDINAL AGINGF STUDY OF INDIA (LASI) 2016-long term study carried out by International Institute for Population Sciences (IIPS) Mumbai along with international partners to assess medical and social characteristics of Indian elderly.
Follows 60,000 individuals across States and UTs for 5 years and proposed to extend 25 years.<br>
slide49. SOME OTHER INITIATIVES INTEGRATED PROGRAM FOR OLDER PERSONS<br>
slide2. Name of investigator
Date of investigation<br>
slide3. GENERAL INFORMATION
Name
S/O
Resident of
Sex
Age
Religion with caste
Marital status
Occupation
Family income
Social class
Education<br>
slide4. PERSONAL HABITS Dietary habits (a) Vegetarian (b) Non-vegetarian (c) Lact-ovo-veg.
Smoking (a) No (b) Yes (c) occasional (d) Regular
Type of smoking (e.g. Bidi, Cigarette, Tobacco, Kaini etc.)
Frequency of smoking
Since when smoking (age/duration)
Alcoholic drinks (a) No (b) Yes (c) occasional (d) Regular
Type of drinks
Frequency of drinks
Since when drinking (age/duration)<br>
slide5. 4. Betel chewing (a) No (b) yes (c) occasional (d) Regular
1. with tobacco
2. without tobacco
3. Since when chewing tobacco
4. Frequency of Betel chewing
5. Monthly expenses on
(a) Smoking
(b) Alcoholic drinks
(c) Betel chewing<br>
slide6. C. HISTORY OF PAST ILLNESS (DURING LAST YEAR)
1. Nature of illness 2. Duration 3. Treatment taken at
D. HISTORY OF PRESENT ILLNESS
1.Nature of complaints 2. Duration<br>
slide7. E. FAMILY CONTACTS
1. Name of family member 2. Sex 3. Age 4. Relationship with patient
F. HISTORY OF CONTACT WITH A PATIENT OF SIMILAR ILLNESS BEFORE ONSET OF ILLNESS
1. Family contact
2. Work place contact
3. Neighbourhood contact
4. School contact
5. Village locality contact
6. No history of any contact
7. Any other<br>
slide8. G. HISTORY OF ONSET OF ILLNESS IN HIS CONTACT (DESCRIBE THE NATURE OF CONTACT AND NATURE OF COMPLAINTS IN HIM)<br>
slide9. H. GENERAL EXAMINATION
SYSTEMIC EXAMINATION
Specially abdomen is to be examined for period of gestation and foetal heart sound heard
J. INVESTIGATION DONE<br>
slide10. K. DIAGNOSIS AND MANAGEMENT
(a) Effects of illness on the family (in terms of money and social impact)
(b) Role of physical, Biological & psychological environment in the causation of this illness.
(c) Level of prevention failed in this case.<br>
slide11. L. SUGGEST RECOMMENDATION AT
1. Individual level
2. Family level
3. Community level<br>
slide12. M. SOCIAL THERAPY AND REHABILITATION
1. What should be done for rehabilitation?
2. What can be done to provide
a. Hospital and home treatment
b. Financial assistance
c. Food supplements
d. Housing
e. Vocational training
f. Shelter jobs
g. Better family relation
h. Any other assistance<br>
slide13. CONCLUSION
Source of illness
Circumstances which led to disease
If the disease was preventable
Likely results of the disease
If there any danger of spread of disease to contacts and neighbours.<br>
slide14. INTRODUCTION “Progressive process associated with declines in structure and function, impaired maintenance and repair systems, increased susceptibility to disease and death and reduced reproductive capacity”
GERIATRICS- “branch which deals with health care of aging people.
GERONTOLOGY- Study of physical, biological, psychological and sociological changes which are incident to old age.
SENILITY- Physical and mental weakness associated with old age
SENESCENCE- Process of growing old.<br>
slide15. UNO defines old age as “person who is more than 60 years of age”
1999 Jan. “ National policy on older persons” GOI adopted “Senior Citizen” or “elderly”as a person who is 60 years of age or above.
60-74- “Young old”
75-84 – “ Middle old”
Above 85- “oldest old” or “infirm”<br>
slide16. COMMON GERIATRIC HEALTH PROBLEMS Normal aging- no symptoms.
Abrupt decline in function-pathological not due to aging.
Multi-factorial process depends upon amount of care, consumed diet, environmental factors, personal habits, genetic factors and neglect of body in previous years.<br>
slide17. HEALTH PROBLEMS OF ELDERLY<br>
slide18. CHANGES IN BODY SYSTEM OF ELDERLY<br>
slide19. BIOLOGICAL Aging is predictable biological process involving progressive cellular and physiological deterioration related to mental, physical, behavior and biomedical domains and increased susceptibility to various diseases and decreased ability to adapt to stress because of impaired homeostasis, changes nonreversible, independent of pathological conditions and contribute to loss of function or death.
Depends upon numerous factors and occur at different rates in different individuals.<br>
slide20. PSYCHOLOGICAL Physical, physiological, psychological conditions, social prestige, financial status, personal lifestyle, family support system-influences health of elders.
Period of critical changes in body, mind and spirit.
Loneliness, boredom, depression, dejection, grief and worrying about the future alter the normal physiological process.
Loss of memory, loss of confidence, sense of hopelessness, senile dementia, Alzheimer’s disease and other mental disorders.<br>
slide21. General attitude towards old age, degradation of status in community, problems of isolation, loneliness and generation gap-socio-psychological frustration among elderly
Elder abuse-psychological abuse in term of verbal assaults, threats and fear of isolation, physical violence and financial exploitation.
More women than men-maltreatment in both physical and verbal abuse.
Old persons with high educational background and sufficient income-abuse.<br>
slide22. SOCIAL Reduction in income, social status, authority, power, respect a after retirement.
After loss of spouse, friends and colleagues-social isolation.
Loss of decision power by those surrendered property in favor of younger's members.
Ageism is accusing them as inefficient and discriminating against elderly people on basis of their age.<br>
slide23. PREVENTIVE AND COMMUNITY GERIATRICS Art and science of preventing diseases in geriatric population and promoting their health and efficacy.
Process of aging should be smooth and physiological rather than pathological-mainly primary prevention.<br>
slide24. PRINCIPAL OF GERITRIC HEALTHCARE Individual become more heterogeneous or dissimilar as they age.
Aging does not produce an abrupt decline in organ function but disease always does.
Aging process is accentuated by disease and attenuated by modification of risk factors such as smoking, sedentary lifestyle and obesity.
Investigation is essential tool for diagnosis but under or over investigation are to be avoided.<br>
slide25. HEALTH PROMOTION: HEALTHY AGING WHO- “Healthy aging is process of developing and maintaining the functional ability that enables well-being in older age”
Functional ability-the health related attributes that enables people to be and to do what they have reasons to value.
Healthy aging starts at birth so care of old age begins with childhood.<br>
slide26. Adoption of healthy lifestyle and promotive measures undertaken during childhood to ensure healthy aging.
Supportive “age friendly” environments allows older people to live fuller lives and maximize the contribution they make.
Older persons have small appetite, small frequent, nutrient dense foods should be included, both quality and quantity.
Nourishing, digestible, easy to chew and easy to swallow foods beverages.
4-5 serving of fruits and vegetables and cut down on fried foods with saturated and trans fats.<br>
slide27. EARLY DIAGNOSIS AND TREATMENT Early detection and treatment of disease developing in young age- D.M., hypertension or early stage of cancer-decreased morbidity and mortality in geriatric age group.<br>
slide28. SCREENING Screening camps-hypertension, D.M.by simple diagnostic procedure and identification of “early warning signs” for cancer training women about breast self examination for presence of lump in breast and exfoliative cytology of vaginal smear.
By conducting health assessment of elderly and collecting information related to vision, joints, hearing, chest, BP, blood sugar etc. and data updated and maintained on subsequent visits.<br>
slide29. SCREENING OF ELDERLY<br>
slide30. PERIODIC HEALTH CHEK-UP Elderly person’s needs are multidisciplinary require medical, social, environmental and mental support.
Annual health check-up includes vision, hearing and laboratory examination of blood test, stool for occult blood and ECG.
Adequate advise on chronic morbidities like COPD, arthritis, D.M., hypertension etc. including lifestyle modification and dietary recommendations.<br>
slide31. COMPONENTS OF COMPREHENSIVE GERIATRIC ASSESSMENT physical
Functional
Psychological: Cognitive, affective
Socioeconomic: Financial status, Social Support and care facility
environment<br>
slide32. REHABILITATION Detection and treatment of debilitating chronic conditions with aim of minimizing residual disability and rehabilitation.
Rehabilitation done by enabling person to acquire skills that is needed to live independent life.
Preventive geriatric focuses on prevention and reduction of disability and improvement of quality of life of old age people.
Spectacles, dentures, sun glasses and hearing aids-free to needy aged person.<br>
slide33. GERIATRIC HEALTHCARE CENTERS At dispensary or a general hospital.
Package of geriatric services at different levels under National Program for Health Care of Elderly(NPHCE)-at subcenter, PHC, CHC, district hospital and regional geriatric center (RGC) level.<br>
slide34. CURRENT APPROACHES GLOBAL APPROACH
Approach changes from curative and rehabilitative to prevention and promotion.
WHO (2002) Based on report on “the world report on aging 2015” changed healthy aging 2015-2030.
HEALTHY AGING (WHO) – “ process of developing and maintaining the functional ability that enables well-being in older age”
FUNCTIONAL ABILITY- “Abilities which enable all elderly to meet their basic needs and to learn, grow and make decisions, remain mobile to build and maintain relationships and to effectively contribute to society”<br>
slide35. October 1st as International Day of Older Persons.
June 15th as World Elder Abuse Day-various types of abuse faced by elderly.
World Health Assembly adopted “The Global Strategy and Action Plan for Aging and Health (GSAP).
May 2016-objective of this strategy- “framework to achieve healthy aging for all”
WHO(2020-2030)- “Decade of elderly”<br>
slide36. GLOBAL STRATEGY AND ACTION PLAN FOR AGING AND HEALTH<br>
slide37. NATIONAL APPROACH Ministry of Social Justice and Empowerment (MoSJE)-social issue of elderly.
MoHFW-health concern.
National Policy on Older Persons (NPOP) 1999,2011
Maintenance and Welfare of Parents and Senior Citizen Act 2007
National Program for Health Care of Elderly -2010<br>
slide38. NATIONAL POLICY ON OLDER PERSONS Financial security
Healthcare and nutrition
Shelter, education, welfare
Protection of life and property
Involvement of NGOs
Training of manpower
Establishment of a National C ouncil for Senior Citizen<br>
slide39. MAINTENANCE OF SENIOR CITZEN ACT 2007 Legal compulsion for children and successors to offer maintenance to senior citizen and parents by monthly allowance.
Provide simple, immediate and economical instrument for protection of life and property of older persons
Senior citizen not capable of maintain himself from own earning or out of property owned by him, entitle to get relief under this act.
If not maintained than get relief from Tribunal constituted under act.<br>
slide40. NATIONAL PROGRAM FOR HEALTH CARE OF ELDERLY 2010-11
Objective-distinct, specialized and comprehensive healthcare to the elderlies at various healthcare delivery system level including services through outreach approach.
Funder and enactment supervised by MoHFW, GOI, after initial implement program run by State Govt.
Initially in 100 selected district, presently 600 district out of 716 in 36 States and UTs<br>
slide41. VISION OF NPHCE To provide accessible, affordable and high quality long-term comprehensive and dedicated care services to aging populations.
Creating new “architecture” for aging.
To build a framework tro create an enabling environment for “a society for all ages”
To provide concept of active and healthy aging.
Convergence with NRHM, AYUSH and other departments like MoSJE<br>
slide42. COMPONENTS OF PROGRAM Dedicated primary care through district hospital, CHC, PHC, SC.
Secondary and tertiary care through RGCs at selected medical colleges.
Centers of excellence- National Centers for Aging-AIMS Delhi and Madras Medical College, Chennai.<br>
slide43. STRATEGIES OF NPHCE PREVENTIVE AND PROMOTIVE CARE
Regular physical exercise, balanced diet, stress management, avoidance of smoking or tobacco products, prevention of fall etc. are provided by expending access to health practices through domiciliary visits by trained health workers.
Health education to elderly and caregivers.
Weekly clinic at PHCs – monitoring and assessment for infirmity.<br>
slide44. MANAGEMENT OF ILLNESS Dedicated outdoor and indoor services at PHCs, CHCs, District hospitals and RGCs for management of chronic and disabling diseases by providing central assistance to State Governments.<br>
slide45. HEALTH MANPOWER DEVELOPMENT In service training through specific modules developed for training of M.O., nurses, community-based workers-conducted.
PG course MD( geriatric medicine) imparted through 4 medical colleges (2 private and 2 government).<br>
slide46. MEDICAL REHABILITATION AND THRAPEUTIC INTERVENTIONS Arranging therapeutic modalities-therapeutic exercises, training in activities of daily life (ADL) and treatment of pain and inflammation through physiotherapy unit at CHC, District Hospital and RGC levels.<br>
slide47. INFORMATION, EDUCATION AND COMMUNICATION(IEC) Health education program through mass media, folk media and other communication channels for promoting concept of healthy aging, importance of physical exercise, healthy habits and reduction of stress.
IEC activities promoted at regular camps.<br>
slide48. LONGITUDINAL AGINGF STUDY OF INDIA (LASI) 2016-long term study carried out by International Institute for Population Sciences (IIPS) Mumbai along with international partners to assess medical and social characteristics of Indian elderly.
Follows 60,000 individuals across States and UTs for 5 years and proposed to extend 25 years.<br>
slide49. SOME OTHER INITIATIVES INTEGRATED PROGRAM FOR OLDER PERSONS<br>