
Liver Disorder-II (Jaundice) Dr. Vivek Kr. Singh











Description: Liver Disorder-II (Jaundice) Dr. Vivek Kr. Singh Assistant Professor Department of Veterinary Clinical Complex UNIT-2 Jaundice is also referred to as icterus, and is an important clinical manifestation to liver diseases and biliary system,
Related Topics
Download Presentation
"Liver Disorder-II (Jaundice) Dr. Vivek Kr. Singh" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Liver Disorder-II
(Jaundice) Dr. Vivek Kr. Singh
Assistant Professor
Department of Veterinary Clinical Complex UNIT-2<br>
slide2. Jaundice is also referred to as icterus, and is an important clinical manifestation to liver diseases and biliary system, characterised by deposition of bilirubin leading to yellow coloration of plasma, visible mucous membrane and other tissues<br>
slide3. Etiology On the basis of etiology jaundice can be of three types
Hemolytic jaundice/ Prehepatic jaundice/ over production jaundice
Hepatocellular jaundice/ Hepatic jaundice/ Intrahepatic jaundice
Obstructive jaundice/ extrahepatic jaundice/post- hepatic jaundice<br>
slide4. Hemolytic jaundice/Prehepatic jaundice Hemoprotozoan (trypanosomiasis, babesiosis, anaplasmosis, theileriosis etc.)
Viral and bacterial toxins (leptospirosis, bacillary haemoglobinuria, infectious anemia)
Inorganic and organic toxins (chronic copper poisoning, Se toxicity)
Plant toxins<br>
slide5. Hepatocellular jaundice/ Hepatic jaunice Infections and toxins causing hepatitis/ hepatosis<br>
slide6. Obstructive jaundice/extrahepatic jaundice Bile duct obstruction (biliary calculi, infection with nematodes and trematodes are the common causes of bile duct obstruction )<br>
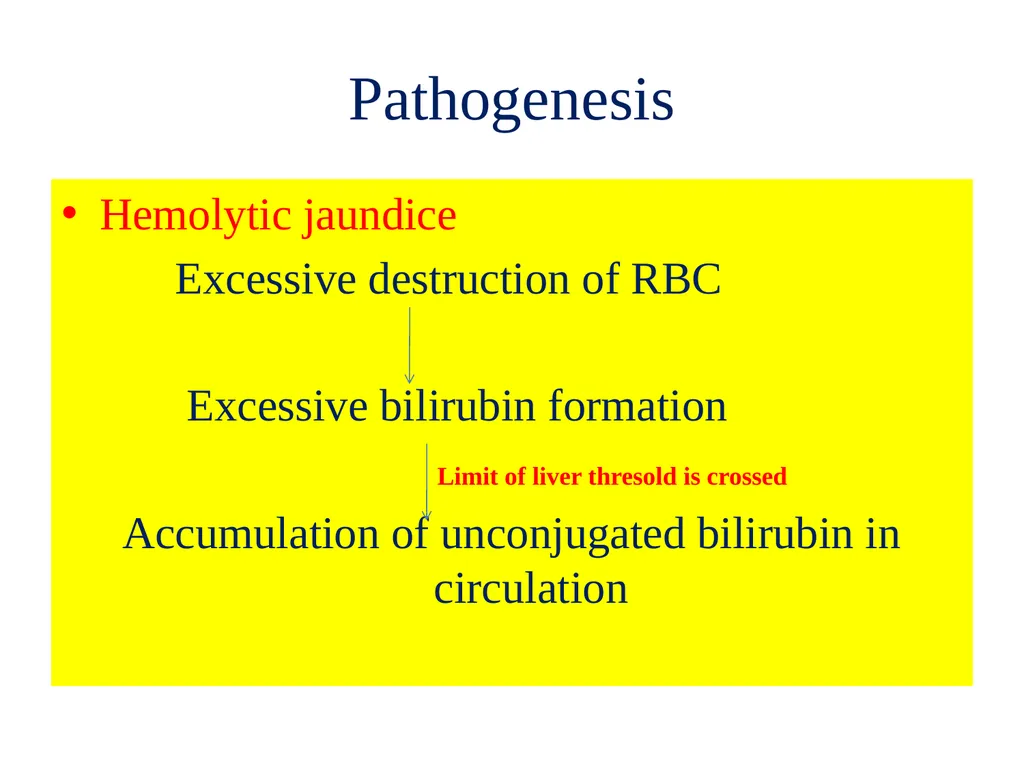
slide7. Pathogenesis Hemolytic jaundice
Excessive destruction of RBC
Excessive bilirubin formation
Limit of liver thresold is crossed
Accumulation of unconjugated bilirubin in circulation<br>
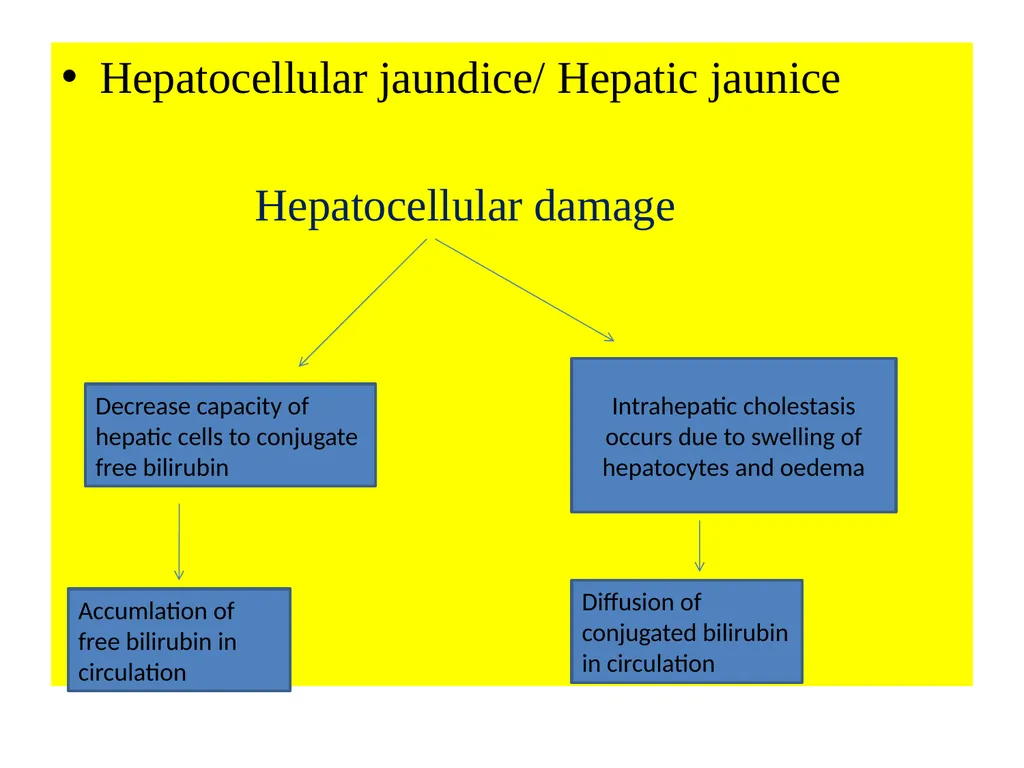
slide8. Hepatocellular jaundice/ Hepatic jaunice
Hepatocellular damage Decrease capacity of hepatic cells to conjugate free bilirubin Intrahepatic cholestasis occurs due to swelling of hepatocytes and oedema Accumlation of free bilirubin in circulation Diffusion of conjugated bilirubin in circulation<br>
slide9. Obstructive jaundice/extrahepatic jaundice Bile duct obstruction
Conjugated bilirubin can not pass into intestine
Diffusion of conjugated bilirubin from bile duct into circulation
Increased level of conjugated bilirubin in serum<br>
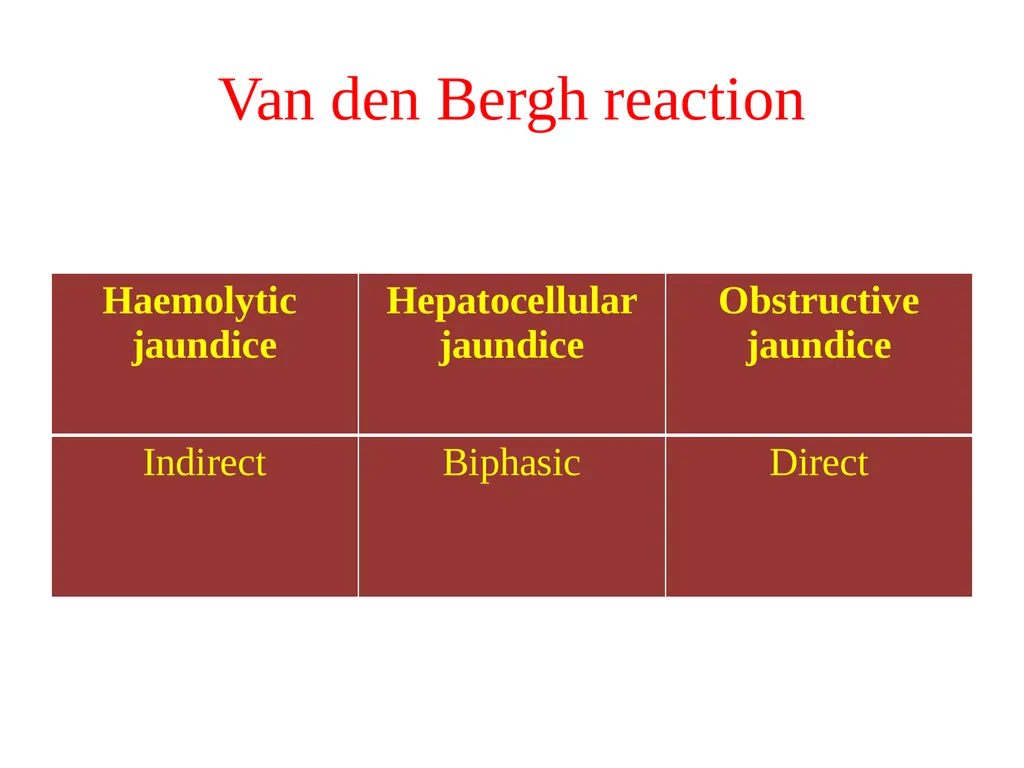
slide10. Van den Bergh reaction<br>
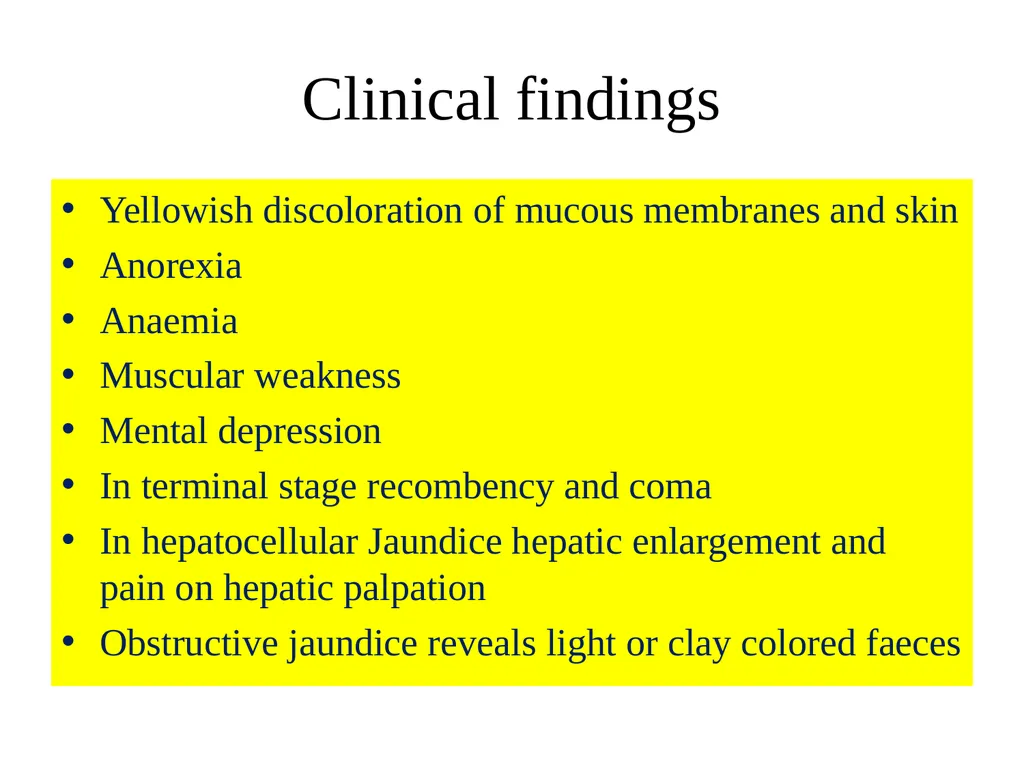
slide11. Clinical findings Yellowish discoloration of mucous membranes and skin
Anorexia
Anaemia
Muscular weakness
Mental depression
In terminal stage recombency and coma
In hepatocellular Jaundice hepatic enlargement and pain on hepatic palpation
Obstructive jaundice reveals light or clay colored faeces<br>
slide12. Diagnosis History and clinical signs
Estimation of Direct, Indirect and Total bilirubin
Van den Bergh test
Urine examination<br>
slide13. Treatment Primary cause should be eliminated
Affected animals should be given carbohydrates rich, palatable and laxative diet
Diet should have minimum amount of fat
Intramuscular administration of liver tonics and vitamin B complex @ 5-10ml once daily in large animals for 4-6 days helps in early recovery<br>
slide14. Thanks<br>
Assistant Professor
Department of Veterinary Clinical Complex UNIT-2<br>
slide2. Jaundice is also referred to as icterus, and is an important clinical manifestation to liver diseases and biliary system, characterised by deposition of bilirubin leading to yellow coloration of plasma, visible mucous membrane and other tissues<br>
slide3. Etiology On the basis of etiology jaundice can be of three types
Hemolytic jaundice/ Prehepatic jaundice/ over production jaundice
Hepatocellular jaundice/ Hepatic jaundice/ Intrahepatic jaundice
Obstructive jaundice/ extrahepatic jaundice/post- hepatic jaundice<br>
slide4. Hemolytic jaundice/Prehepatic jaundice Hemoprotozoan (trypanosomiasis, babesiosis, anaplasmosis, theileriosis etc.)
Viral and bacterial toxins (leptospirosis, bacillary haemoglobinuria, infectious anemia)
Inorganic and organic toxins (chronic copper poisoning, Se toxicity)
Plant toxins<br>
slide5. Hepatocellular jaundice/ Hepatic jaunice Infections and toxins causing hepatitis/ hepatosis<br>
slide6. Obstructive jaundice/extrahepatic jaundice Bile duct obstruction (biliary calculi, infection with nematodes and trematodes are the common causes of bile duct obstruction )<br>
slide7. Pathogenesis Hemolytic jaundice
Excessive destruction of RBC
Excessive bilirubin formation
Limit of liver thresold is crossed
Accumulation of unconjugated bilirubin in circulation<br>
slide8. Hepatocellular jaundice/ Hepatic jaunice
Hepatocellular damage Decrease capacity of hepatic cells to conjugate free bilirubin Intrahepatic cholestasis occurs due to swelling of hepatocytes and oedema Accumlation of free bilirubin in circulation Diffusion of conjugated bilirubin in circulation<br>
slide9. Obstructive jaundice/extrahepatic jaundice Bile duct obstruction
Conjugated bilirubin can not pass into intestine
Diffusion of conjugated bilirubin from bile duct into circulation
Increased level of conjugated bilirubin in serum<br>
slide10. Van den Bergh reaction<br>
slide11. Clinical findings Yellowish discoloration of mucous membranes and skin
Anorexia
Anaemia
Muscular weakness
Mental depression
In terminal stage recombency and coma
In hepatocellular Jaundice hepatic enlargement and pain on hepatic palpation
Obstructive jaundice reveals light or clay colored faeces<br>
slide12. Diagnosis History and clinical signs
Estimation of Direct, Indirect and Total bilirubin
Van den Bergh test
Urine examination<br>
slide13. Treatment Primary cause should be eliminated
Affected animals should be given carbohydrates rich, palatable and laxative diet
Diet should have minimum amount of fat
Intramuscular administration of liver tonics and vitamin B complex @ 5-10ml once daily in large animals for 4-6 days helps in early recovery<br>
slide14. Thanks<br>