
Pharmacology of the Autonomic Nervous System Part

























Description: Pharmacology of the Autonomic Nervous System Part 2 Thomas E. Tenner, Jr., Ph.D. Dept. of Medical Education Dept. Pharmacology Neuroscience tom.tennerttuhsc.edu 743-7169 1 Recommended Background Reading : Chapters 7, 8, 9, and 10 Basic
Related Topics
Download Presentation
"Pharmacology of the Autonomic Nervous System Part" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Pharmacology of the
Autonomic Nervous System
Part 2 Thomas E. Tenner, Jr., Ph.D.
Dept. of Medical Education
Dept. Pharmacology & Neuroscience
tom.tenner@ttuhsc.edu
743-7169 1<br>
slide2. Recommended Background Reading :
Chapters 7, 8, 9, and 10
Basic and Clinical Pharmacology
Bertram Katzung
(13th Edition) 2<br>
slide3. Learning Objectives: List and describe the mechanism of action, therapeutic indications, and adverse effects of cholinergic agonists and cholinesterase inhibitors.
List and describe the mechanism of action, therapeutic indications, and adverse effects of muscarinic and nicotinic receptor antagonists.
List and describe the mechanism of action, therapeutic indications, and adverse effects of direct, indirect, and mixed acting adrenergic agonists.
List and describe the mechanism of action, therapeutic indications, and adverse effects of adrenergic and -adrenergic blocking agents. 3<br>
slide4. ANS – Cholinergic Pharmacology 4<br>
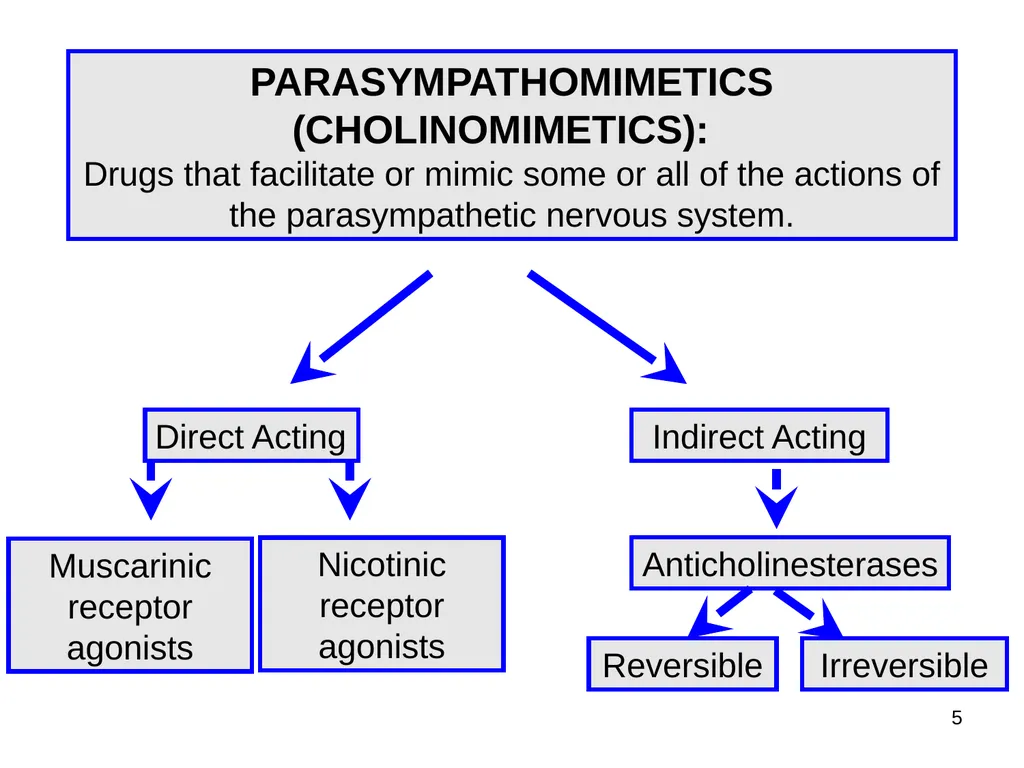
slide5. PARASYMPATHOMIMETICS (CHOLINOMIMETICS):
Drugs that facilitate or mimic some or all of the actions of the parasympathetic nervous system. Muscarinic receptor agonists Anticholinesterases 5 Reversible Indirect Acting Irreversible Direct Acting Nicotinic receptor agonists<br>
slide6. 6 Direct Acting Cholinergic Agonists Acetylcholine *not used therapeutically – N/M
Carbachol * (Miostat) – N/M
Bethanechol * (Urecholine) – M
Pilocarpine (Pilocar, Ocusert) – M
Indications – Urinary retention after surgery or postpartum, Glaucoma
Adverse effects –
Muscarinic (M): salivation, flushing, bronchospasm, sweating, nausea, abdominal pain – acid indigestion and GI cramping, diarrhea, and possibly, decreased blood pressure.
Nicotinic (N)- Fasciculations, respiratory arrest<br>
slide7. 7 Direct Acting Cholinergic Nicotinic Agonists Nicotine
MOA**- Low doses – ganglionic stimulation causing euphoria and arousal. CNS effects cause relaxation and improves attention (Acute)
Indications – None
Adverse effects – Vomiting, convulsions, hypertension, cardiac arrhythmias, Respiratory arrest – (depolarizing blockade), Muscarinic effects - PNS ganglia stimulation.
Succinylcholine *:
MOA - Overstimulation results in depolarizing blockade
Indications – muscle relaxation/paralysis associated with intubation, other procedures
Adverse effects – Fasciculations, respiratory arrest, malignant hyperthermia<br>
slide8. 8 Indirect Acting Cholinergic Agonists - Reversible Edrophonium *(Tensilon)
Neostigmine *
Pyridostigmine* (Mestinon,)
Physostigmine
MOA - Prolongs duration of acetylcholine by binding with and blocking acetylcholinesterase.
Therefore both Nicotinic(N) and Muscarinic(M) effects!
Indications – Myasthenia Gravis, Glaucoma, Atropine Poisoning
Adverse effects –salivation, flushing, bradycardia, bronchospasm, sweating, nausea, abdominal pain, diarrhea, decreased blood pressure, muscle fasciculations (N), and respiratory arrest (N).<br>
slide9. 9 Indirect Acting Cholinergic Agonists – Reversible - CNS Used in Alzheimer’s :
Donepezil (Aricept, Aricept ODT)
Galantamine (Razadyne, Razadyne ER)
Rivastigmine (Exelon) – tertiary amine
Mechanism of action – Increase cerebral concentrations of acetylcholine by inhibiting acetylcholinesterase
Adverse effects –Same as other reversible ACHase Inhibitors<br>
slide10. 10 Indirect Acting Cholinergic Agonists - Irreversible Echothiophate* (Phospholine)
MOA- Prolongs duration of acetylcholine by permanently inactivating acetylcholinesterase.
Therefore both Nicotinic(N) and Muscarinic(M) effects!
Indications – Glaucoma
Adverse effects –salivation, flushing, bradycardia, bronchospasm, sweating, nausea, abdominal pain, diarrhea, decreased blood pressure, muscle fasciculations (N), and respiratory arrest (N).<br>
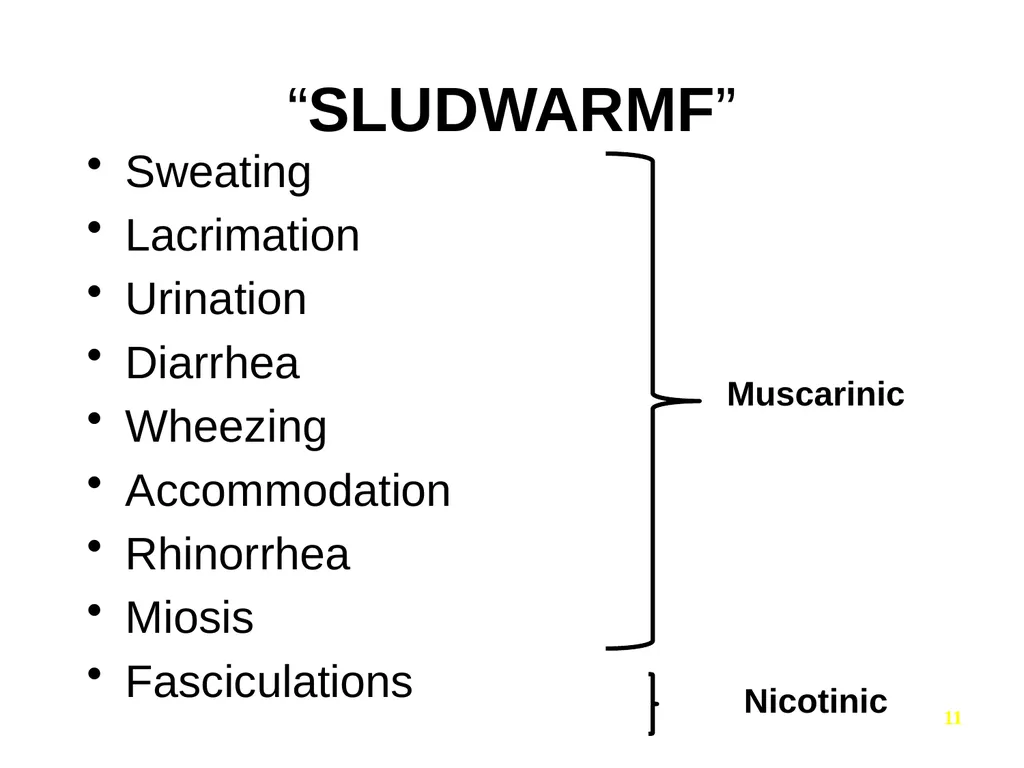
slide11. “SLUDWARMF” Sweating
Lacrimation
Urination
Diarrhea
Wheezing
Accommodation
Rhinorrhea
Miosis
Fasciculations 11 Muscarinic Nicotinic<br>
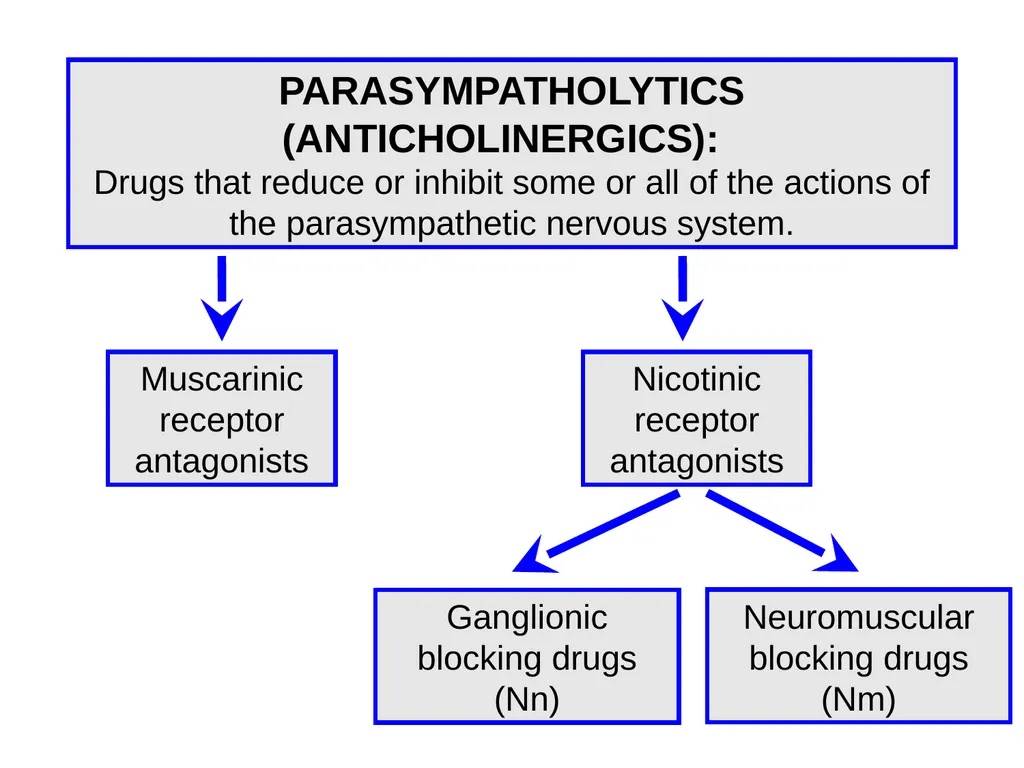
slide12. PARASYMPATHOLYTICS (ANTICHOLINERGICS):
Drugs that reduce or inhibit some or all of the actions of the parasympathetic nervous system. Muscarinic receptor antagonists Ganglionic blocking drugs (Nn) 12 Neuromuscular blocking drugs (Nm) Nicotinic receptor antagonists<br>
slide13. 13 Parasympatholytics Muscarinic receptor antagonists MOA- Block muscarinic receptors on the effector organs of the parasympathetic nervous system and on the sweat glands
Indications – Varied - specificity for muscarinic receptors is a key reason behind their usefulness.
Adverse effects –
Autonomic
PNS - dry mouth, blurred vision, tachycardia, urinary retention, and constipation
SAS - Inhibition of sweating
CNS - restlessness, confusion, and hallucinations
Common mnemonic : “hot as a hare, blind as a bat, dry as a bone, red as a beet, and mad as a hatter"<br>
slide14. 14 Parasympatholytics Muscarinic receptor antagonists Atropine Sulfate – Cholinesterase poisoning,
ACLS: Bradycardia, Pulseless Electrical Activity and Asystole
Benztropine (Cogentin) – Parkinsonism
Dicyclomine (Bentyl) – Irritable Bowel Syndrome
Ipratropium *(Atrovent) – COPD, Rhinorrhea
Tiotropium * (Spiriva) – COPD, Rhinorrhea
Oxybutynin (Ditropan) – Overactive bladder
Tolterodine (Detrol) – Overactive bladder
Tropicamide (Mydriacyl) - Mydriasis (short duration)
Scopolamine - Motion Sickness, Amnesia<br>
slide15. 15 Parasympatholytics Nicotinic receptor antagonists- Ganglionic Blockers (NN) Mecamylamine – Non-depolarizing, competitive blocker
Nicotine – Depolarizing blocker
High doses – ganglionic blockade causing respiratory paralysis and hypotension
No selectivity - block receptors on both the parasympathetic and sympathetic ganglia
Adverse Effects – Intolerable
Hypotension, Orthostatic Hypotension, atony of bladder and GI Tract, cycloplegia, xerostomia, sexual dysfunction, hyperthermia
Rarely used therapeutically<br>
slide16. 16 Parasympatholytics Nicotinic receptor antagonists- Neuromuscular Blockers (NM) Tubocurarine* - Prototype
Atracurium*
Pancuronium *
Rocuronium*
Vecuronium*
Indications – muscle relaxation/paralysis associated with intubation, other procedures
MOA - Competitive blocker - action can be reversed by increasing concentration of Ach**
Adverse Effects – Respiratory arrest.<br>
slide17. ANS – Adrenergic Pharmacology 17<br>
slide18. Raymond Ahlquist (1948) on Adrenergic receptor function “Alpha receptors are excitatory everywhere but the gut”
“Beta receptors are inhibitory everywhere but the heart” 18<br>
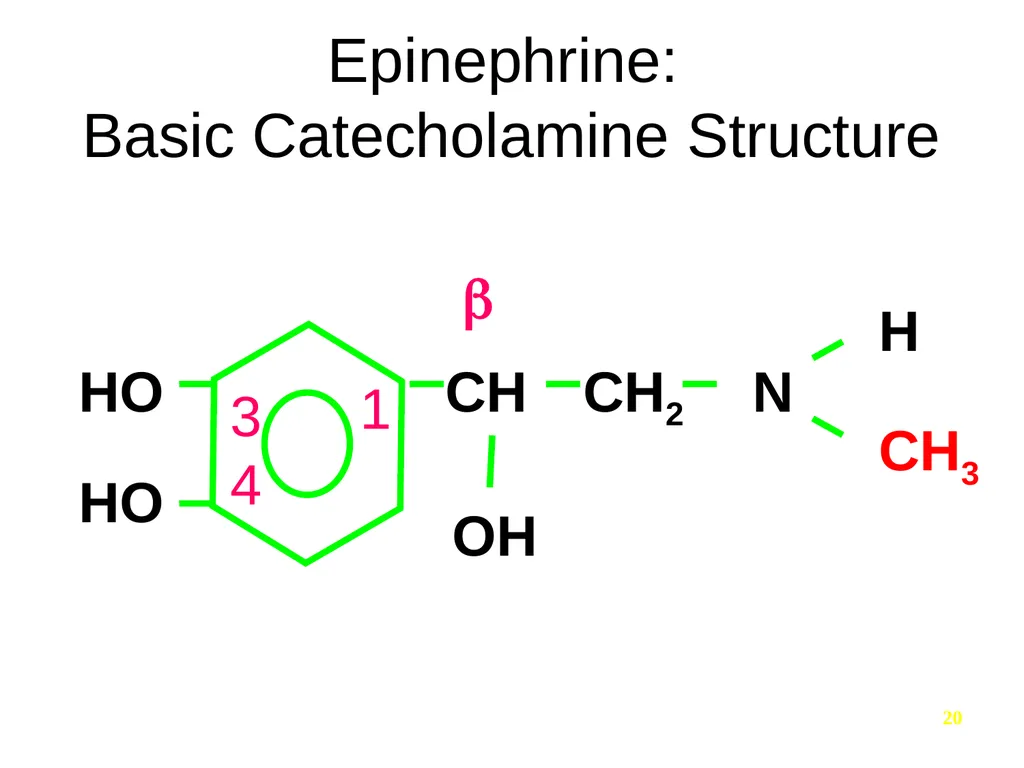
slide19. 19 Adrenergic Agonists Catecholamines - Name is based on their chemical structure (hydroxyl groups at the 3 and 4 position of a benzene ring):
High potency - activate both alpha and beta receptors
Rapid inactivation - Destroyed by COMT (Catechol O-methyltransferase) and by MAO (Monoamine oxidase) which are both located at the neuron and in the gut wall. Catecholamines are not effective when given orally
Poor CNS penetration - They are polar but they still may cause some CNS effects
5 catecholamines - epinephrine, norepinephrine, dopamine, dobutamine, and isoproterenol<br>
slide20. 20 Epinephrine: Basic Catecholamine Structure HO HO CH CH2 N H CH3 OH 1 3 4 0 <br>
slide21. 21 Norepinephrine: Basic Catecholamine Structure HO HO CH CH2 N H H OH 1 3 4 0 <br>
slide22. 22 Dopamine: Basic Catecholamine Structure HO HO CH CH2 N H H H 1 3 4 0 <br>
slide23. 23 Isoproterenol: Basic Catecholamine Structure HO HO CH CH2 N H CH H 1 3 4 0 CH3 CH3<br>
slide24. 24 Amphetamine: Non - Catecholamine CH CH N H
H CH3 H 1 3 4 0 <br>
slide25. 25 Adrenergic agonists Cont. Non-catecholamines -
Not destroyed by COMT and MAO deactivation is limited, so they have longer half lives
Better CNS penetration due to increased lipid solubility<br>
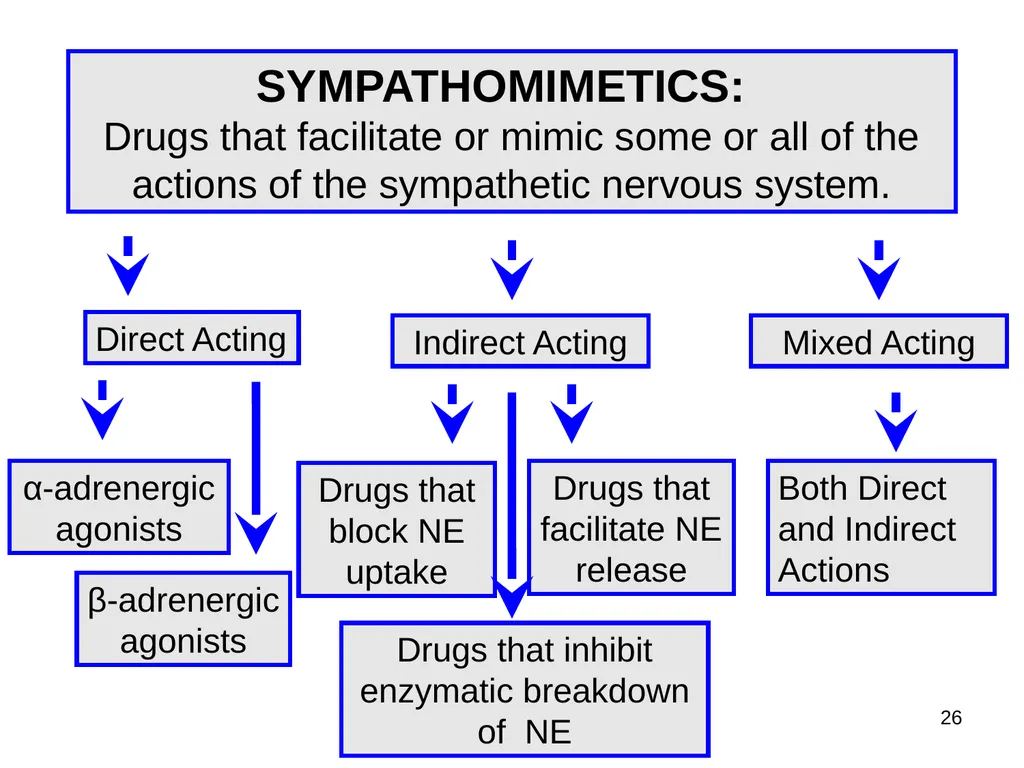
slide26. SYMPATHOMIMETICS:
Drugs that facilitate or mimic some or all of the actions of the sympathetic nervous system. 26 Indirect Acting Direct Acting Drugs that facilitate NE release α-adrenergic agonists β-adrenergic agonists Drugs that block NE uptake Mixed Acting Both Direct and Indirect Actions Drugs that inhibit enzymatic breakdown of NE<br>
slide27. Mechanism of action of adrenergic agonists Direct-Acting Agonists - Mimic NE and EPI. They bind to the adrenergic receptors without interacting with the prejunctional neuron.
(EPI, NE, ISO and Phenylephrine)
Indirect-Acting Agonists:
Displace norepinephrine from storage sites (Amphetamine, hydroxyamphetamine, and tyramine)
Block the uptake of norepinephrine at storage sites (Cocaine, Tricylic Antidepressants, SNRI)
Inhibit enzymatic breakdown of norepinephrine (Monoamine Oxidase Inhibitors, i.e., phenelzine)
Mixed-action agonists - Both stimulate receptors and displace NE from storage sites.
(Ephedrine, pseudoephedrine) 0<br>
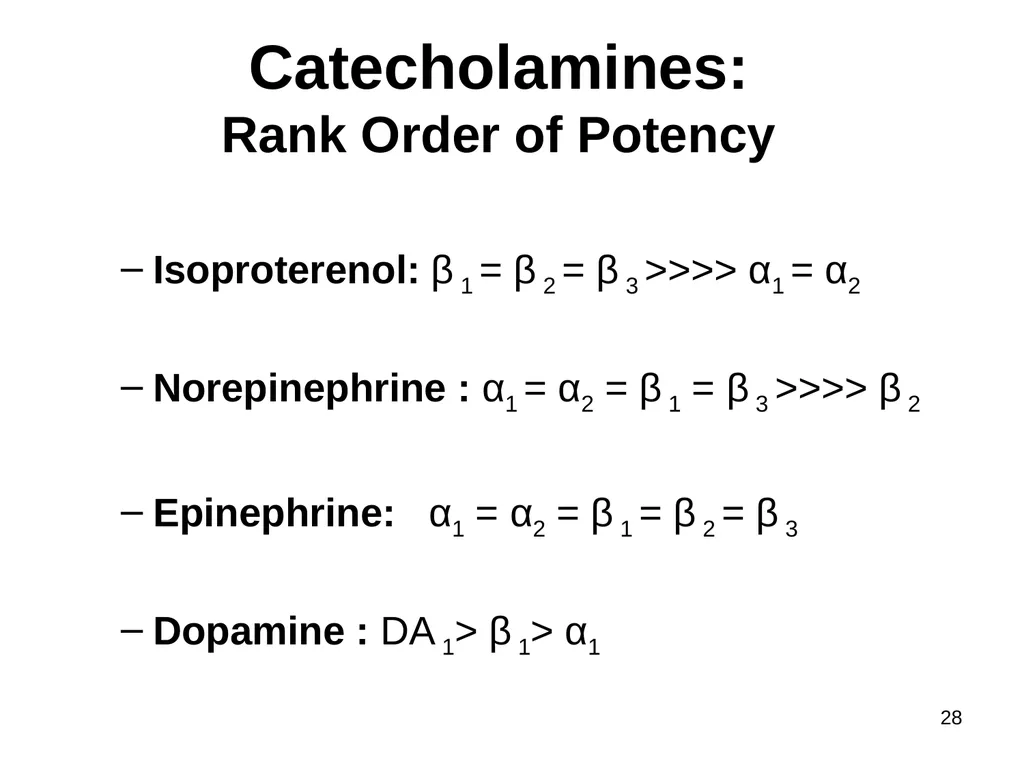
slide28. Catecholamines: Rank Order of Potency Isoproterenol: β 1 = β 2 = β 3 >>>> α1 = α2
Norepinephrine : α1 = α2 = β 1 = β 3 >>>> β 2
Epinephrine: α1 = α2 = β 1 = β 2 = β 3
Dopamine : DA 1> β 1> α1 28<br>
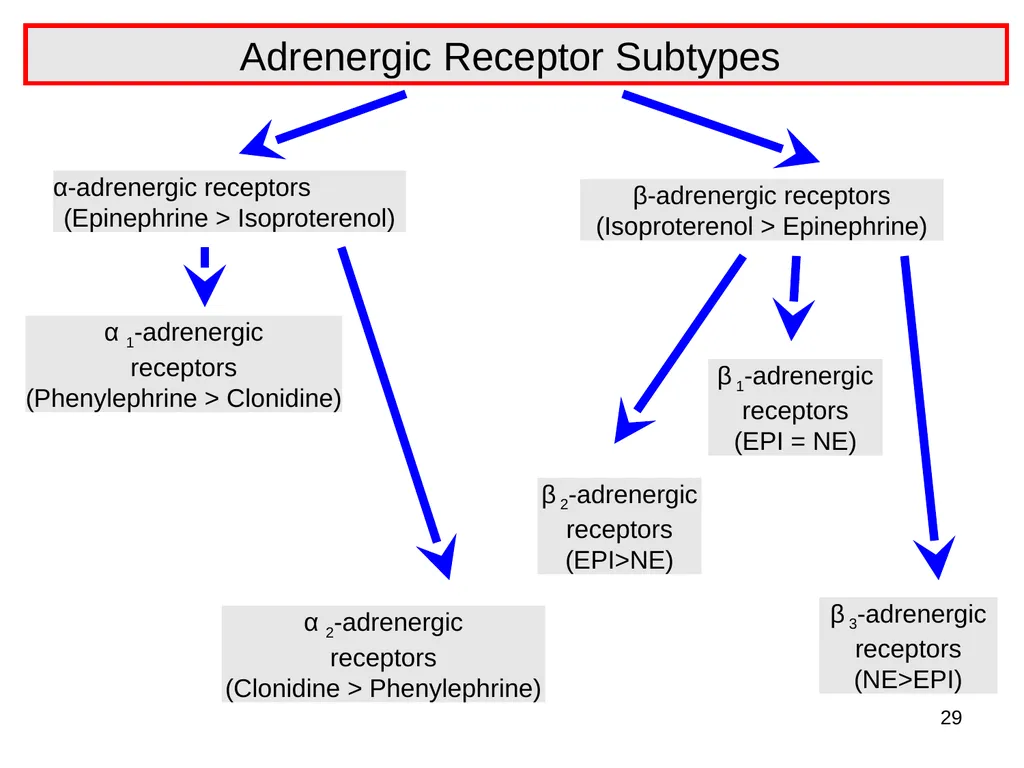
slide29. Adrenergic Receptor Subtypes a α-adrenergic receptors
(Epinephrine > Isoproterenol) β-adrenergic receptors
(Isoproterenol > Epinephrine) α 1-adrenergic
receptors
(Phenylephrine > Clonidine) α 2-adrenergic
receptors
(Clonidine > Phenylephrine) β 1-adrenergic
receptors
(EPI = NE) β 2-adrenergic
receptors
(EPI>NE) β 3-adrenergic
receptors
(NE>EPI) 29<br>
slide30. 30 Direct Acting Alpha1 - Adrenergic Agonists Phenylephrine (Neo-Synephrine)
Oxymetazoline ( Afrin, Visine L.R.)
Indications – Nasal decongestant, mydriatic, and systemically as a vasopressor for hypotension to raise BP.
Adverse effects – Hypertension, Nervousness, Headaches<br>
slide31. 31 Direct Acting Alpha 2 - Adrenergic Agonists Clonidine (Catapres)
Apraclonidine a (Lopidine)
Brimonidine a (Alphagan P)
Indications :
Hypertension - produces inhibition of sympathetic vasomotor centers, reducing blood pressure.
ADHD and impulsive behavior
Glaucoma a
Adverse effects – Bradycardia, Hypotension, Headaches, Sedation, Depression,
Caution for Withdrawal Supersensitivity with Chronic use<br>
slide32. 32 Direct Acting Beta 1- Adrenergic Agonists Dobutamine (Dobutrex)
Mechanism of Action – Primarily a beta 1 agonist. Increases cardiac output with few heart rate or vascular effects
Indication - Congestive heart failure
Adverse actions – tachycardia, palpitations, severe hypotension (alpha antagonist effect). Can increase ventricular rate in atrial fibrillation<br>
slide33. 33 Direct Acting Beta 2- Adrenergic Agonists Albuterol (Proventil, Ventolin)
Terbutaline (Brethine, Bricanyl)
Metaproterenol (Alupent)
Long Acting Beta Agonists (LABA)
Salmeterol (Serevent)
Formoterol (Perforomist)
Indications : Bronchodilator, Asthma; LABA only in COPD.
Adverse effects – Nervousness, muscle tremors, tachycardia.
Systemic route: Hypokalemia and hyperglycemia<br>
slide34. 34 Indirect Acting Adrenergic Agonists Amphetaminea
Hydroxyamphetamine
Cocaine
TCA’s, SNRI’sb
MAOI’sb
Indications :
Attention Deficit Disorder (ADD) a
Narcolepsya
Depressioni/Neuropathic painb
Adverse effects – Similar to direct acting Adrenomimetic drugs. (See next slides).<br>
slide35. Amphetamines - Adverse Effects: CNS
confusion
insomnia
irritability
weakness
vertigo/dizziness
tremor
hyperactive reflexes
delirium
panic
suicide
amphetamine psychosis CVS
palpitations
arrhythmias
hypertension
angina
circulatory collapse
headache
chills
sweating
GI
anorexia
nausea, vomitinmg & diarrhea
abdominal cramping<br>
slide36. Adverse Effects:
Anxiety* reaction (hypertension, tachycardia, sweating & paranoia)
Depression
Agitation*
Cardiac Arrhythmias
Seizures*
Incidence of MI unrelated to dose, duration of use or route of administration (no marker)
* Can be treated with Benzodiazepines-Diazepam Cocaine<br>
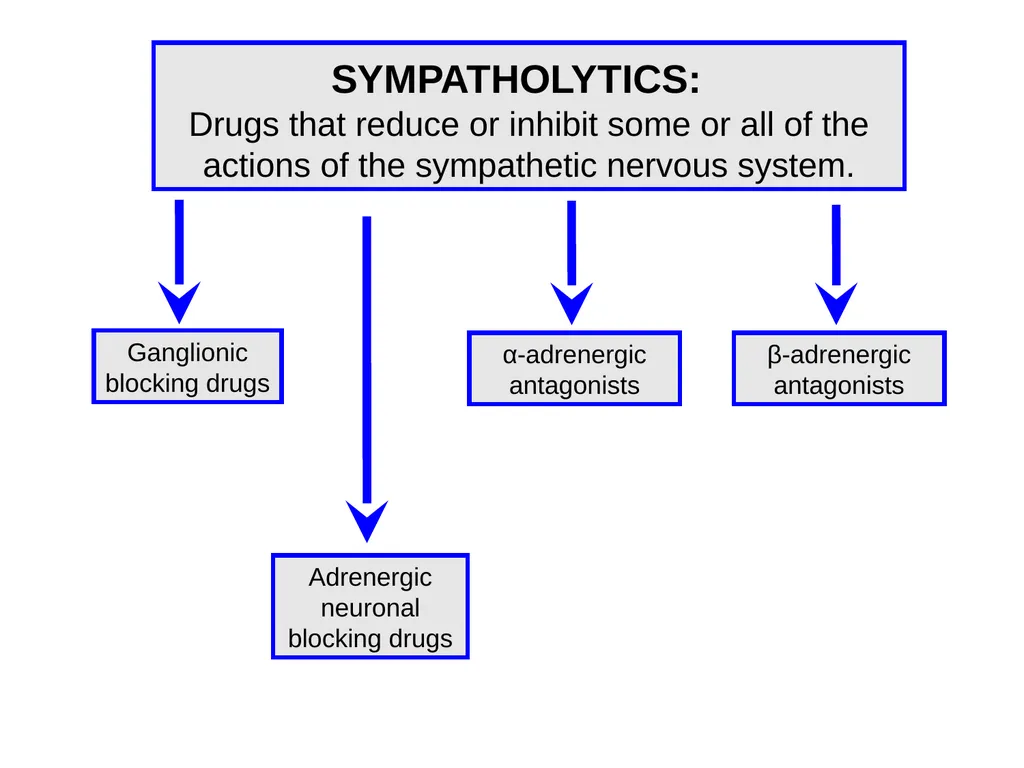
slide37. SYMPATHOLYTICS:
Drugs that reduce or inhibit some or all of the actions of the sympathetic nervous system.<br>
slide38. 38 Adrenergic Neuronal Blocking Drug Reserpine – Discontinued in US
MOA: Prevents uptake of biogenic amines (DA, NE, EPI, 5HT) in both central and peripheral neurons (also adrenal chromaffin granules) Results in Biogenic amine depletion - denervation
Indications : Hypertension .
Adverse effects – Diarrhea, cramps, GI acid secretion, postural hypotension, bradycardia, sexual dysfunction, sedation, depression (suicide).
Caution for Supersensitivity with Chronic use.<br>
slide39. 39 Nonselective Alpha Adrenergic Blocking Agents Phentolaminea (Regitine)
reversible and competitive
Phenoxybenzamineb (Dibenzyline)
irreversible and non-competitive
MOA – block both Alpha1 and Alpha2
Indications : Diagnosisa and Treatmentb of Pheochromocytoma
Adverse effects – Orthostatic hypotension, exaggerated reflex tachycardia (why), nasal stuffiness, ejaculatory dysfunction<br>
slide40. 40 Alpha-1 Selective Adrenergic Blocking Agents Prazosin (Minipress) - Prototype
Doxazosin (Cardura)
Terazosin (Hytrin)
Tamsulosin (Flomax) – Selective for Alpha 1Aa
Indications:
Hypertension – not monotherapy
Benign Prostatic Hypertrophya - relaxes bladder neck and prostate smooth muscle<br>
slide41. 41 Alpha-1 Selective Adrenergic Blocking Agents Adverse effects :
First Dose Effect - Exaggerated hypotension that can lead to syncope especially when patient stands after sitting or lying down (orthostatic hypotension)
less reflex tachycardia (why)
sodium and water retention (prazosin) (limits use in high blood pressure)
nasal stuffiness
ejaculatory dysfunction<br>
slide42. 42 Beta Adrenergic Blocking Agents Propranolol a (Inderal)
Timolol a (Timoptic)
Nadolol a (Corgard)
Atenolol b (Tenormin)
Metoprolol b (Lopressor)
Esmolol b (Brevibloc)
MOA :
a Nonselective - both beta-1 and 2
b “Cardioselective” Beta-1 specific<br>
slide43. 43 Beta Blockers Indications cont. Indications :
Prevention of migraines - May prevent catecholamine vasodilation in the brain vasculature (Beta-2?)
Hyperthyroidism – Thyroid storm
Glaucoma – (Timolol)
Arrhythmias, Angina pectoris, Myocardial Infarction, Heart failure – Protective effect against sympathetic overstimulation – improved survival !!
Adverse reactions – Bradycardia, Heart block, Heart failure, Raynaud’s (peripheral vasospasm), Vivid dreams, depression, Bronchoconstriction in asthmatics/COPD, Sexual dysfunction, Decreased glycogenolysis and glucagon secretion
Caution for Withdrawal Supersensitivity with Chronic use<br>
slide44. 44 Alpha and Beta Adrenergic Blocking Agents Labetalol a(Trandate, Normodyne)
Carvedilol b(Coreg)
MOA – block both Alpha1 and Beta Adrenoceptors.
Result in peripheral vasodilation that lowers blood pressure with reduced cardiac rate and contraction
Indications : Hypertension a and Congestive heart failure b
Adverse effects – Combines BOTH Alpha and Beta adrenoceptor blocker adverse effects.<br>
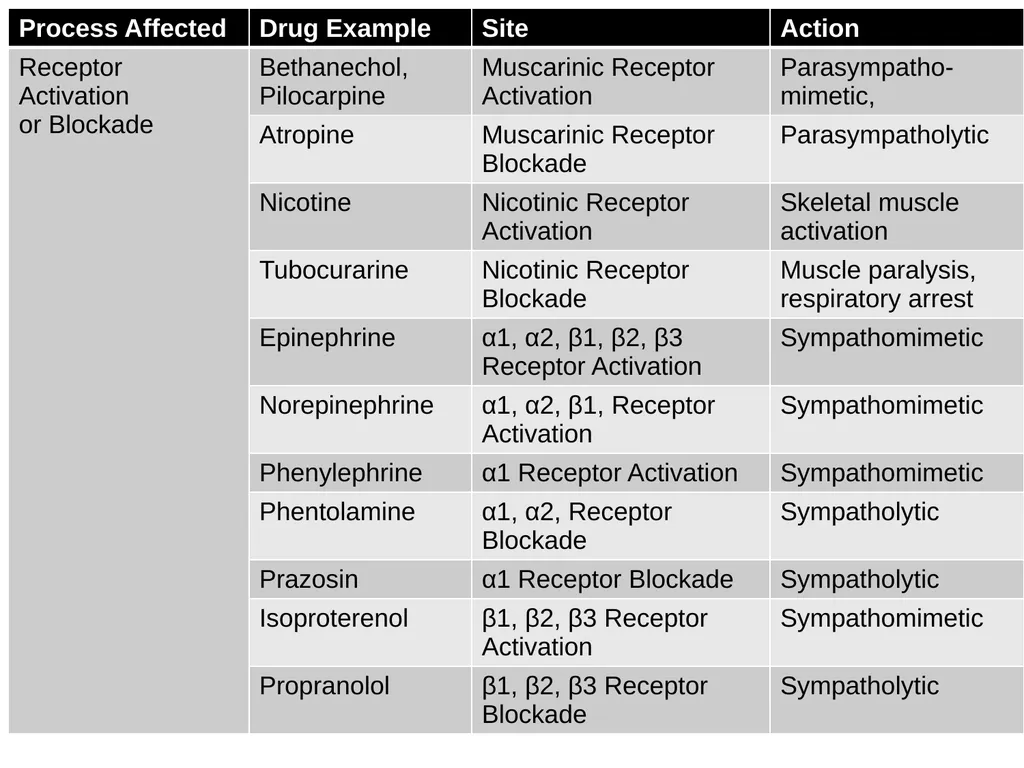
slide45. 45<br>
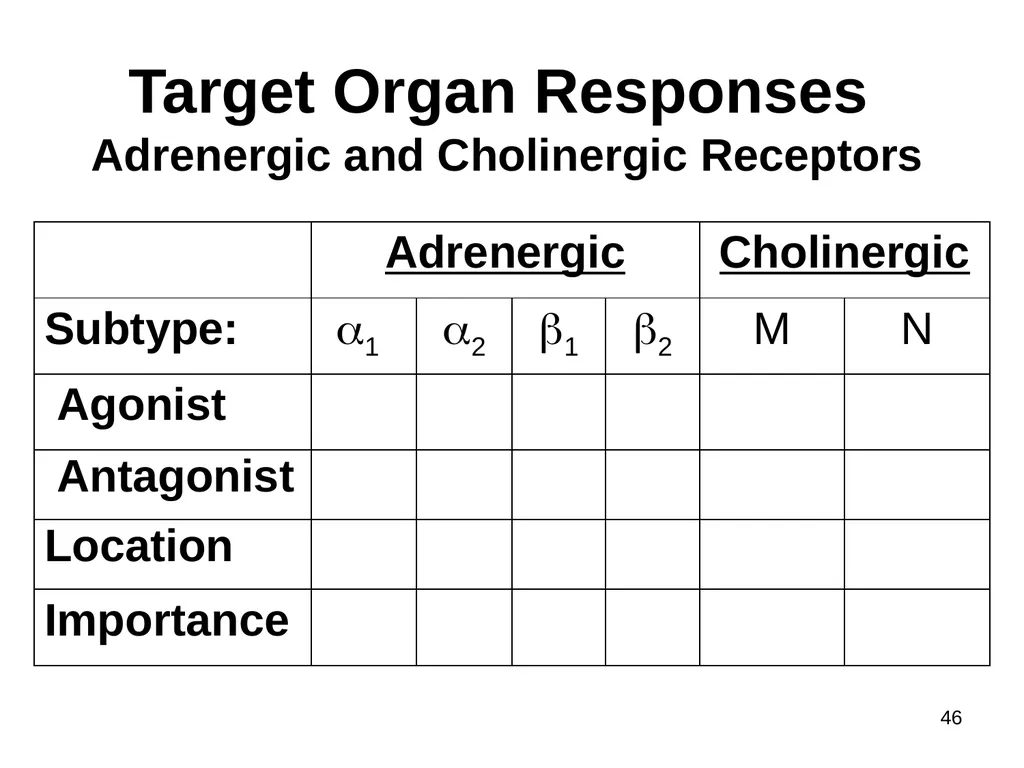
slide46. Target Organ Responses Adrenergic and Cholinergic Receptors 46<br>
slide47. Prototype Drugs 47<br>
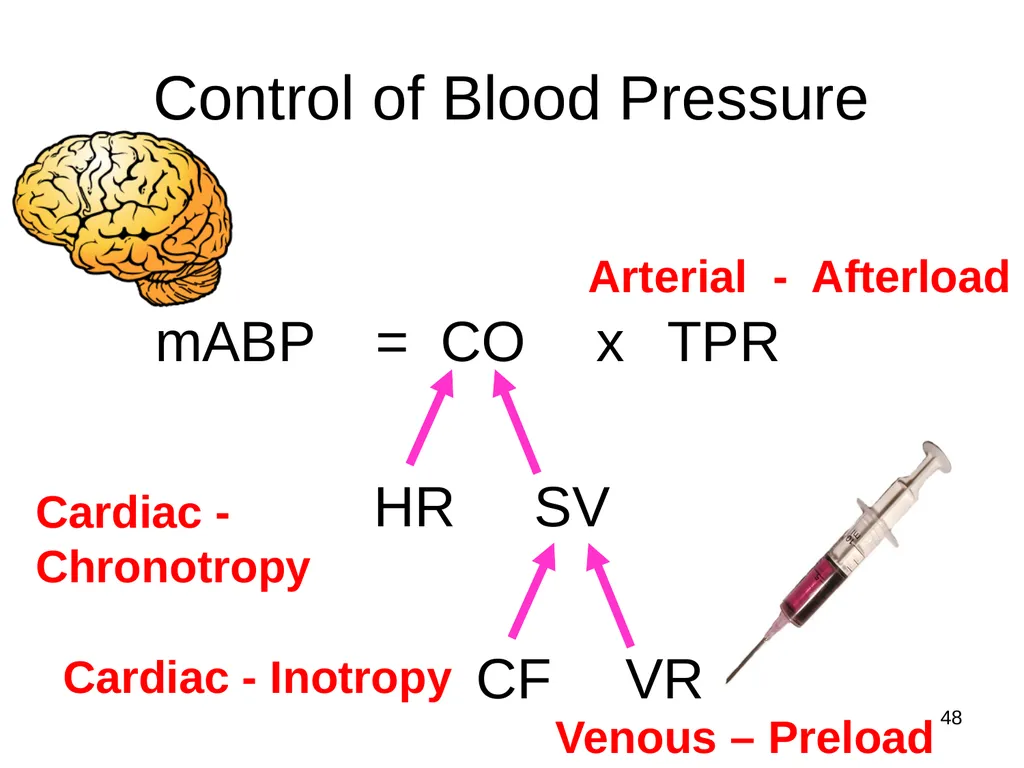
slide48. 48 Control of Blood Pressure Cardiac -
Chronotropy Venous – Preload Arterial - Afterload Cardiac - Inotropy<br>
Dept. of Medical Education
Dept. Pharmacology & Neuroscience
tom.tenner@ttuhsc.edu
743-7169 1<br>
slide2. Recommended Background Reading :
Chapters 7, 8, 9, and 10
Basic and Clinical Pharmacology
Bertram Katzung
(13th Edition) 2<br>
slide3. Learning Objectives: List and describe the mechanism of action, therapeutic indications, and adverse effects of cholinergic agonists and cholinesterase inhibitors.
List and describe the mechanism of action, therapeutic indications, and adverse effects of muscarinic and nicotinic receptor antagonists.
List and describe the mechanism of action, therapeutic indications, and adverse effects of direct, indirect, and mixed acting adrenergic agonists.
List and describe the mechanism of action, therapeutic indications, and adverse effects of adrenergic and -adrenergic blocking agents. 3<br>
slide4. ANS – Cholinergic Pharmacology 4<br>
slide5. PARASYMPATHOMIMETICS (CHOLINOMIMETICS):
Drugs that facilitate or mimic some or all of the actions of the parasympathetic nervous system. Muscarinic receptor agonists Anticholinesterases 5 Reversible Indirect Acting Irreversible Direct Acting Nicotinic receptor agonists<br>
slide6. 6 Direct Acting Cholinergic Agonists Acetylcholine *not used therapeutically – N/M
Carbachol * (Miostat) – N/M
Bethanechol * (Urecholine) – M
Pilocarpine (Pilocar, Ocusert) – M
Indications – Urinary retention after surgery or postpartum, Glaucoma
Adverse effects –
Muscarinic (M): salivation, flushing, bronchospasm, sweating, nausea, abdominal pain – acid indigestion and GI cramping, diarrhea, and possibly, decreased blood pressure.
Nicotinic (N)- Fasciculations, respiratory arrest<br>
slide7. 7 Direct Acting Cholinergic Nicotinic Agonists Nicotine
MOA**- Low doses – ganglionic stimulation causing euphoria and arousal. CNS effects cause relaxation and improves attention (Acute)
Indications – None
Adverse effects – Vomiting, convulsions, hypertension, cardiac arrhythmias, Respiratory arrest – (depolarizing blockade), Muscarinic effects - PNS ganglia stimulation.
Succinylcholine *:
MOA - Overstimulation results in depolarizing blockade
Indications – muscle relaxation/paralysis associated with intubation, other procedures
Adverse effects – Fasciculations, respiratory arrest, malignant hyperthermia<br>
slide8. 8 Indirect Acting Cholinergic Agonists - Reversible Edrophonium *(Tensilon)
Neostigmine *
Pyridostigmine* (Mestinon,)
Physostigmine
MOA - Prolongs duration of acetylcholine by binding with and blocking acetylcholinesterase.
Therefore both Nicotinic(N) and Muscarinic(M) effects!
Indications – Myasthenia Gravis, Glaucoma, Atropine Poisoning
Adverse effects –salivation, flushing, bradycardia, bronchospasm, sweating, nausea, abdominal pain, diarrhea, decreased blood pressure, muscle fasciculations (N), and respiratory arrest (N).<br>
slide9. 9 Indirect Acting Cholinergic Agonists – Reversible - CNS Used in Alzheimer’s :
Donepezil (Aricept, Aricept ODT)
Galantamine (Razadyne, Razadyne ER)
Rivastigmine (Exelon) – tertiary amine
Mechanism of action – Increase cerebral concentrations of acetylcholine by inhibiting acetylcholinesterase
Adverse effects –Same as other reversible ACHase Inhibitors<br>
slide10. 10 Indirect Acting Cholinergic Agonists - Irreversible Echothiophate* (Phospholine)
MOA- Prolongs duration of acetylcholine by permanently inactivating acetylcholinesterase.
Therefore both Nicotinic(N) and Muscarinic(M) effects!
Indications – Glaucoma
Adverse effects –salivation, flushing, bradycardia, bronchospasm, sweating, nausea, abdominal pain, diarrhea, decreased blood pressure, muscle fasciculations (N), and respiratory arrest (N).<br>
slide11. “SLUDWARMF” Sweating
Lacrimation
Urination
Diarrhea
Wheezing
Accommodation
Rhinorrhea
Miosis
Fasciculations 11 Muscarinic Nicotinic<br>
slide12. PARASYMPATHOLYTICS (ANTICHOLINERGICS):
Drugs that reduce or inhibit some or all of the actions of the parasympathetic nervous system. Muscarinic receptor antagonists Ganglionic blocking drugs (Nn) 12 Neuromuscular blocking drugs (Nm) Nicotinic receptor antagonists<br>
slide13. 13 Parasympatholytics Muscarinic receptor antagonists MOA- Block muscarinic receptors on the effector organs of the parasympathetic nervous system and on the sweat glands
Indications – Varied - specificity for muscarinic receptors is a key reason behind their usefulness.
Adverse effects –
Autonomic
PNS - dry mouth, blurred vision, tachycardia, urinary retention, and constipation
SAS - Inhibition of sweating
CNS - restlessness, confusion, and hallucinations
Common mnemonic : “hot as a hare, blind as a bat, dry as a bone, red as a beet, and mad as a hatter"<br>
slide14. 14 Parasympatholytics Muscarinic receptor antagonists Atropine Sulfate – Cholinesterase poisoning,
ACLS: Bradycardia, Pulseless Electrical Activity and Asystole
Benztropine (Cogentin) – Parkinsonism
Dicyclomine (Bentyl) – Irritable Bowel Syndrome
Ipratropium *(Atrovent) – COPD, Rhinorrhea
Tiotropium * (Spiriva) – COPD, Rhinorrhea
Oxybutynin (Ditropan) – Overactive bladder
Tolterodine (Detrol) – Overactive bladder
Tropicamide (Mydriacyl) - Mydriasis (short duration)
Scopolamine - Motion Sickness, Amnesia<br>
slide15. 15 Parasympatholytics Nicotinic receptor antagonists- Ganglionic Blockers (NN) Mecamylamine – Non-depolarizing, competitive blocker
Nicotine – Depolarizing blocker
High doses – ganglionic blockade causing respiratory paralysis and hypotension
No selectivity - block receptors on both the parasympathetic and sympathetic ganglia
Adverse Effects – Intolerable
Hypotension, Orthostatic Hypotension, atony of bladder and GI Tract, cycloplegia, xerostomia, sexual dysfunction, hyperthermia
Rarely used therapeutically<br>
slide16. 16 Parasympatholytics Nicotinic receptor antagonists- Neuromuscular Blockers (NM) Tubocurarine* - Prototype
Atracurium*
Pancuronium *
Rocuronium*
Vecuronium*
Indications – muscle relaxation/paralysis associated with intubation, other procedures
MOA - Competitive blocker - action can be reversed by increasing concentration of Ach**
Adverse Effects – Respiratory arrest.<br>
slide17. ANS – Adrenergic Pharmacology 17<br>
slide18. Raymond Ahlquist (1948) on Adrenergic receptor function “Alpha receptors are excitatory everywhere but the gut”
“Beta receptors are inhibitory everywhere but the heart” 18<br>
slide19. 19 Adrenergic Agonists Catecholamines - Name is based on their chemical structure (hydroxyl groups at the 3 and 4 position of a benzene ring):
High potency - activate both alpha and beta receptors
Rapid inactivation - Destroyed by COMT (Catechol O-methyltransferase) and by MAO (Monoamine oxidase) which are both located at the neuron and in the gut wall. Catecholamines are not effective when given orally
Poor CNS penetration - They are polar but they still may cause some CNS effects
5 catecholamines - epinephrine, norepinephrine, dopamine, dobutamine, and isoproterenol<br>
slide20. 20 Epinephrine: Basic Catecholamine Structure HO HO CH CH2 N H CH3 OH 1 3 4 0 <br>
slide21. 21 Norepinephrine: Basic Catecholamine Structure HO HO CH CH2 N H H OH 1 3 4 0 <br>
slide22. 22 Dopamine: Basic Catecholamine Structure HO HO CH CH2 N H H H 1 3 4 0 <br>
slide23. 23 Isoproterenol: Basic Catecholamine Structure HO HO CH CH2 N H CH H 1 3 4 0 CH3 CH3<br>
slide24. 24 Amphetamine: Non - Catecholamine CH CH N H
H CH3 H 1 3 4 0 <br>
slide25. 25 Adrenergic agonists Cont. Non-catecholamines -
Not destroyed by COMT and MAO deactivation is limited, so they have longer half lives
Better CNS penetration due to increased lipid solubility<br>
slide26. SYMPATHOMIMETICS:
Drugs that facilitate or mimic some or all of the actions of the sympathetic nervous system. 26 Indirect Acting Direct Acting Drugs that facilitate NE release α-adrenergic agonists β-adrenergic agonists Drugs that block NE uptake Mixed Acting Both Direct and Indirect Actions Drugs that inhibit enzymatic breakdown of NE<br>
slide27. Mechanism of action of adrenergic agonists Direct-Acting Agonists - Mimic NE and EPI. They bind to the adrenergic receptors without interacting with the prejunctional neuron.
(EPI, NE, ISO and Phenylephrine)
Indirect-Acting Agonists:
Displace norepinephrine from storage sites (Amphetamine, hydroxyamphetamine, and tyramine)
Block the uptake of norepinephrine at storage sites (Cocaine, Tricylic Antidepressants, SNRI)
Inhibit enzymatic breakdown of norepinephrine (Monoamine Oxidase Inhibitors, i.e., phenelzine)
Mixed-action agonists - Both stimulate receptors and displace NE from storage sites.
(Ephedrine, pseudoephedrine) 0<br>
slide28. Catecholamines: Rank Order of Potency Isoproterenol: β 1 = β 2 = β 3 >>>> α1 = α2
Norepinephrine : α1 = α2 = β 1 = β 3 >>>> β 2
Epinephrine: α1 = α2 = β 1 = β 2 = β 3
Dopamine : DA 1> β 1> α1 28<br>
slide29. Adrenergic Receptor Subtypes a α-adrenergic receptors
(Epinephrine > Isoproterenol) β-adrenergic receptors
(Isoproterenol > Epinephrine) α 1-adrenergic
receptors
(Phenylephrine > Clonidine) α 2-adrenergic
receptors
(Clonidine > Phenylephrine) β 1-adrenergic
receptors
(EPI = NE) β 2-adrenergic
receptors
(EPI>NE) β 3-adrenergic
receptors
(NE>EPI) 29<br>
slide30. 30 Direct Acting Alpha1 - Adrenergic Agonists Phenylephrine (Neo-Synephrine)
Oxymetazoline ( Afrin, Visine L.R.)
Indications – Nasal decongestant, mydriatic, and systemically as a vasopressor for hypotension to raise BP.
Adverse effects – Hypertension, Nervousness, Headaches<br>
slide31. 31 Direct Acting Alpha 2 - Adrenergic Agonists Clonidine (Catapres)
Apraclonidine a (Lopidine)
Brimonidine a (Alphagan P)
Indications :
Hypertension - produces inhibition of sympathetic vasomotor centers, reducing blood pressure.
ADHD and impulsive behavior
Glaucoma a
Adverse effects – Bradycardia, Hypotension, Headaches, Sedation, Depression,
Caution for Withdrawal Supersensitivity with Chronic use<br>
slide32. 32 Direct Acting Beta 1- Adrenergic Agonists Dobutamine (Dobutrex)
Mechanism of Action – Primarily a beta 1 agonist. Increases cardiac output with few heart rate or vascular effects
Indication - Congestive heart failure
Adverse actions – tachycardia, palpitations, severe hypotension (alpha antagonist effect). Can increase ventricular rate in atrial fibrillation<br>
slide33. 33 Direct Acting Beta 2- Adrenergic Agonists Albuterol (Proventil, Ventolin)
Terbutaline (Brethine, Bricanyl)
Metaproterenol (Alupent)
Long Acting Beta Agonists (LABA)
Salmeterol (Serevent)
Formoterol (Perforomist)
Indications : Bronchodilator, Asthma; LABA only in COPD.
Adverse effects – Nervousness, muscle tremors, tachycardia.
Systemic route: Hypokalemia and hyperglycemia<br>
slide34. 34 Indirect Acting Adrenergic Agonists Amphetaminea
Hydroxyamphetamine
Cocaine
TCA’s, SNRI’sb
MAOI’sb
Indications :
Attention Deficit Disorder (ADD) a
Narcolepsya
Depressioni/Neuropathic painb
Adverse effects – Similar to direct acting Adrenomimetic drugs. (See next slides).<br>
slide35. Amphetamines - Adverse Effects: CNS
confusion
insomnia
irritability
weakness
vertigo/dizziness
tremor
hyperactive reflexes
delirium
panic
suicide
amphetamine psychosis CVS
palpitations
arrhythmias
hypertension
angina
circulatory collapse
headache
chills
sweating
GI
anorexia
nausea, vomitinmg & diarrhea
abdominal cramping<br>
slide36. Adverse Effects:
Anxiety* reaction (hypertension, tachycardia, sweating & paranoia)
Depression
Agitation*
Cardiac Arrhythmias
Seizures*
Incidence of MI unrelated to dose, duration of use or route of administration (no marker)
* Can be treated with Benzodiazepines-Diazepam Cocaine<br>
slide37. SYMPATHOLYTICS:
Drugs that reduce or inhibit some or all of the actions of the sympathetic nervous system.<br>
slide38. 38 Adrenergic Neuronal Blocking Drug Reserpine – Discontinued in US
MOA: Prevents uptake of biogenic amines (DA, NE, EPI, 5HT) in both central and peripheral neurons (also adrenal chromaffin granules) Results in Biogenic amine depletion - denervation
Indications : Hypertension .
Adverse effects – Diarrhea, cramps, GI acid secretion, postural hypotension, bradycardia, sexual dysfunction, sedation, depression (suicide).
Caution for Supersensitivity with Chronic use.<br>
slide39. 39 Nonselective Alpha Adrenergic Blocking Agents Phentolaminea (Regitine)
reversible and competitive
Phenoxybenzamineb (Dibenzyline)
irreversible and non-competitive
MOA – block both Alpha1 and Alpha2
Indications : Diagnosisa and Treatmentb of Pheochromocytoma
Adverse effects – Orthostatic hypotension, exaggerated reflex tachycardia (why), nasal stuffiness, ejaculatory dysfunction<br>
slide40. 40 Alpha-1 Selective Adrenergic Blocking Agents Prazosin (Minipress) - Prototype
Doxazosin (Cardura)
Terazosin (Hytrin)
Tamsulosin (Flomax) – Selective for Alpha 1Aa
Indications:
Hypertension – not monotherapy
Benign Prostatic Hypertrophya - relaxes bladder neck and prostate smooth muscle<br>
slide41. 41 Alpha-1 Selective Adrenergic Blocking Agents Adverse effects :
First Dose Effect - Exaggerated hypotension that can lead to syncope especially when patient stands after sitting or lying down (orthostatic hypotension)
less reflex tachycardia (why)
sodium and water retention (prazosin) (limits use in high blood pressure)
nasal stuffiness
ejaculatory dysfunction<br>
slide42. 42 Beta Adrenergic Blocking Agents Propranolol a (Inderal)
Timolol a (Timoptic)
Nadolol a (Corgard)
Atenolol b (Tenormin)
Metoprolol b (Lopressor)
Esmolol b (Brevibloc)
MOA :
a Nonselective - both beta-1 and 2
b “Cardioselective” Beta-1 specific<br>
slide43. 43 Beta Blockers Indications cont. Indications :
Prevention of migraines - May prevent catecholamine vasodilation in the brain vasculature (Beta-2?)
Hyperthyroidism – Thyroid storm
Glaucoma – (Timolol)
Arrhythmias, Angina pectoris, Myocardial Infarction, Heart failure – Protective effect against sympathetic overstimulation – improved survival !!
Adverse reactions – Bradycardia, Heart block, Heart failure, Raynaud’s (peripheral vasospasm), Vivid dreams, depression, Bronchoconstriction in asthmatics/COPD, Sexual dysfunction, Decreased glycogenolysis and glucagon secretion
Caution for Withdrawal Supersensitivity with Chronic use<br>
slide44. 44 Alpha and Beta Adrenergic Blocking Agents Labetalol a(Trandate, Normodyne)
Carvedilol b(Coreg)
MOA – block both Alpha1 and Beta Adrenoceptors.
Result in peripheral vasodilation that lowers blood pressure with reduced cardiac rate and contraction
Indications : Hypertension a and Congestive heart failure b
Adverse effects – Combines BOTH Alpha and Beta adrenoceptor blocker adverse effects.<br>
slide45. 45<br>
slide46. Target Organ Responses Adrenergic and Cholinergic Receptors 46<br>
slide47. Prototype Drugs 47<br>
slide48. 48 Control of Blood Pressure Cardiac -
Chronotropy Venous – Preload Arterial - Afterload Cardiac - Inotropy<br>