
Physiotherapy management of PSP and CBD Helen













Description: Physiotherapy management of PSP and CBD Helen Carten Physiotherapist Parkinsons Team NHS Ayrshire and Arran Role of Physiotherapy One of the key members of the MDT involved in the care of people with PSP and CBD Our role is to maximise a
Related Topics
Download Presentation
"Physiotherapy management of PSP and CBD Helen" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Physiotherapy management of PSP and CBD Helen Carten
Physiotherapist
Parkinson’s Team
NHS Ayrshire and Arran<br>
slide2. Role of Physiotherapy One of the key members of the MDT involved in the care of people with PSP and CBD
Our role is to maximise a person’s function, ability and participation in order to have the best quality of life possible throughout their journey with PSP or CBD
Raising concerns to MDT, prompt referral to Neurologist if red flags for either condition
Patients should have prompt referral to Specialist Physiotherapy- access may vary
Rare conditions but physiotherapists have the skills, knowledge and transferrable skills to manage patients with PSP/CBD<br>
slide3. My role within Ayrshire and Arran In post since July 2022 as the Specialist Physiotherapist with the Parkinson’s Team
Parkinson’s Team look after patients with the Atypical Parkinsonian conditions including PSP and CBD
Part of the Atypical Clinic- prompt access to assessment, advice and ongoing follow up (clinic or home), role in aiding diagnosis with feedback to Neurologist/Consultant. Onward referrals to appropriate services
Always learning!!<br>
slide4. PSP vs PD PSP PD
Falls Backwards- early falls Early falls rare, forward
Vision Difficulty with up/down gaze Eyes can be slow/jerky
Posture Axial rigidity, erect posture Forward leaning
Tremor Rarer More common
FIGS
F- Frequent falls
I- Ineffective medication
G- Gaze Palsy
S- Speech and swallowing changes<br>
slide5. Areas affected by PSP and presentation Basal ganglia (particularly subthalamic nucleus, substantia nigra, globus palladus
Motor control and initiation, motor learning, executive functions and emotional behaviours. Also role in reward/reinforcement
Brainstem
Breathing, Heart rate, BP, Regulation of balance, bridge communication between cerebrum with cerebellum and spinal cord
Cerebral Cortex
Memory, thinking, learning, reasoning, problem solving, emotions, consciousness, sensory functions
Dentate Nucleus of Cerebellum- dorsal( motor) and ventral (non-motor) domain
Regulates fine control of voluntary movement, cognition, language and sensory functions<br>
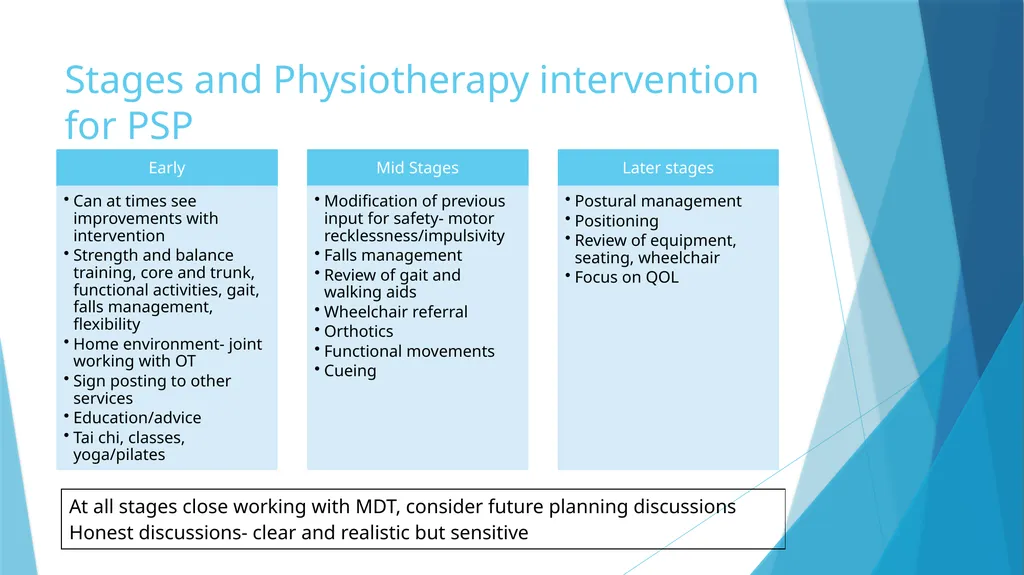
slide6. Stages and Physiotherapy intervention for PSP<br>
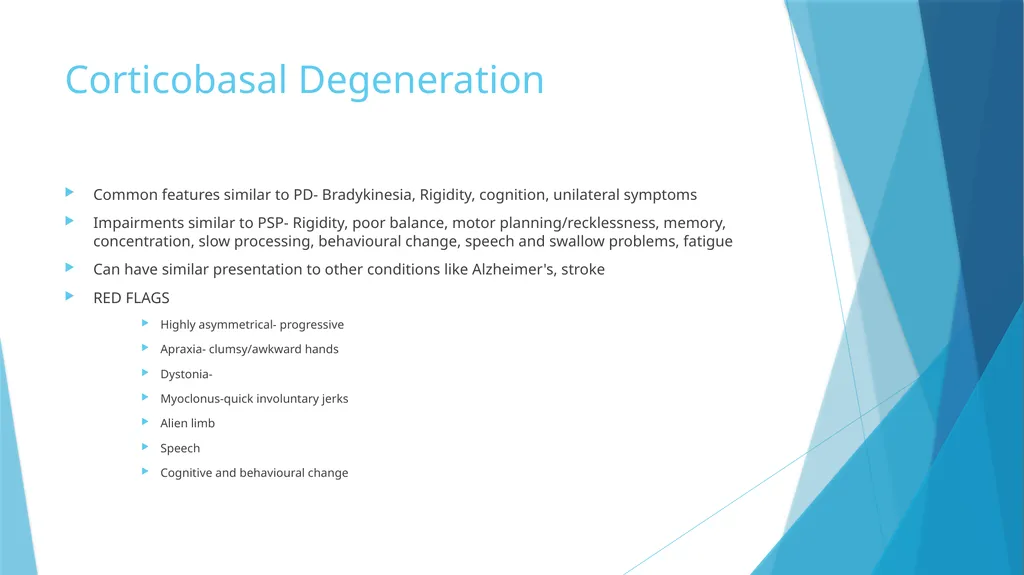
slide7. Corticobasal Degeneration Common features similar to PD- Bradykinesia, Rigidity, cognition, unilateral symptoms
Impairments similar to PSP- Rigidity, poor balance, motor planning/recklessness, memory, concentration, slow processing, behavioural change, speech and swallow problems, fatigue
Can have similar presentation to other conditions like Alzheimer's, stroke
RED FLAGS
Highly asymmetrical- progressive
Apraxia- clumsy/awkward hands
Dystonia-
Myoclonus-quick involuntary jerks
Alien limb
Speech
Cognitive and behavioural change<br>
slide8. Principle areas of brain affected by CBD Basal Ganglia
Motor control and initiation, motor learning, executive functions and emotional behaviours. Also role in reward/reinforcement
Cerebral Cortex-
Memory, thinking, learning, reasoning, problem solving, emotions, consciousness, sensory functions<br>
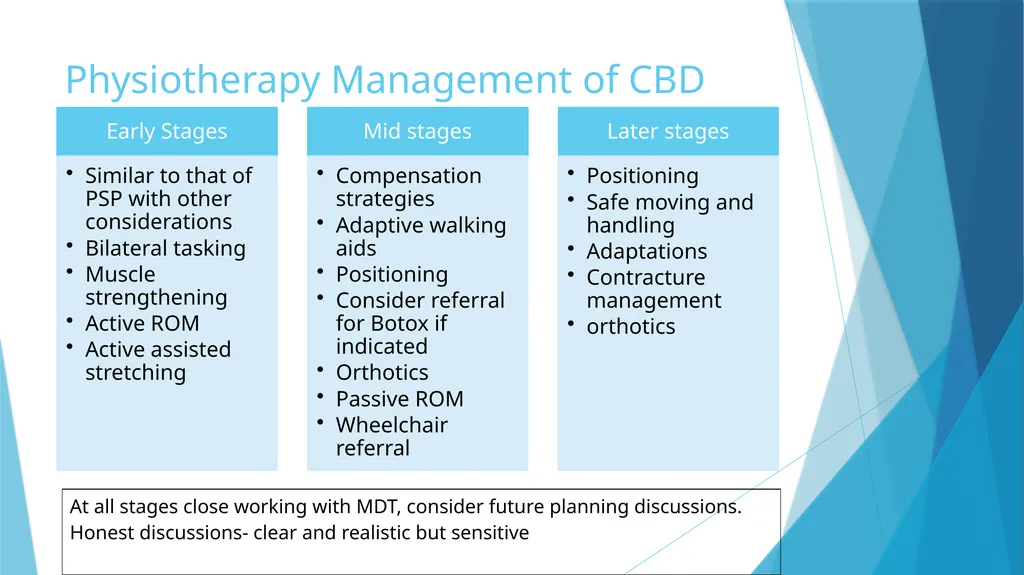
slide9. Physiotherapy Management of CBD<br>
slide10. Challenges and considerations in physiotherapy management of PSP and CBD Rare conditions but with an understanding of the condition you are able to use your skills, experience and knowledge to effectively help this group of patients
Know the red flags
Progressive conditions but they don’t change overnight- consider other causes for sudden deterioration
Walking aids don’t always work
Use PSPA guides and interactive tools
Shifting our and patients ideas of rehabilitation/treatment and what we can do.
Adapting, managing and maintaining
Future planning
Maximising QOL and independence
Small changes can make a big difference<br>
slide11. Case Study 1 Gentleman (70s) diagnosed with PSP. Referred to physio with balance and gait problems. Independently mobile
Motor recklessness, impulsivity, postural instability, falls
Initial treatment was working on high level strength and balance in PT gym
Falls advice, review of walking aid, wheelchair referral
Increased frequency of falls, concerns from wife regarding impulsivity and functional activities
Joint visit and working with OT to explore aids , adaptations and strategies
Trials of different walking aids
Wheelchair referral
Adaptation of exercise programme to take in to account postural instability and impulsivity/motor recklessness. Work on sit to stand to sit and transfers
Developing increasing problems with swallow and respiratory issues. Mobility becoming more unsafe
Joint sessions with SLT, PDNS
Liaison with respiratory PT- trial of acapella. Went on to have input from them and cough assist and suction unit at home
Mobile with assistance or with wheelchair
Sara Stedy
Referral to Social Work- this was discussed at earlier stages
Support of patients wife- significant carer strain- struggled with impulsivity and behavioural changes<br>
slide12. Case Study 2 Patient had diagnosis of possible PD, levodopa not effective, continuing have major issues with freezing and falls. ? PSP
Input post fall from enhanced re-enablement services then referred to me
Close liaison with patient’s consultant- ongoing presentation in keeping with PSP, patient referred to Neurology
Ongoing input from physio focused on safe mobility, cueing, falls prevention, modified strength, balance and functional work. Home environment contributing to concerns
Referral to OT, SW, already had SLT, wheelchair referral
Diagnosis of PSP confirmed by neurologist<br>
slide13. Case study 3 Patient diagnosed with CBD, 80s. Lives alone, mobile with WZF.
Supported by her daughter-in-law
Progressive deterioration of function and control R side. No longer able to safely mobilise
Transfers only with WZF> Sara Stedy
Increased POC to x 4 daily
Joint sessions with OT and PDNS
Referral to Hospice Team, patient already known to PSPA
Future planning- patient was clear about her future plans had been able to discuss these honestly and frankly with her daughter-in-law. Involved in supporting some of these discussions
Patient decided to move to Care Home as her care needs increased and no longer able to get outdoors
Followed up at care home with PDNS<br>
slide14. Questions and Answers<br>
slide15. Contact helen.carten@aapct.scot.nhs.co.uk<br>
Physiotherapist
Parkinson’s Team
NHS Ayrshire and Arran<br>
slide2. Role of Physiotherapy One of the key members of the MDT involved in the care of people with PSP and CBD
Our role is to maximise a person’s function, ability and participation in order to have the best quality of life possible throughout their journey with PSP or CBD
Raising concerns to MDT, prompt referral to Neurologist if red flags for either condition
Patients should have prompt referral to Specialist Physiotherapy- access may vary
Rare conditions but physiotherapists have the skills, knowledge and transferrable skills to manage patients with PSP/CBD<br>
slide3. My role within Ayrshire and Arran In post since July 2022 as the Specialist Physiotherapist with the Parkinson’s Team
Parkinson’s Team look after patients with the Atypical Parkinsonian conditions including PSP and CBD
Part of the Atypical Clinic- prompt access to assessment, advice and ongoing follow up (clinic or home), role in aiding diagnosis with feedback to Neurologist/Consultant. Onward referrals to appropriate services
Always learning!!<br>
slide4. PSP vs PD PSP PD
Falls Backwards- early falls Early falls rare, forward
Vision Difficulty with up/down gaze Eyes can be slow/jerky
Posture Axial rigidity, erect posture Forward leaning
Tremor Rarer More common
FIGS
F- Frequent falls
I- Ineffective medication
G- Gaze Palsy
S- Speech and swallowing changes<br>
slide5. Areas affected by PSP and presentation Basal ganglia (particularly subthalamic nucleus, substantia nigra, globus palladus
Motor control and initiation, motor learning, executive functions and emotional behaviours. Also role in reward/reinforcement
Brainstem
Breathing, Heart rate, BP, Regulation of balance, bridge communication between cerebrum with cerebellum and spinal cord
Cerebral Cortex
Memory, thinking, learning, reasoning, problem solving, emotions, consciousness, sensory functions
Dentate Nucleus of Cerebellum- dorsal( motor) and ventral (non-motor) domain
Regulates fine control of voluntary movement, cognition, language and sensory functions<br>
slide6. Stages and Physiotherapy intervention for PSP<br>
slide7. Corticobasal Degeneration Common features similar to PD- Bradykinesia, Rigidity, cognition, unilateral symptoms
Impairments similar to PSP- Rigidity, poor balance, motor planning/recklessness, memory, concentration, slow processing, behavioural change, speech and swallow problems, fatigue
Can have similar presentation to other conditions like Alzheimer's, stroke
RED FLAGS
Highly asymmetrical- progressive
Apraxia- clumsy/awkward hands
Dystonia-
Myoclonus-quick involuntary jerks
Alien limb
Speech
Cognitive and behavioural change<br>
slide8. Principle areas of brain affected by CBD Basal Ganglia
Motor control and initiation, motor learning, executive functions and emotional behaviours. Also role in reward/reinforcement
Cerebral Cortex-
Memory, thinking, learning, reasoning, problem solving, emotions, consciousness, sensory functions<br>
slide9. Physiotherapy Management of CBD<br>
slide10. Challenges and considerations in physiotherapy management of PSP and CBD Rare conditions but with an understanding of the condition you are able to use your skills, experience and knowledge to effectively help this group of patients
Know the red flags
Progressive conditions but they don’t change overnight- consider other causes for sudden deterioration
Walking aids don’t always work
Use PSPA guides and interactive tools
Shifting our and patients ideas of rehabilitation/treatment and what we can do.
Adapting, managing and maintaining
Future planning
Maximising QOL and independence
Small changes can make a big difference<br>
slide11. Case Study 1 Gentleman (70s) diagnosed with PSP. Referred to physio with balance and gait problems. Independently mobile
Motor recklessness, impulsivity, postural instability, falls
Initial treatment was working on high level strength and balance in PT gym
Falls advice, review of walking aid, wheelchair referral
Increased frequency of falls, concerns from wife regarding impulsivity and functional activities
Joint visit and working with OT to explore aids , adaptations and strategies
Trials of different walking aids
Wheelchair referral
Adaptation of exercise programme to take in to account postural instability and impulsivity/motor recklessness. Work on sit to stand to sit and transfers
Developing increasing problems with swallow and respiratory issues. Mobility becoming more unsafe
Joint sessions with SLT, PDNS
Liaison with respiratory PT- trial of acapella. Went on to have input from them and cough assist and suction unit at home
Mobile with assistance or with wheelchair
Sara Stedy
Referral to Social Work- this was discussed at earlier stages
Support of patients wife- significant carer strain- struggled with impulsivity and behavioural changes<br>
slide12. Case Study 2 Patient had diagnosis of possible PD, levodopa not effective, continuing have major issues with freezing and falls. ? PSP
Input post fall from enhanced re-enablement services then referred to me
Close liaison with patient’s consultant- ongoing presentation in keeping with PSP, patient referred to Neurology
Ongoing input from physio focused on safe mobility, cueing, falls prevention, modified strength, balance and functional work. Home environment contributing to concerns
Referral to OT, SW, already had SLT, wheelchair referral
Diagnosis of PSP confirmed by neurologist<br>
slide13. Case study 3 Patient diagnosed with CBD, 80s. Lives alone, mobile with WZF.
Supported by her daughter-in-law
Progressive deterioration of function and control R side. No longer able to safely mobilise
Transfers only with WZF> Sara Stedy
Increased POC to x 4 daily
Joint sessions with OT and PDNS
Referral to Hospice Team, patient already known to PSPA
Future planning- patient was clear about her future plans had been able to discuss these honestly and frankly with her daughter-in-law. Involved in supporting some of these discussions
Patient decided to move to Care Home as her care needs increased and no longer able to get outdoors
Followed up at care home with PDNS<br>
slide14. Questions and Answers<br>
slide15. Contact helen.carten@aapct.scot.nhs.co.uk<br>