
Pruritus DR. Anwar Issa Hasan 25/11/2018 pruritus
















Description: Pruritus DR. Anwar Issa Hasan 25112018 pruritus Pruritus : is unpleasant sensation elicit desire to itch or scratching. Pruritus is most common dermatological complaint. In general pruritus classify in to : Primary pruritus (idiopathic).
Related Topics
Download Presentation
"Pruritus DR. Anwar Issa Hasan 25/11/2018 pruritus" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Pruritus DR. Anwar Issa Hasan
25/11/2018<br>
slide2. pruritus Pruritus : is unpleasant sensation elicit desire to itch or scratching.
Pruritus is most common dermatological complaint.
In general pruritus classify in to :
Primary pruritus (idiopathic).
Secondary pruritus: result from underlying primary dermatological disease or systemic disease, Its most common type.<br>
slide3. Pruritus Causes of secondary pruritus:
Dermatological disorders
Allergic or hypersensitive syndromes.
Medication.
Toxins associated with kidney and liver diseases.
Neurological disorders.
Systemic disease & Malignancy.
Psychiatric conditions. Pruritus could be localized or generalized.
Pruritus can present with or without cutaneous manifestation.
Localized pruritus without cutaneous manifestation : consider neuropathic itch &dysesthesia or psychogenic pruritus.
Localized pruritus with cutaneous manifestations:
Eczema(LSC)
LICHEN PLANUS.
PEDICULOSIS.
DERMATITIS HERBETIFORMIS.<br>
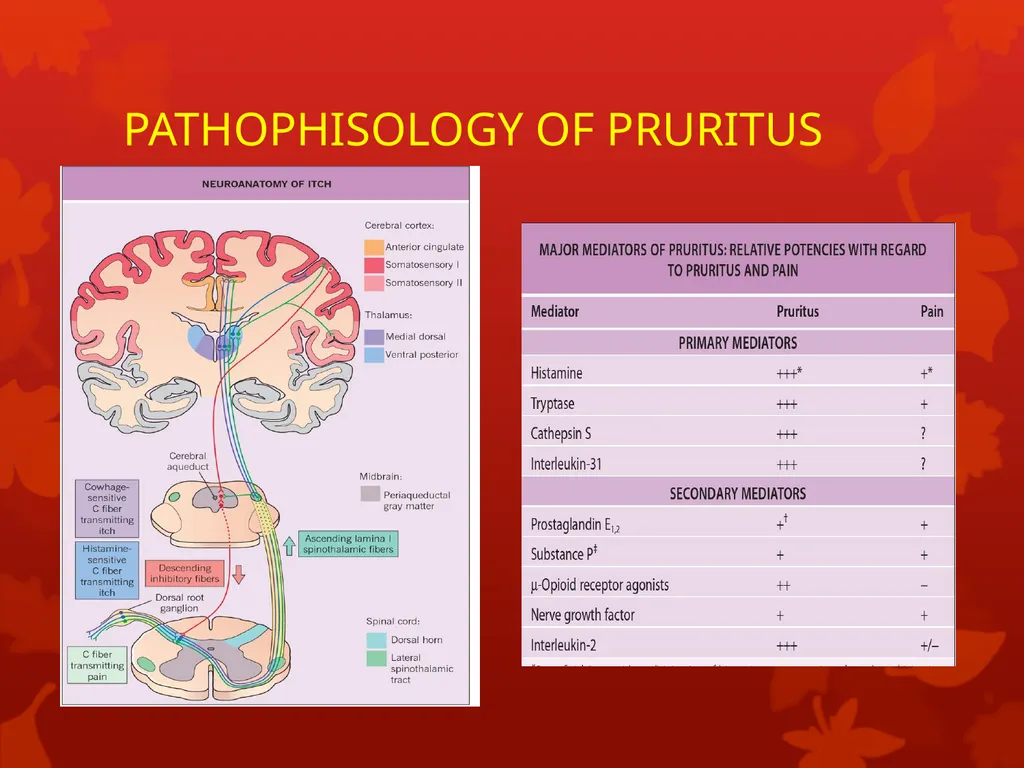
slide4. PATHOPHISOLOGY OF PRURITUS Pruritus result from activation of sensory nerve fibers at four sequential levels:
Peripheral nervous system: sensory nerve fibers at dermoepidermal junction, type C- fibers (small, slow, unmyelinated nerve fibers)
Dorsal root ganglia.
Spinal cord : ascending in spinothalamic tract.
Brain; thalamus and cortical level.<br>
slide5. PATHOPHISOLOGY OF PRURITUS Itching or scratching may either cause:
Inhibition of itch receptors by stimulation of ascending sensory nerve fibers witch inhibits itch at spinal cord.
Scratching interfere with itch fibers lying superficially in skin which may damaged directly by scratching .
Pruritus receptors units: removal of epidermis abolishes the perception of itch, so pruritus receptor unit located predominantly at this layer, LM.EXAMINATION show intraepidermal free non-specialized nerve ending in the granular layer( sub class of C-fiber),contain receptors that mediated itch .<br>
slide6. PATHOPHISOLOGY OF PRURITUS<br>
slide7. Causes of pruritus Common dermatological disease with generalized pruritus as major symptoms:
Infestation: scabies, pediculosis & arthropod bites.
Inflammation: Eczema(AD,SD,CD),psoriasis, LP, urticaria, bullous diseases (BP)& drug eruption.
Autoimmune connective tissue disease: dermatomyositis & SLE.
Infections: bacterial (folliculitis),viral (varicella),fungal(tinea).
Neoplastic :cutaneous T cell lymphoma.
Others: Xerosis & pregnancy dermatoses.
g<br>
slide8. Causes of pruritus Common skin disease with localized pruritus:
LSC & NUMMULAR ECZEMA.
LP.
DH.
PEDICULOSIS.
Common body sites affected by localized pruritus:
Vulva.
Anal region: Oxyuriasis, LSC, CD , SD, anal discharge (fissure, sinus or piles).
Perineum.
Scalp: pediculosis, dermatoses (psoriasis, SD )
External auditory canal.<br>
slide9. Causes of the pruritus vulvae Common problem, affected girls :
Intravaginal causes:usualy in adult women
Candidiasis.
Trichomoniasis.
Bacterial vaginosis.
Atrophic vaginitis in old women. Extravaginal causes:
Candidiasis.
LSC.
Pediculosis pubis.
Oxyuriasis.
Others:LP,l lichen sclerosus atrophicus(LSA).
Idiopathic.<br>
slide10. Pruritus secondary to systemic diseases Liver disease: primary biliary cirrhosis ,HCV & HBV ,obstructive jaundice,
pruritus result from cholestasis &increase of serum bile salt ,but severity of itch not directly correlated with bilirubin level.
Central opioids effects.
Chronic renal failure: itching common in patients undergo dialysis, sever ,refractory to the treatment, improved after dialysis section.
Mechanism :multifactorial, including
Increase in the serum urea level.
Xerosis.
Secondary hyperparathyroidism( hypocalcemia) .
Increase in the mast cell & serum histamine level.
Central opioids effects.<br>
slide11. Pruritus secondary to systemic diseases Hematological disease: iron deficiency anemia , Polycythemia rubra Vera, Leukemia (CLL), lymphoma & myeloma.
Endocrine diseases:
Thyroid disease: hyper & hypothyroidism (xerosis ).
Diabetes mellitus: usually localized ,xerosis may cause.
Pregnancy : at 3rd trimester.
Malignancy: most common in Hodgkin's lymphoma( 30% of patients, may antedate other symptoms by years), other carcinoma e.g. breast & pancreatic CA.
HIV infection: mechanism unknown, may associated with eosinophilia.
Psychogenic :diagnosis by exclusion.<br>
slide12. Primary (idiopathic) pruritus Pruritus with no evidence of skin disease ,usually result from underlying systemic disorders ,but in the absent of any systemic abnormality then its consider idiopathic pruritus,
in Chronic idiopathic pruritus ,patient should undergo serial examination ,because pruritus ante date other symptoms of disease by long period example lymphoma & bullous pemphigoid .
Pruritus with no clinical signs could be result from mild degree of skin dryness (frequent use of soap ,prolong bath & irritation) ,many of these patients incorrectly put in systemic cause of pruritus.
Aquagenic pruritus: itch provoked by cooling of skin after emergence from bath could be idiopathic or PCV (after hot shower),continue for one hour.<br>
slide13. Management of pruritus History taken (see table).
Cutaneous and general examination.
Investigation: all patient with pruritus ;
CBC: eosinophilia ( worm infestation), anemia, polycythemia,RBS,serum iron & ferritin
ESR: low in PCV, high in malignancy.
Renal function test ; blood urea& serum creatinine.
Liver function test: alkaline phosphatase& bilirubin.
Lactate dehydrogenase (LDH).
Thyroid function test :TSH & thyroxin level.
HIV TEST.
GSE & GUE.<br>
slide15. Treatment of pruritus All types: lukewarm baths with nonsaop cleansers, moisturization skin while still damp (ointment rather than creams), moisturization at am & before bedtime avoids woolens & harsh fabrics & keep nails cut short.
Treatment underlying dermatological condition.
Idiopathic pruritus:
Topical: low potency CS, cooling agents( menthol, camphor) & Capsaicin.
Systemic :antihistamine ,nonsedative at am & sedative at pm e.g, Doxepin 10-25mg at bedtime.
Thalidomide in chronic refractory cases‘& CA patient: central sedative effects.
Opioid antagonists:1st line in pruritus result from liver & renal diseases e.g.Naltrexone & Nalfuraline(renal itch).<br>
slide16. Treatment of pruritus Antidepressants : 1st line psychogenic pruritus & PCV, e.g Amitriptyline &fluoxetine.
Others: colysteramine , activated charcoal(liver & renal disease)&Gabapentin( central sedation).
Photo therapy:UVB orPUVA
Acupuncture.
Psychological intervention.<br>
25/11/2018<br>
slide2. pruritus Pruritus : is unpleasant sensation elicit desire to itch or scratching.
Pruritus is most common dermatological complaint.
In general pruritus classify in to :
Primary pruritus (idiopathic).
Secondary pruritus: result from underlying primary dermatological disease or systemic disease, Its most common type.<br>
slide3. Pruritus Causes of secondary pruritus:
Dermatological disorders
Allergic or hypersensitive syndromes.
Medication.
Toxins associated with kidney and liver diseases.
Neurological disorders.
Systemic disease & Malignancy.
Psychiatric conditions. Pruritus could be localized or generalized.
Pruritus can present with or without cutaneous manifestation.
Localized pruritus without cutaneous manifestation : consider neuropathic itch &dysesthesia or psychogenic pruritus.
Localized pruritus with cutaneous manifestations:
Eczema(LSC)
LICHEN PLANUS.
PEDICULOSIS.
DERMATITIS HERBETIFORMIS.<br>
slide4. PATHOPHISOLOGY OF PRURITUS Pruritus result from activation of sensory nerve fibers at four sequential levels:
Peripheral nervous system: sensory nerve fibers at dermoepidermal junction, type C- fibers (small, slow, unmyelinated nerve fibers)
Dorsal root ganglia.
Spinal cord : ascending in spinothalamic tract.
Brain; thalamus and cortical level.<br>
slide5. PATHOPHISOLOGY OF PRURITUS Itching or scratching may either cause:
Inhibition of itch receptors by stimulation of ascending sensory nerve fibers witch inhibits itch at spinal cord.
Scratching interfere with itch fibers lying superficially in skin which may damaged directly by scratching .
Pruritus receptors units: removal of epidermis abolishes the perception of itch, so pruritus receptor unit located predominantly at this layer, LM.EXAMINATION show intraepidermal free non-specialized nerve ending in the granular layer( sub class of C-fiber),contain receptors that mediated itch .<br>
slide6. PATHOPHISOLOGY OF PRURITUS<br>
slide7. Causes of pruritus Common dermatological disease with generalized pruritus as major symptoms:
Infestation: scabies, pediculosis & arthropod bites.
Inflammation: Eczema(AD,SD,CD),psoriasis, LP, urticaria, bullous diseases (BP)& drug eruption.
Autoimmune connective tissue disease: dermatomyositis & SLE.
Infections: bacterial (folliculitis),viral (varicella),fungal(tinea).
Neoplastic :cutaneous T cell lymphoma.
Others: Xerosis & pregnancy dermatoses.
g<br>
slide8. Causes of pruritus Common skin disease with localized pruritus:
LSC & NUMMULAR ECZEMA.
LP.
DH.
PEDICULOSIS.
Common body sites affected by localized pruritus:
Vulva.
Anal region: Oxyuriasis, LSC, CD , SD, anal discharge (fissure, sinus or piles).
Perineum.
Scalp: pediculosis, dermatoses (psoriasis, SD )
External auditory canal.<br>
slide9. Causes of the pruritus vulvae Common problem, affected girls :
Intravaginal causes:usualy in adult women
Candidiasis.
Trichomoniasis.
Bacterial vaginosis.
Atrophic vaginitis in old women. Extravaginal causes:
Candidiasis.
LSC.
Pediculosis pubis.
Oxyuriasis.
Others:LP,l lichen sclerosus atrophicus(LSA).
Idiopathic.<br>
slide10. Pruritus secondary to systemic diseases Liver disease: primary biliary cirrhosis ,HCV & HBV ,obstructive jaundice,
pruritus result from cholestasis &increase of serum bile salt ,but severity of itch not directly correlated with bilirubin level.
Central opioids effects.
Chronic renal failure: itching common in patients undergo dialysis, sever ,refractory to the treatment, improved after dialysis section.
Mechanism :multifactorial, including
Increase in the serum urea level.
Xerosis.
Secondary hyperparathyroidism( hypocalcemia) .
Increase in the mast cell & serum histamine level.
Central opioids effects.<br>
slide11. Pruritus secondary to systemic diseases Hematological disease: iron deficiency anemia , Polycythemia rubra Vera, Leukemia (CLL), lymphoma & myeloma.
Endocrine diseases:
Thyroid disease: hyper & hypothyroidism (xerosis ).
Diabetes mellitus: usually localized ,xerosis may cause.
Pregnancy : at 3rd trimester.
Malignancy: most common in Hodgkin's lymphoma( 30% of patients, may antedate other symptoms by years), other carcinoma e.g. breast & pancreatic CA.
HIV infection: mechanism unknown, may associated with eosinophilia.
Psychogenic :diagnosis by exclusion.<br>
slide12. Primary (idiopathic) pruritus Pruritus with no evidence of skin disease ,usually result from underlying systemic disorders ,but in the absent of any systemic abnormality then its consider idiopathic pruritus,
in Chronic idiopathic pruritus ,patient should undergo serial examination ,because pruritus ante date other symptoms of disease by long period example lymphoma & bullous pemphigoid .
Pruritus with no clinical signs could be result from mild degree of skin dryness (frequent use of soap ,prolong bath & irritation) ,many of these patients incorrectly put in systemic cause of pruritus.
Aquagenic pruritus: itch provoked by cooling of skin after emergence from bath could be idiopathic or PCV (after hot shower),continue for one hour.<br>
slide13. Management of pruritus History taken (see table).
Cutaneous and general examination.
Investigation: all patient with pruritus ;
CBC: eosinophilia ( worm infestation), anemia, polycythemia,RBS,serum iron & ferritin
ESR: low in PCV, high in malignancy.
Renal function test ; blood urea& serum creatinine.
Liver function test: alkaline phosphatase& bilirubin.
Lactate dehydrogenase (LDH).
Thyroid function test :TSH & thyroxin level.
HIV TEST.
GSE & GUE.<br>
slide15. Treatment of pruritus All types: lukewarm baths with nonsaop cleansers, moisturization skin while still damp (ointment rather than creams), moisturization at am & before bedtime avoids woolens & harsh fabrics & keep nails cut short.
Treatment underlying dermatological condition.
Idiopathic pruritus:
Topical: low potency CS, cooling agents( menthol, camphor) & Capsaicin.
Systemic :antihistamine ,nonsedative at am & sedative at pm e.g, Doxepin 10-25mg at bedtime.
Thalidomide in chronic refractory cases‘& CA patient: central sedative effects.
Opioid antagonists:1st line in pruritus result from liver & renal diseases e.g.Naltrexone & Nalfuraline(renal itch).<br>
slide16. Treatment of pruritus Antidepressants : 1st line psychogenic pruritus & PCV, e.g Amitriptyline &fluoxetine.
Others: colysteramine , activated charcoal(liver & renal disease)&Gabapentin( central sedation).
Photo therapy:UVB orPUVA
Acupuncture.
Psychological intervention.<br>