
Role of Inflammation in Oral cancer

























Description: Role of Inflammation in Oral cancer Assist.prof.Layla Sabri There is evidence that chronic inflammation brought about by persistent chemical, bacterial or viral agents is a risk factor for cancer . For example, chronic infection with
Related Topics
Download Presentation
"Role of Inflammation in Oral cancer" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Role of Inflammation in Oral cancer Assist.prof.Layla Sabri<br>
slide2. There is evidence that chronic inflammation brought about by persistent chemical, bacterial or viral agents is a risk factor for cancer .
For example, chronic infection with Helicobacter pylori is associated with gastric cancer, chronic viral hepatitis B or C is associated with hepatocellular cancer, and chronic pancreatitis or chronic prostatitis of non-specific origin are associated with cancers of the pancreas or of the prostate, respectively<br>
slide3. Dysregulated inflammatory processes brought about by certain autoimmune reactions, or by minor, persistent repetitive soft tissue trauma, also impose a risk of cancer .
Cytokines, chemokines, prostaglandins and reactive oxygen and nitrogen radicals accumulate in the microenvironment of tissues affected by chronic inflammation.
If persistent, these inflammatory factors have the capacity to induce cell proliferation and to promote prolonged cell survival through
1-activation of oncogenes and
2-inactivation of tumour-suppressor genes.
This may result in genetic instability with an increased risk of cancer<br>
slide4. In genetically altered cells at different stages of transformation, the intrinsic cellular circuits that bring about increased cell proliferation and cell survival may also bring about the production and secretion of inflammatory mediators.
These biological mediators generate an inflammatory microenvironment that further increase cell survival and proliferation of the transformed cells, as well as promoting angiogenesis and evasion of protective immune responses<br>
slide5. Once an inflammatory microenvironment has been established, reciprocal interactions between the evolving tumour cells and their stromal cells sustain cancer cell proliferation and promote the progression of the tumour . Thus, common transcription factors that normally regulate genes producing inflammatory mediators, and genes controlling cell survival and proliferation are the link between cancer and inflammation .
However, as chronic inflammatory processes of the oral mucosa are common and as cancers of the oral mucosa are relatively uncommon, it is evident that inflammatory processes on their own only rarely induce cancer development .<br>
slide6. aim of this lecture is to
1- outline the association between inflammation and cancer and
2- to shed light on the role of inflammation in the pathogenesis of oral squamous cell carcinoma<br>
slide7. Inflammation-driven carcinogenesis and cancer-induced inflammation
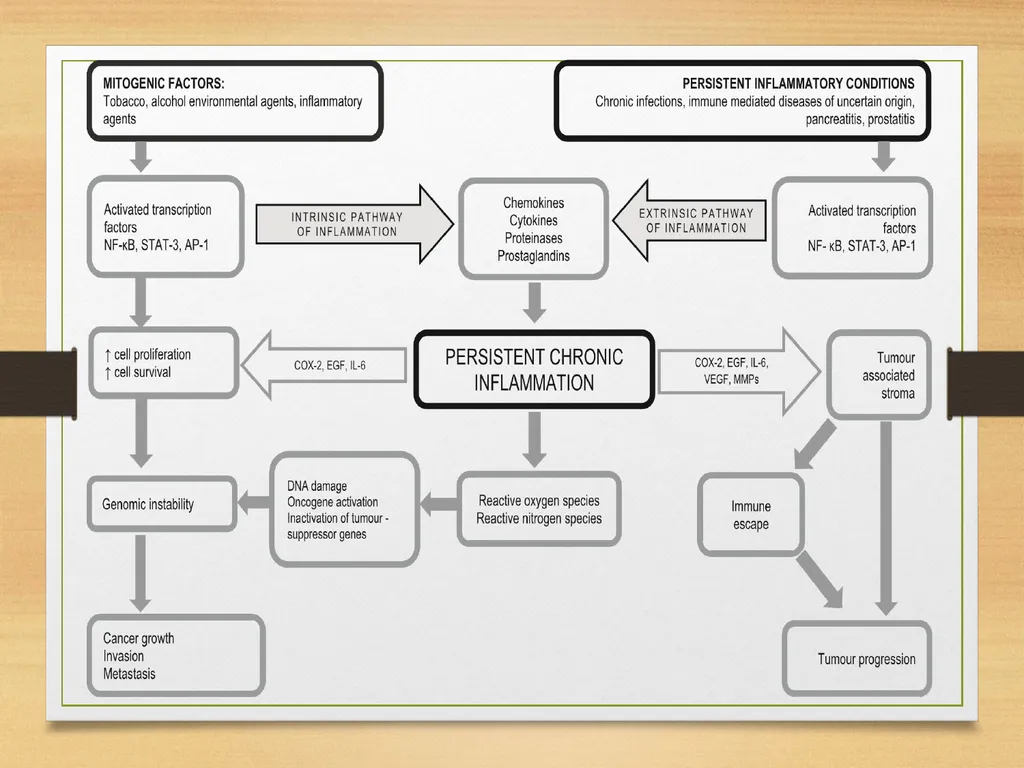
Tobacco, alcohol, certain environmental and infectious agents and inflammatory mediators have the capacity to activate
1-the nuclear signal transducers and activators of transcription-3 (STAT-3),
2-the activator protein-1 (AP-1) and
3-the nuclear factor-kB (NF-kB).
In turn, these transcription factors activate
oncogenes regulating apoptosis, cell proliferation and angiogenesis;
And
genes regulating the production of inflammatory mediators including growth factors, cytokines, prostaglandins and proteinases<br>
slide8. Thus, through these common transcription factors, cancer cells, concurrently induce both inflammation and uncontrolled self proliferation (intrinsic pathway) . The inflammatory microenvironment in turn, is conducive to tumour progression.
This intrinsic pathway explains why inflammatory cells and inflammatory mediators are almost invariably present in the microenvironment of all cancer types .<br>
slide9. In addition, there is cross talk between cancer cells and noncancer cells within the tumour-associated stroma. The cancer cells induce the secretion of inflammatory mediators by immunoinflammatory cells within the stroma; the inflammatory mediators in turn induce cancer cell proliferation and survival, and the angiogenesis essential to tumour progression
This might explain why cancers that are rapidly progressing, microscopically show an intense inflammatory infiltrate<br>
slide10. In inflamed non-cancerous tissues the transcription factors mentioned above may bring about an increase in cell proliferation and prolonged cell survival that may favour initial cancerous transformation (extrinsic pathway).
Inflammatory cells may secrete reactive oxygen species and reactive nitrogen species that have the capacity to cause direct DNA damage, and to dysregulate mechanisms of DNA repair, of cell-cycle checkpoint control and of apoptosis. This brings about a genomic instability favouring the evolution of random mutations and development of cancer.<br>
slide11. Thus, inflammatory pathways activated by the chronic inflammation of chronic infections, autoimmune diseases, or by repetitive and habit-related chemical trauma may not only promote cancer progression but may also constitute the risk factors of initial cell transformation<br>
slide13. Tumour-associated stroma
There is a reciprocal signalling interaction between cancer cells and stromal cells within the tumour microenvironment.
The tumour-associated stromal cell population comprises distinctive cancer-associated cell types including fibroblasts, endothelial cells, pericytes, tissue-specific stem cells, bone marrow derived stem and progenitor cells and immuno-inflammatory cells.
In established cancers, these distinctive stromal cells support cancer progression<br>
slide14. Tumour-associated inflammatory cells include myeloid dendritic cells, macrophage subtypes (M1 and M2), mast cells, neutrophils, and T and B lymphocytes.
These cells secrete chemokines, prostaglandins, proteinases, and complement components that collectively bring about an exaggerated inflammatory state, and that promote cancer growth, tissue invasion and metastasis
In addition to the above mentioned immuno-inflammatory cells, tumour-associated stroma contains partially differentiated myeloid (progenitor) cells which have the capacity to support tumour progression<br>
slide15. .The myeloid-derived suppressor cells are an important subclass of these partially differentiated myeloid cells, and are the immature myeloid precursors of dendritic cells, macrophages and granulocytes and express both the macrophage marker CD11b and the neutrophil marker Gr1.<br>
slide16. cancer cells escape immunity-mediated killing
Myeloid-derived suppressor cells are induced by tumour-secreted inflammatory factors including vascular endothelial growth factor, granulocyte-monocyte colony stimulating factors, IL-1b, IL-6, COX2-derived PGE-2, and S100A8/A9 proteins and have the capacity to suppress the activities of natural killer cells and cytotoxic T lymphocytes, thus enabling cancer cells to escape immunity-mediated killing<br>
slide17. 1-Myeloid-derived suppressor cells,
through the secretion of high-levels of reactive oxidative species and of reactive nitrogen species, mediate immune tolerance of cancer cells in the local microenvironment. They mediate T-cell anergy to tumour-specific antigens by
inducing non-specific suppression of T-cell function and apoptosis of T-cells.<br>
slide18. 2-Myeloid-derived suppressor cells also downregulate effective antitumour cell-mediated immunity through induction of regulatory T cells, and promote IL-10-driven suppression of anti-tumour immune responses<br>
slide19. On the other hand, some immuno-inflammatory responses, particularly Th1 and possibly Th17 responses within the tumour-associated stroma represent anti-tumour protective reactions aimed at eradicating tumour cells by cytotoxic T lymphocytes (CTL) and natural killer cells
Thus, the cancer-associated inflammatory infiltrate has the capacity either to promote or to inhibit cancer growth, and it appears that the transcription factor in macrophages plays a key role in determining whether promotion or inhibition of cancer growth will predominate<br>
slide20. Chronic inflammation and oral squamous cell carcinoma<br>
slide21. Approximately 15% of cancers are attributable to the inflammatory process, and growing evidence supports an association between oral squamous cell carcinoma (OSCC) and chronic inflammation.
Different oral inflammatory conditions, such as oral lichen planus (OLP), submucous fibrosis, and oral discoid lupus, are all predisposing for the development of OSCC.
The microenvironment of these conditions contains various transcription factors and inflammatory mediators with the ability to induce proliferation, epithelial-to-mesenchymal transition (EMT), and invasion of genetically predisposed lesions, thereby promoting tumor development<br>
slide22. Chronic inflammation and oral squamous cell carcinoma
There are a number of oral inflammatory conditions that have been proposed as being implicated in the pathogenesis of oral squamous cell carcinoma:
1- oral submucous fibrosis,
2-oral lichen planus,
3-discoid lupus erythematosus,
4-oral ulcers related to repetitive tissue injury and
5-chronic periodontal disease<br>
slide23. Oral submucous fibrosis is a potentially malignant condition that is causally associated with the habitual use of areca nut/betel quid. It is characterised histopathologically by dense fibrosis of the lamina propria at the affected site, by a juxta-epithelial inflammatory reaction, and by atrophy or hyperplasia of the overlying epithelium. The inflammatory infiltrate comprises predominantly lymphocytes, but also plasma cells and macrophages<br>
slide24. Oral lichen planus has been associated, although debatably, with an increased risk of oral squamous cell carcinoma . It has been suggested that the unique profile of the cytokines and chemokines that initiate oral lichen planus may also on occasion be a factor in the transformation of oral lichen planus to oral squamous cell carcinoma
Oral lichen planus is characterised by a T cell-mediated chronic immuno-inflammatory reaction against an as yet undefined antigen within the basal cell layer of the oral epithelium, and by upregulated expression of several inflammatory mediators including TGF-b, TNF-a, IL-6, COX-2 and MMP-7<br>
slide25. It is probable that in those rare cases of oral lichen planus that evolve to OSCC, the local inflammatory microenvironment provides the signals that activate transcription factors that not only promote proliferation of the epithelial cells affected by the lichen planus but also promote angiogenesis, invasion and metastasis<br>
slide26. In established oral squamous cell carcinoma, TNF-a and IL-6 are produced by malignant keratinocytes, and by stromal fibroblasts and macrophages . These cytokines not only increase tumour cell proliferation and survival, but also promote tumour growth through modifying the expression of cell-adhesion molecules and extracellular matrix proteins, and by stimulation of angiogenesis<br>
slide27. Mast Cells in Oral Squamous Cell Carcinoma
Squamous cell carcinoma is a malignant tumor that derives from covering epithelium, including those of the oral mucosa. It is tumor type represents approximately 90% of all malignant tumors from the oral region and remains a serious oral health problem at global level<br>
slide28. Angiogenesis or neovascularization is an important component of several biological processes, in both physiologic and pathologic conditions, such as neoplasms . Angiogenesis is known to aid progression and metastasis in different malignant tumors including the tumors of the oral cavity .
MCs stimulate neovascularization through
1-the release of angiogenic factors, such as VEGF, or different substances with angiogenic properties, such as tryptase, IL-8, tumor necrosis factor (TNF), heparin, and histamine.<br>
slide29. Mast cell heparin induces vessel proliferation and increases basic FGF half-life, which is a strong angiogenic substance, thus promoting tumor angiogenesis and facilitating the local invasion. Interleukin-1 (IL-1) leads to epithelial proliferation<br>
slide30. Mast cells are also
2- a rich source of proteases, especially tryptase and chymase, which directly degrade the extracellular matrix through their proteolytic activity and indirectly stimulate angiogenesis and facilitate invasion and metastasis through extracellular matrix remodeling.
3-Also, the matrix metalloproteinases produced by MCs may contribute to extracellular matrix degradation.
thus, MCs may have an impact both on the development of the primary tumor and on the following tumor progression and metastases in squamous cell carcinomas of the oral cavity<br>
slide31. Besides the role of MCs in maintaining homeostasis , several studies described an association between mast cell density and different malignant tumors, amongst which the oral squamous cells carcinoma is considered.
The presence of MCs at the periphery of the tumor areas was reported for the first time by Westphal in 1891, and since then this observation was conermed by numerous researchers .<br>
slide32. the increase in mast cell density is associated with poor prognosis in different malignant tumors, indicating their role in tumor progression .
Recent data suggest that mast cell accumulation at the periphery of tumor areas and the release of proangiogenic factors may represent a tumor-host interaction that probably favors tumor progression<br>
slide33. Summary
The link between cancer and inflammation is specific transcription factors that once activated, have the capacity to enhance the expression of genes regulating the production of inflammatory mediators and to enhance the expression of genes regulating cell survival and proliferation, as well as mediating angiogenesis, immune evasion and metastasis<br>
slide34. There is clear evidence that persistent inflammation promotes cell proliferation and may induce DNA damage; and that at initial stages of tumorigenesis, inflammatory factors mediate the development of a tumour associated stroma. In turn, activated cells in this stroma promote angiogenesis, cancer growth and metastasis, and mediate immune evasion.<br>
slide2. There is evidence that chronic inflammation brought about by persistent chemical, bacterial or viral agents is a risk factor for cancer .
For example, chronic infection with Helicobacter pylori is associated with gastric cancer, chronic viral hepatitis B or C is associated with hepatocellular cancer, and chronic pancreatitis or chronic prostatitis of non-specific origin are associated with cancers of the pancreas or of the prostate, respectively<br>
slide3. Dysregulated inflammatory processes brought about by certain autoimmune reactions, or by minor, persistent repetitive soft tissue trauma, also impose a risk of cancer .
Cytokines, chemokines, prostaglandins and reactive oxygen and nitrogen radicals accumulate in the microenvironment of tissues affected by chronic inflammation.
If persistent, these inflammatory factors have the capacity to induce cell proliferation and to promote prolonged cell survival through
1-activation of oncogenes and
2-inactivation of tumour-suppressor genes.
This may result in genetic instability with an increased risk of cancer<br>
slide4. In genetically altered cells at different stages of transformation, the intrinsic cellular circuits that bring about increased cell proliferation and cell survival may also bring about the production and secretion of inflammatory mediators.
These biological mediators generate an inflammatory microenvironment that further increase cell survival and proliferation of the transformed cells, as well as promoting angiogenesis and evasion of protective immune responses<br>
slide5. Once an inflammatory microenvironment has been established, reciprocal interactions between the evolving tumour cells and their stromal cells sustain cancer cell proliferation and promote the progression of the tumour . Thus, common transcription factors that normally regulate genes producing inflammatory mediators, and genes controlling cell survival and proliferation are the link between cancer and inflammation .
However, as chronic inflammatory processes of the oral mucosa are common and as cancers of the oral mucosa are relatively uncommon, it is evident that inflammatory processes on their own only rarely induce cancer development .<br>
slide6. aim of this lecture is to
1- outline the association between inflammation and cancer and
2- to shed light on the role of inflammation in the pathogenesis of oral squamous cell carcinoma<br>
slide7. Inflammation-driven carcinogenesis and cancer-induced inflammation
Tobacco, alcohol, certain environmental and infectious agents and inflammatory mediators have the capacity to activate
1-the nuclear signal transducers and activators of transcription-3 (STAT-3),
2-the activator protein-1 (AP-1) and
3-the nuclear factor-kB (NF-kB).
In turn, these transcription factors activate
oncogenes regulating apoptosis, cell proliferation and angiogenesis;
And
genes regulating the production of inflammatory mediators including growth factors, cytokines, prostaglandins and proteinases<br>
slide8. Thus, through these common transcription factors, cancer cells, concurrently induce both inflammation and uncontrolled self proliferation (intrinsic pathway) . The inflammatory microenvironment in turn, is conducive to tumour progression.
This intrinsic pathway explains why inflammatory cells and inflammatory mediators are almost invariably present in the microenvironment of all cancer types .<br>
slide9. In addition, there is cross talk between cancer cells and noncancer cells within the tumour-associated stroma. The cancer cells induce the secretion of inflammatory mediators by immunoinflammatory cells within the stroma; the inflammatory mediators in turn induce cancer cell proliferation and survival, and the angiogenesis essential to tumour progression
This might explain why cancers that are rapidly progressing, microscopically show an intense inflammatory infiltrate<br>
slide10. In inflamed non-cancerous tissues the transcription factors mentioned above may bring about an increase in cell proliferation and prolonged cell survival that may favour initial cancerous transformation (extrinsic pathway).
Inflammatory cells may secrete reactive oxygen species and reactive nitrogen species that have the capacity to cause direct DNA damage, and to dysregulate mechanisms of DNA repair, of cell-cycle checkpoint control and of apoptosis. This brings about a genomic instability favouring the evolution of random mutations and development of cancer.<br>
slide11. Thus, inflammatory pathways activated by the chronic inflammation of chronic infections, autoimmune diseases, or by repetitive and habit-related chemical trauma may not only promote cancer progression but may also constitute the risk factors of initial cell transformation<br>
slide13. Tumour-associated stroma
There is a reciprocal signalling interaction between cancer cells and stromal cells within the tumour microenvironment.
The tumour-associated stromal cell population comprises distinctive cancer-associated cell types including fibroblasts, endothelial cells, pericytes, tissue-specific stem cells, bone marrow derived stem and progenitor cells and immuno-inflammatory cells.
In established cancers, these distinctive stromal cells support cancer progression<br>
slide14. Tumour-associated inflammatory cells include myeloid dendritic cells, macrophage subtypes (M1 and M2), mast cells, neutrophils, and T and B lymphocytes.
These cells secrete chemokines, prostaglandins, proteinases, and complement components that collectively bring about an exaggerated inflammatory state, and that promote cancer growth, tissue invasion and metastasis
In addition to the above mentioned immuno-inflammatory cells, tumour-associated stroma contains partially differentiated myeloid (progenitor) cells which have the capacity to support tumour progression<br>
slide15. .The myeloid-derived suppressor cells are an important subclass of these partially differentiated myeloid cells, and are the immature myeloid precursors of dendritic cells, macrophages and granulocytes and express both the macrophage marker CD11b and the neutrophil marker Gr1.<br>
slide16. cancer cells escape immunity-mediated killing
Myeloid-derived suppressor cells are induced by tumour-secreted inflammatory factors including vascular endothelial growth factor, granulocyte-monocyte colony stimulating factors, IL-1b, IL-6, COX2-derived PGE-2, and S100A8/A9 proteins and have the capacity to suppress the activities of natural killer cells and cytotoxic T lymphocytes, thus enabling cancer cells to escape immunity-mediated killing<br>
slide17. 1-Myeloid-derived suppressor cells,
through the secretion of high-levels of reactive oxidative species and of reactive nitrogen species, mediate immune tolerance of cancer cells in the local microenvironment. They mediate T-cell anergy to tumour-specific antigens by
inducing non-specific suppression of T-cell function and apoptosis of T-cells.<br>
slide18. 2-Myeloid-derived suppressor cells also downregulate effective antitumour cell-mediated immunity through induction of regulatory T cells, and promote IL-10-driven suppression of anti-tumour immune responses<br>
slide19. On the other hand, some immuno-inflammatory responses, particularly Th1 and possibly Th17 responses within the tumour-associated stroma represent anti-tumour protective reactions aimed at eradicating tumour cells by cytotoxic T lymphocytes (CTL) and natural killer cells
Thus, the cancer-associated inflammatory infiltrate has the capacity either to promote or to inhibit cancer growth, and it appears that the transcription factor in macrophages plays a key role in determining whether promotion or inhibition of cancer growth will predominate<br>
slide20. Chronic inflammation and oral squamous cell carcinoma<br>
slide21. Approximately 15% of cancers are attributable to the inflammatory process, and growing evidence supports an association between oral squamous cell carcinoma (OSCC) and chronic inflammation.
Different oral inflammatory conditions, such as oral lichen planus (OLP), submucous fibrosis, and oral discoid lupus, are all predisposing for the development of OSCC.
The microenvironment of these conditions contains various transcription factors and inflammatory mediators with the ability to induce proliferation, epithelial-to-mesenchymal transition (EMT), and invasion of genetically predisposed lesions, thereby promoting tumor development<br>
slide22. Chronic inflammation and oral squamous cell carcinoma
There are a number of oral inflammatory conditions that have been proposed as being implicated in the pathogenesis of oral squamous cell carcinoma:
1- oral submucous fibrosis,
2-oral lichen planus,
3-discoid lupus erythematosus,
4-oral ulcers related to repetitive tissue injury and
5-chronic periodontal disease<br>
slide23. Oral submucous fibrosis is a potentially malignant condition that is causally associated with the habitual use of areca nut/betel quid. It is characterised histopathologically by dense fibrosis of the lamina propria at the affected site, by a juxta-epithelial inflammatory reaction, and by atrophy or hyperplasia of the overlying epithelium. The inflammatory infiltrate comprises predominantly lymphocytes, but also plasma cells and macrophages<br>
slide24. Oral lichen planus has been associated, although debatably, with an increased risk of oral squamous cell carcinoma . It has been suggested that the unique profile of the cytokines and chemokines that initiate oral lichen planus may also on occasion be a factor in the transformation of oral lichen planus to oral squamous cell carcinoma
Oral lichen planus is characterised by a T cell-mediated chronic immuno-inflammatory reaction against an as yet undefined antigen within the basal cell layer of the oral epithelium, and by upregulated expression of several inflammatory mediators including TGF-b, TNF-a, IL-6, COX-2 and MMP-7<br>
slide25. It is probable that in those rare cases of oral lichen planus that evolve to OSCC, the local inflammatory microenvironment provides the signals that activate transcription factors that not only promote proliferation of the epithelial cells affected by the lichen planus but also promote angiogenesis, invasion and metastasis<br>
slide26. In established oral squamous cell carcinoma, TNF-a and IL-6 are produced by malignant keratinocytes, and by stromal fibroblasts and macrophages . These cytokines not only increase tumour cell proliferation and survival, but also promote tumour growth through modifying the expression of cell-adhesion molecules and extracellular matrix proteins, and by stimulation of angiogenesis<br>
slide27. Mast Cells in Oral Squamous Cell Carcinoma
Squamous cell carcinoma is a malignant tumor that derives from covering epithelium, including those of the oral mucosa. It is tumor type represents approximately 90% of all malignant tumors from the oral region and remains a serious oral health problem at global level<br>
slide28. Angiogenesis or neovascularization is an important component of several biological processes, in both physiologic and pathologic conditions, such as neoplasms . Angiogenesis is known to aid progression and metastasis in different malignant tumors including the tumors of the oral cavity .
MCs stimulate neovascularization through
1-the release of angiogenic factors, such as VEGF, or different substances with angiogenic properties, such as tryptase, IL-8, tumor necrosis factor (TNF), heparin, and histamine.<br>
slide29. Mast cell heparin induces vessel proliferation and increases basic FGF half-life, which is a strong angiogenic substance, thus promoting tumor angiogenesis and facilitating the local invasion. Interleukin-1 (IL-1) leads to epithelial proliferation<br>
slide30. Mast cells are also
2- a rich source of proteases, especially tryptase and chymase, which directly degrade the extracellular matrix through their proteolytic activity and indirectly stimulate angiogenesis and facilitate invasion and metastasis through extracellular matrix remodeling.
3-Also, the matrix metalloproteinases produced by MCs may contribute to extracellular matrix degradation.
thus, MCs may have an impact both on the development of the primary tumor and on the following tumor progression and metastases in squamous cell carcinomas of the oral cavity<br>
slide31. Besides the role of MCs in maintaining homeostasis , several studies described an association between mast cell density and different malignant tumors, amongst which the oral squamous cells carcinoma is considered.
The presence of MCs at the periphery of the tumor areas was reported for the first time by Westphal in 1891, and since then this observation was conermed by numerous researchers .<br>
slide32. the increase in mast cell density is associated with poor prognosis in different malignant tumors, indicating their role in tumor progression .
Recent data suggest that mast cell accumulation at the periphery of tumor areas and the release of proangiogenic factors may represent a tumor-host interaction that probably favors tumor progression<br>
slide33. Summary
The link between cancer and inflammation is specific transcription factors that once activated, have the capacity to enhance the expression of genes regulating the production of inflammatory mediators and to enhance the expression of genes regulating cell survival and proliferation, as well as mediating angiogenesis, immune evasion and metastasis<br>
slide34. There is clear evidence that persistent inflammation promotes cell proliferation and may induce DNA damage; and that at initial stages of tumorigenesis, inflammatory factors mediate the development of a tumour associated stroma. In turn, activated cells in this stroma promote angiogenesis, cancer growth and metastasis, and mediate immune evasion.<br>