
SEROLOGY LESSON -11 By OMKAR YADAV INSP/PH Upon
























Description: SEROLOGY LESSON -11 By OMKAR YADAV INSPPH Upon completion of this lesson, you will be able to: List of SEROLOGY TEST: Determination of Widal Determination of RA Factor Determination of CRP Determination of ASO Determination of HIV
Related Topics
Download Presentation
"SEROLOGY LESSON -11 By OMKAR YADAV INSP/PH Upon" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. SEROLOGY LESSON -11 By
OMKAR YADAV
INSP/PH<br>
slide2. Upon completion of this lesson, you will be able to:
List of SEROLOGY TEST:
Determination of Widal
Determination of RA Factor
Determination of CRP
Determination of ASO
Determination of HIV
Determination of VDRL
7.Determination of Hepatitis (Hepatitis B, C, )<br>
slide3. INTRODUCTION:-
Serology is the scientific study of blood serum and other body fluids. In practice, the term usually refers to the diagnostic identification of antibodies in the serum. Such antibodies are typically formed in response to an infection (against a given microorganism), against other foreign proteins (in response, for example, to a mismatched blood transfusion), or to one's own proteins (in instances of autoimmune disease).Serological tests may be performed for diagnostic purposes when an infection is suspected, in rheumatic illnesses, and in many other situations, such as checking an individual's blood type. Serology blood tests help to diagnose patients with certain immune deficiencies associated with the lack of antibodies, such as X-linked a gammaglobulinemia. In such cases, tests for antibodies will be consistently negative.
There are several serology techniques that can be used depending on the antibodies being studied. These include: ELISA, agglutination, precipitation, complement-fixation, and fluorescent antibodies<br>
slide4. WIDAL TEST
(QUALITATIVE SLIDE AGGLUTINATION METHOD)
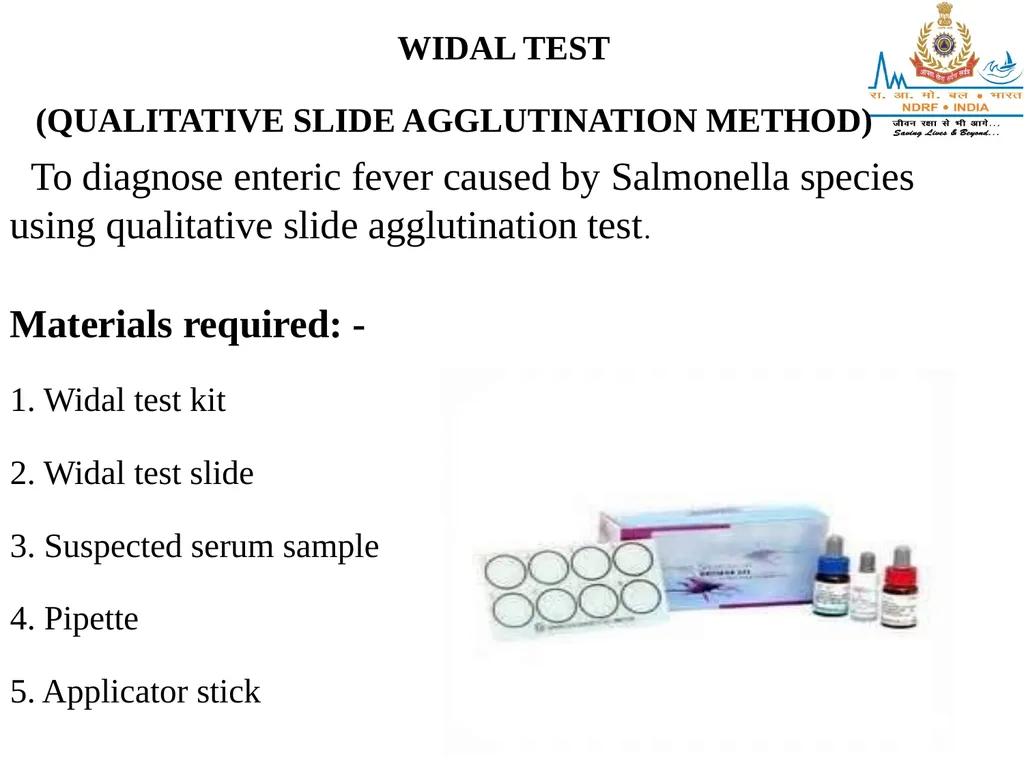
To diagnose enteric fever caused by Salmonella species using qualitative slide agglutination test. Materials required: -
1. Widal test kit
2. Widal test slide
3. Suspected serum sample
4. Pipette
5. Applicator stick<br>
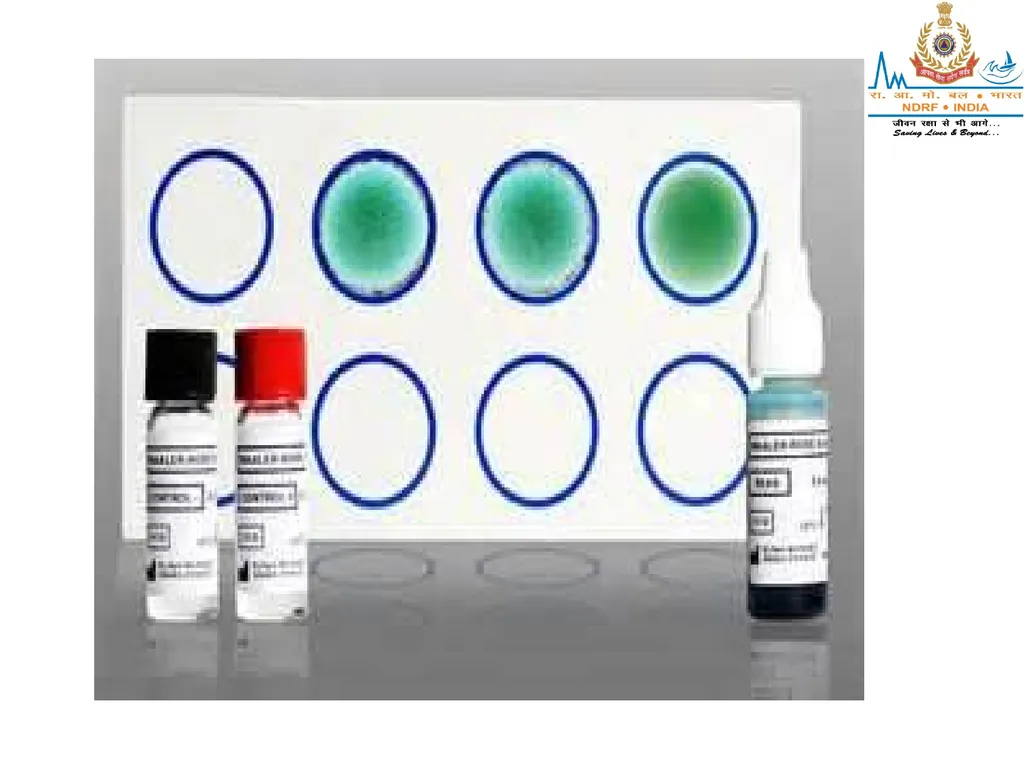
slide5. Procedure: - 1. A clean glass marked with six circles was taken.
2. The circles were labeled as “H”, “O”, “A”, “B”, positive control and negative control from the first circle to the last.
3. One drop of undiluted serum was placed in the first four circles with the help of a sterile pasture pipette.
4. One drop of positive control serum and one drop of negative control serum was placed in the fifth and the last circle respectively.
5. One drop of H antigen was added to the first circle and one drop of Salmonella typhi O antigen was added in the second circle. Salmonella paratyphi A antigen and Salmonella paratyphi B antigen were added in the third and fourth circles respectively.<br>
slide6. 6. One drop of ‘H’ antigen was placed at the fifth circle and sixth circle.
7. With separate applicator sticks serum and the antigen was mixed together and was spread well to fill the whole of the individual circle. Then slide was observed for agglutination.
Result: -
The given test patient’s serum is positive for typhoid.
The given test patient’s serum is positive for paratyphoid A or B
The given test patient’s serum is negative for typhoid and paratyphoid<br>
slide7. SPECIMEN COLLECTION AND PREPARATION:
No special preparation of the patient is required prior to specimen collection by approved techniques. Only serum must be used for testing. Should a delay in testing occur, store the sample at 2-80C. Samples can be stored for upto a week. Do not use hemolysed serum.
ADDITIONAL MATERIAL REQUIRED
Stop watch, Test tubes, a high intensity direct light source, Isotonic saline.<br>
slide9. TEST PROCEDURE
Bring reagent and samples to room temperature before use.
Qualitative Method:
1. Pipette one drop (40 μl) of serum onto the glass slide using the disposable pipette provided with kit.
2. Add one drop of RHELAX-RF™ latex reagent to the drop of serum on the slide. Do not let the dropper tip touch the liquid on the slide.
3. Using a mixing stick, mix the serum and RHELAX-RF™ latex reagent uniformly over the entire circle.
4. Immediately start a stopwatch. Rock the slide gently, back and forth, observing for agglutination macroscopically at two minutes.<br>
slide10. CRP (C - reactive protein)
SUMMARY
CRP usually appears in the sera of patients in the acute stages of a number of inflammatory conditions such as most bacterial and some viral infections; acute rheumatoid fever with or without carditis; rheumatoid arthritis and most other collagen diseases; and in a number of other conditions characterized by inflammation. CRP is considered to be a sensitive indicator of inflammation. Changes in the serum level of CRP with time from the same patient can be used as an index of recovery. The use of the CRP test to measure the effectiveness of therapy is of great clinical significance in cases such as acute rheumatoid fever.<br>
slide11. MATERIALS REQUIRED
1. Serological pipettes.
2. Test tubes 12x75 mm.
3. Timing device.
4. Distilled water<br>
slide12. STORAGE & STABILITY
When not in use, store reagents and controls at 2º to 8º C. DO NOT FREEZE. Prior to use, allow reagents and controls to warm up to room temperature. Biological indication of product instability is evidenced by inappropriate reaction of the latex reagent with the corresponding positive and negative control sera.
PRECAUTIONS
1. The preservative sodium azide may react with metal plumbing to from explosive metal oxides. In disposal, flush with a large a volume of water to prevent metal azide build up.
2. Human control sera were tested for the presence of Hepatitis B Surface Antigen (HBsAg) and anti-HIV antibody and found to be negative. However, all materials should still be handled as infectious agents.<br>
slide13. TEST PROCEDURE
Method I (Qualitative)
1. Bring all reagents, controls and serum samples to room temperature.
2. Shake the CRP latex reagent gently before use. Deliver one drop of reagent to the test circle. Using the disposable pipettes, add one drop of the undiluted patient serum onto the same circle and mix both together with the paddle end of the pipette.
3. Positive and negative controls should be run with each series of test serums in the same way as in Step 2.
4. Rotate slide back and forth for 2 minutes and read result under an indirect oblique light source<br>
slide14. Method II (Semi-Quantitative method):
1. Set up at least 5 test tubes and label 1:2, 1:4, 1:8, 1:16, 1:32, and etc.
2. Use diluted Glycine-Saline Buffer to serially dilute sample to be tittered according to standard laboratory practice.
3. Repeat all steps as in Qualitative Method using these new samples.<br>
slide15. RESULTS:
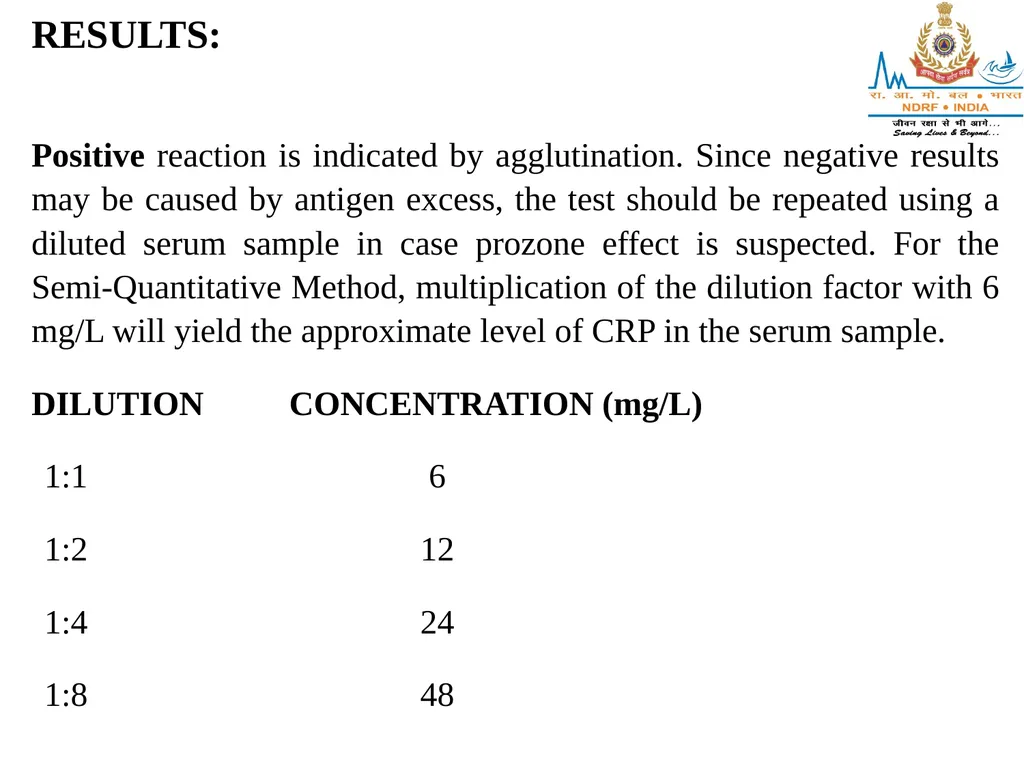
Positive reaction is indicated by agglutination. Since negative results may be caused by antigen excess, the test should be repeated using a diluted serum sample in case prozone effect is suspected. For the Semi-Quantitative Method, multiplication of the dilution factor with 6 mg/L will yield the approximate level of CRP in the serum sample.
DILUTION CONCENTRATION (mg/L)
1:1 6
1:2 12
1:4 24
1:8 48<br>
slide16. LIMITATIONS OF THE PROCEDURE
1. The strength of the agglutination reaction is not indicative of the CRP concentration. Weak reactions may occur with slightly elevated or markedly elevated concentrations.
2. A prozone phenomena (antigen excess) may cause false negatives. It is advisable, therefore, to check all negative sera by retesting at a 1:10 dilution.
3. Reaction times longer than specified may produce apparent false reactions due to a drying effect.
4. Strongly lipemic or contaminated sera can cause false positive reactions.
5. Only serum should be used in this test.
EXPECTED VALUES
Normal adult levels of CRP are reported to be less than 12 mg/L. Trace levels of CRP had been reported in the sera of apparently healthy adults3 and normal children4. The CRP level can increase significantly (>10 fold) above the normal values with the onset of a substantial inflammatory stimulus.<br>
slide17. HIV
HIV Testing Introduction
Human immunodeficiency virus (HIV) is the virus that causes acquired immune deficiency syndrome (AIDS). HIV destroys the body's immune system and eventually leads to AIDS. People with AIDS develop many diseases and "opportunistic" infections (such as pneumonia, tuberculosis, cancer, and skin infections) that may ultimately lead to death. Prevention is critical. There is no cure for HIV/AIDS, but currently, there are effective treatments that can drastically slow the disease process. If you have been exposed to the HIV virus in any number of ways, you can very easily be tested to determine whether or not you have been infected with the virus.<br>
slide18. Diagnosis of HIV/AIDS
HIV tests are used to detect the presence of the human immunodeficiency virus (HIV), the virus that causes acquired immunodeficiency syndrome (AIDS), in serum, saliva, or urine. Such tests may detect antibodies, antigens, or RNA. Contents<br>
slide19. Diagnosis of HIV infection
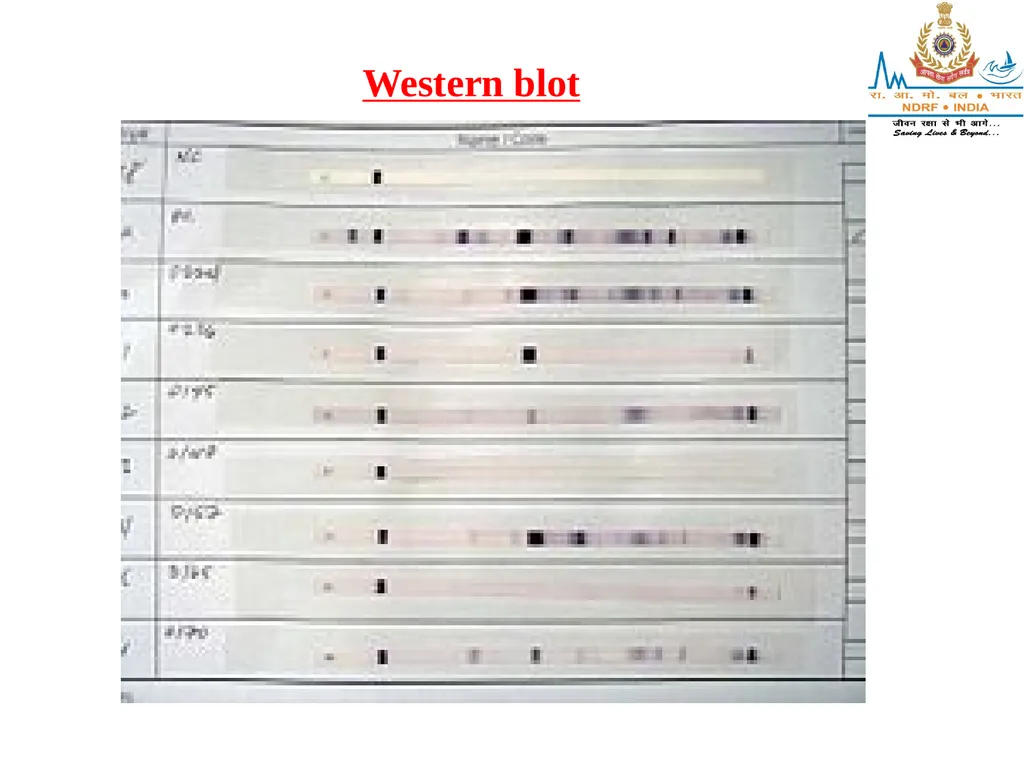
Tests used for the diagnosis of HIV infection in a particular person require a high degree of both sensitivity and specificity. In the United States, this is achieved using an algorithm combining two tests for HIV antibodies. If antibodies are detected by an initial test based on the ELISA method, then a second test using the Western blot procedure determines the size of the antigens in the test kit binding to the antibodies. The combination of these two methods is
Antibody tests
HIV antibody tests are specifically designed for routine diagnostic testing of adults; these tests are inexpensive and extremely accurate.<br>
slide20. ELISA
The enzyme-linked immunosorbent assay (ELISA), or enzyme immunoassay (EIA), was the first screening test commonly employed for HIV. It has a high sensitivity.
In an ELISA test, a person's serum is diluted 400-fold and applied to a plate to which HIV antigens have been attached. If antibodies to HIV are present in the serum, they may bind to these HIV antigens. The plate is then washed to remove all other components of the serum. A specially prepared "secondary antibody" — an antibody that binds to human antibodies — is then applied to the plate, followed by another wash. This secondary antibody is chemically linked in advance to an enzyme. Thus the plate will contain enzyme in proportion to the amount of secondary antibody bound to the plate. A substrate for the enzyme is applied, and catalysis by the enzyme leads to a change in color or fluorescence. ELISA results are reported as a number; the most controversial aspect of this test is determining the "cut-off" point between a positive and negative result.<br>
slide21. Western blot<br>
slide22. Rapid Oral HIV Test Introduction
The Centers for Disease Control and Prevention (CDC) now recommends that all people between the ages of 13 and 64 get tested for HIV regardless of risk. Getting tested for HIV is now easier.
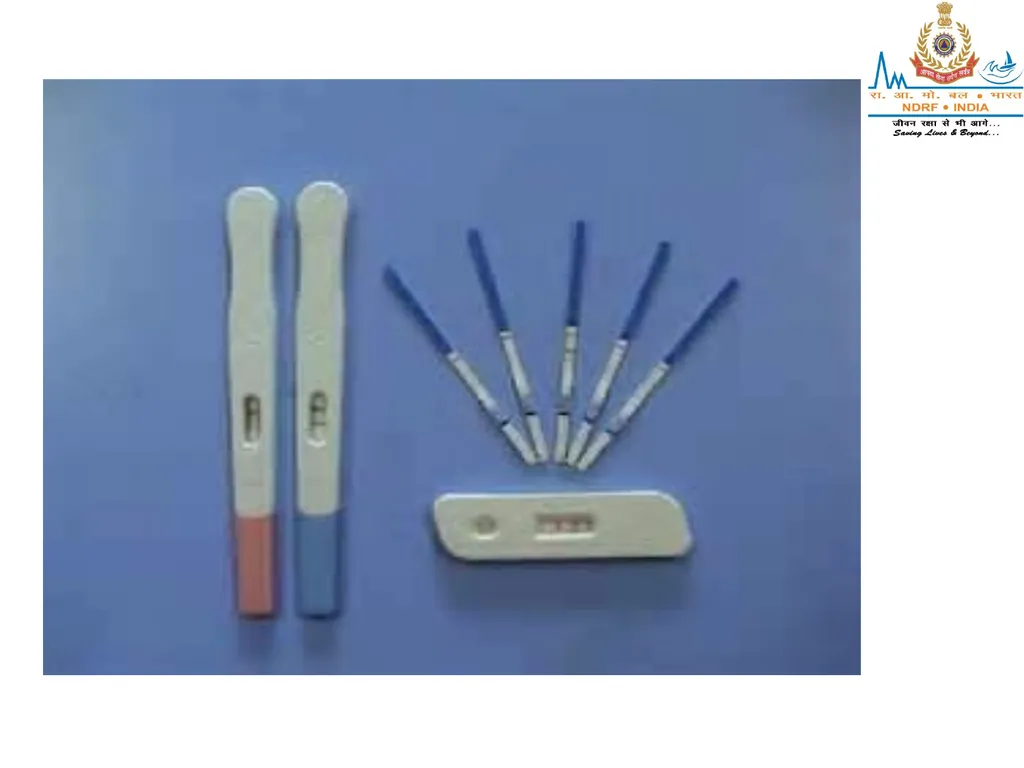
In October 2004, OraSure Technologies, Inc. announced that it had FDA approval for a rapid HIV test that can detect antibodies to both HIV-1 and HIV type 2 (HIV-2). This is called the Ora Quick Advance Rapid HIV-1/2 Antibody Test. It can provide results in 20 minutes using oral fluid, a finger-stick sample of blood, or plasma<br>
slide23. Rapid Oral HIV Test Procedure
To perform an oral test, the tester takes the device that has an absorbent pad at one end, places the pad above a person's teeth along the outer gum, and swabs once around both the upper and lower gums. The tester then inserts the device into a vial containing the developing solution.
In 20 minutes, the device indicates whether HIV-1 or HIV-2 antibodies are present. If one line appears on the strip, it means that the person is not infected with HIV (with 99.8% accuracy). If two lines appear, the person is likely infected (99.3% accuracy). If the result is positive, it has to be confirmed with an additional, more specific test called a western blot. As with all antibody tests for HIV, it could take from two to 12 weeks for a newly infected person to develop antibodies to the HIV virus and thus test positive for HIV. Therefore, if there is a negative result and a possibility of a recent exposure to HIV, the test must be repeated in 12 weeks.<br>
slide24. Traditional HIV tests require an entire vial of blood and take up to two weeks to get results. In addition to the OraQuick ADVANCE Rapid HIV-1/2 Antibody test, which can be done on oral fluid, finger-stick blood or plasma, there are other rapid HIV tests approved by the FDA that can be performed on a finger-stick blood sample with results in 20 minutes. These are the Uni-Gold Recombigen HIV test, Clearview HIV-1/2 Stat Pak, and Clearview Complete HIV-1/2.
These rapid tests have revolutionized HIV screening by making testing available in many clinics, emergency departments, and temporary testing sites such as at health fairs and special HIV testing events.Hospitals use these rapid HIV screening tests to tell if health workers have been exposed to HIV-infected blood and to test women in labor who had not been previously checked. This way, exposed workers and newborns can get anti-HIV drugs immediately to possibly prevent infection. In 2003, the CDC emphasized the use of these rapid HIV screening tests at shelters, drug treatment centers, and other nonmedical facilities.<br>
slide25. PCR (polymerase chain reaction)
Polymerase chain reaction (PCR) is a technique that is used to amplify trace amounts of DNA (and in some instances, RNA) located in or on almost any liquid or surface where DNA strands may be deposited. The key to understanding PCR is to know that every human, animal, plant, parasite, bacterium, or virus contains genetic material such as DNA (or RNA) sequences (nucleotide sequences or pieces of DNA or RNA) that are unique to their species, and to the individual member of that species. Consequently, if a sample contains segments of DNA or RNA, PCR is a method used to amplify (make many more identical copies) of these unique sequences so they can then be used to determine with a very high probability the identity of the source (a specific person, animal, or pathogenic organism) of the trace DNA or RNA found in or on almost any sample of material.<br>
slide26. PCR amplification is only part of the identifying test, however. Once the amplification is done (see below), the amplified segments need to be compared to other nucleotide segments from a known source (for example, a specific person, animal, or pathogenic organism). This comparison of unique segments is often done by placing PCR-generated nucleotide sequences next to known nucleotide sequences from humans, pathogens, or other sources in a separating gel.<br>
slide27. Electrical current is run through the gel and the various nucleotide sequences form bands that resemble a "ladder" according to their electrical charge and molecular size. This is termed gel electrophoresis. Bands or "ladder" like steps that migrate to the same levels in the gel show identity of nucleotide sequences. This method is one of the most popular ways PCR tests are completed (See Fig 1).
Figure 1, Bands or "ladder" like steps of PCR produced DNA of Mycobacterium (courtesy of the CDC<br>
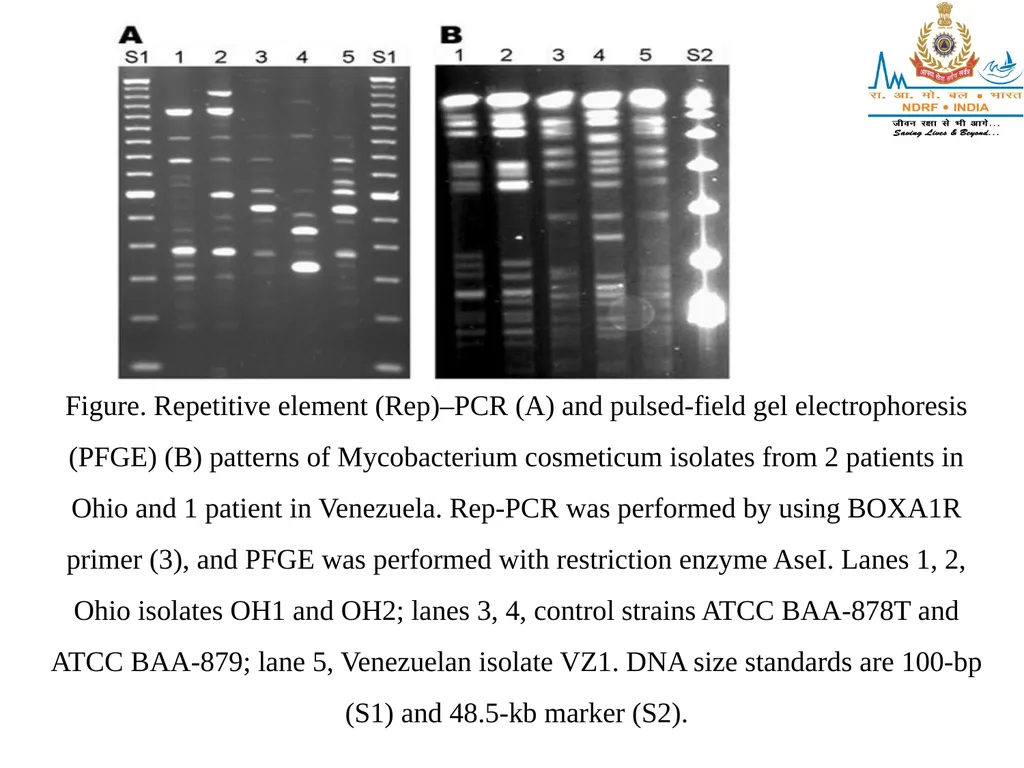
slide28. Figure. Repetitive element (Rep)–PCR (A) and pulsed-field gel electrophoresis (PFGE) (B) patterns of Mycobacterium cosmeticum isolates from 2 patients in Ohio and 1 patient in Venezuela. Rep-PCR was performed by using BOXA1R primer (3), and PFGE was performed with restriction enzyme AseI. Lanes 1, 2, Ohio isolates OH1 and OH2; lanes 3, 4, control strains ATCC BAA-878T and ATCC BAA-879; lane 5, Venezuelan isolate VZ1. DNA size standards are 100-bp (S1) and 48.5-kb marker (S2).<br>
slide29. VDRL
PRINCIPLE / THEORY GOVERNING THE TEST: Flocculation test detects reagin (antibody to non - treponemal antigen).
REAGENTS REQUIRED
A. Antigen:
1.Prepare antigen suspension as described for the VDRL Slide Test.
2.Add one part of 10% saline to one part of VDRL antigen.
3.Mix by gently rotating the bottle or inverting the tube and allow to stand at least 5 minutes but not more than 2 hours before use.<br>
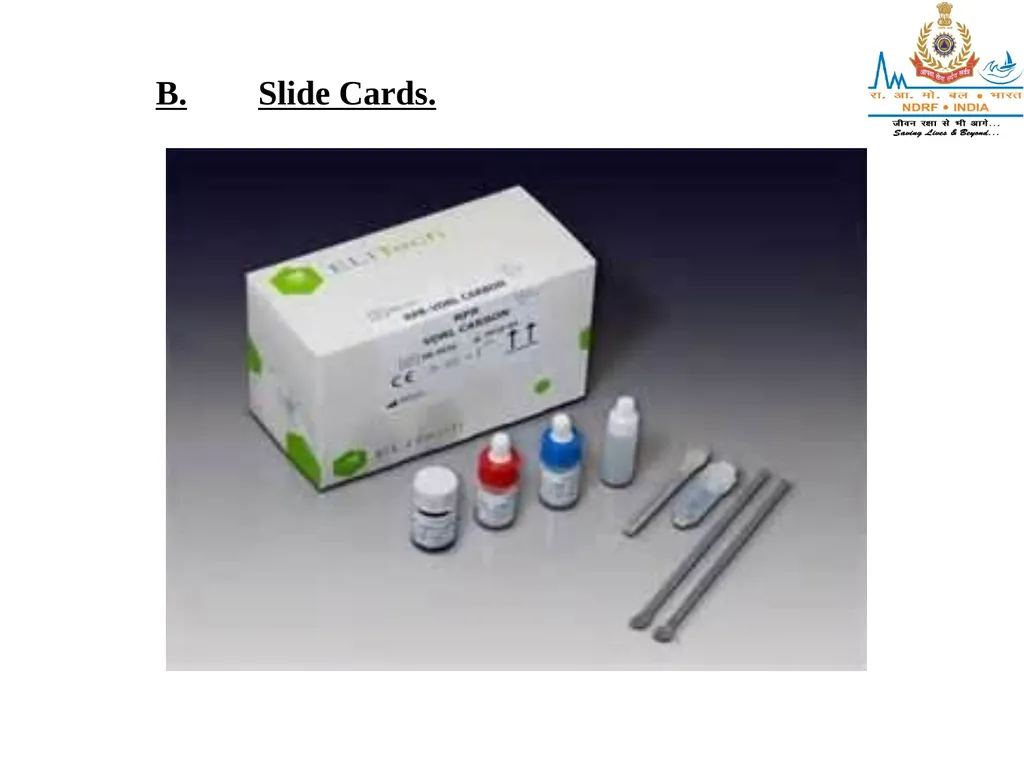
slide30. B. Slide Cards.<br>
slide32. ADDITIONAL MATERIALS NEEDED:
A. Stirrers
B. Rotator
SPECIMEN COLLECTION & HANDLING: (CSF or Serum)
a) CSF: Centrifuge and decant each spinal fluid. The spinal fluid is tested without preliminary heating. Spinal fluids that are visibly contaminated or that contain gross blood are unsatisfactory for testing.
b) Serum: No special preparations needed.<br>
slide33. PROCEDURE:
A. Pipette 0.05 ml of specimen into one concavity of an agglutination slide
B. Add one drop (0.01 ml) of sensitized antigen suspension to each specimen with a 21 or 22 gauge needle.
C. Rotate slides for 8 minutes on a mechanical rotator at 180 rpm.
NOTE: When tests are performed in a dry climate, the slides may be covered with a box lid to prevent evaporation.
D. Read test microscopically, with a 10X objective immediately after rotation.<br>
slide34. NORMAL VALUES: Non-Reactive
INTERPRETATION OF RESULTS:
Definite clumping Reactive (R)
No clumping or slight roughness Non-reactive (NR)<br>
slide35. HEPATITIS
Hepatitis B testing will be offered if there is an overt blood-borne exposure, if there is sexual contact to a known infectious hepatitis B partner, or in the case of acute hepatic illness. Routine determination of immune status is no longer available. Three viral markers are available to determine the status of a patient: HBsAb - Hepatitis B surface antibody; HBsAg - Hepatitis B surface antigen; and HBc-IgM - Hepatitis B core IgM antibody.
HBsAg Hepatitis B surface antigen. This marker should be requested to detect surface antigen and determine whether the patient has an acute or chronic hepatitis B infection and to determine if the blood is potentially infectious. This should be ordered in conjunction with HBc-lgM.<br>
slide36. Hepatitis C is available for testing of high-risk individuals. Antibody tests for Hepatitis C cannot distinguish between a past or present infection.
HCV Antibody to hepatitis C virus. This marker should be requested when screening for hepatitis C antibody. This screening test (EIA) will not differentiate between acute, chronic, or resolved infections. Patient may or may not be infectious if screening test is positive.<br>
slide37. HEPATITIS MARKERS SHOULD BE REQUESTED UNDER FOUR CIRCUMSTANCES
Acute illness - patient is exhibiting signs and symptoms of hepatitis infection.
Test Requests: HBsAb, HBsAg, HBcIgM, HCV, HAV-Total, HAV-IgM
Eligibility: No restrictions if submitted through public health, State Institutions, or correctional facilities.<br>
slide39. Post blood-borne exposure –
patient has recently had a Blood borne exposure. Test Requests: Source HBsAg, HBcIgM, HCV Exposed: HBsAb, HCV Eligibility: State employees, public health discretion
High risk screening - patient meets the Department of Health criteria for high risk individual.
Test Requests: HBsAb, HBsAg, HBcIgM, HCV Eligibility: No restrictions if submitted through publicly funded programs and meet the definition of high risk criteria.
Post Hepatitis B vaccination screening - patient has recently completed their three shot Hepatitis B vaccination series. Post immunization screening should be done 4-8 weeks following the third dose.<br>
slide40. HEPATITIS TESTING INTERPRETATIONS
Hepatitis-B HBsAb (positive) results indicate that the patient has antibody to hepatitis B virus. This is usually a result of a resolved infection with hepatitis B or a result of immunization against hepatitis B.
HBsAb (negative) results indicate that the patient has no antibody to hepatitis B virus and they are considered susceptible to infection with the Hepatitis B virus. If the patient is known to have been vaccinated against hepatitis B, their antibody levels may be present but non-detectable.
HBsAg (positive) results indicate that the patient has an acute or chronic infection with hepatitis B virus and is considered infectious.<br>
slide41. HBsAg (negative) results indicate that no detectable hepatitis B viral antigen can be detected and status of the patient should be made on the result of the HBcIgM.
HBcIgM (positive) results indicate that the patient has IgM antibody to hepatitis B and has recently been infected with the hepatitis B virus. The patient should be considered infectious at this time.
HBcIgM (negative) results indicate that no detectable level of IgM antibody to hepatitis B virus exists and the status of the patient should be made in conjunction with the result of the HBsAg.<br>
slide42. ANY QUESTION
?<br>
slide43. THANKS<br>
OMKAR YADAV
INSP/PH<br>
slide2. Upon completion of this lesson, you will be able to:
List of SEROLOGY TEST:
Determination of Widal
Determination of RA Factor
Determination of CRP
Determination of ASO
Determination of HIV
Determination of VDRL
7.Determination of Hepatitis (Hepatitis B, C, )<br>
slide3. INTRODUCTION:-
Serology is the scientific study of blood serum and other body fluids. In practice, the term usually refers to the diagnostic identification of antibodies in the serum. Such antibodies are typically formed in response to an infection (against a given microorganism), against other foreign proteins (in response, for example, to a mismatched blood transfusion), or to one's own proteins (in instances of autoimmune disease).Serological tests may be performed for diagnostic purposes when an infection is suspected, in rheumatic illnesses, and in many other situations, such as checking an individual's blood type. Serology blood tests help to diagnose patients with certain immune deficiencies associated with the lack of antibodies, such as X-linked a gammaglobulinemia. In such cases, tests for antibodies will be consistently negative.
There are several serology techniques that can be used depending on the antibodies being studied. These include: ELISA, agglutination, precipitation, complement-fixation, and fluorescent antibodies<br>
slide4. WIDAL TEST
(QUALITATIVE SLIDE AGGLUTINATION METHOD)
To diagnose enteric fever caused by Salmonella species using qualitative slide agglutination test. Materials required: -
1. Widal test kit
2. Widal test slide
3. Suspected serum sample
4. Pipette
5. Applicator stick<br>
slide5. Procedure: - 1. A clean glass marked with six circles was taken.
2. The circles were labeled as “H”, “O”, “A”, “B”, positive control and negative control from the first circle to the last.
3. One drop of undiluted serum was placed in the first four circles with the help of a sterile pasture pipette.
4. One drop of positive control serum and one drop of negative control serum was placed in the fifth and the last circle respectively.
5. One drop of H antigen was added to the first circle and one drop of Salmonella typhi O antigen was added in the second circle. Salmonella paratyphi A antigen and Salmonella paratyphi B antigen were added in the third and fourth circles respectively.<br>
slide6. 6. One drop of ‘H’ antigen was placed at the fifth circle and sixth circle.
7. With separate applicator sticks serum and the antigen was mixed together and was spread well to fill the whole of the individual circle. Then slide was observed for agglutination.
Result: -
The given test patient’s serum is positive for typhoid.
The given test patient’s serum is positive for paratyphoid A or B
The given test patient’s serum is negative for typhoid and paratyphoid<br>
slide7. SPECIMEN COLLECTION AND PREPARATION:
No special preparation of the patient is required prior to specimen collection by approved techniques. Only serum must be used for testing. Should a delay in testing occur, store the sample at 2-80C. Samples can be stored for upto a week. Do not use hemolysed serum.
ADDITIONAL MATERIAL REQUIRED
Stop watch, Test tubes, a high intensity direct light source, Isotonic saline.<br>
slide9. TEST PROCEDURE
Bring reagent and samples to room temperature before use.
Qualitative Method:
1. Pipette one drop (40 μl) of serum onto the glass slide using the disposable pipette provided with kit.
2. Add one drop of RHELAX-RF™ latex reagent to the drop of serum on the slide. Do not let the dropper tip touch the liquid on the slide.
3. Using a mixing stick, mix the serum and RHELAX-RF™ latex reagent uniformly over the entire circle.
4. Immediately start a stopwatch. Rock the slide gently, back and forth, observing for agglutination macroscopically at two minutes.<br>
slide10. CRP (C - reactive protein)
SUMMARY
CRP usually appears in the sera of patients in the acute stages of a number of inflammatory conditions such as most bacterial and some viral infections; acute rheumatoid fever with or without carditis; rheumatoid arthritis and most other collagen diseases; and in a number of other conditions characterized by inflammation. CRP is considered to be a sensitive indicator of inflammation. Changes in the serum level of CRP with time from the same patient can be used as an index of recovery. The use of the CRP test to measure the effectiveness of therapy is of great clinical significance in cases such as acute rheumatoid fever.<br>
slide11. MATERIALS REQUIRED
1. Serological pipettes.
2. Test tubes 12x75 mm.
3. Timing device.
4. Distilled water<br>
slide12. STORAGE & STABILITY
When not in use, store reagents and controls at 2º to 8º C. DO NOT FREEZE. Prior to use, allow reagents and controls to warm up to room temperature. Biological indication of product instability is evidenced by inappropriate reaction of the latex reagent with the corresponding positive and negative control sera.
PRECAUTIONS
1. The preservative sodium azide may react with metal plumbing to from explosive metal oxides. In disposal, flush with a large a volume of water to prevent metal azide build up.
2. Human control sera were tested for the presence of Hepatitis B Surface Antigen (HBsAg) and anti-HIV antibody and found to be negative. However, all materials should still be handled as infectious agents.<br>
slide13. TEST PROCEDURE
Method I (Qualitative)
1. Bring all reagents, controls and serum samples to room temperature.
2. Shake the CRP latex reagent gently before use. Deliver one drop of reagent to the test circle. Using the disposable pipettes, add one drop of the undiluted patient serum onto the same circle and mix both together with the paddle end of the pipette.
3. Positive and negative controls should be run with each series of test serums in the same way as in Step 2.
4. Rotate slide back and forth for 2 minutes and read result under an indirect oblique light source<br>
slide14. Method II (Semi-Quantitative method):
1. Set up at least 5 test tubes and label 1:2, 1:4, 1:8, 1:16, 1:32, and etc.
2. Use diluted Glycine-Saline Buffer to serially dilute sample to be tittered according to standard laboratory practice.
3. Repeat all steps as in Qualitative Method using these new samples.<br>
slide15. RESULTS:
Positive reaction is indicated by agglutination. Since negative results may be caused by antigen excess, the test should be repeated using a diluted serum sample in case prozone effect is suspected. For the Semi-Quantitative Method, multiplication of the dilution factor with 6 mg/L will yield the approximate level of CRP in the serum sample.
DILUTION CONCENTRATION (mg/L)
1:1 6
1:2 12
1:4 24
1:8 48<br>
slide16. LIMITATIONS OF THE PROCEDURE
1. The strength of the agglutination reaction is not indicative of the CRP concentration. Weak reactions may occur with slightly elevated or markedly elevated concentrations.
2. A prozone phenomena (antigen excess) may cause false negatives. It is advisable, therefore, to check all negative sera by retesting at a 1:10 dilution.
3. Reaction times longer than specified may produce apparent false reactions due to a drying effect.
4. Strongly lipemic or contaminated sera can cause false positive reactions.
5. Only serum should be used in this test.
EXPECTED VALUES
Normal adult levels of CRP are reported to be less than 12 mg/L. Trace levels of CRP had been reported in the sera of apparently healthy adults3 and normal children4. The CRP level can increase significantly (>10 fold) above the normal values with the onset of a substantial inflammatory stimulus.<br>
slide17. HIV
HIV Testing Introduction
Human immunodeficiency virus (HIV) is the virus that causes acquired immune deficiency syndrome (AIDS). HIV destroys the body's immune system and eventually leads to AIDS. People with AIDS develop many diseases and "opportunistic" infections (such as pneumonia, tuberculosis, cancer, and skin infections) that may ultimately lead to death. Prevention is critical. There is no cure for HIV/AIDS, but currently, there are effective treatments that can drastically slow the disease process. If you have been exposed to the HIV virus in any number of ways, you can very easily be tested to determine whether or not you have been infected with the virus.<br>
slide18. Diagnosis of HIV/AIDS
HIV tests are used to detect the presence of the human immunodeficiency virus (HIV), the virus that causes acquired immunodeficiency syndrome (AIDS), in serum, saliva, or urine. Such tests may detect antibodies, antigens, or RNA. Contents<br>
slide19. Diagnosis of HIV infection
Tests used for the diagnosis of HIV infection in a particular person require a high degree of both sensitivity and specificity. In the United States, this is achieved using an algorithm combining two tests for HIV antibodies. If antibodies are detected by an initial test based on the ELISA method, then a second test using the Western blot procedure determines the size of the antigens in the test kit binding to the antibodies. The combination of these two methods is
Antibody tests
HIV antibody tests are specifically designed for routine diagnostic testing of adults; these tests are inexpensive and extremely accurate.<br>
slide20. ELISA
The enzyme-linked immunosorbent assay (ELISA), or enzyme immunoassay (EIA), was the first screening test commonly employed for HIV. It has a high sensitivity.
In an ELISA test, a person's serum is diluted 400-fold and applied to a plate to which HIV antigens have been attached. If antibodies to HIV are present in the serum, they may bind to these HIV antigens. The plate is then washed to remove all other components of the serum. A specially prepared "secondary antibody" — an antibody that binds to human antibodies — is then applied to the plate, followed by another wash. This secondary antibody is chemically linked in advance to an enzyme. Thus the plate will contain enzyme in proportion to the amount of secondary antibody bound to the plate. A substrate for the enzyme is applied, and catalysis by the enzyme leads to a change in color or fluorescence. ELISA results are reported as a number; the most controversial aspect of this test is determining the "cut-off" point between a positive and negative result.<br>
slide21. Western blot<br>
slide22. Rapid Oral HIV Test Introduction
The Centers for Disease Control and Prevention (CDC) now recommends that all people between the ages of 13 and 64 get tested for HIV regardless of risk. Getting tested for HIV is now easier.
In October 2004, OraSure Technologies, Inc. announced that it had FDA approval for a rapid HIV test that can detect antibodies to both HIV-1 and HIV type 2 (HIV-2). This is called the Ora Quick Advance Rapid HIV-1/2 Antibody Test. It can provide results in 20 minutes using oral fluid, a finger-stick sample of blood, or plasma<br>
slide23. Rapid Oral HIV Test Procedure
To perform an oral test, the tester takes the device that has an absorbent pad at one end, places the pad above a person's teeth along the outer gum, and swabs once around both the upper and lower gums. The tester then inserts the device into a vial containing the developing solution.
In 20 minutes, the device indicates whether HIV-1 or HIV-2 antibodies are present. If one line appears on the strip, it means that the person is not infected with HIV (with 99.8% accuracy). If two lines appear, the person is likely infected (99.3% accuracy). If the result is positive, it has to be confirmed with an additional, more specific test called a western blot. As with all antibody tests for HIV, it could take from two to 12 weeks for a newly infected person to develop antibodies to the HIV virus and thus test positive for HIV. Therefore, if there is a negative result and a possibility of a recent exposure to HIV, the test must be repeated in 12 weeks.<br>
slide24. Traditional HIV tests require an entire vial of blood and take up to two weeks to get results. In addition to the OraQuick ADVANCE Rapid HIV-1/2 Antibody test, which can be done on oral fluid, finger-stick blood or plasma, there are other rapid HIV tests approved by the FDA that can be performed on a finger-stick blood sample with results in 20 minutes. These are the Uni-Gold Recombigen HIV test, Clearview HIV-1/2 Stat Pak, and Clearview Complete HIV-1/2.
These rapid tests have revolutionized HIV screening by making testing available in many clinics, emergency departments, and temporary testing sites such as at health fairs and special HIV testing events.Hospitals use these rapid HIV screening tests to tell if health workers have been exposed to HIV-infected blood and to test women in labor who had not been previously checked. This way, exposed workers and newborns can get anti-HIV drugs immediately to possibly prevent infection. In 2003, the CDC emphasized the use of these rapid HIV screening tests at shelters, drug treatment centers, and other nonmedical facilities.<br>
slide25. PCR (polymerase chain reaction)
Polymerase chain reaction (PCR) is a technique that is used to amplify trace amounts of DNA (and in some instances, RNA) located in or on almost any liquid or surface where DNA strands may be deposited. The key to understanding PCR is to know that every human, animal, plant, parasite, bacterium, or virus contains genetic material such as DNA (or RNA) sequences (nucleotide sequences or pieces of DNA or RNA) that are unique to their species, and to the individual member of that species. Consequently, if a sample contains segments of DNA or RNA, PCR is a method used to amplify (make many more identical copies) of these unique sequences so they can then be used to determine with a very high probability the identity of the source (a specific person, animal, or pathogenic organism) of the trace DNA or RNA found in or on almost any sample of material.<br>
slide26. PCR amplification is only part of the identifying test, however. Once the amplification is done (see below), the amplified segments need to be compared to other nucleotide segments from a known source (for example, a specific person, animal, or pathogenic organism). This comparison of unique segments is often done by placing PCR-generated nucleotide sequences next to known nucleotide sequences from humans, pathogens, or other sources in a separating gel.<br>
slide27. Electrical current is run through the gel and the various nucleotide sequences form bands that resemble a "ladder" according to their electrical charge and molecular size. This is termed gel electrophoresis. Bands or "ladder" like steps that migrate to the same levels in the gel show identity of nucleotide sequences. This method is one of the most popular ways PCR tests are completed (See Fig 1).
Figure 1, Bands or "ladder" like steps of PCR produced DNA of Mycobacterium (courtesy of the CDC<br>
slide28. Figure. Repetitive element (Rep)–PCR (A) and pulsed-field gel electrophoresis (PFGE) (B) patterns of Mycobacterium cosmeticum isolates from 2 patients in Ohio and 1 patient in Venezuela. Rep-PCR was performed by using BOXA1R primer (3), and PFGE was performed with restriction enzyme AseI. Lanes 1, 2, Ohio isolates OH1 and OH2; lanes 3, 4, control strains ATCC BAA-878T and ATCC BAA-879; lane 5, Venezuelan isolate VZ1. DNA size standards are 100-bp (S1) and 48.5-kb marker (S2).<br>
slide29. VDRL
PRINCIPLE / THEORY GOVERNING THE TEST: Flocculation test detects reagin (antibody to non - treponemal antigen).
REAGENTS REQUIRED
A. Antigen:
1.Prepare antigen suspension as described for the VDRL Slide Test.
2.Add one part of 10% saline to one part of VDRL antigen.
3.Mix by gently rotating the bottle or inverting the tube and allow to stand at least 5 minutes but not more than 2 hours before use.<br>
slide30. B. Slide Cards.<br>
slide32. ADDITIONAL MATERIALS NEEDED:
A. Stirrers
B. Rotator
SPECIMEN COLLECTION & HANDLING: (CSF or Serum)
a) CSF: Centrifuge and decant each spinal fluid. The spinal fluid is tested without preliminary heating. Spinal fluids that are visibly contaminated or that contain gross blood are unsatisfactory for testing.
b) Serum: No special preparations needed.<br>
slide33. PROCEDURE:
A. Pipette 0.05 ml of specimen into one concavity of an agglutination slide
B. Add one drop (0.01 ml) of sensitized antigen suspension to each specimen with a 21 or 22 gauge needle.
C. Rotate slides for 8 minutes on a mechanical rotator at 180 rpm.
NOTE: When tests are performed in a dry climate, the slides may be covered with a box lid to prevent evaporation.
D. Read test microscopically, with a 10X objective immediately after rotation.<br>
slide34. NORMAL VALUES: Non-Reactive
INTERPRETATION OF RESULTS:
Definite clumping Reactive (R)
No clumping or slight roughness Non-reactive (NR)<br>
slide35. HEPATITIS
Hepatitis B testing will be offered if there is an overt blood-borne exposure, if there is sexual contact to a known infectious hepatitis B partner, or in the case of acute hepatic illness. Routine determination of immune status is no longer available. Three viral markers are available to determine the status of a patient: HBsAb - Hepatitis B surface antibody; HBsAg - Hepatitis B surface antigen; and HBc-IgM - Hepatitis B core IgM antibody.
HBsAg Hepatitis B surface antigen. This marker should be requested to detect surface antigen and determine whether the patient has an acute or chronic hepatitis B infection and to determine if the blood is potentially infectious. This should be ordered in conjunction with HBc-lgM.<br>
slide36. Hepatitis C is available for testing of high-risk individuals. Antibody tests for Hepatitis C cannot distinguish between a past or present infection.
HCV Antibody to hepatitis C virus. This marker should be requested when screening for hepatitis C antibody. This screening test (EIA) will not differentiate between acute, chronic, or resolved infections. Patient may or may not be infectious if screening test is positive.<br>
slide37. HEPATITIS MARKERS SHOULD BE REQUESTED UNDER FOUR CIRCUMSTANCES
Acute illness - patient is exhibiting signs and symptoms of hepatitis infection.
Test Requests: HBsAb, HBsAg, HBcIgM, HCV, HAV-Total, HAV-IgM
Eligibility: No restrictions if submitted through public health, State Institutions, or correctional facilities.<br>
slide39. Post blood-borne exposure –
patient has recently had a Blood borne exposure. Test Requests: Source HBsAg, HBcIgM, HCV Exposed: HBsAb, HCV Eligibility: State employees, public health discretion
High risk screening - patient meets the Department of Health criteria for high risk individual.
Test Requests: HBsAb, HBsAg, HBcIgM, HCV Eligibility: No restrictions if submitted through publicly funded programs and meet the definition of high risk criteria.
Post Hepatitis B vaccination screening - patient has recently completed their three shot Hepatitis B vaccination series. Post immunization screening should be done 4-8 weeks following the third dose.<br>
slide40. HEPATITIS TESTING INTERPRETATIONS
Hepatitis-B HBsAb (positive) results indicate that the patient has antibody to hepatitis B virus. This is usually a result of a resolved infection with hepatitis B or a result of immunization against hepatitis B.
HBsAb (negative) results indicate that the patient has no antibody to hepatitis B virus and they are considered susceptible to infection with the Hepatitis B virus. If the patient is known to have been vaccinated against hepatitis B, their antibody levels may be present but non-detectable.
HBsAg (positive) results indicate that the patient has an acute or chronic infection with hepatitis B virus and is considered infectious.<br>
slide41. HBsAg (negative) results indicate that no detectable hepatitis B viral antigen can be detected and status of the patient should be made on the result of the HBcIgM.
HBcIgM (positive) results indicate that the patient has IgM antibody to hepatitis B and has recently been infected with the hepatitis B virus. The patient should be considered infectious at this time.
HBcIgM (negative) results indicate that no detectable level of IgM antibody to hepatitis B virus exists and the status of the patient should be made in conjunction with the result of the HBsAg.<br>
slide42. ANY QUESTION
?<br>
slide43. THANKS<br>