
SpR 2; Intensive Care in the SCE Annette Fisher









Description: SpR 2; Intensive Care in the SCE Annette Fisher ST3 Respiratory Medicine Sunderland Royal Hospital Question 1. A 54 year old woman is referred to critical care 48 hrs post laparotomy for a perforated duodenal ulcer with four-quadrant
Related Topics
Download Presentation
"SpR 2; Intensive Care in the SCE Annette Fisher" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. SpR 2; Intensive Care in the SCE Annette Fisher
ST3 Respiratory Medicine
Sunderland Royal Hospital<br>
slide2. Question 1. A 54 year old woman is referred to critical care 48 hrs post laparotomy for a perforated duodenal ulcer with four-quadrant peritonitis. She has deteriorated over the past 12 hrs with respiratory distress.
On examination she appears confused and is speaking in broken sentences. RR is 30 and SpO2 on 92 % via 15 L/min non-rebreathe mask. Auscultation reveals fine crackles bilaterally. HR is 110 bpm and BP is 100/60. Her JVP is not elevated and she has normal heart sounds. There is no peripheral oedema and her calves are soft and non-tender. Fluid balance is 800 ml positive.
A portable CXR demonstrates extensive bilateral infiltrates. A blood gas is performed with the following result;
pH 7.32
pCO2 3.8 kPa
pO2 8.1 kPa
HCO3 18.7 mmol/L
What would be the most useful next investigation in assessing the suspected cause for her deterioration?
CT pulmonary angiogram
Thoracic USS
Echocardiogram
Bronchoscopy with bronchoalveolar lavage
ECG<br>
slide3. Acute Respiratory Distress Syndrome1, 2 Severe end of spectrum of acute lung injury due to many different insults;
Sepsis/pneumonia
Gastric aspiration
Trauma/burns
Panceatitis
TRALI
Post stem cell transplant
Overdose
Near drowning<br>
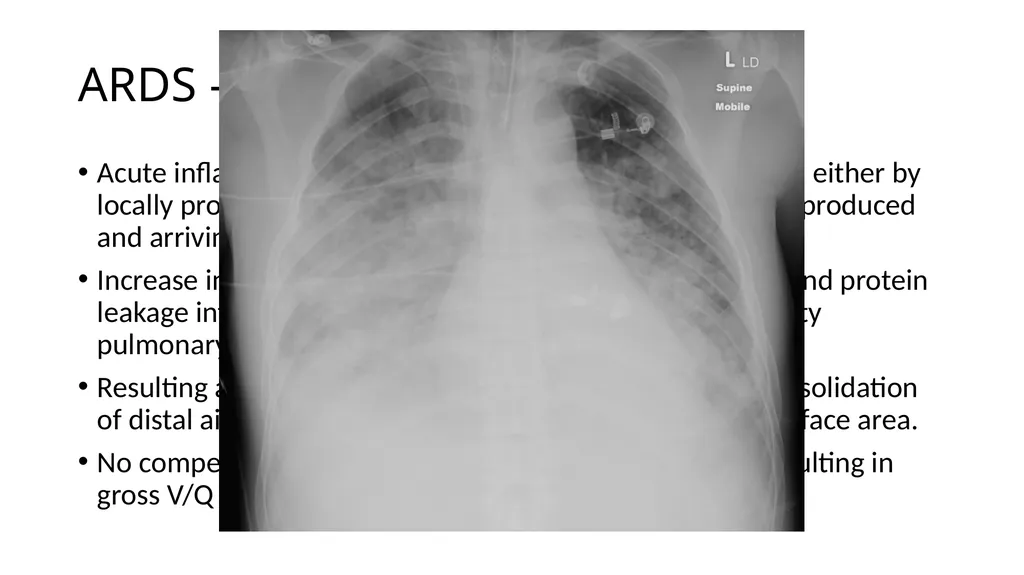
slide4. ARDS - Pathophysiology Acute inflammation affecting alveolar-capillary membrane, either by locally produced pro-inflammatory mediators or remotely produced and arriving via pulmonary artery.
Increase in permeability of the membrane allowing fluid and protein leakage into alveolar space manifesting as high permeability pulmonary oedema.
Resulting acute inflammatory exudate collapse and consolidation of distal airpaces with progressive loss of gas exchange surface area.
No compensatory hypoxic pulmonary vasoconstriction resulting in gross V/Q mismatch.<br>
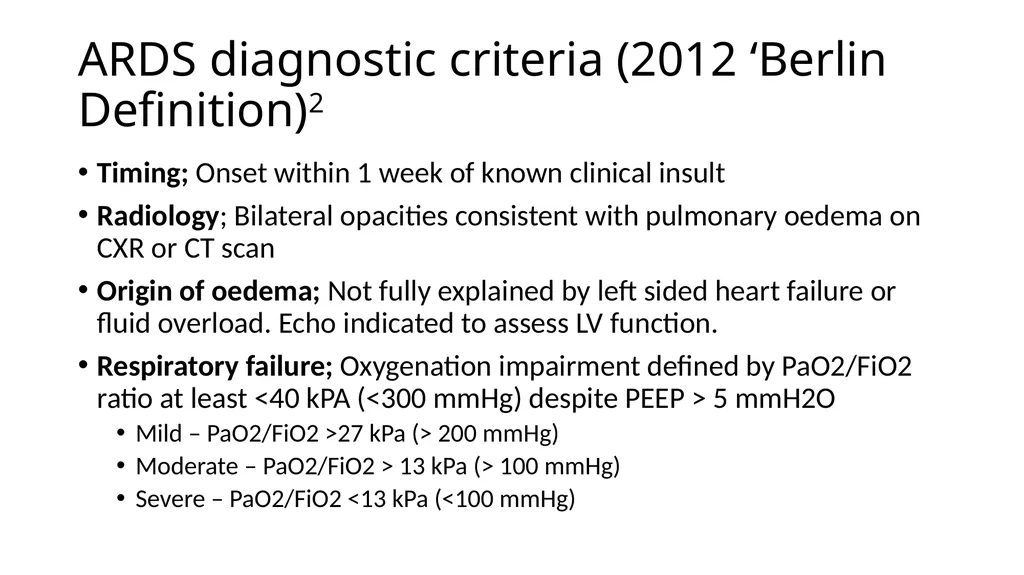
slide5. ARDS diagnostic criteria (2012 ‘Berlin Definition)2 Timing; Onset within 1 week of known clinical insult
Radiology; Bilateral opacities consistent with pulmonary oedema on CXR or CT scan
Origin of oedema; Not fully explained by left sided heart failure or fluid overload. Echo indicated to assess LV function.
Respiratory failure; Oxygenation impairment defined by PaO2/FiO2 ratio at least <40 kPA (<300 mmHg) despite PEEP > 5 mmH2O
Mild – PaO2/FiO2 >27 kPa (> 200 mmHg)
Moderate – PaO2/FiO2 > 13 kPa (> 100 mmHg)
Severe – PaO2/FiO2 <13 kPa (<100 mmHg)<br>
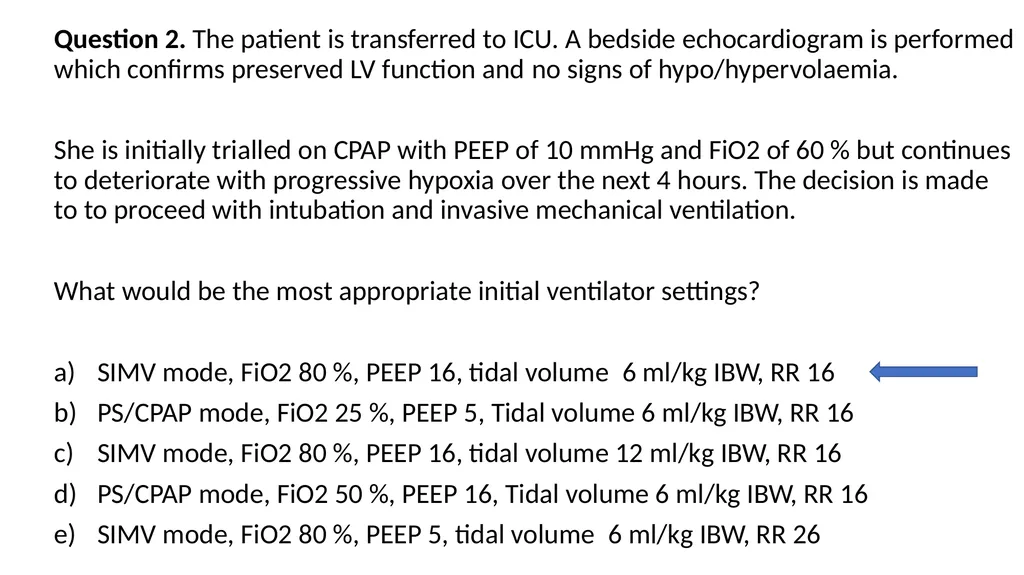
slide6. Question 2. The patient is transferred to ICU. A bedside echocardiogram is performed which confirms preserved LV function and no signs of hypo/hypervolaemia.
She is initially trialled on CPAP with PEEP of 10 mmHg and FiO2 of 60 % but continues to deteriorate with progressive hypoxia over the next 4 hours. The decision is made to to proceed with intubation and invasive mechanical ventilation.
What would be the most appropriate initial ventilator settings?
SIMV mode, FiO2 80 %, PEEP 16, tidal volume 6 ml/kg IBW, RR 16
PS/CPAP mode, FiO2 25 %, PEEP 5, Tidal volume 6 ml/kg IBW, RR 16
SIMV mode, FiO2 80 %, PEEP 16, tidal volume 12 ml/kg IBW, RR 16
PS/CPAP mode, FiO2 50 %, PEEP 16, Tidal volume 6 ml/kg IBW, RR 16
SIMV mode, FiO2 80 %, PEEP 5, tidal volume 6 ml/kg IBW, RR 26<br>
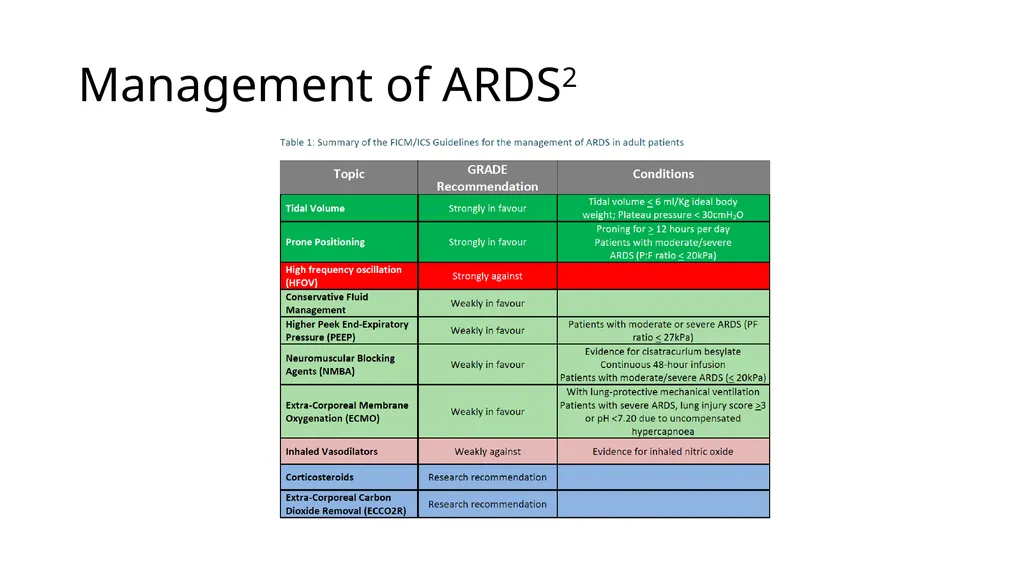
slide7. Management of ARDS2<br>
slide8. Question 3. Over the next 6 days, the patient is managed with lung protective ventilation, high PEEP, prone positioning and a 48 hr infusion of neuromuscular blocking agent. In spite of this she fails to improve, as evidenced by worsening hypoxia. She has also developed an acute kidney injury necessitating renal replacement therapy, and her vasopressor requirements are increasing.
The ICU team decide to refer her for consideration of Extra-Corporeal Membrane Oxygenation.
What is most likely to lead to a decline in the referral?
Age >50 years
Recent extensive intra-abdominal surgery
Refractory multi-organ failure
Invasive ventilation for >5 days
CPAP treatment preceding invasive ventilation<br>
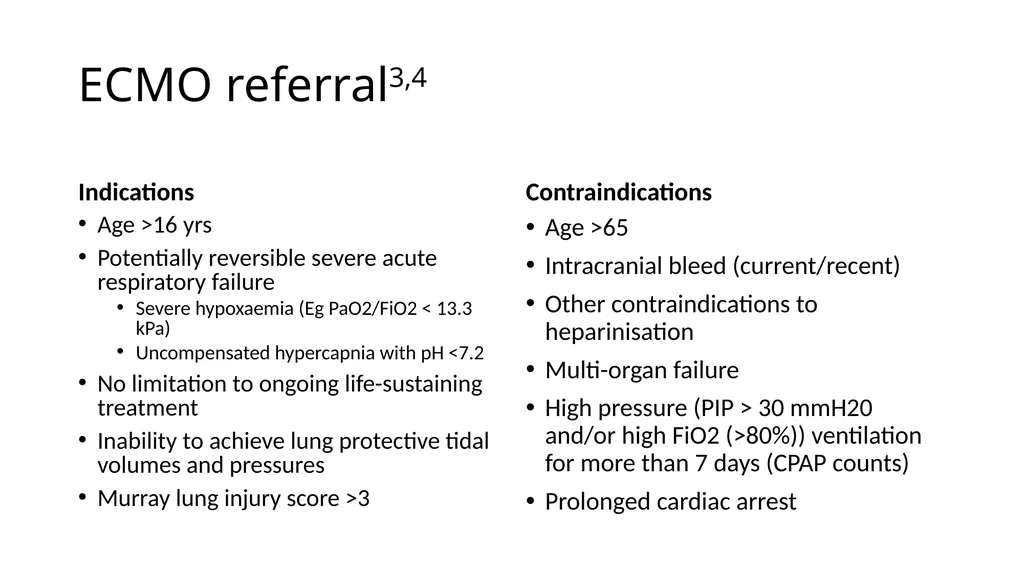
slide9. ECMO referral3,4 Indications Age >16 yrs
Potentially reversible severe acute respiratory failure
Severe hypoxaemia (Eg PaO2/FiO2 < 13.3 kPa)
Uncompensated hypercapnia with pH <7.2
No limitation to ongoing life-sustaining treatment
Inability to achieve lung protective tidal volumes and pressures
Murray lung injury score >3 Contraindications Age >65
Intracranial bleed (current/recent)
Other contraindications to heparinisation
Multi-organ failure
High pressure (PIP > 30 mmH20 and/or high FiO2 (>80%)) ventilation for more than 7 days (CPAP counts)
Prolonged cardiac arrest<br>
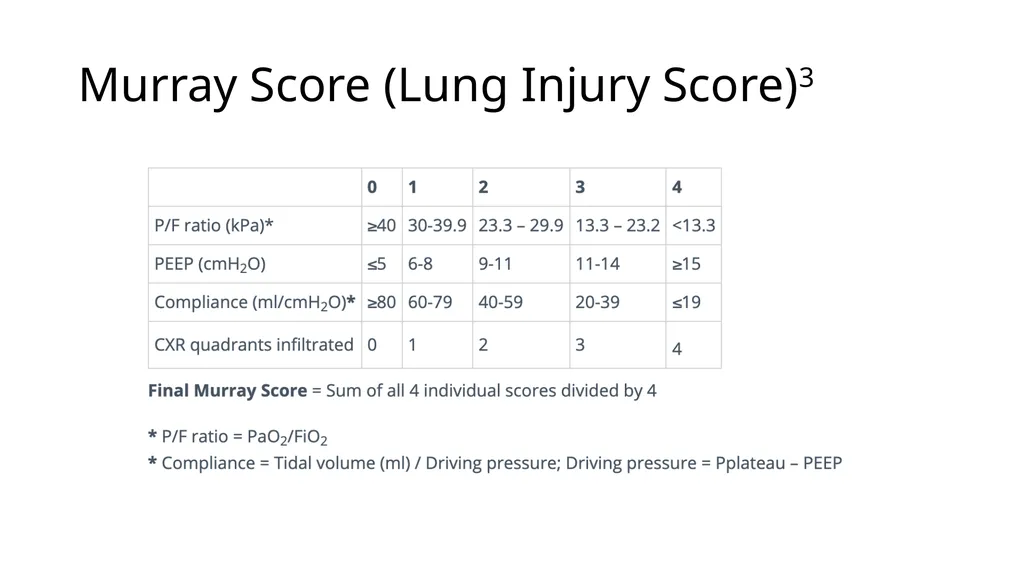
slide10. Murray Score (Lung Injury Score)3<br>
slide11. Question 4. The patient is declined for ECMO on the basis of established multi-organ failure. Her condition does, however, stabilise over the next few days, with reducing ventilatory support and the recovery of some renal function. The ICU team decide to proceed with full active management.
During a night shift as the ICU resident you are called by nursing staff to review her urgently. Her oxygen saturations have dropped rapidly – they are currently 85 % on 100 % FiO2 with PEEP of 16. HR is 130 bpm, sinus tachycardia, BP is 90/50. On examination there is decreased right sided chest expansion with minimal breath sounds. The oral ETT is 24 cm at the lips, which is unchanged from previously. Peak inspiratory pressures have risen to >40 mmH20.
What is the most appropriate treatment to improve the patient’s condition?
a) Therapeutic bronchoscopy
b) Needle decompression followed by chest drain insertion
c) Broad spectrum antibiotics
d) Thrombolysis
c) Pull back ETT 2 cm<br>
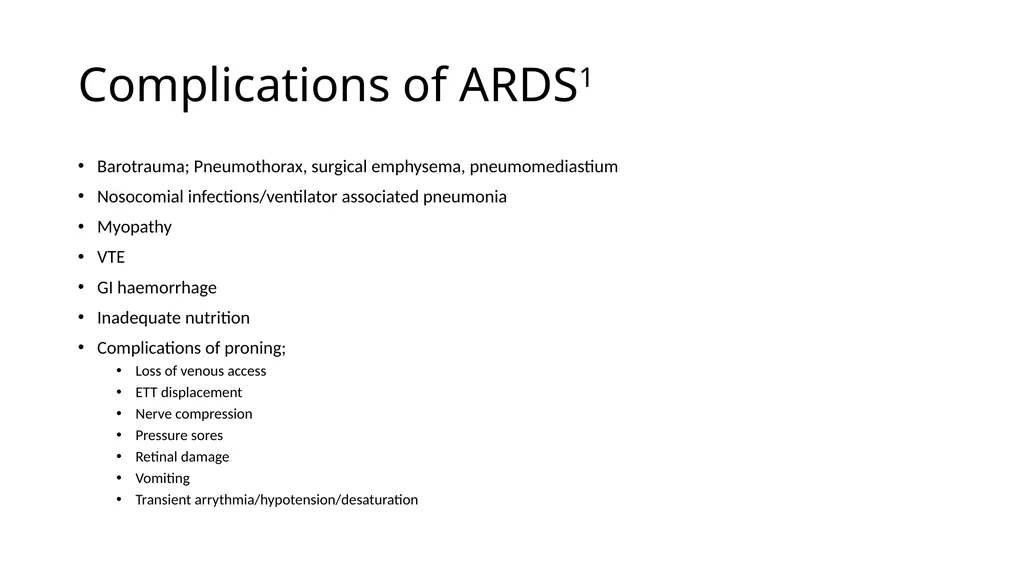
slide12. Complications of ARDS1 Barotrauma; Pneumothorax, surgical emphysema, pneumomediastium
Nosocomial infections/ventilator associated pneumonia
Myopathy
VTE
GI haemorrhage
Inadequate nutrition
Complications of proning;
Loss of venous access
ETT displacement
Nerve compression
Pressure sores
Retinal damage
Vomiting
Transient arrythmia/hypotension/desaturation<br>
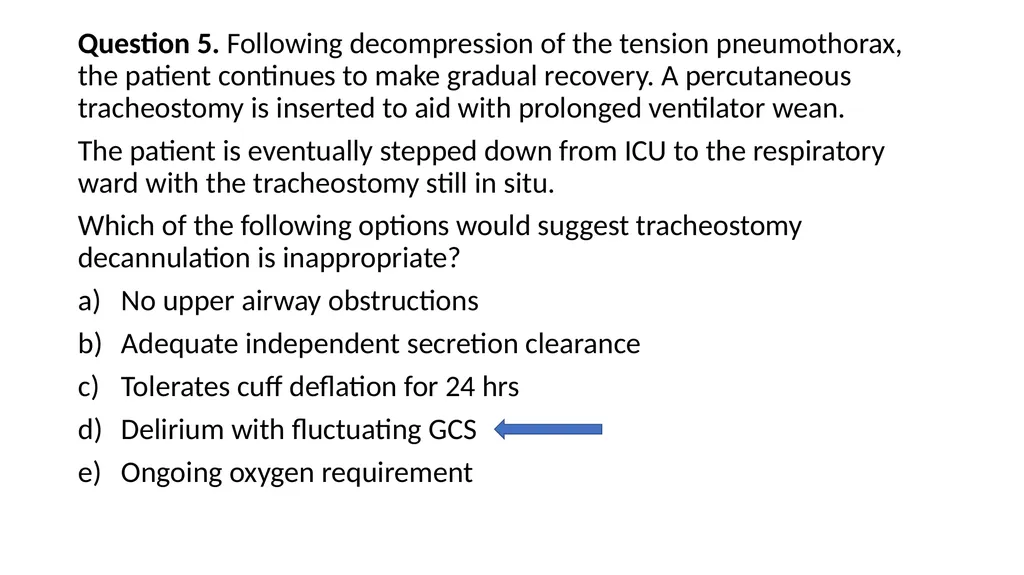
slide13. Question 5. Following decompression of the tension pneumothorax, the patient continues to make gradual recovery. A percutaneous tracheostomy is inserted to aid with prolonged ventilator wean.
The patient is eventually stepped down from ICU to the respiratory ward with the tracheostomy still in situ.
Which of the following options would suggest tracheostomy decannulation is inappropriate?
No upper airway obstructions
Adequate independent secretion clearance
Tolerates cuff deflation for 24 hrs
Delirium with fluctuating GCS
Ongoing oxygen requirement<br>
slide14. Tracheostomy1, 5 Indications
Airway protection following major head and neck surgery
Prolonged ventilator wean
Neurospinal indications; cervical cord pathology, reduced GCS following neurological injury
Advantages
Improved patient communication
Improved tube tolerance
Reduced sedation requirement
Disadvantages
Increased tendency to aspirate
Reduced ability to talk
Increased infection risk
Tracheal stenosis<br>
slide15. Tracheostomy decannulation Should be carried out as soon as;
Adequate secretion clearance
Low probability of thick mucous plugs blocking large airways
No upper airway obstruction
No significant aspiration
No need to continue ventilation or reduce dead space for gas exchange
Patient tolerates cuff deflation for 24 hrs/speaking valve for 12 hrs
Haemodynamic stability
No new lung infiltrates on CXR
MDT agreement for decannulation<br>
slide16. References 1. Oxford Handbook of Respiratory Medicine 4th Edition
2. Faculty of Intensive Care Medicine/Intensive Care Society (2018) ”Guidelines on the Management of Acute Respiratory Distress Syndrome” Version 1
3. Royal Bromptom and Harefield Hospitals “ECMO Referrals and Transfer Pathways” https://www.rbht.nhs.uk/our-services/clinical_support/critical-care-and-anaesthesia/ecmo-and-severe-respiratory-failure/ecmo-referrals-and-transfer-pathway
4.NHS England ECMO National Referral Pathway https://www.signpost.healthcare/ecmo-referral-pathway
5. Stelfox HT, Crimi C, Berra L, Noto A, Schmidt U, Bigatello LM, Hess D (2008) “Determinants of tracheostomy decannulation: an international survey” Critical care 12:R26.<br>
slide17. Thank you for listening, any questions?<br>
ST3 Respiratory Medicine
Sunderland Royal Hospital<br>
slide2. Question 1. A 54 year old woman is referred to critical care 48 hrs post laparotomy for a perforated duodenal ulcer with four-quadrant peritonitis. She has deteriorated over the past 12 hrs with respiratory distress.
On examination she appears confused and is speaking in broken sentences. RR is 30 and SpO2 on 92 % via 15 L/min non-rebreathe mask. Auscultation reveals fine crackles bilaterally. HR is 110 bpm and BP is 100/60. Her JVP is not elevated and she has normal heart sounds. There is no peripheral oedema and her calves are soft and non-tender. Fluid balance is 800 ml positive.
A portable CXR demonstrates extensive bilateral infiltrates. A blood gas is performed with the following result;
pH 7.32
pCO2 3.8 kPa
pO2 8.1 kPa
HCO3 18.7 mmol/L
What would be the most useful next investigation in assessing the suspected cause for her deterioration?
CT pulmonary angiogram
Thoracic USS
Echocardiogram
Bronchoscopy with bronchoalveolar lavage
ECG<br>
slide3. Acute Respiratory Distress Syndrome1, 2 Severe end of spectrum of acute lung injury due to many different insults;
Sepsis/pneumonia
Gastric aspiration
Trauma/burns
Panceatitis
TRALI
Post stem cell transplant
Overdose
Near drowning<br>
slide4. ARDS - Pathophysiology Acute inflammation affecting alveolar-capillary membrane, either by locally produced pro-inflammatory mediators or remotely produced and arriving via pulmonary artery.
Increase in permeability of the membrane allowing fluid and protein leakage into alveolar space manifesting as high permeability pulmonary oedema.
Resulting acute inflammatory exudate collapse and consolidation of distal airpaces with progressive loss of gas exchange surface area.
No compensatory hypoxic pulmonary vasoconstriction resulting in gross V/Q mismatch.<br>
slide5. ARDS diagnostic criteria (2012 ‘Berlin Definition)2 Timing; Onset within 1 week of known clinical insult
Radiology; Bilateral opacities consistent with pulmonary oedema on CXR or CT scan
Origin of oedema; Not fully explained by left sided heart failure or fluid overload. Echo indicated to assess LV function.
Respiratory failure; Oxygenation impairment defined by PaO2/FiO2 ratio at least <40 kPA (<300 mmHg) despite PEEP > 5 mmH2O
Mild – PaO2/FiO2 >27 kPa (> 200 mmHg)
Moderate – PaO2/FiO2 > 13 kPa (> 100 mmHg)
Severe – PaO2/FiO2 <13 kPa (<100 mmHg)<br>
slide6. Question 2. The patient is transferred to ICU. A bedside echocardiogram is performed which confirms preserved LV function and no signs of hypo/hypervolaemia.
She is initially trialled on CPAP with PEEP of 10 mmHg and FiO2 of 60 % but continues to deteriorate with progressive hypoxia over the next 4 hours. The decision is made to to proceed with intubation and invasive mechanical ventilation.
What would be the most appropriate initial ventilator settings?
SIMV mode, FiO2 80 %, PEEP 16, tidal volume 6 ml/kg IBW, RR 16
PS/CPAP mode, FiO2 25 %, PEEP 5, Tidal volume 6 ml/kg IBW, RR 16
SIMV mode, FiO2 80 %, PEEP 16, tidal volume 12 ml/kg IBW, RR 16
PS/CPAP mode, FiO2 50 %, PEEP 16, Tidal volume 6 ml/kg IBW, RR 16
SIMV mode, FiO2 80 %, PEEP 5, tidal volume 6 ml/kg IBW, RR 26<br>
slide7. Management of ARDS2<br>
slide8. Question 3. Over the next 6 days, the patient is managed with lung protective ventilation, high PEEP, prone positioning and a 48 hr infusion of neuromuscular blocking agent. In spite of this she fails to improve, as evidenced by worsening hypoxia. She has also developed an acute kidney injury necessitating renal replacement therapy, and her vasopressor requirements are increasing.
The ICU team decide to refer her for consideration of Extra-Corporeal Membrane Oxygenation.
What is most likely to lead to a decline in the referral?
Age >50 years
Recent extensive intra-abdominal surgery
Refractory multi-organ failure
Invasive ventilation for >5 days
CPAP treatment preceding invasive ventilation<br>
slide9. ECMO referral3,4 Indications Age >16 yrs
Potentially reversible severe acute respiratory failure
Severe hypoxaemia (Eg PaO2/FiO2 < 13.3 kPa)
Uncompensated hypercapnia with pH <7.2
No limitation to ongoing life-sustaining treatment
Inability to achieve lung protective tidal volumes and pressures
Murray lung injury score >3 Contraindications Age >65
Intracranial bleed (current/recent)
Other contraindications to heparinisation
Multi-organ failure
High pressure (PIP > 30 mmH20 and/or high FiO2 (>80%)) ventilation for more than 7 days (CPAP counts)
Prolonged cardiac arrest<br>
slide10. Murray Score (Lung Injury Score)3<br>
slide11. Question 4. The patient is declined for ECMO on the basis of established multi-organ failure. Her condition does, however, stabilise over the next few days, with reducing ventilatory support and the recovery of some renal function. The ICU team decide to proceed with full active management.
During a night shift as the ICU resident you are called by nursing staff to review her urgently. Her oxygen saturations have dropped rapidly – they are currently 85 % on 100 % FiO2 with PEEP of 16. HR is 130 bpm, sinus tachycardia, BP is 90/50. On examination there is decreased right sided chest expansion with minimal breath sounds. The oral ETT is 24 cm at the lips, which is unchanged from previously. Peak inspiratory pressures have risen to >40 mmH20.
What is the most appropriate treatment to improve the patient’s condition?
a) Therapeutic bronchoscopy
b) Needle decompression followed by chest drain insertion
c) Broad spectrum antibiotics
d) Thrombolysis
c) Pull back ETT 2 cm<br>
slide12. Complications of ARDS1 Barotrauma; Pneumothorax, surgical emphysema, pneumomediastium
Nosocomial infections/ventilator associated pneumonia
Myopathy
VTE
GI haemorrhage
Inadequate nutrition
Complications of proning;
Loss of venous access
ETT displacement
Nerve compression
Pressure sores
Retinal damage
Vomiting
Transient arrythmia/hypotension/desaturation<br>
slide13. Question 5. Following decompression of the tension pneumothorax, the patient continues to make gradual recovery. A percutaneous tracheostomy is inserted to aid with prolonged ventilator wean.
The patient is eventually stepped down from ICU to the respiratory ward with the tracheostomy still in situ.
Which of the following options would suggest tracheostomy decannulation is inappropriate?
No upper airway obstructions
Adequate independent secretion clearance
Tolerates cuff deflation for 24 hrs
Delirium with fluctuating GCS
Ongoing oxygen requirement<br>
slide14. Tracheostomy1, 5 Indications
Airway protection following major head and neck surgery
Prolonged ventilator wean
Neurospinal indications; cervical cord pathology, reduced GCS following neurological injury
Advantages
Improved patient communication
Improved tube tolerance
Reduced sedation requirement
Disadvantages
Increased tendency to aspirate
Reduced ability to talk
Increased infection risk
Tracheal stenosis<br>
slide15. Tracheostomy decannulation Should be carried out as soon as;
Adequate secretion clearance
Low probability of thick mucous plugs blocking large airways
No upper airway obstruction
No significant aspiration
No need to continue ventilation or reduce dead space for gas exchange
Patient tolerates cuff deflation for 24 hrs/speaking valve for 12 hrs
Haemodynamic stability
No new lung infiltrates on CXR
MDT agreement for decannulation<br>
slide16. References 1. Oxford Handbook of Respiratory Medicine 4th Edition
2. Faculty of Intensive Care Medicine/Intensive Care Society (2018) ”Guidelines on the Management of Acute Respiratory Distress Syndrome” Version 1
3. Royal Bromptom and Harefield Hospitals “ECMO Referrals and Transfer Pathways” https://www.rbht.nhs.uk/our-services/clinical_support/critical-care-and-anaesthesia/ecmo-and-severe-respiratory-failure/ecmo-referrals-and-transfer-pathway
4.NHS England ECMO National Referral Pathway https://www.signpost.healthcare/ecmo-referral-pathway
5. Stelfox HT, Crimi C, Berra L, Noto A, Schmidt U, Bigatello LM, Hess D (2008) “Determinants of tracheostomy decannulation: an international survey” Critical care 12:R26.<br>
slide17. Thank you for listening, any questions?<br>