
SURVEYOR-I: 98% – 100% SVR4 in HCV Genotype 1





Description: SURVEYOR-I: 98 100 SVR4 in HCV Genotype 1 Non-Cirrhotic Treatment-Naïve or Pegylated InterferonRibavirin Null-Responders with the Combination of the Next Generation NS34A Protease Inhibitor ABT-493 and NS5A Inhibitor ABT-530 Fred
Related Topics
Download Presentation
"SURVEYOR-I: 98% – 100% SVR4 in HCV Genotype 1" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. SURVEYOR-I: 98% – 100% SVR4 in HCV Genotype 1 Non-Cirrhotic Treatment-Naïve or Pegylated Interferon/Ribavirin Null-Responders with the Combination of the Next Generation NS3/4A Protease Inhibitor ABT-493 and NS5A Inhibitor ABT-530 Fred Poordad,1 Franco Felizarta,2 Armen Asatryan,3 Tarek Hassanein,4 Humberto Aguilar,5 Jacob Lalezari,6 J. Scott Overcash,7 Teresa I. Ng,3 Ran Liu,3 Chih-Wei Lin,3 Federico J. Mensa,3 Jens Kort3 66th Annual Meeting of the American Association for the Study of Liver Diseases
• San Francisco, CA •
15 November 2015 1Texas Liver Institute, University of Texas Health Science Center, San Antonio, TX, USA; 2Private practice, Bakersfield, CA, USA; 3AbbVie Inc., North Chicago, IL, USA; 4Southern California GI and Liver Centers and Southern California Research Center, Coronado, CA, USA; 5Louisiana Research Center, Shreveport, LA, USA; 6Quest Clinical Research, San Francisco, CA, USA; 7eStudySite, San Diego, CA, USA<br>
slide2. Disclosures F Poordad: Grant/Research support: Abbvie, Achillion Pharmaceuticals, Anadys Pharmaceuticals, Biolex Therapeutics, Boehringer Ingelheim, Bristol-Myers Squibb, Genentech, Gilead Sciences, GlaxoSmithKline, GlobeImmune, Idenix Pharmaceuticals, Idera Pharmaceuticals, Intercept Pharmaceuticals, Janssen, Medarex, Medtronic, Merck, Novartis, Santaris Pharmaceuticals, Scynexis Pharmaceuticals, Vertex Pharmaceuticals, ZymoGenetics. Speaker: Gilead, Kadmon, Merck, Onyx/Bayer, Genentech, GlaxoSmithKline, Salix, Vertex. Consultant/Advisor: AbbVie, Achillion Pharmaceuticals, Anadys Pharmaceuticals, Biolex Therapeutics, Boehringer Ingelheim, Bristol-Myers Squibb, Gilead Sciences, GlaxoSmithKline, GlobeImmune, Idenix, Merck, Novartis, Tibotec/Janssen, Theravance, Vertex
F Felizarta: Research support (principal investigator): AbbVie, Achillion, BMS, Gilead, Janssen, Merck, and Novartis. Speaker: AbbVie, Gilead, Janssen, Merck
T Hassanein: Grants/Research support: AbbVie (Advisory Board), Boehringer-Ingelheim, Bristol-Myers Squibb (Advisory Board), Eisai, Gilead Sciences, Janssen, Idenix, Ikaria, Mochida, Roche, Ocera, Taigen, Takeda, Salix, Sundise, Vertex. Speaker: Baxter, Bristol-Myers Squibb, Gilead, Salix
H Aguilar: Grants: AbbVie. Speaker: Santarus, Ironwood, AbbVie
J Lalezari: Research support (principal investigator): AbbVie
JS Overcash: No relevant conflicts to disclose
A Asatryan, TI Ng, R Liu, CW Lin, F Mensa, and J Kort: AbbVie employees and may hold AbbVie stock or stock options.
The design, study conduct, analysis, and financial support of the SURVEYOR-I (NCT02243280) study were provided by AbbVie. AbbVie participated in the interpretation of data, review, and approval of the content. All authors had access to all relevant data and participated in writing, review, and approval of this presentation. Medical writing support was provided by Sharanya Ford, PhD, of AbbVie.
This presentation contains information on the investigational products ABT-493 and ABT-530.<br>
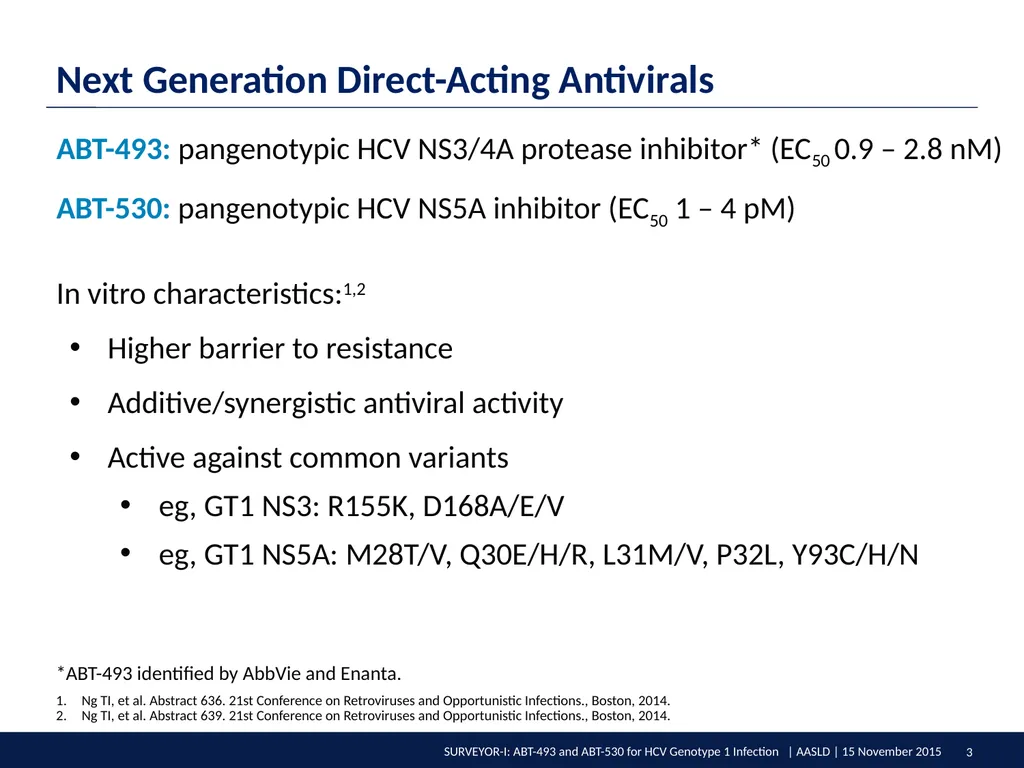
slide3. Next Generation Direct-Acting Antivirals ABT-493: pangenotypic HCV NS3/4A protease inhibitor* (EC50 0.9 – 2.8 nM)
ABT-530: pangenotypic HCV NS5A inhibitor (EC50 1 – 4 pM)
In vitro characteristics:1,2
Higher barrier to resistance
Additive/synergistic antiviral activity
Active against common variants
eg, GT1 NS3: R155K, D168A/E/V
eg, GT1 NS5A: M28T/V, Q30E/H/R, L31M/V, P32L, Y93C/H/N *ABT-493 identified by AbbVie and Enanta.
Ng TI, et al. Abstract 636. 21st Conference on Retroviruses and Opportunistic Infections., Boston, 2014.
Ng TI, et al. Abstract 639. 21st Conference on Retroviruses and Opportunistic Infections., Boston, 2014.<br>
slide4. Simeprevir prescribing information
Chase R, et al. IAPAC, 2013
McPhee F, et al. AAC, 2012
Yang H, et al. AAC, 2014
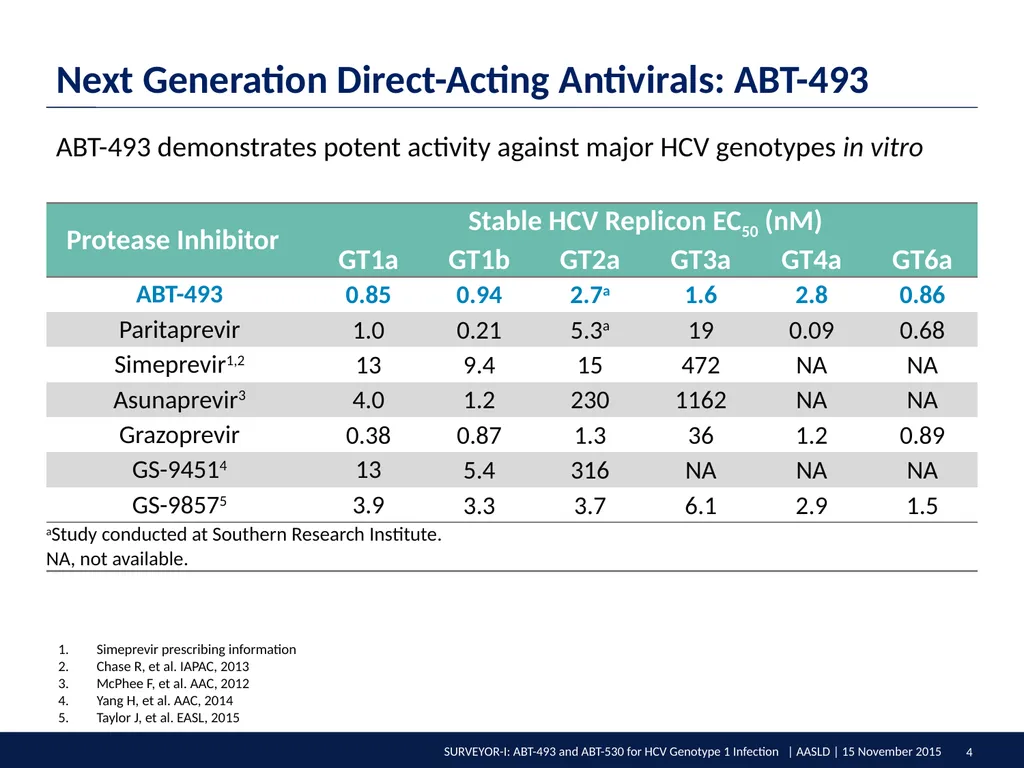
Taylor J, et al. EASL, 2015 Next Generation Direct-Acting Antivirals: ABT-493 ABT-493 demonstrates potent activity against major HCV genotypes in vitro<br>
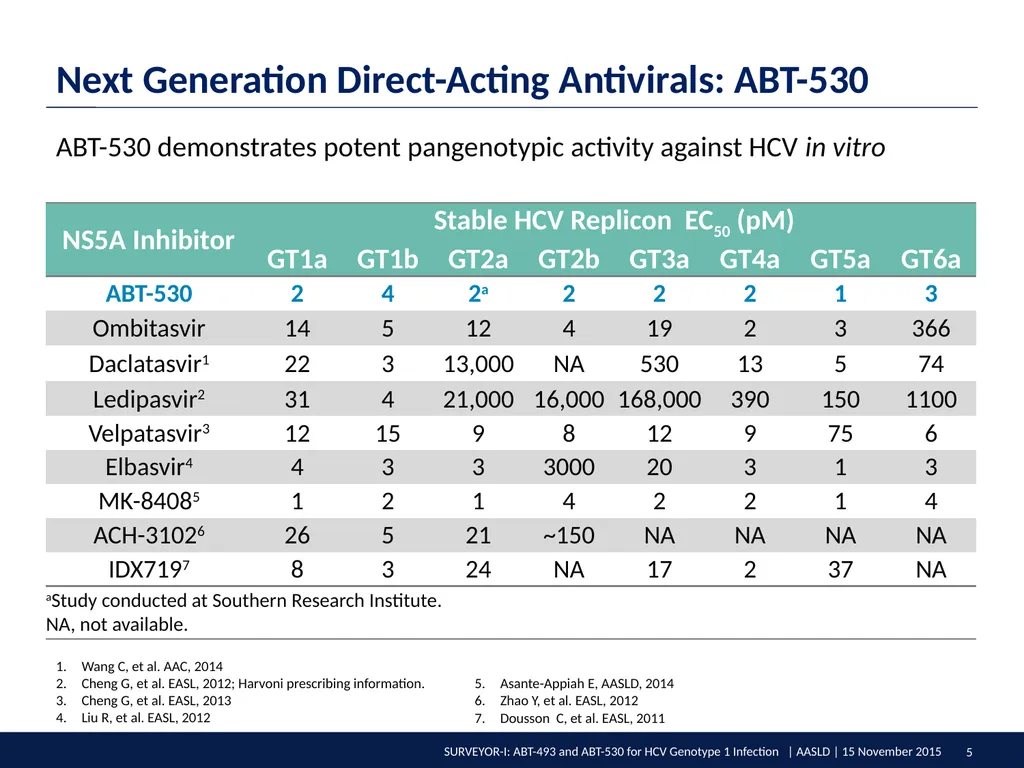
slide5. Next Generation Direct-Acting Antivirals: ABT-530 ABT-530 demonstrates potent pangenotypic activity against HCV in vitro<br>
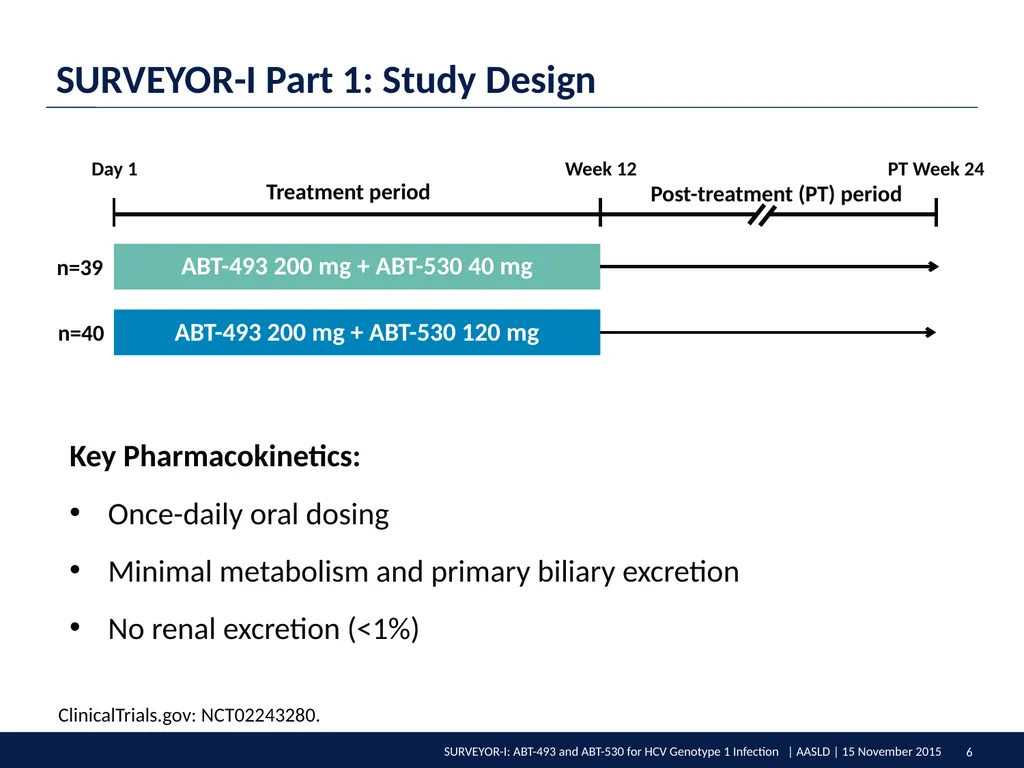
slide6. Key Pharmacokinetics:
Once-daily oral dosing
Minimal metabolism and primary biliary excretion
No renal excretion (<1%) SURVEYOR-I Part 1: Study Design ClinicalTrials.gov: NCT02243280.<br>
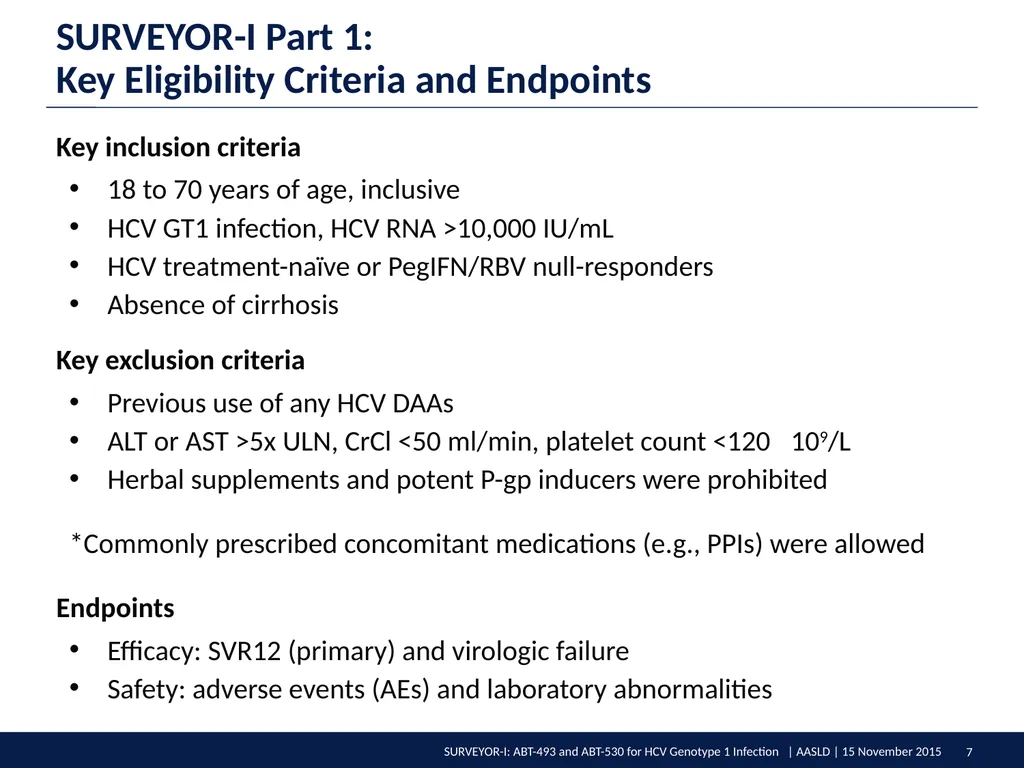
slide7. SURVEYOR-I Part 1: Key Eligibility Criteria and Endpoints Key inclusion criteria
18 to 70 years of age, inclusive
HCV GT1 infection, HCV RNA >10,000 IU/mL
HCV treatment-naïve or PegIFN/RBV null-responders
Absence of cirrhosis
Key exclusion criteria
Previous use of any HCV DAAs
ALT or AST >5x ULN, CrCl <50 ml/min, platelet count <120 109/L
Herbal supplements and potent P-gp inducers were prohibited
*Commonly prescribed concomitant medications (e.g., PPIs) were allowed
Endpoints
Efficacy: SVR12 (primary) and virologic failure
Safety: adverse events (AEs) and laboratory abnormalities<br>
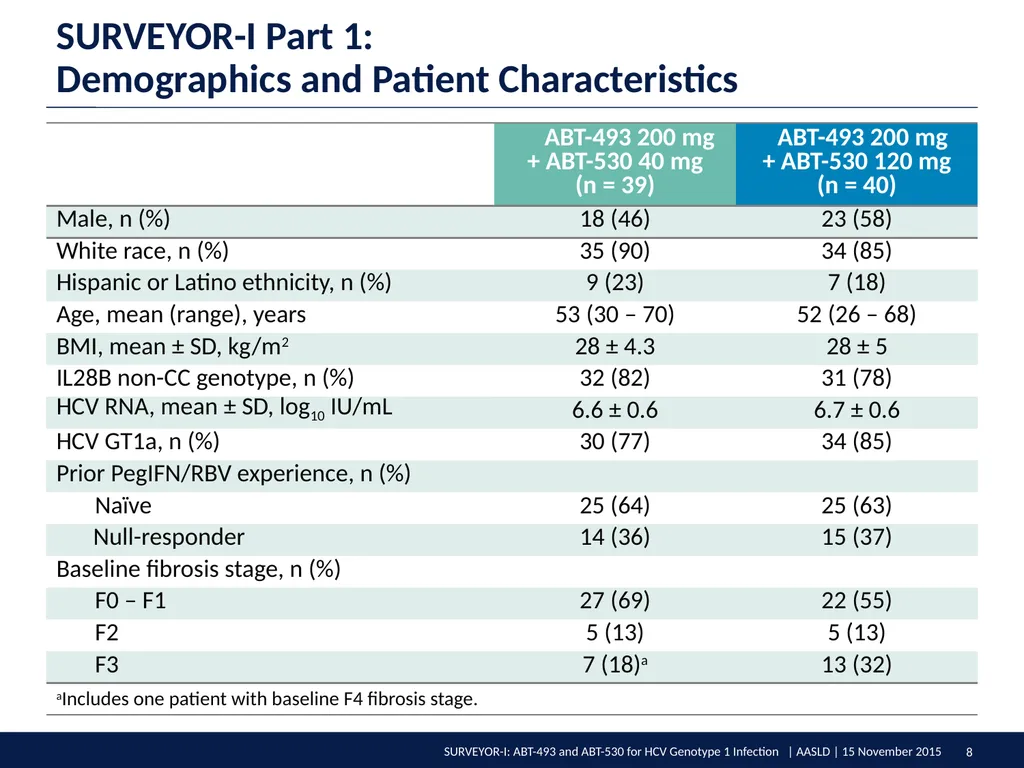
slide8. SURVEYOR-I Part 1: Demographics and Patient Characteristics<br>
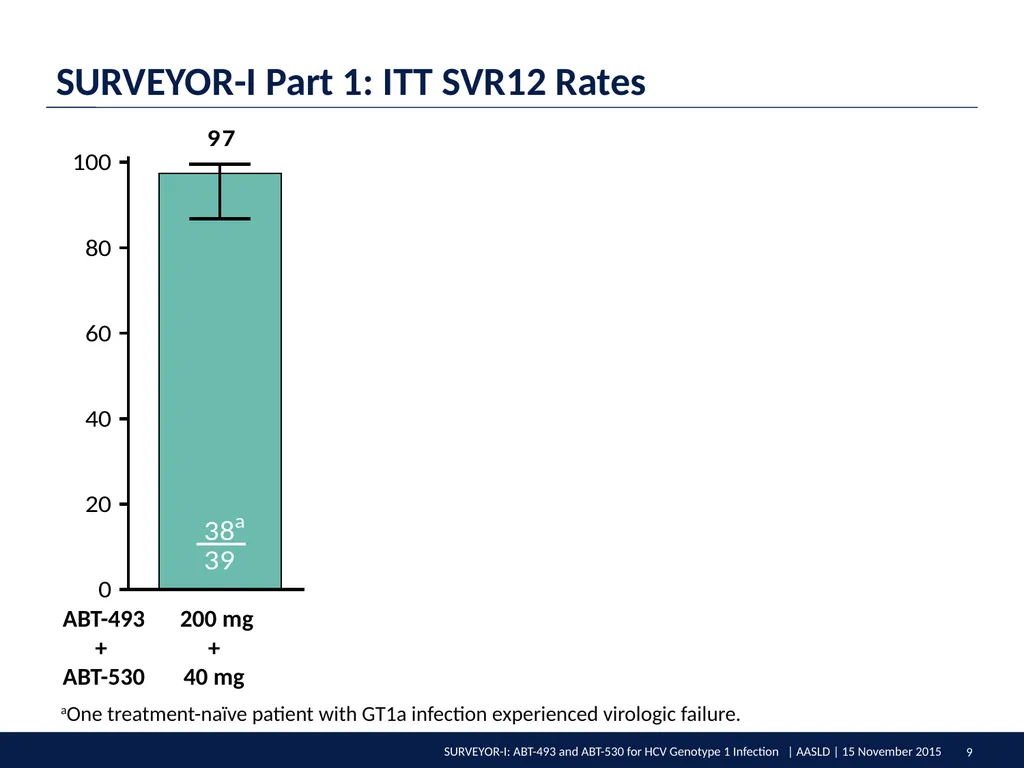
slide9. SURVEYOR-I Part 1: ITT SVR12 Rates ABT-493 200 mg
+
ABT-530 120 mg aOne treatment-naïve patient with GT1a infection experienced virologic failure.<br>
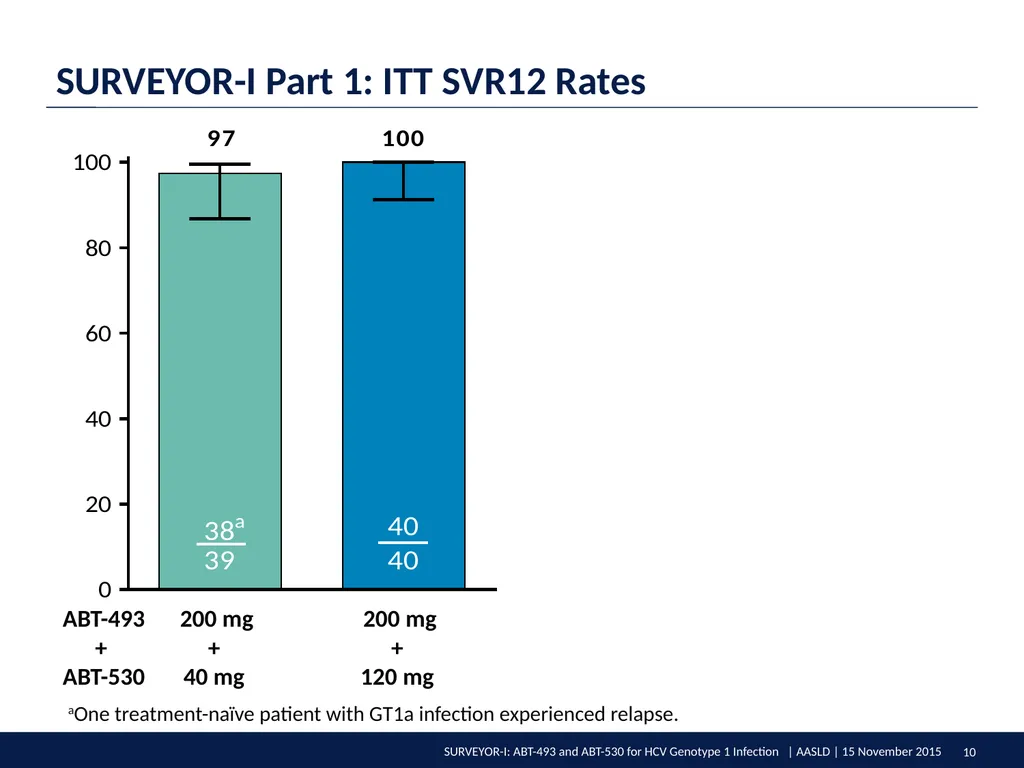
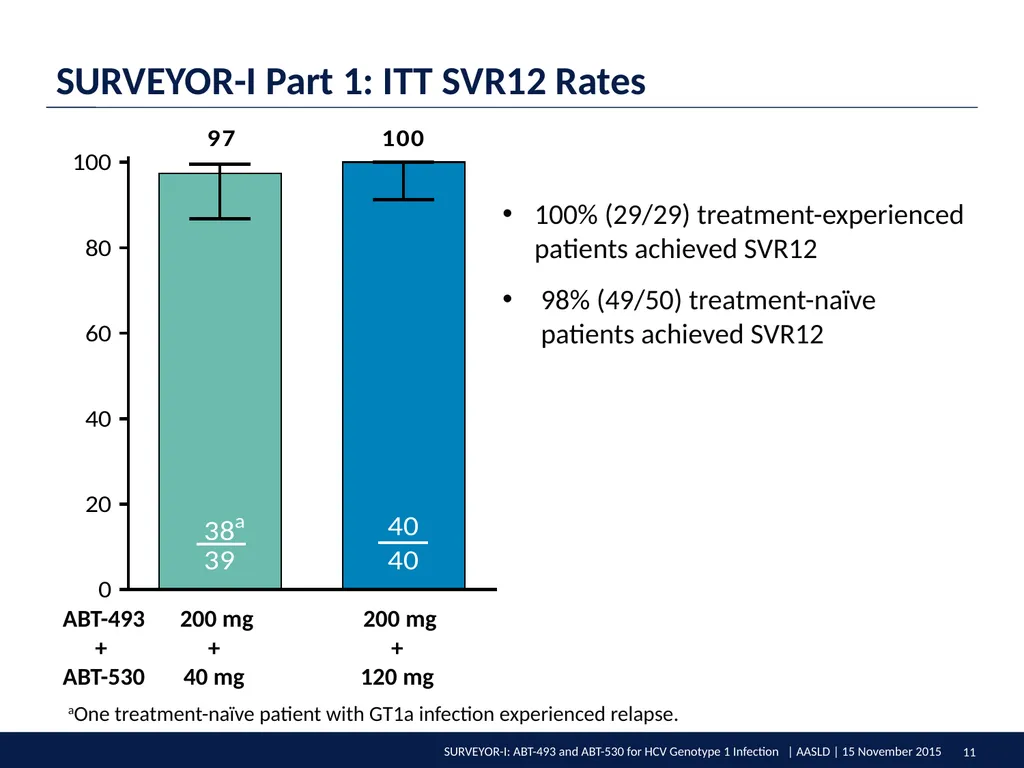
slide10. SURVEYOR-I Part 1: ITT SVR12 Rates aOne treatment-naïve patient with GT1a infection experienced relapse.<br>
slide11. SURVEYOR-I Part 1: ITT SVR12 Rates aOne treatment-naïve patient with GT1a infection experienced relapse. 100% (29/29) treatment-experienced patients achieved SVR12
98% (49/50) treatment-naïve patients achieved SVR12<br>
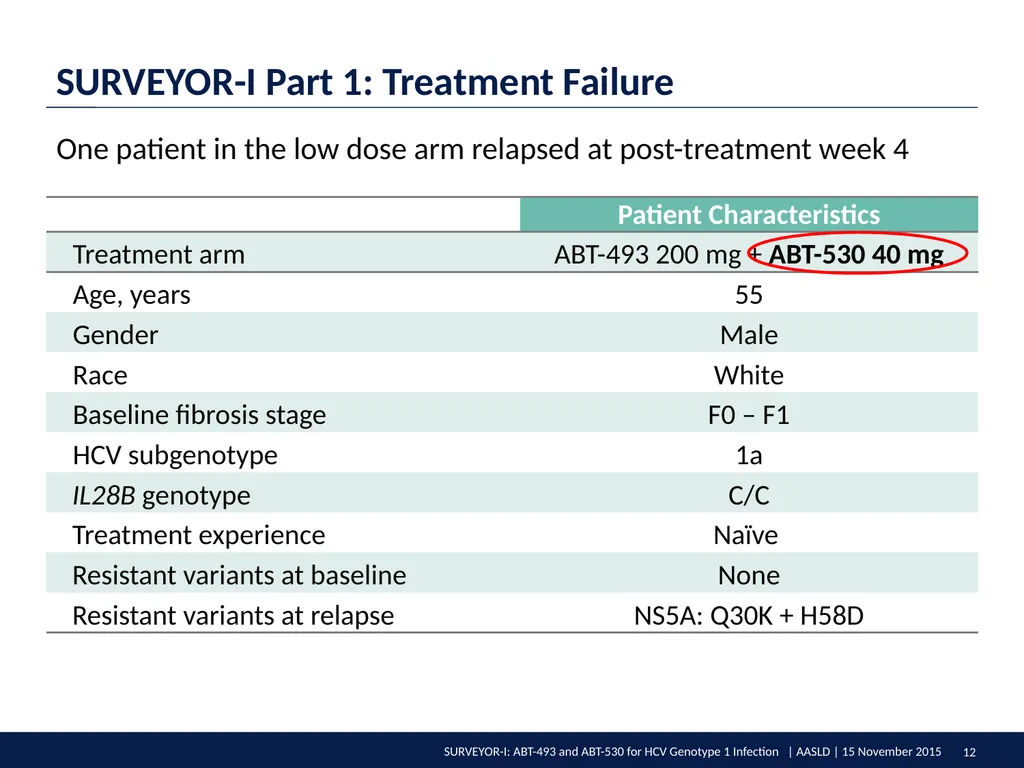
slide12. One patient in the low dose arm relapsed at post-treatment week 4 SURVEYOR-I Part 1: Treatment Failure<br>
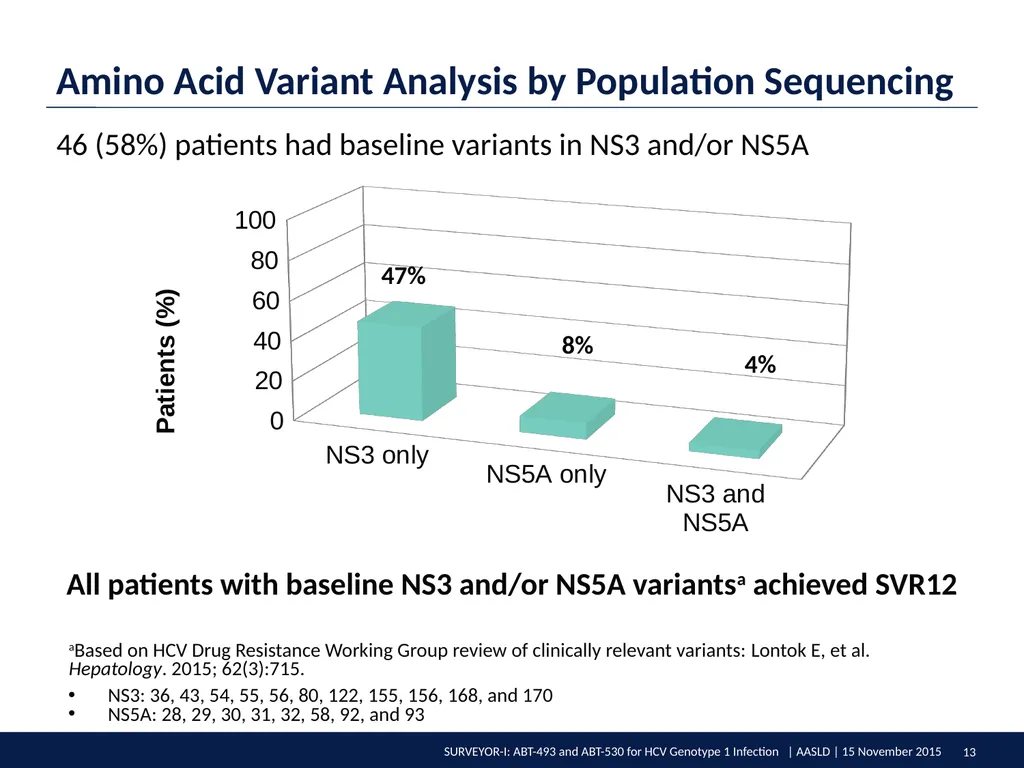
slide13. 46 (58%) patients had baseline variants in NS3 and/or NS5A Amino Acid Variant Analysis by Population Sequencing aBased on HCV Drug Resistance Working Group review of clinically relevant variants: Lontok E, et al. Hepatology. 2015; 62(3):715.
NS3: 36, 43, 54, 55, 56, 80, 122, 155, 156, 168, and 170
NS5A: 28, 29, 30, 31, 32, 58, 92, and 93 All patients with baseline NS3 and/or NS5A variantsa achieved SVR12<br>
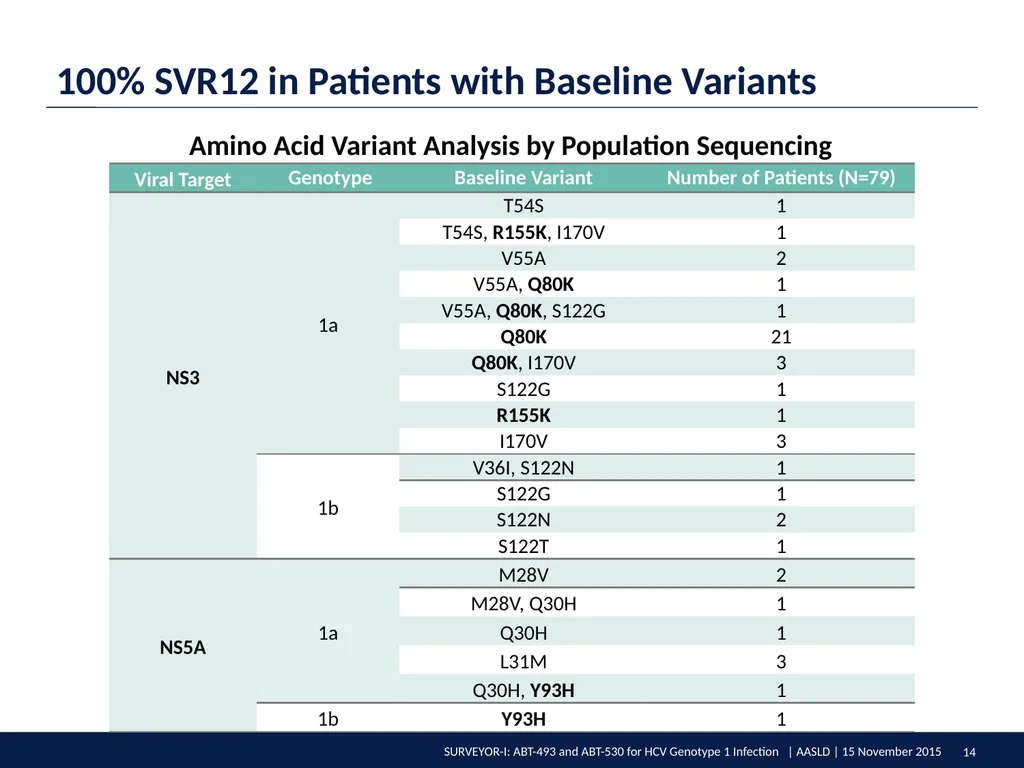
slide14. 100% SVR12 in Patients with Baseline Variants Amino Acid Variant Analysis by Population Sequencing<br>
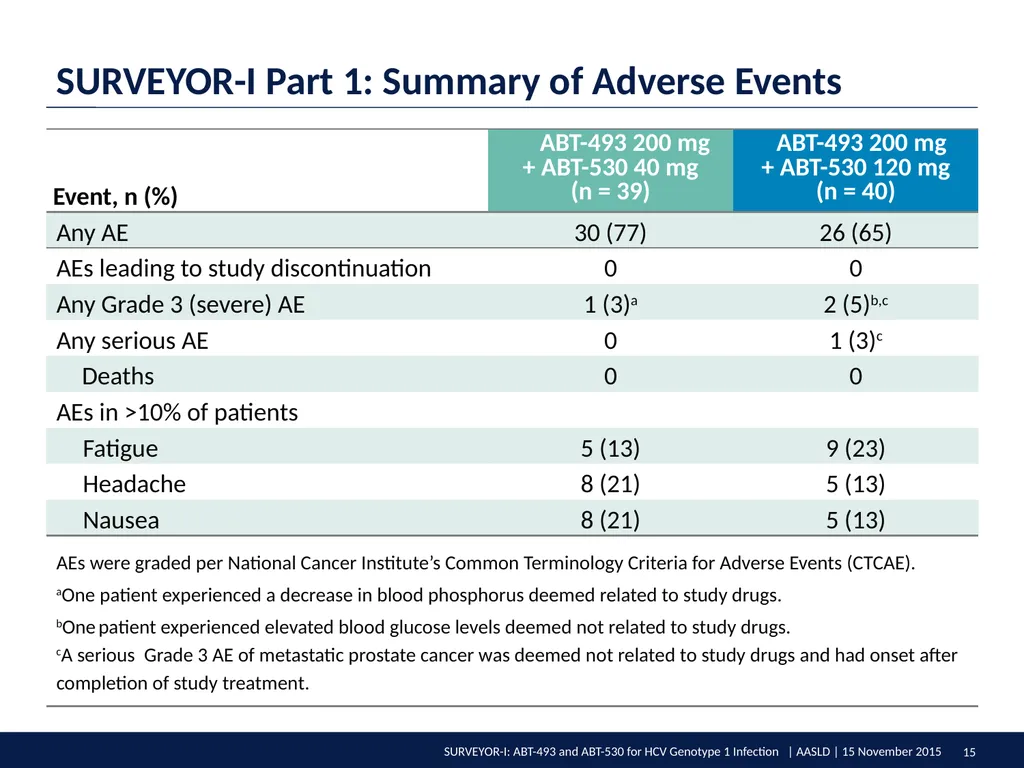
slide15. SURVEYOR-I Part 1: Summary of Adverse Events<br>
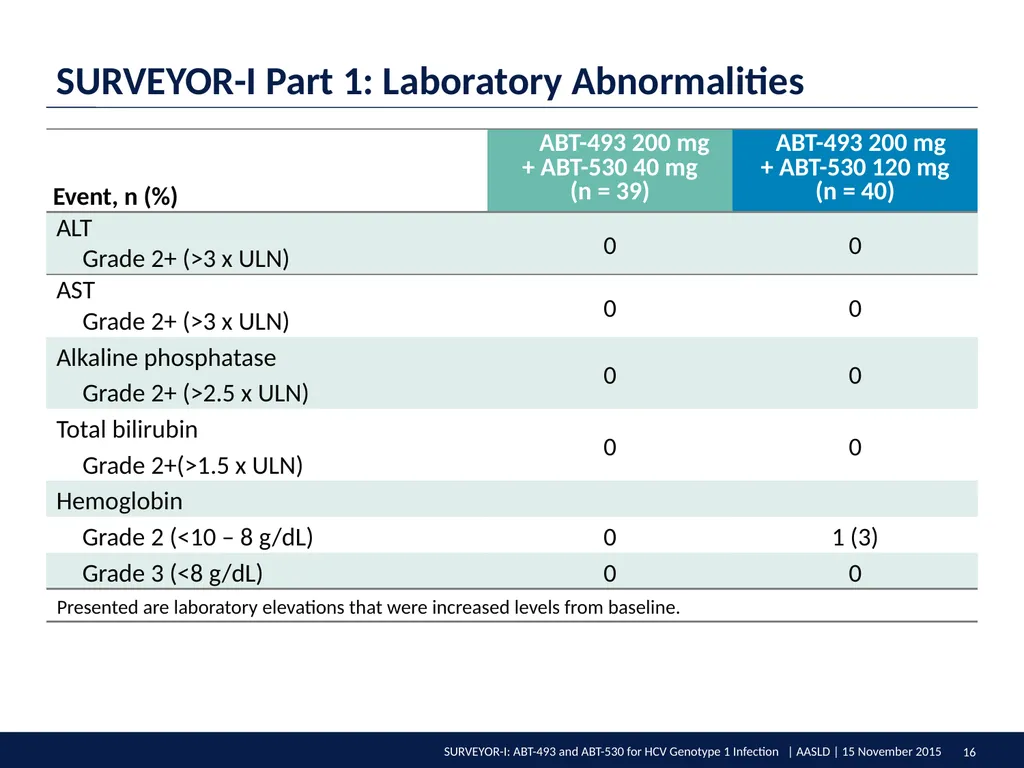
slide16. SURVEYOR-I Part 1: Laboratory Abnormalities<br>
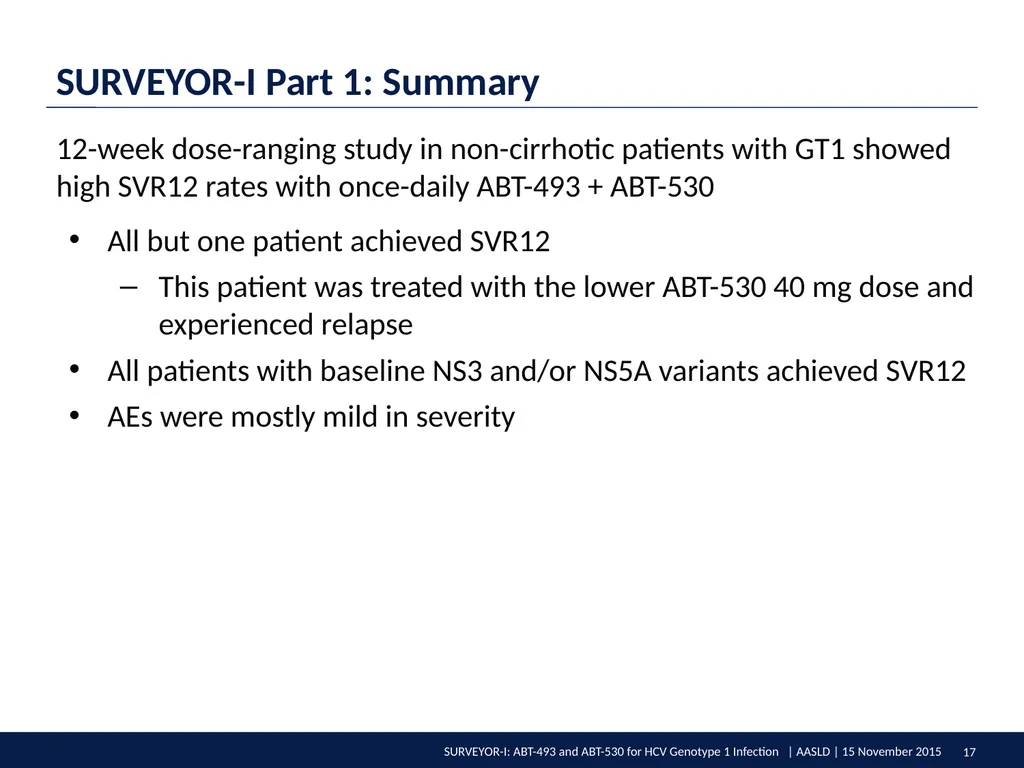
slide17. SURVEYOR-I Part 1: Summary 12-week dose-ranging study in non-cirrhotic patients with GT1 showed high SVR12 rates with once-daily ABT-493 + ABT-530
All but one patient achieved SVR12
This patient was treated with the lower ABT-530 40 mg dose and experienced relapse
All patients with baseline NS3 and/or NS5A variants achieved SVR12
AEs were mostly mild in severity<br>
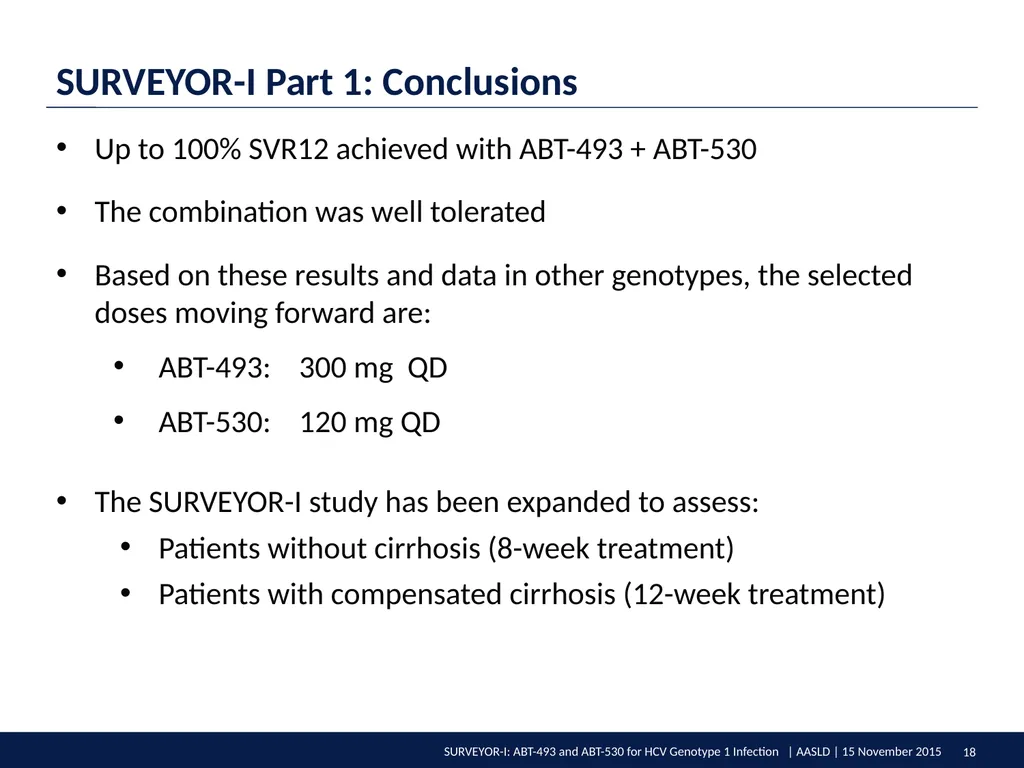
slide18. Up to 100% SVR12 achieved with ABT-493 + ABT-530
The combination was well tolerated
Based on these results and data in other genotypes, the selected doses moving forward are:
ABT-493: 300 mg QD
ABT-530: 120 mg QD
The SURVEYOR-I study has been expanded to assess:
Patients without cirrhosis (8-week treatment)
Patients with compensated cirrhosis (12-week treatment) SURVEYOR-I Part 1: Conclusions<br>
slide19. Acknowledgments The authors would like to express their gratitude to the patients and their families, investigators, study coordinators, and AbbVie/CRO study staff who made this study possible.<br>
• San Francisco, CA •
15 November 2015 1Texas Liver Institute, University of Texas Health Science Center, San Antonio, TX, USA; 2Private practice, Bakersfield, CA, USA; 3AbbVie Inc., North Chicago, IL, USA; 4Southern California GI and Liver Centers and Southern California Research Center, Coronado, CA, USA; 5Louisiana Research Center, Shreveport, LA, USA; 6Quest Clinical Research, San Francisco, CA, USA; 7eStudySite, San Diego, CA, USA<br>
slide2. Disclosures F Poordad: Grant/Research support: Abbvie, Achillion Pharmaceuticals, Anadys Pharmaceuticals, Biolex Therapeutics, Boehringer Ingelheim, Bristol-Myers Squibb, Genentech, Gilead Sciences, GlaxoSmithKline, GlobeImmune, Idenix Pharmaceuticals, Idera Pharmaceuticals, Intercept Pharmaceuticals, Janssen, Medarex, Medtronic, Merck, Novartis, Santaris Pharmaceuticals, Scynexis Pharmaceuticals, Vertex Pharmaceuticals, ZymoGenetics. Speaker: Gilead, Kadmon, Merck, Onyx/Bayer, Genentech, GlaxoSmithKline, Salix, Vertex. Consultant/Advisor: AbbVie, Achillion Pharmaceuticals, Anadys Pharmaceuticals, Biolex Therapeutics, Boehringer Ingelheim, Bristol-Myers Squibb, Gilead Sciences, GlaxoSmithKline, GlobeImmune, Idenix, Merck, Novartis, Tibotec/Janssen, Theravance, Vertex
F Felizarta: Research support (principal investigator): AbbVie, Achillion, BMS, Gilead, Janssen, Merck, and Novartis. Speaker: AbbVie, Gilead, Janssen, Merck
T Hassanein: Grants/Research support: AbbVie (Advisory Board), Boehringer-Ingelheim, Bristol-Myers Squibb (Advisory Board), Eisai, Gilead Sciences, Janssen, Idenix, Ikaria, Mochida, Roche, Ocera, Taigen, Takeda, Salix, Sundise, Vertex. Speaker: Baxter, Bristol-Myers Squibb, Gilead, Salix
H Aguilar: Grants: AbbVie. Speaker: Santarus, Ironwood, AbbVie
J Lalezari: Research support (principal investigator): AbbVie
JS Overcash: No relevant conflicts to disclose
A Asatryan, TI Ng, R Liu, CW Lin, F Mensa, and J Kort: AbbVie employees and may hold AbbVie stock or stock options.
The design, study conduct, analysis, and financial support of the SURVEYOR-I (NCT02243280) study were provided by AbbVie. AbbVie participated in the interpretation of data, review, and approval of the content. All authors had access to all relevant data and participated in writing, review, and approval of this presentation. Medical writing support was provided by Sharanya Ford, PhD, of AbbVie.
This presentation contains information on the investigational products ABT-493 and ABT-530.<br>
slide3. Next Generation Direct-Acting Antivirals ABT-493: pangenotypic HCV NS3/4A protease inhibitor* (EC50 0.9 – 2.8 nM)
ABT-530: pangenotypic HCV NS5A inhibitor (EC50 1 – 4 pM)
In vitro characteristics:1,2
Higher barrier to resistance
Additive/synergistic antiviral activity
Active against common variants
eg, GT1 NS3: R155K, D168A/E/V
eg, GT1 NS5A: M28T/V, Q30E/H/R, L31M/V, P32L, Y93C/H/N *ABT-493 identified by AbbVie and Enanta.
Ng TI, et al. Abstract 636. 21st Conference on Retroviruses and Opportunistic Infections., Boston, 2014.
Ng TI, et al. Abstract 639. 21st Conference on Retroviruses and Opportunistic Infections., Boston, 2014.<br>
slide4. Simeprevir prescribing information
Chase R, et al. IAPAC, 2013
McPhee F, et al. AAC, 2012
Yang H, et al. AAC, 2014
Taylor J, et al. EASL, 2015 Next Generation Direct-Acting Antivirals: ABT-493 ABT-493 demonstrates potent activity against major HCV genotypes in vitro<br>
slide5. Next Generation Direct-Acting Antivirals: ABT-530 ABT-530 demonstrates potent pangenotypic activity against HCV in vitro<br>
slide6. Key Pharmacokinetics:
Once-daily oral dosing
Minimal metabolism and primary biliary excretion
No renal excretion (<1%) SURVEYOR-I Part 1: Study Design ClinicalTrials.gov: NCT02243280.<br>
slide7. SURVEYOR-I Part 1: Key Eligibility Criteria and Endpoints Key inclusion criteria
18 to 70 years of age, inclusive
HCV GT1 infection, HCV RNA >10,000 IU/mL
HCV treatment-naïve or PegIFN/RBV null-responders
Absence of cirrhosis
Key exclusion criteria
Previous use of any HCV DAAs
ALT or AST >5x ULN, CrCl <50 ml/min, platelet count <120 109/L
Herbal supplements and potent P-gp inducers were prohibited
*Commonly prescribed concomitant medications (e.g., PPIs) were allowed
Endpoints
Efficacy: SVR12 (primary) and virologic failure
Safety: adverse events (AEs) and laboratory abnormalities<br>
slide8. SURVEYOR-I Part 1: Demographics and Patient Characteristics<br>
slide9. SURVEYOR-I Part 1: ITT SVR12 Rates ABT-493 200 mg
+
ABT-530 120 mg aOne treatment-naïve patient with GT1a infection experienced virologic failure.<br>
slide10. SURVEYOR-I Part 1: ITT SVR12 Rates aOne treatment-naïve patient with GT1a infection experienced relapse.<br>
slide11. SURVEYOR-I Part 1: ITT SVR12 Rates aOne treatment-naïve patient with GT1a infection experienced relapse. 100% (29/29) treatment-experienced patients achieved SVR12
98% (49/50) treatment-naïve patients achieved SVR12<br>
slide12. One patient in the low dose arm relapsed at post-treatment week 4 SURVEYOR-I Part 1: Treatment Failure<br>
slide13. 46 (58%) patients had baseline variants in NS3 and/or NS5A Amino Acid Variant Analysis by Population Sequencing aBased on HCV Drug Resistance Working Group review of clinically relevant variants: Lontok E, et al. Hepatology. 2015; 62(3):715.
NS3: 36, 43, 54, 55, 56, 80, 122, 155, 156, 168, and 170
NS5A: 28, 29, 30, 31, 32, 58, 92, and 93 All patients with baseline NS3 and/or NS5A variantsa achieved SVR12<br>
slide14. 100% SVR12 in Patients with Baseline Variants Amino Acid Variant Analysis by Population Sequencing<br>
slide15. SURVEYOR-I Part 1: Summary of Adverse Events<br>
slide16. SURVEYOR-I Part 1: Laboratory Abnormalities<br>
slide17. SURVEYOR-I Part 1: Summary 12-week dose-ranging study in non-cirrhotic patients with GT1 showed high SVR12 rates with once-daily ABT-493 + ABT-530
All but one patient achieved SVR12
This patient was treated with the lower ABT-530 40 mg dose and experienced relapse
All patients with baseline NS3 and/or NS5A variants achieved SVR12
AEs were mostly mild in severity<br>
slide18. Up to 100% SVR12 achieved with ABT-493 + ABT-530
The combination was well tolerated
Based on these results and data in other genotypes, the selected doses moving forward are:
ABT-493: 300 mg QD
ABT-530: 120 mg QD
The SURVEYOR-I study has been expanded to assess:
Patients without cirrhosis (8-week treatment)
Patients with compensated cirrhosis (12-week treatment) SURVEYOR-I Part 1: Conclusions<br>
slide19. Acknowledgments The authors would like to express their gratitude to the patients and their families, investigators, study coordinators, and AbbVie/CRO study staff who made this study possible.<br>