
Timby’s Introductory Medical–Surgical Nursing, 13e


















Description: Timbys Introductory MedicalSurgical Nursing, 13e Chapter 11: Pain Management Pain Pain is a privately experienced, unpleasant sensation usually associated with disease or injury. Emotional componentsuffering Classification Source:
Related Topics
Download Presentation
"Timby’s Introductory Medical–Surgical Nursing, 13e" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Timby’s Introductory Medical–Surgical Nursing, 13e Chapter 11: Pain Management<br>
slide2. Pain Pain is a privately experienced, unpleasant sensation usually associated with disease or injury.
Emotional component—suffering
Classification
Source: nociceptive or neuropathic
Onset, intensity, and duration: acute or chronic<br>
slide3. Nociceptive Pain Noxious stimuli that are transmitted from the point of cellular injury over peripheral sensory nerves to pathways between the spinal cord and thalamus and from the thalamus to the cerebral cortex of the brain
Nociceptive pain types
Somatic pain
Visceral pain<br>
slide4. Nociceptive: Somatic Pain Caused by mechanical, chemical, thermal, or electrical injuries or disorders affecting bones, joints, muscles, skin, or other structures composed of connective tissue
Superficial somatic pain/cutaneous pain: from insect bite or paper cut; perceived as sharp or burning discomfort
Deeper somatic pain: caused by trauma; produces sensations that are sharp, throbbing, and intense
Dull, aching, diffuse discomfort with long-term disorders
Example: arthritis<br>
slide5. Nociceptive: Visceral Pain Arises from internal organs such as the heart, kidneys, and intestine that are diseased or injured
Causes: ischemia, compression of an organ, intestinal distention, contraction
Is usually diffuse, poorly localized, accompanied by ANS symptoms such as nausea, vomiting, pallor, hypotension, and sweating
Referred pain: discomfort in a general area of the body but not in the exact site where an organ is located<br>
slide6. Neuropathic Pain Pain processed abnormally by the nervous system
Results from damage to either the pain pathways in peripheral nerves or pain-processing centers in the brain
Examples: phantom limb pain, spinal cord injuries, strokes, diabetes, and herpes zoster (shingles)
Cancer pain: nociceptive or neuropathic
Nerve damage: radiation or drugs<br>
slide7. Acute Pain Acute pain: less than 6 months
Associated with tissue trauma: eases with healing
Manifestations: elevated blood pressure and heart and respiratory rates, diaphoresis, and dilated pupils
See Table 11-1
Chronic pain: lasts longer than 6 months
Affects quality of life; others begin to show negative reactions to sufferer
Breakthrough pain
Manifestations: similar to the symptoms of depression, including hopelessness, weight loss, fatigue, or physical immobility<br>
slide8. Question #1 Chronic pain is described as an unpleasant sensory and emotional experience associated with:
A) Actual tissue damage
B) Actual or potential tissue damage
C) Only observable pain behaviors
D) Physiologic signs and symptoms that the pain exists<br>
slide9. Answer to Question #1 B) Actual or potential tissue damage
Rationale: Chronic pain is associated with actual or potential tissue damage. Chronic pain is associated with many pain behaviors that people do not normally associate with pain. There is no change in vital signs with chronic pain.<br>
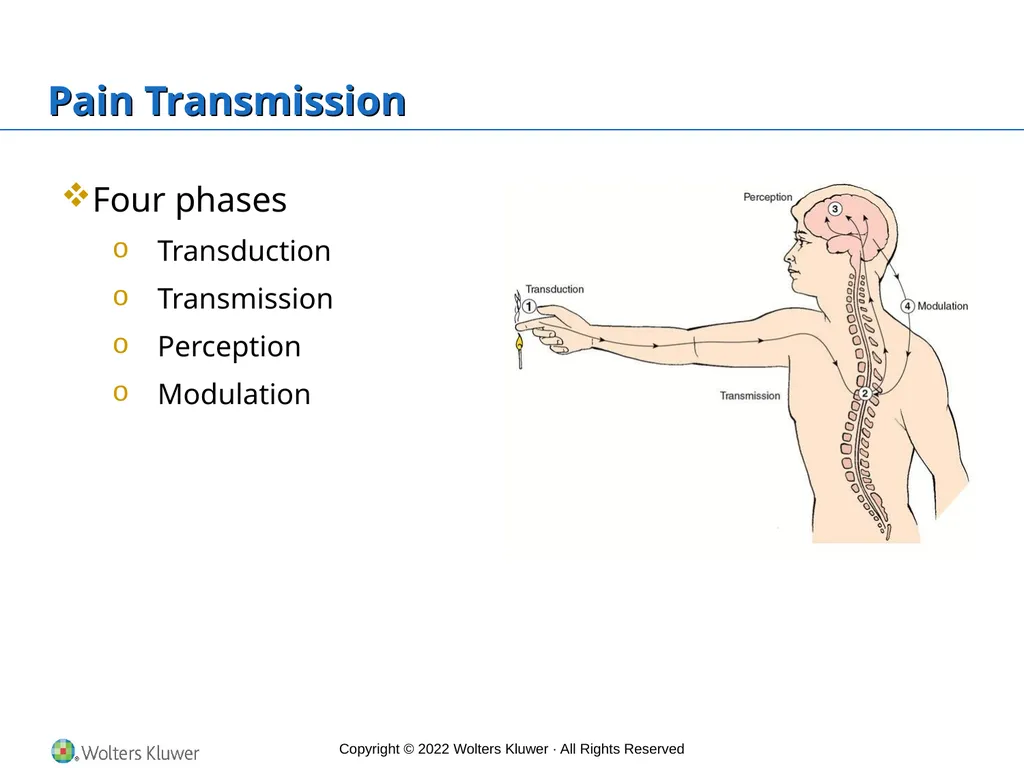
slide10. Pain Transmission Four phases
Transduction
Transmission
Perception
Modulation<br>
slide11. Transduction Conversion of chemical information in the cellular environment to electrical impulses that move toward the spinal cord
Initiated by cellular disruption
Nociceptors: specialized pain receptors located in the free nerve endings of peripheral sensory nerves
A-delta fibers: can carry pain impulses fast or slow; get sharp, acute initial pain
C-fibers: throbbing, aching, or burning after initial pain<br>
slide12. Transmission Peripheral nerve fibers form synapses with neurons in the spinal cord.
Impulses move from the spinal cord to the brain.<br>
slide13. Perception Brain experiences pain at a conscious level; locates pain, its intensity, and what it means; and gives emotional response.
Pain threshold: point at which the pain-transmitting neurochemicals reach the brain, causing conscious awareness
Hyperalgesia
Pain tolerance: amount of pain a person endures once the threshold has been reached
Variables: age, gender, fatigue<br>
slide14. Modulation Brain transmits a response down the spinal nerves to the point where the pain transmission originated to alter the pain experience.
Endogenous opioids—neurochemical
Painful sensation is reduced.
Pain Theories
Specificity Theory
Pattern Theory
Gate Control Theory
Neuromatrix Theory
Endogenous Opioid Theory<br>
slide15. Pain Assessment #1 Client’s description of its onset, quality, intensity, location, and duration
What makes the pain better or worse?
Nonverbal behaviors: clenched jaw, frowning, crying, rocking, or fidgeting
Allodynia—exaggerated pain response
Assessment biases: client’s pain misunderstood<br>
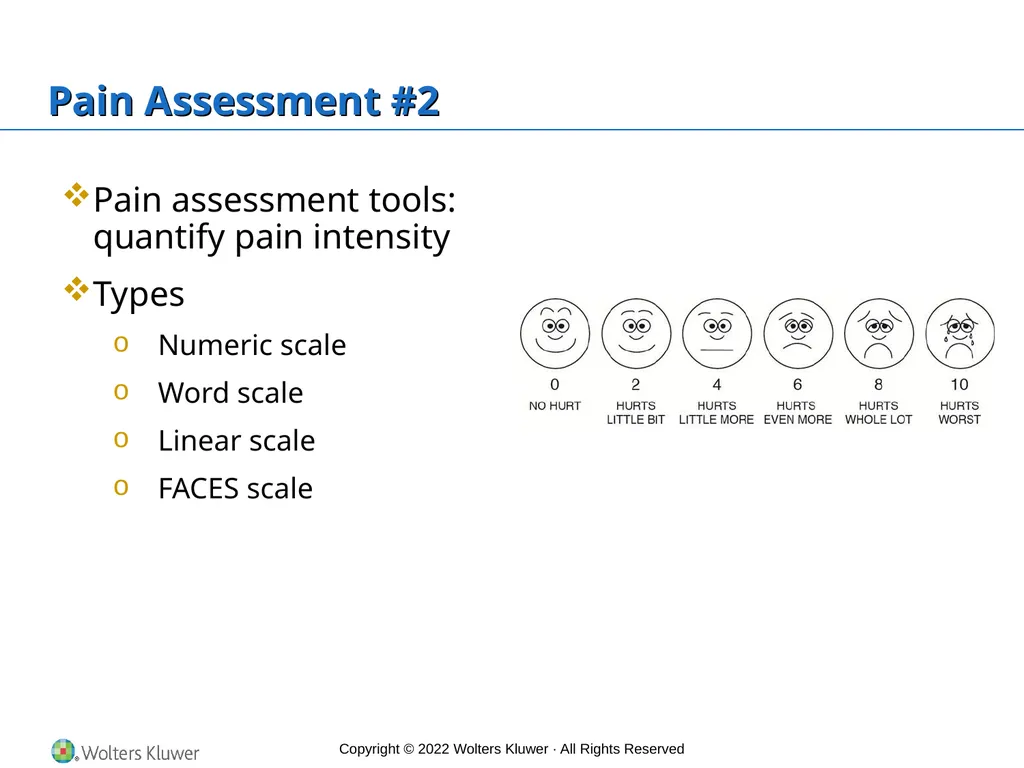
slide16. Pain Assessment #2 Pain assessment tools: quantify pain intensity
Types
Numeric scale
Word scale
Linear scale
FACES scale<br>
slide17. Assessment Standards Accredited health care facilities
Right to assessment and pain management
Assessment is appropriate for age, developmental level, condition, and culture.
Pain is reassessed regularly.
Health care workers are educated on pain management.
Client’s choices of pain management are respected.<br>
slide18. Pain Management #1 Drug and nondrug interventions
Techniques for pain management
Blocking brain perception
Interrupting pain-transmitting chemicals
Combining analgesics
Substituting sensory stimuli
Altering pain transmission<br>
slide19. Question #2 To evaluate adequately the effectiveness of pain control regimens, the nurse should:
A) Be casual and informal
B) Not bother if the client is quiet
C) Use a pain assessment tool
D) Rely on the feedback from the client’s family member<br>
slide20. Answer to Question #2 C) Use a pain assessment tool
Rationale: An effective pain treatment requires a thorough pain assessment.<br>
slide21. Pain Management #2 Techniques used to prevent, reduce, or relieve pain
Drug therapy See Table 11-1
Opioids—narcotic: interfere with pain perception centrally (at the brain); used for mild to moderate pain
Oxycodone, morphine sulfate
Adjuvant Drug Therapy
medications that are ordinarily administered for reasons other than treating pain
Nonopioids—non-narcotic: alter neurotransmission at the peripheral level (sight of injury); for mild pain
Ketorolac tromethamine (Toradol), Tylenol<br>
slide22. Methods of Pain Medication Administration Routes
Analgesic drugs: oral, rectal, transdermal, or parenteral
Equianalgesic dose
Patient-controlled analgesia (PCA)
Intraspinal analgesia
Palliative sedation: relieving intractable pain experienced by dying client
See Table 11-4<br>
slide23. Addiction Repetitive pattern of drug seeking and drug use to satisfy a craving for a drug’s mind-altering or mood-altering effects
Fewer than 1% of clients who need drugs for pain relief, even for more than 6 months become addicted.
Fears
Refuse or self-limit prescribed drug therapy
Nurses administer subtherapeutic doses.<br>
slide24. Tolerance Condition in which a client needs increasingly larger doses of a drug to achieve the same effect as when the drug was first administered
Consequence of poor pain control
An ineffective dose should be increased by 25% to 50%
Consult with primary provider<br>
slide25. Physical Dependence Person experiences physical discomfort, known as withdrawal symptoms, when a drug taken routinely for some time is abruptly discontinued.
To avoid withdrawal symptoms, drugs should be discontinued gradually.
Lowered over 1 week or longer
Adjuvant Drug Therapy<br>
slide26. Question #3 A client taking opioids for cancer pain begins to require more medication to provide the same amount of analgesia. This is known as:
A) Physical dependence
B) Drug tolerance
C) Drug addiction
D) Obsessive-compulsive<br>
slide27. Answer to Question #3 C) Drug tolerance
Rationale: Drug tolerance is the need for an increased opioid dose to maintain the same effect.<br>
slide28. Nondrug Interventions Alternative nondrug methods
Transcutaneous electrical nerve stimulation (TENS) and percutaneous electrical nerve stimulation (PENS)
Acupuncture and acupressure
Heat or cold application
Spinal surgery: spinal cord stimulation, rhizotomy, cordotomy
Other
Distraction, relaxation, imagery<br>
slide29. Nursing Management Performs a comprehensive assessment of each client’s pain on admission
Determines the onset, quality, intensity, location, and duration of pain
Administration of analgesics every 3 hours rather than PRN often provides a uniform level of pain relief.
Collaborates with client: informs of pain relief options
Assess complications related to pain or prolonged pain medication; risk for falls, knowledge deficit, constipation
See Box 11-2<br>
slide30. Nursing Care Plan: Acute Pain Nursing diagnosis: Acute Pain
Expected outcome: Client will rate pain intensity at tolerable level of “5” within 30 minutes of pain management technique.
Interventions
Assess client’s pain and its characteristics at least every 2 hours while awake.
Modify or eliminate factors that contribute to pain.
Administer prescribed analgesics or alternative pain management techniques promptly.<br>
slide2. Pain Pain is a privately experienced, unpleasant sensation usually associated with disease or injury.
Emotional component—suffering
Classification
Source: nociceptive or neuropathic
Onset, intensity, and duration: acute or chronic<br>
slide3. Nociceptive Pain Noxious stimuli that are transmitted from the point of cellular injury over peripheral sensory nerves to pathways between the spinal cord and thalamus and from the thalamus to the cerebral cortex of the brain
Nociceptive pain types
Somatic pain
Visceral pain<br>
slide4. Nociceptive: Somatic Pain Caused by mechanical, chemical, thermal, or electrical injuries or disorders affecting bones, joints, muscles, skin, or other structures composed of connective tissue
Superficial somatic pain/cutaneous pain: from insect bite or paper cut; perceived as sharp or burning discomfort
Deeper somatic pain: caused by trauma; produces sensations that are sharp, throbbing, and intense
Dull, aching, diffuse discomfort with long-term disorders
Example: arthritis<br>
slide5. Nociceptive: Visceral Pain Arises from internal organs such as the heart, kidneys, and intestine that are diseased or injured
Causes: ischemia, compression of an organ, intestinal distention, contraction
Is usually diffuse, poorly localized, accompanied by ANS symptoms such as nausea, vomiting, pallor, hypotension, and sweating
Referred pain: discomfort in a general area of the body but not in the exact site where an organ is located<br>
slide6. Neuropathic Pain Pain processed abnormally by the nervous system
Results from damage to either the pain pathways in peripheral nerves or pain-processing centers in the brain
Examples: phantom limb pain, spinal cord injuries, strokes, diabetes, and herpes zoster (shingles)
Cancer pain: nociceptive or neuropathic
Nerve damage: radiation or drugs<br>
slide7. Acute Pain Acute pain: less than 6 months
Associated with tissue trauma: eases with healing
Manifestations: elevated blood pressure and heart and respiratory rates, diaphoresis, and dilated pupils
See Table 11-1
Chronic pain: lasts longer than 6 months
Affects quality of life; others begin to show negative reactions to sufferer
Breakthrough pain
Manifestations: similar to the symptoms of depression, including hopelessness, weight loss, fatigue, or physical immobility<br>
slide8. Question #1 Chronic pain is described as an unpleasant sensory and emotional experience associated with:
A) Actual tissue damage
B) Actual or potential tissue damage
C) Only observable pain behaviors
D) Physiologic signs and symptoms that the pain exists<br>
slide9. Answer to Question #1 B) Actual or potential tissue damage
Rationale: Chronic pain is associated with actual or potential tissue damage. Chronic pain is associated with many pain behaviors that people do not normally associate with pain. There is no change in vital signs with chronic pain.<br>
slide10. Pain Transmission Four phases
Transduction
Transmission
Perception
Modulation<br>
slide11. Transduction Conversion of chemical information in the cellular environment to electrical impulses that move toward the spinal cord
Initiated by cellular disruption
Nociceptors: specialized pain receptors located in the free nerve endings of peripheral sensory nerves
A-delta fibers: can carry pain impulses fast or slow; get sharp, acute initial pain
C-fibers: throbbing, aching, or burning after initial pain<br>
slide12. Transmission Peripheral nerve fibers form synapses with neurons in the spinal cord.
Impulses move from the spinal cord to the brain.<br>
slide13. Perception Brain experiences pain at a conscious level; locates pain, its intensity, and what it means; and gives emotional response.
Pain threshold: point at which the pain-transmitting neurochemicals reach the brain, causing conscious awareness
Hyperalgesia
Pain tolerance: amount of pain a person endures once the threshold has been reached
Variables: age, gender, fatigue<br>
slide14. Modulation Brain transmits a response down the spinal nerves to the point where the pain transmission originated to alter the pain experience.
Endogenous opioids—neurochemical
Painful sensation is reduced.
Pain Theories
Specificity Theory
Pattern Theory
Gate Control Theory
Neuromatrix Theory
Endogenous Opioid Theory<br>
slide15. Pain Assessment #1 Client’s description of its onset, quality, intensity, location, and duration
What makes the pain better or worse?
Nonverbal behaviors: clenched jaw, frowning, crying, rocking, or fidgeting
Allodynia—exaggerated pain response
Assessment biases: client’s pain misunderstood<br>
slide16. Pain Assessment #2 Pain assessment tools: quantify pain intensity
Types
Numeric scale
Word scale
Linear scale
FACES scale<br>
slide17. Assessment Standards Accredited health care facilities
Right to assessment and pain management
Assessment is appropriate for age, developmental level, condition, and culture.
Pain is reassessed regularly.
Health care workers are educated on pain management.
Client’s choices of pain management are respected.<br>
slide18. Pain Management #1 Drug and nondrug interventions
Techniques for pain management
Blocking brain perception
Interrupting pain-transmitting chemicals
Combining analgesics
Substituting sensory stimuli
Altering pain transmission<br>
slide19. Question #2 To evaluate adequately the effectiveness of pain control regimens, the nurse should:
A) Be casual and informal
B) Not bother if the client is quiet
C) Use a pain assessment tool
D) Rely on the feedback from the client’s family member<br>
slide20. Answer to Question #2 C) Use a pain assessment tool
Rationale: An effective pain treatment requires a thorough pain assessment.<br>
slide21. Pain Management #2 Techniques used to prevent, reduce, or relieve pain
Drug therapy See Table 11-1
Opioids—narcotic: interfere with pain perception centrally (at the brain); used for mild to moderate pain
Oxycodone, morphine sulfate
Adjuvant Drug Therapy
medications that are ordinarily administered for reasons other than treating pain
Nonopioids—non-narcotic: alter neurotransmission at the peripheral level (sight of injury); for mild pain
Ketorolac tromethamine (Toradol), Tylenol<br>
slide22. Methods of Pain Medication Administration Routes
Analgesic drugs: oral, rectal, transdermal, or parenteral
Equianalgesic dose
Patient-controlled analgesia (PCA)
Intraspinal analgesia
Palliative sedation: relieving intractable pain experienced by dying client
See Table 11-4<br>
slide23. Addiction Repetitive pattern of drug seeking and drug use to satisfy a craving for a drug’s mind-altering or mood-altering effects
Fewer than 1% of clients who need drugs for pain relief, even for more than 6 months become addicted.
Fears
Refuse or self-limit prescribed drug therapy
Nurses administer subtherapeutic doses.<br>
slide24. Tolerance Condition in which a client needs increasingly larger doses of a drug to achieve the same effect as when the drug was first administered
Consequence of poor pain control
An ineffective dose should be increased by 25% to 50%
Consult with primary provider<br>
slide25. Physical Dependence Person experiences physical discomfort, known as withdrawal symptoms, when a drug taken routinely for some time is abruptly discontinued.
To avoid withdrawal symptoms, drugs should be discontinued gradually.
Lowered over 1 week or longer
Adjuvant Drug Therapy<br>
slide26. Question #3 A client taking opioids for cancer pain begins to require more medication to provide the same amount of analgesia. This is known as:
A) Physical dependence
B) Drug tolerance
C) Drug addiction
D) Obsessive-compulsive<br>
slide27. Answer to Question #3 C) Drug tolerance
Rationale: Drug tolerance is the need for an increased opioid dose to maintain the same effect.<br>
slide28. Nondrug Interventions Alternative nondrug methods
Transcutaneous electrical nerve stimulation (TENS) and percutaneous electrical nerve stimulation (PENS)
Acupuncture and acupressure
Heat or cold application
Spinal surgery: spinal cord stimulation, rhizotomy, cordotomy
Other
Distraction, relaxation, imagery<br>
slide29. Nursing Management Performs a comprehensive assessment of each client’s pain on admission
Determines the onset, quality, intensity, location, and duration of pain
Administration of analgesics every 3 hours rather than PRN often provides a uniform level of pain relief.
Collaborates with client: informs of pain relief options
Assess complications related to pain or prolonged pain medication; risk for falls, knowledge deficit, constipation
See Box 11-2<br>
slide30. Nursing Care Plan: Acute Pain Nursing diagnosis: Acute Pain
Expected outcome: Client will rate pain intensity at tolerable level of “5” within 30 minutes of pain management technique.
Interventions
Assess client’s pain and its characteristics at least every 2 hours while awake.
Modify or eliminate factors that contribute to pain.
Administer prescribed analgesics or alternative pain management techniques promptly.<br>