
Transplantation surgery Dr. Ammar Fadil 1 History



















Description: Transplantation surgery Dr. Ammar Fadil 1 History Since early times the idea of tissue and organ transplantation has captured the imagination of successive generations Early attempts at organ transplantation were ended with failure due to
Related Topics
Download Presentation
"Transplantation surgery Dr. Ammar Fadil 1 History" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Transplantation surgery Dr. Ammar Fadil 1<br>
slide2. History Since early times the idea of tissue and organ transplantation has captured the imagination of successive generations
Early attempts at organ transplantation were ended with failure due to lack of suppressive immune therapy that resulted in destruction of transplanted organ.
1954
Murray in Boston first renal transplant between identical twin. 2<br>
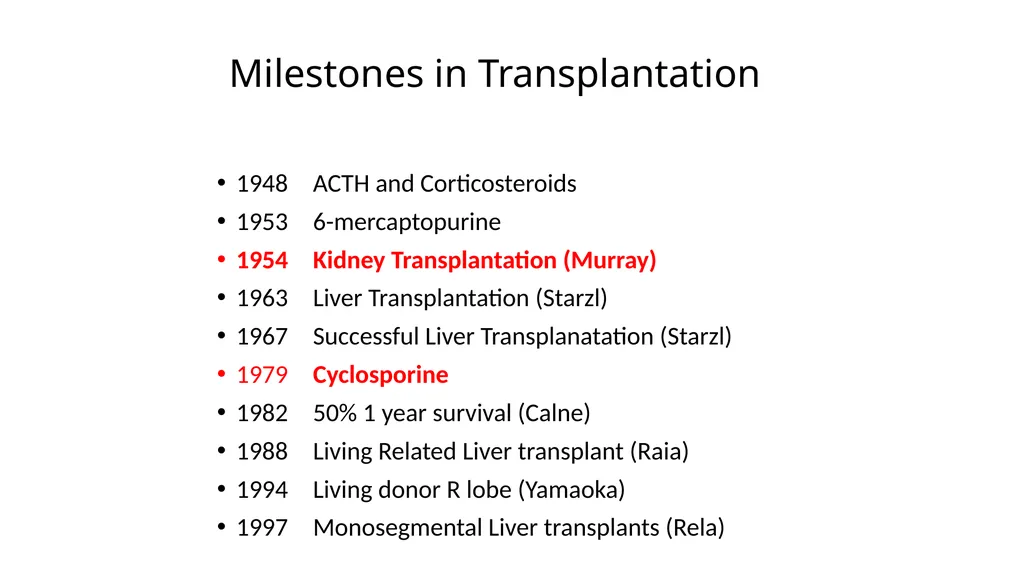
slide3. Milestones in Transplantation 1948 ACTH and Corticosteroids
1953 6-mercaptopurine
1954 Kidney Transplantation (Murray)
1963 Liver Transplantation (Starzl)
1967 Successful Liver Transplanatation (Starzl)
1979 Cyclosporine
1982 50% 1 year survival (Calne)
1988 Living Related Liver transplant (Raia)
1994 Living donor R lobe (Yamaoka)
1997 Monosegmental Liver transplants (Rela)<br>
slide4. Cyclosporine introduction of ciclosporin was a major advance and ciclosporin (usually given together with azathioprine and steroids)
not only improved the results of renal transplantation but also
allowed transplantation of the heart & liver. 4<br>
slide5. Classification of Graft Autograft
transplant from one part of body to another e.g skin graft.
■ Allograft
an organ or tissue transplanted from one individual to another
■ Xenograft
a graft performed between different species
■ Orthotopic graft
a graft placed in its normal position 5<br>
slide6. Transplant antigens Allografts (transplant) trigger a graft rejection response because of allelic differences at genes that give rise to histocompatibility antigens (transplant antigens)
1. ABO blood group antigens &
2. HLA: human leucocyte antigen, the main trigger of graft rejection 6<br>
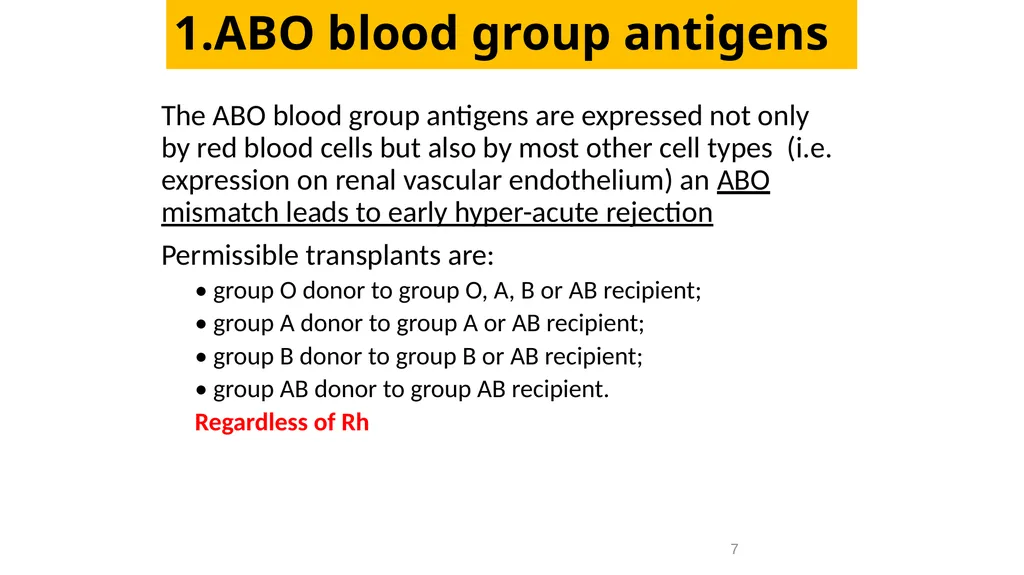
slide7. 1.ABO blood group antigens The ABO blood group antigens are expressed not only by red blood cells but also by most other cell types (i.e. expression on renal vascular endothelium) an ABO mismatch leads to early hyper-acute rejection
Permissible transplants are:
• group O donor to group O, A, B or AB recipient;
• group A donor to group A or AB recipient;
• group B donor to group B or AB recipient;
• group AB donor to group AB recipient.
Regardless of Rh 7<br>
slide8. 2.THE MAJOR HISTOCOMPATIBILITY COMPLEX (MHC)- HLA Each individual inherits HLA-A, -B (class I) & -DR (class II) antigen from each parent; so six HLA antigens constitute an individual tissue type
The HLA molecules are polymorphic (over 150 defined), HLA antigens not shared between two individual will generate an Immune response. 8<br>
slide9. HLA matching (cross match) Must be performed before each kidney transplantation. Donor’s cells (lymphocyte) are mixed with recipient serum
The test is considered –ve and donor suitable 9 HLA test -Ve<br>
slide10. In summary HLA HLA system is a group of antigens present on the surface of all nucleated cells in the body.
Are the most common cause of graft rejection
■ Are highly polymorphic (amino acid sequence
differs widely between individuals)
■ The more similar the HLA system of recipient & donor the less the incidence of rejection episodes require less intensive immunosuppression 10<br>
slide11. 11 In clinical practice, the impact of HLA on graft survival is small in the first years, but plays an important role after 5 years.
other factors affect survival of graft:
donor organ quality (age, function, size, etc.)
recipient age &
comorbidities.<br>
slide12. Renal transplantation Treatment of CRF (chronic renal failure) by surgical implantation of a kidney that is obtained from healthy kidney donor or brain stem cadaver death.
The majority of renal transplant recipients are on dialysis (peritoneal or hemodialysis) at the time of transplantation 12<br>
slide13. Chronic renal failure is irreversible loss of kidney function due to progressive damage of kidney tissue by disease involving the two kidneys
ESRD: GFR < 15ml/min
Diabetes mellitus
Glomerulo-nephritis/focal sclerosis
Hypertension
Cystic kidney disease (APCKD) &
Unknown causes 13% 13<br>
slide14. Patient with ESRD requiring renal replacement therapy 1.Dialysis
Peritoneal dialysis
Haemodialysis
2.Renal transplant
cost effective form of tx for ESRD & allows return to normal lifestyle 14<br>
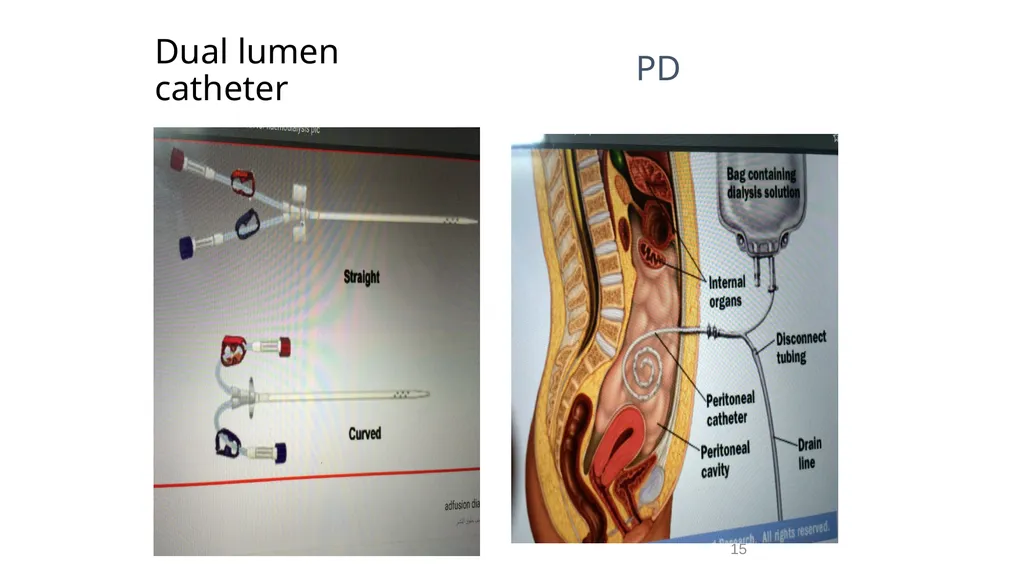
slide15. Dual lumen catheter 15 PD<br>
slide16. CONTRAINDICATIONS FOR TRANSPLANT (in recipient) Patient refusal
Psychosis
Systemic disease e.g.
severe respiratory disease
Severe cardiovascular disease
Malignancy
(skin tumor & CIS of cervix ) are exceptions
Active infection
AIDS
Chronic active hepatitis B 16<br>
slide17. Contraindication for donation Psychosis
Age <18 & >60
Renal disease
Associated medical disease H.F
Malignancy 17<br>
slide18. Types of kidney donor Living donors
Related donor one of the relatives of the recipient.
Unrelated donors
Cadaveric donors
brain –dead donors (beating heart) are considered dead. Donor’s heart continues to pump and maintain the circulation.
Brain death occurs when severe brain injury causes irreversible loss of the capacity for consciousness combined with the irreversible loss of the capacity for breathing 18<br>
slide19. Clinical testing for brainstem death Absence of cranial nerve reflexes
■ Pupillary reflex
■ Corneal reflex
■ Pharyngeal (gag) and tracheal (cough) reflex
■ Oculovestibular (caloric) reflex
Absence of motor response
Absence of spontaneous respiration 19<br>
slide20. adult kidney can be stored for about 31 h
a liver for 12-18 h
a heart for only 4-6 h. 20<br>
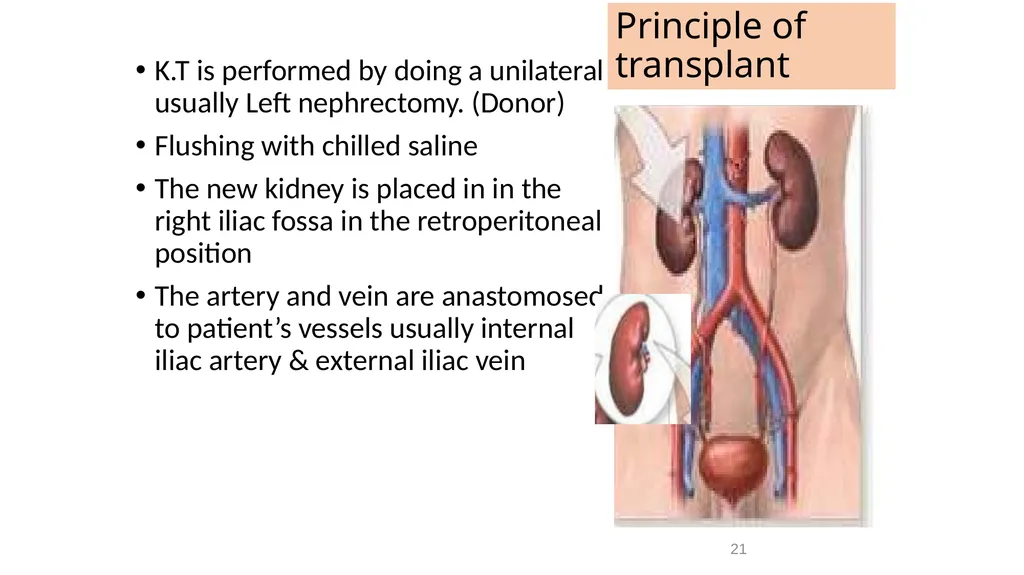
slide21. Principle of transplant K.T is performed by doing a unilateral usually Left nephrectomy. (Donor)
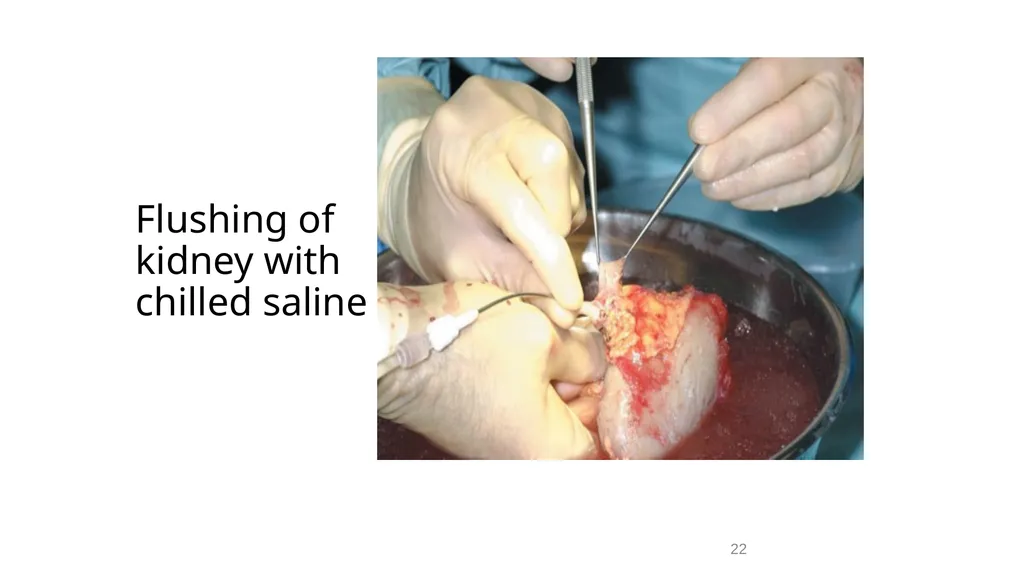
Flushing with chilled saline
The new kidney is placed in in the right iliac fossa in the retroperitoneal position
The artery and vein are anastomosed to patient’s vessels usually internal iliac artery & external iliac vein 21<br>
slide22. Flushing of kidney with chilled saline 22<br>
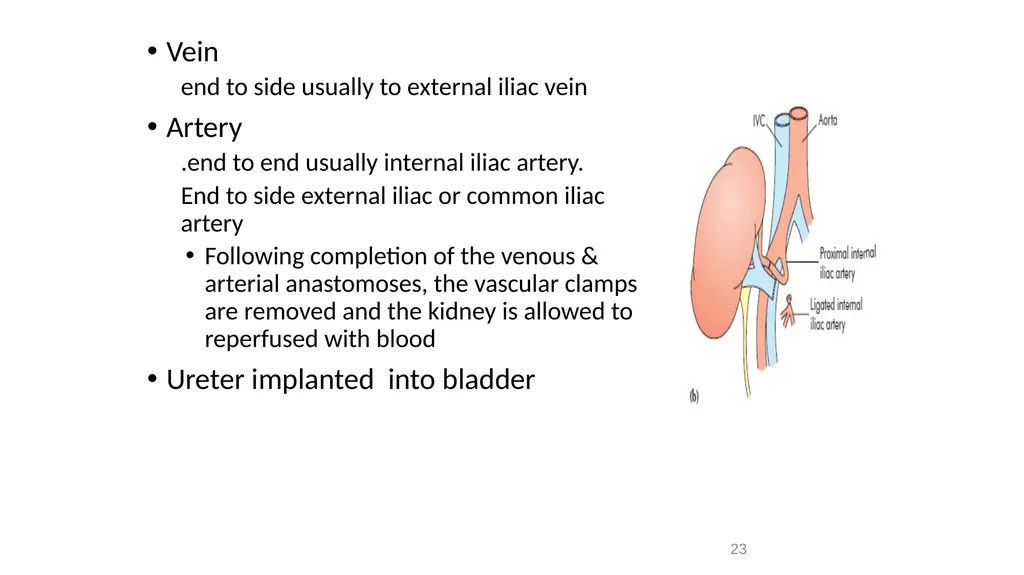
slide23. Vein
end to side usually to external iliac vein
Artery
.end to end usually internal iliac artery.
End to side external iliac or common iliac artery
Following completion of the venous & arterial anastomoses, the vascular clamps are removed and the kidney is allowed to reperfused with blood
Ureter implanted into bladder 23<br>
slide24. The native kidneys are usually left in place
indications to be removed
Hugely enlarged kidneys e.g. adult polycystic kidneys
Uncontrolled hypertension
Infected kidney. 24<br>
slide25. Immunosuppression Is used after transplantation in order to modify the recipient immune system so that rejection is prevented.
Duration: continues for life.
Mode of action:
Each drug has different mechanism by which it can depress leukocyte which are the responsible for the immune response. 25<br>
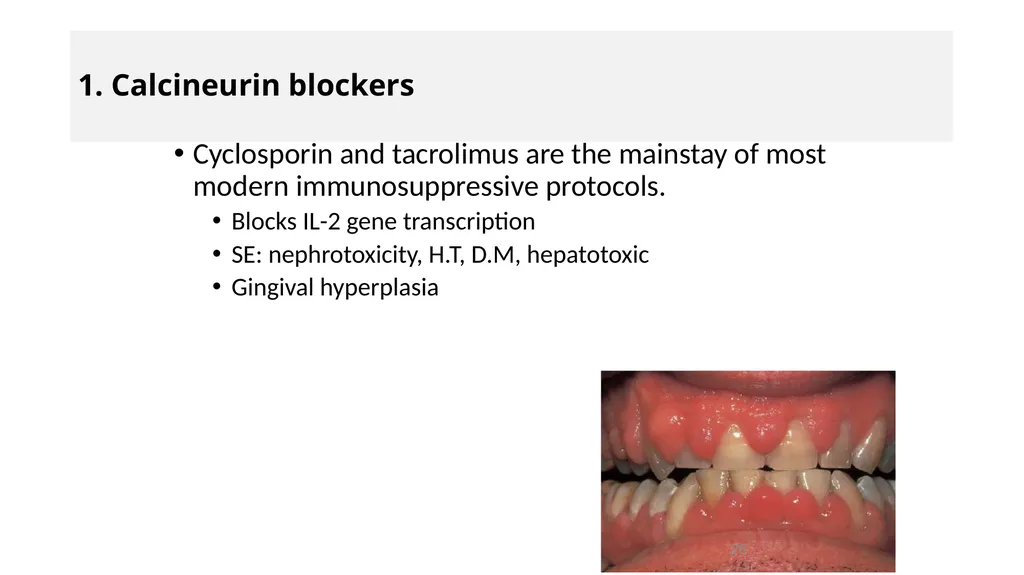
slide26. 1. Calcineurin blockers Cyclosporin and tacrolimus are the mainstay of most modern immunosuppressive protocols.
Blocks IL-2 gene transcription
SE: nephrotoxicity, H.T, D.M, hepatotoxic
Gingival hyperplasia 26<br>
slide27. 2.Anti-proliferative agents The antiproliferative agents are azathioprine and mycophenolate mofetil (MMF)
Action: Prevents lymphocyte proliferation.
SE: bone marrow suppression & gastrointestinal symptoms. 27<br>
slide28. 3.Steroids Corticosteroids are wide spread anti-inflammatory agents and have wide-ranging effects on the immune response
SE: H.T, D.M, bone disease, GIT bleeding, cataract 28<br>
slide29. 4.Antibody therapies Monoclonal antibodies directed against the IL-2 receptor on T lymphocytes (CD25) are commonly given at the time of transplantation to temporarily augment the effects of calcineurin blockade during the early post-transplant period 29<br>
slide30. Regimens Steroids are the corner stone drug used.
Triple regimen
Steroid ,mycophenolate mofetile MMF,& cyclosporine is the commonest regimen.
The need for immunosuppression is highest in the first 3 months. 30<br>
slide31. Complications of Immunosuppressive Transplant recipients are at high risk of
1. opportunistic infection
Viral infection
may result from reactivation of latent virus or from primary infection. CMV is major problem
the clinical picture depends on the organ system most affected. It may present as:
• pneumonia;
• gastrointestinal disease;
• hepatitis;
• encephalitis. 31<br>
slide32. Bacterial and fungal infections are also common. Risk of infection is highest during first 6 months after transplantation
Protozoal
Pneumocystis carinii is the most important protozoal infection seen after transplantation.
Prophylaxis with co-trimoxazole is effective and is continued for up to 6 months after transplantation. 32<br>
slide33. 2. Malignancy
■ post-transplant lymphoproliferative disorder
■ squamous cancer of the skin
Most cases of Post transplant lymphoproliferative disease (PTLD) are associated with an Epstein-Barr virus (EBV) infection. Most cases of PTLD are observed in the first year following transplant.
Successful treatment of PTLD involves the reduction of immunosuppressive medication 33<br>
slide34. Types of Rejection 1.HYPER-ACUTE REJECTION
This is due to the presence in the recipient of pre-formed antibodies against HLA class I antigens expressed by the donor. These arise from a previous blood transfusion, a failed transplant or pregnancy.
This type of rejection also occurs if an ABO blood group incompatible organ graft is performed.
This may occur within the first day of transplant. It often results in loss of allograft within the first few days after transplant. 34<br>
slide35. 35 Kidney transplants are particularly vulnerable to hyper acute graft rejection, whereas heart and liver transplants are relatively resistant.
Treatment : graft nephrectomy
Prevention :
can be avoided by ensuring ABO blood group compatibility and by performing a cross-match test on recipient serum to ensure that there are no antibodies directed against HLA antigens<br>
slide36. 2. ACUTE REJECTION This may occur any time after transplant, most commonly occurs during first 6 months
It is mediated predominantly by T lymphocytes
it is usually a sudden event.
• it is usually reversible with little or no damage to allograft.
May occur if non compliant with immunosuppressive medications 36<br>
slide37. 2. ACUTE REJECTION All types of organ allograft are susceptible to acute rejection and, although relatively common (occurring in around 20–30% of grafts),
most episodes of acute rejection can be reversed by additional immunosuppressive therapy.
Treatment: high dose steroid 37<br>
slide38. Signs and Symptoms of acute Rejection • Pain, swelling or tenderness over graft site
High temperature
• Decreased urine output
• High blood pressure
• puffiness of face
• Increase in creatinine level 38<br>
slide39. 3. CHRONIC REJECTION •This usually occurs after the first 6 months gradual decline in renal function. it is the major cause of allograft failure. takes months or years to develop and manifested by
proteinuria
hypertension,
rise in serum creatinine level.
DX: diagnosis is by renal biopsy
R: ACE inhibitor .
Finally, the patient will require another transplant
The most important risk factors for chronic rejection after kidney transplantation is recurrent episodes of acute rejection 39<br>
slide40. Better quality of life.
Correction of manifestations of CRF that are not corrected by dialysis.
Less cost than dialysis. Complication of immunosuppressions
The possibility of graft loss.
Need of kidney donor advantage disadvantage 40<br>
slide41. Liver transplantation The indications
• cirrhosis;
• acute fulminant liver failure;
• metabolic liver disease;
• primary hepatic malignancy. 41<br>
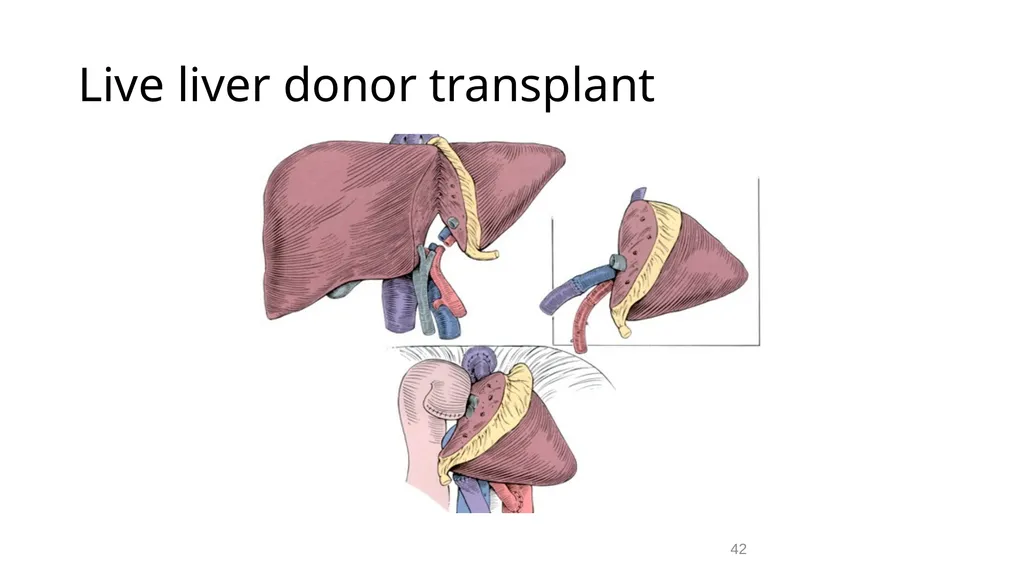
slide42. Live liver donor transplant 42<br>
slide43. Heart transplantation 1967 Dr. Christiaan Barnard the first human heart Tx in Cape town south Africa
Indication in cardiomyopathy, end stage HF (symptoms on mild exertion).
Pt under 65 y
Median sternotomy patient placed on cardiopulmonary bypass and cooled to 28 C 43<br>
slide44. Pancreas transplantation Successful pancreas transplantation restores the normal control of glucose metabolism and obviates the need for insulin therapy in patients with diabetes mellitus
One of the sever complication is leakage of pancreatic exocrine secretions 44<br>
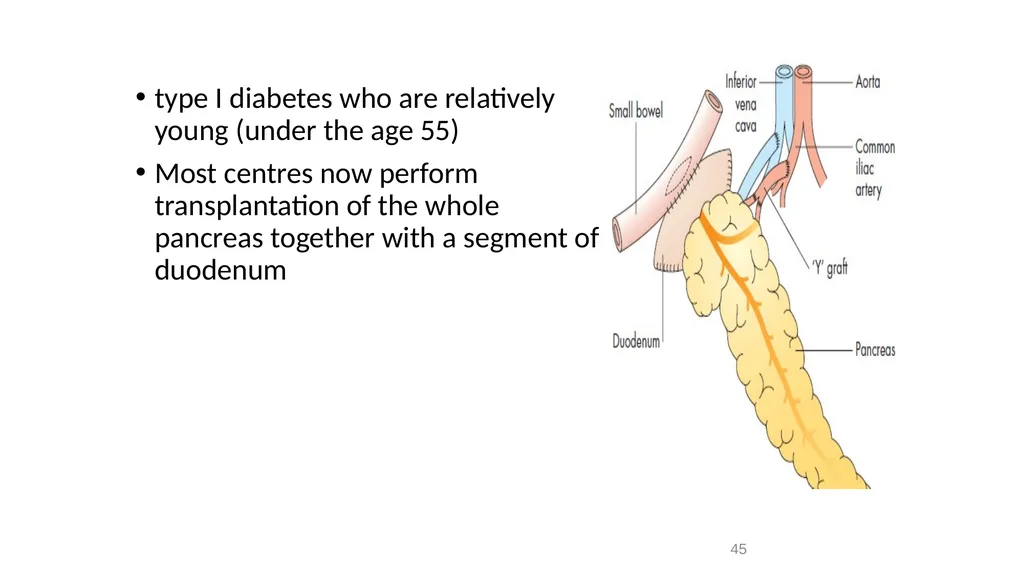
slide45. 45 type I diabetes who are relatively young (under the age 55)
Most centres now perform transplantation of the whole pancreas together with a segment of duodenum<br>
slide46. transplantation of isolated islets of Langerhans Pancreatic islets for transplantation are obtained by mechanically disrupting the pancreas after injection of collagenase into the pancreatic duct.
The islets are then purified from the dispersed tissue and can be delivered
into the recipient liver (the preferred site for transplantation) by injection into the portal vein 46<br>
slide2. History Since early times the idea of tissue and organ transplantation has captured the imagination of successive generations
Early attempts at organ transplantation were ended with failure due to lack of suppressive immune therapy that resulted in destruction of transplanted organ.
1954
Murray in Boston first renal transplant between identical twin. 2<br>
slide3. Milestones in Transplantation 1948 ACTH and Corticosteroids
1953 6-mercaptopurine
1954 Kidney Transplantation (Murray)
1963 Liver Transplantation (Starzl)
1967 Successful Liver Transplanatation (Starzl)
1979 Cyclosporine
1982 50% 1 year survival (Calne)
1988 Living Related Liver transplant (Raia)
1994 Living donor R lobe (Yamaoka)
1997 Monosegmental Liver transplants (Rela)<br>
slide4. Cyclosporine introduction of ciclosporin was a major advance and ciclosporin (usually given together with azathioprine and steroids)
not only improved the results of renal transplantation but also
allowed transplantation of the heart & liver. 4<br>
slide5. Classification of Graft Autograft
transplant from one part of body to another e.g skin graft.
■ Allograft
an organ or tissue transplanted from one individual to another
■ Xenograft
a graft performed between different species
■ Orthotopic graft
a graft placed in its normal position 5<br>
slide6. Transplant antigens Allografts (transplant) trigger a graft rejection response because of allelic differences at genes that give rise to histocompatibility antigens (transplant antigens)
1. ABO blood group antigens &
2. HLA: human leucocyte antigen, the main trigger of graft rejection 6<br>
slide7. 1.ABO blood group antigens The ABO blood group antigens are expressed not only by red blood cells but also by most other cell types (i.e. expression on renal vascular endothelium) an ABO mismatch leads to early hyper-acute rejection
Permissible transplants are:
• group O donor to group O, A, B or AB recipient;
• group A donor to group A or AB recipient;
• group B donor to group B or AB recipient;
• group AB donor to group AB recipient.
Regardless of Rh 7<br>
slide8. 2.THE MAJOR HISTOCOMPATIBILITY COMPLEX (MHC)- HLA Each individual inherits HLA-A, -B (class I) & -DR (class II) antigen from each parent; so six HLA antigens constitute an individual tissue type
The HLA molecules are polymorphic (over 150 defined), HLA antigens not shared between two individual will generate an Immune response. 8<br>
slide9. HLA matching (cross match) Must be performed before each kidney transplantation. Donor’s cells (lymphocyte) are mixed with recipient serum
The test is considered –ve and donor suitable 9 HLA test -Ve<br>
slide10. In summary HLA HLA system is a group of antigens present on the surface of all nucleated cells in the body.
Are the most common cause of graft rejection
■ Are highly polymorphic (amino acid sequence
differs widely between individuals)
■ The more similar the HLA system of recipient & donor the less the incidence of rejection episodes require less intensive immunosuppression 10<br>
slide11. 11 In clinical practice, the impact of HLA on graft survival is small in the first years, but plays an important role after 5 years.
other factors affect survival of graft:
donor organ quality (age, function, size, etc.)
recipient age &
comorbidities.<br>
slide12. Renal transplantation Treatment of CRF (chronic renal failure) by surgical implantation of a kidney that is obtained from healthy kidney donor or brain stem cadaver death.
The majority of renal transplant recipients are on dialysis (peritoneal or hemodialysis) at the time of transplantation 12<br>
slide13. Chronic renal failure is irreversible loss of kidney function due to progressive damage of kidney tissue by disease involving the two kidneys
ESRD: GFR < 15ml/min
Diabetes mellitus
Glomerulo-nephritis/focal sclerosis
Hypertension
Cystic kidney disease (APCKD) &
Unknown causes 13% 13<br>
slide14. Patient with ESRD requiring renal replacement therapy 1.Dialysis
Peritoneal dialysis
Haemodialysis
2.Renal transplant
cost effective form of tx for ESRD & allows return to normal lifestyle 14<br>
slide15. Dual lumen catheter 15 PD<br>
slide16. CONTRAINDICATIONS FOR TRANSPLANT (in recipient) Patient refusal
Psychosis
Systemic disease e.g.
severe respiratory disease
Severe cardiovascular disease
Malignancy
(skin tumor & CIS of cervix ) are exceptions
Active infection
AIDS
Chronic active hepatitis B 16<br>
slide17. Contraindication for donation Psychosis
Age <18 & >60
Renal disease
Associated medical disease H.F
Malignancy 17<br>
slide18. Types of kidney donor Living donors
Related donor one of the relatives of the recipient.
Unrelated donors
Cadaveric donors
brain –dead donors (beating heart) are considered dead. Donor’s heart continues to pump and maintain the circulation.
Brain death occurs when severe brain injury causes irreversible loss of the capacity for consciousness combined with the irreversible loss of the capacity for breathing 18<br>
slide19. Clinical testing for brainstem death Absence of cranial nerve reflexes
■ Pupillary reflex
■ Corneal reflex
■ Pharyngeal (gag) and tracheal (cough) reflex
■ Oculovestibular (caloric) reflex
Absence of motor response
Absence of spontaneous respiration 19<br>
slide20. adult kidney can be stored for about 31 h
a liver for 12-18 h
a heart for only 4-6 h. 20<br>
slide21. Principle of transplant K.T is performed by doing a unilateral usually Left nephrectomy. (Donor)
Flushing with chilled saline
The new kidney is placed in in the right iliac fossa in the retroperitoneal position
The artery and vein are anastomosed to patient’s vessels usually internal iliac artery & external iliac vein 21<br>
slide22. Flushing of kidney with chilled saline 22<br>
slide23. Vein
end to side usually to external iliac vein
Artery
.end to end usually internal iliac artery.
End to side external iliac or common iliac artery
Following completion of the venous & arterial anastomoses, the vascular clamps are removed and the kidney is allowed to reperfused with blood
Ureter implanted into bladder 23<br>
slide24. The native kidneys are usually left in place
indications to be removed
Hugely enlarged kidneys e.g. adult polycystic kidneys
Uncontrolled hypertension
Infected kidney. 24<br>
slide25. Immunosuppression Is used after transplantation in order to modify the recipient immune system so that rejection is prevented.
Duration: continues for life.
Mode of action:
Each drug has different mechanism by which it can depress leukocyte which are the responsible for the immune response. 25<br>
slide26. 1. Calcineurin blockers Cyclosporin and tacrolimus are the mainstay of most modern immunosuppressive protocols.
Blocks IL-2 gene transcription
SE: nephrotoxicity, H.T, D.M, hepatotoxic
Gingival hyperplasia 26<br>
slide27. 2.Anti-proliferative agents The antiproliferative agents are azathioprine and mycophenolate mofetil (MMF)
Action: Prevents lymphocyte proliferation.
SE: bone marrow suppression & gastrointestinal symptoms. 27<br>
slide28. 3.Steroids Corticosteroids are wide spread anti-inflammatory agents and have wide-ranging effects on the immune response
SE: H.T, D.M, bone disease, GIT bleeding, cataract 28<br>
slide29. 4.Antibody therapies Monoclonal antibodies directed against the IL-2 receptor on T lymphocytes (CD25) are commonly given at the time of transplantation to temporarily augment the effects of calcineurin blockade during the early post-transplant period 29<br>
slide30. Regimens Steroids are the corner stone drug used.
Triple regimen
Steroid ,mycophenolate mofetile MMF,& cyclosporine is the commonest regimen.
The need for immunosuppression is highest in the first 3 months. 30<br>
slide31. Complications of Immunosuppressive Transplant recipients are at high risk of
1. opportunistic infection
Viral infection
may result from reactivation of latent virus or from primary infection. CMV is major problem
the clinical picture depends on the organ system most affected. It may present as:
• pneumonia;
• gastrointestinal disease;
• hepatitis;
• encephalitis. 31<br>
slide32. Bacterial and fungal infections are also common. Risk of infection is highest during first 6 months after transplantation
Protozoal
Pneumocystis carinii is the most important protozoal infection seen after transplantation.
Prophylaxis with co-trimoxazole is effective and is continued for up to 6 months after transplantation. 32<br>
slide33. 2. Malignancy
■ post-transplant lymphoproliferative disorder
■ squamous cancer of the skin
Most cases of Post transplant lymphoproliferative disease (PTLD) are associated with an Epstein-Barr virus (EBV) infection. Most cases of PTLD are observed in the first year following transplant.
Successful treatment of PTLD involves the reduction of immunosuppressive medication 33<br>
slide34. Types of Rejection 1.HYPER-ACUTE REJECTION
This is due to the presence in the recipient of pre-formed antibodies against HLA class I antigens expressed by the donor. These arise from a previous blood transfusion, a failed transplant or pregnancy.
This type of rejection also occurs if an ABO blood group incompatible organ graft is performed.
This may occur within the first day of transplant. It often results in loss of allograft within the first few days after transplant. 34<br>
slide35. 35 Kidney transplants are particularly vulnerable to hyper acute graft rejection, whereas heart and liver transplants are relatively resistant.
Treatment : graft nephrectomy
Prevention :
can be avoided by ensuring ABO blood group compatibility and by performing a cross-match test on recipient serum to ensure that there are no antibodies directed against HLA antigens<br>
slide36. 2. ACUTE REJECTION This may occur any time after transplant, most commonly occurs during first 6 months
It is mediated predominantly by T lymphocytes
it is usually a sudden event.
• it is usually reversible with little or no damage to allograft.
May occur if non compliant with immunosuppressive medications 36<br>
slide37. 2. ACUTE REJECTION All types of organ allograft are susceptible to acute rejection and, although relatively common (occurring in around 20–30% of grafts),
most episodes of acute rejection can be reversed by additional immunosuppressive therapy.
Treatment: high dose steroid 37<br>
slide38. Signs and Symptoms of acute Rejection • Pain, swelling or tenderness over graft site
High temperature
• Decreased urine output
• High blood pressure
• puffiness of face
• Increase in creatinine level 38<br>
slide39. 3. CHRONIC REJECTION •This usually occurs after the first 6 months gradual decline in renal function. it is the major cause of allograft failure. takes months or years to develop and manifested by
proteinuria
hypertension,
rise in serum creatinine level.
DX: diagnosis is by renal biopsy
R: ACE inhibitor .
Finally, the patient will require another transplant
The most important risk factors for chronic rejection after kidney transplantation is recurrent episodes of acute rejection 39<br>
slide40. Better quality of life.
Correction of manifestations of CRF that are not corrected by dialysis.
Less cost than dialysis. Complication of immunosuppressions
The possibility of graft loss.
Need of kidney donor advantage disadvantage 40<br>
slide41. Liver transplantation The indications
• cirrhosis;
• acute fulminant liver failure;
• metabolic liver disease;
• primary hepatic malignancy. 41<br>
slide42. Live liver donor transplant 42<br>
slide43. Heart transplantation 1967 Dr. Christiaan Barnard the first human heart Tx in Cape town south Africa
Indication in cardiomyopathy, end stage HF (symptoms on mild exertion).
Pt under 65 y
Median sternotomy patient placed on cardiopulmonary bypass and cooled to 28 C 43<br>
slide44. Pancreas transplantation Successful pancreas transplantation restores the normal control of glucose metabolism and obviates the need for insulin therapy in patients with diabetes mellitus
One of the sever complication is leakage of pancreatic exocrine secretions 44<br>
slide45. 45 type I diabetes who are relatively young (under the age 55)
Most centres now perform transplantation of the whole pancreas together with a segment of duodenum<br>
slide46. transplantation of isolated islets of Langerhans Pancreatic islets for transplantation are obtained by mechanically disrupting the pancreas after injection of collagenase into the pancreatic duct.
The islets are then purified from the dispersed tissue and can be delivered
into the recipient liver (the preferred site for transplantation) by injection into the portal vein 46<br>