
Varicose veins Miss Julie Reid Consultant Vascular













Description: Varicose veins Miss Julie Reid Consultant Vascular Surgeon Objectives Know about the anatomy, epidemiology and pathophysiology of varicose veins Know how to assess a patients with varicose veins Know how to investigate a patient with
Related Topics
Download Presentation
"Varicose veins Miss Julie Reid Consultant Vascular" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Varicose veins Miss Julie Reid
Consultant Vascular Surgeon<br>
slide2. Objectives Know about the anatomy, epidemiology and pathophysiology of varicose veins
Know how to assess a patients with varicose veins
Know how to investigate a patient with varicose veins
Know about the management and outcomes of treatment for varicose veins<br>
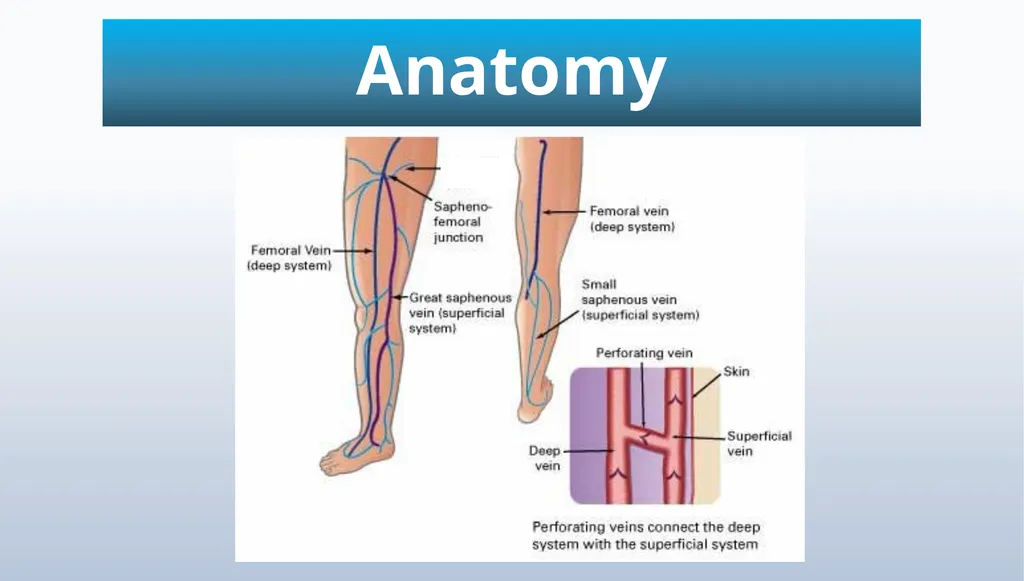
slide3. Anatomy<br>
slide4. Epidemiology Venous disease – 80%
35% trunk varices
Women > men, 2:1
Prevalence increases with age
Positive family history
Obesity
Occupation<br>
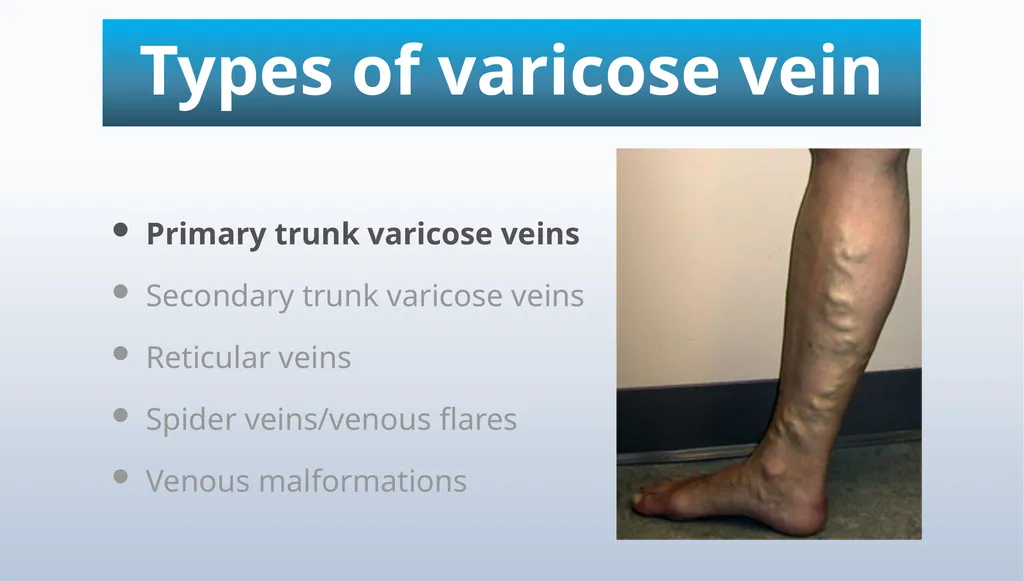
slide5. Types of varicose vein Primary trunk varicose veins
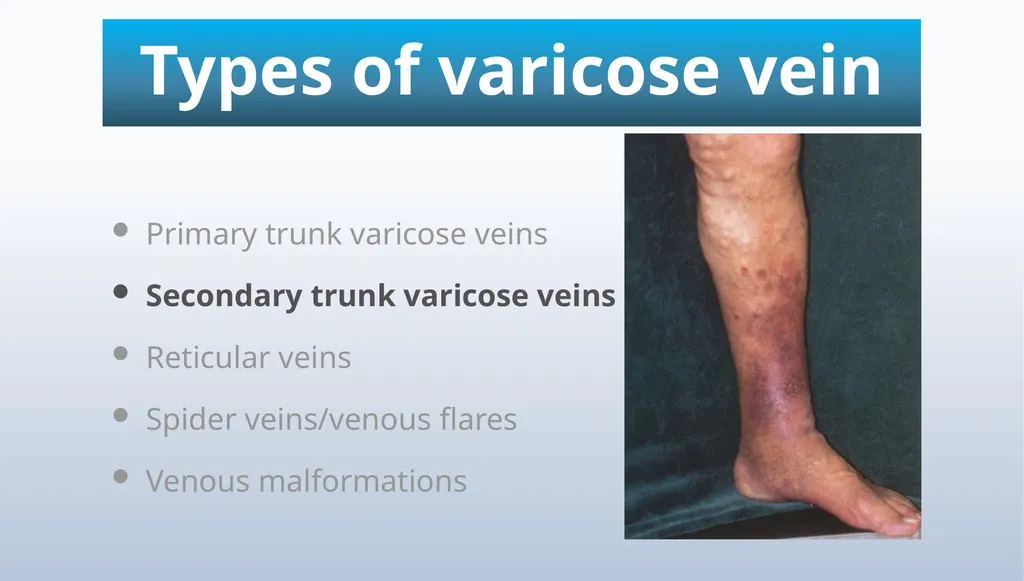
Secondary trunk varicose veins
Reticular veins
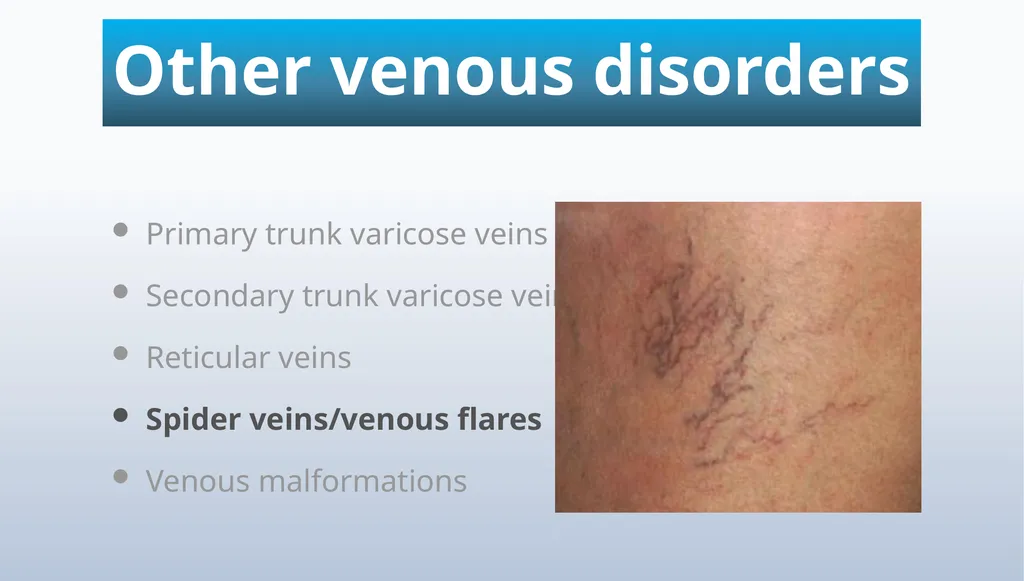
Spider veins/venous flares
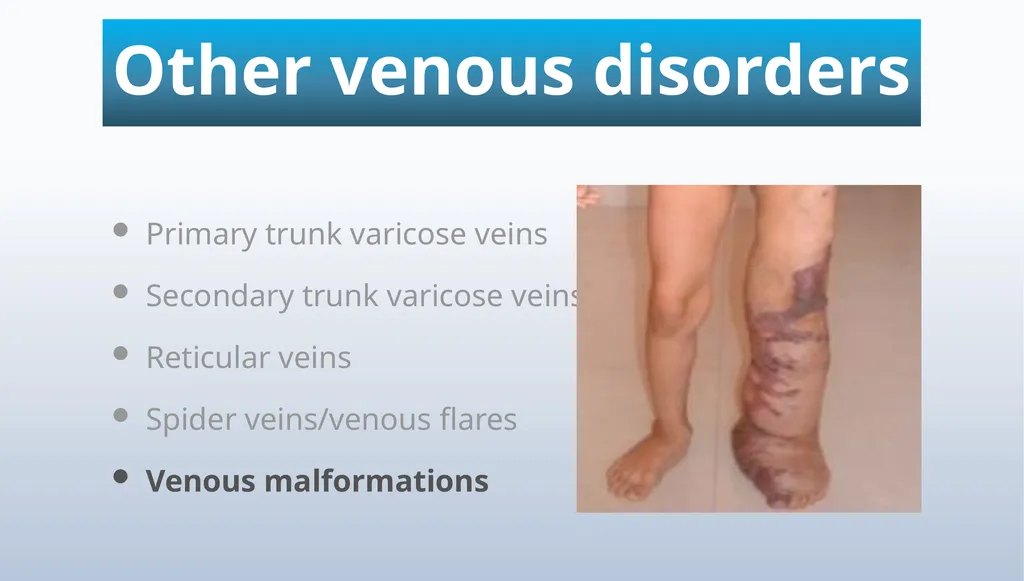
Venous malformations<br>
slide6. Types of varicose vein Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide7. Other venous disorders Primary trunk varicose veins
Secondary trunk varicose veins
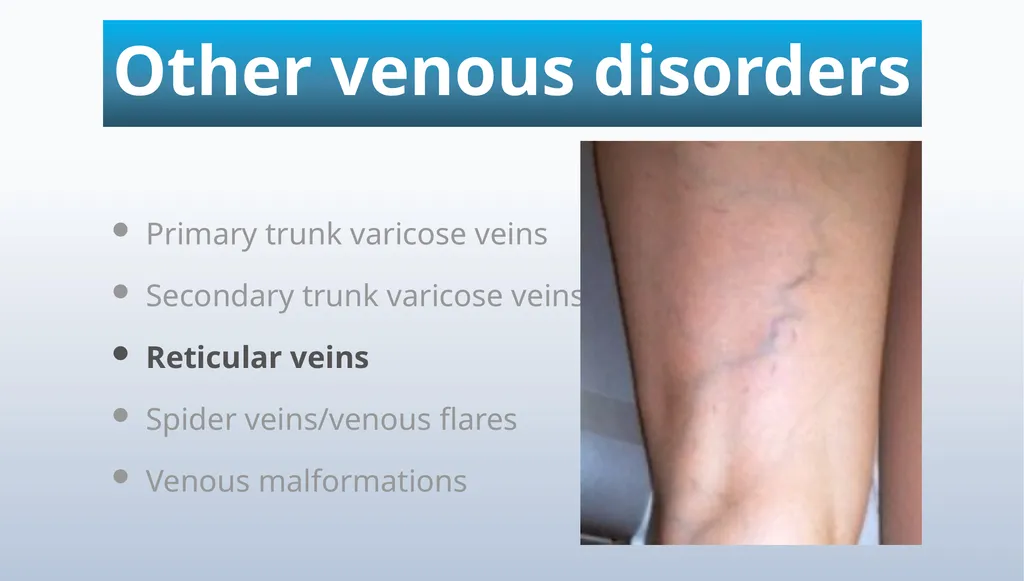
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide8. Other venous disorders Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide9. Other venous disorders Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
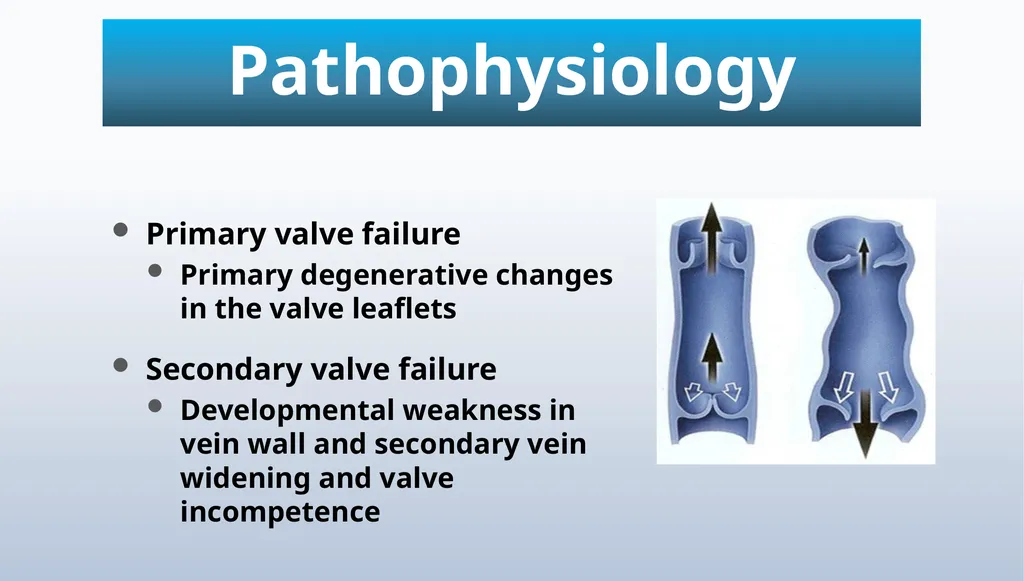
slide10. Pathophysiology Primary valve failure
Primary degenerative changes in the valve leaflets
Secondary valve failure
Developmental weakness in vein wall and secondary vein widening and valve incompetence<br>
slide11. Presentation Uncomplicated veins Cosmesis
Symptoms
For reassurance<br>
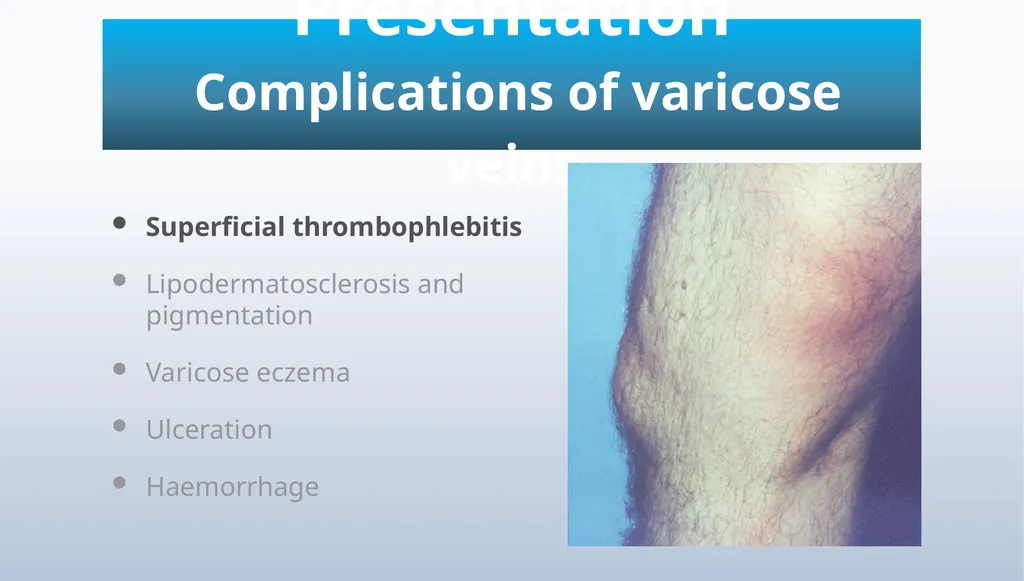
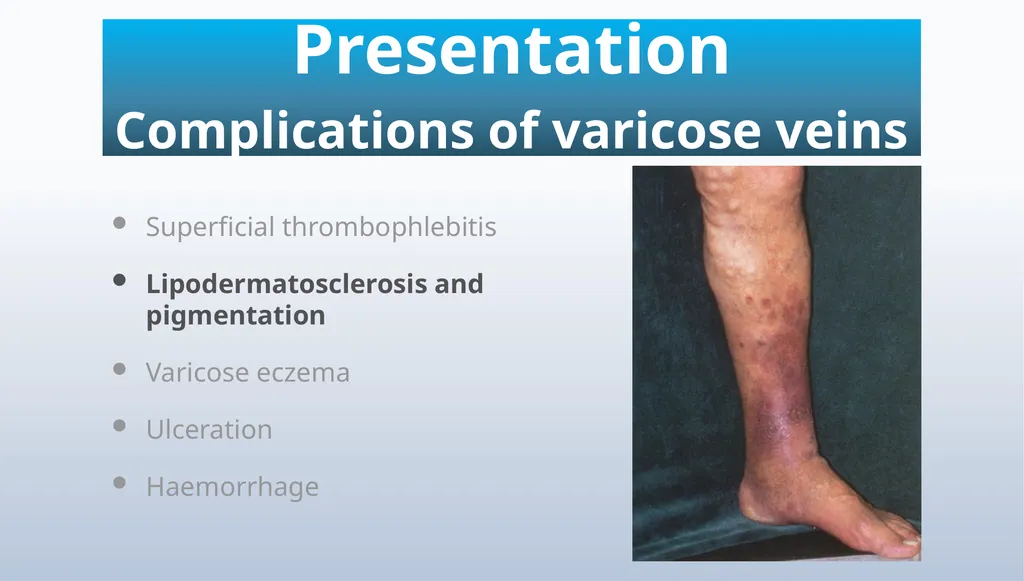
slide12. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
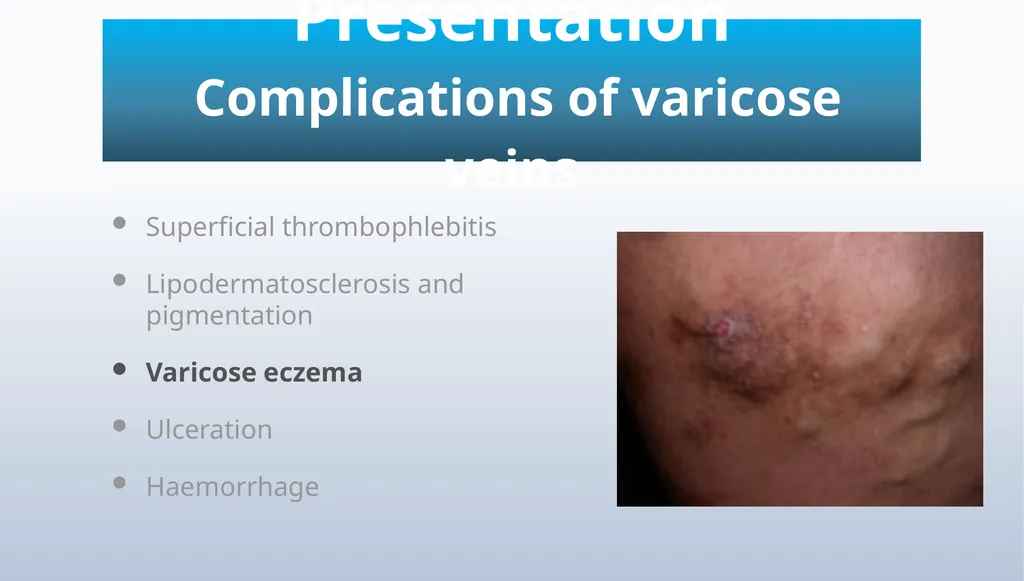
Varicose eczema
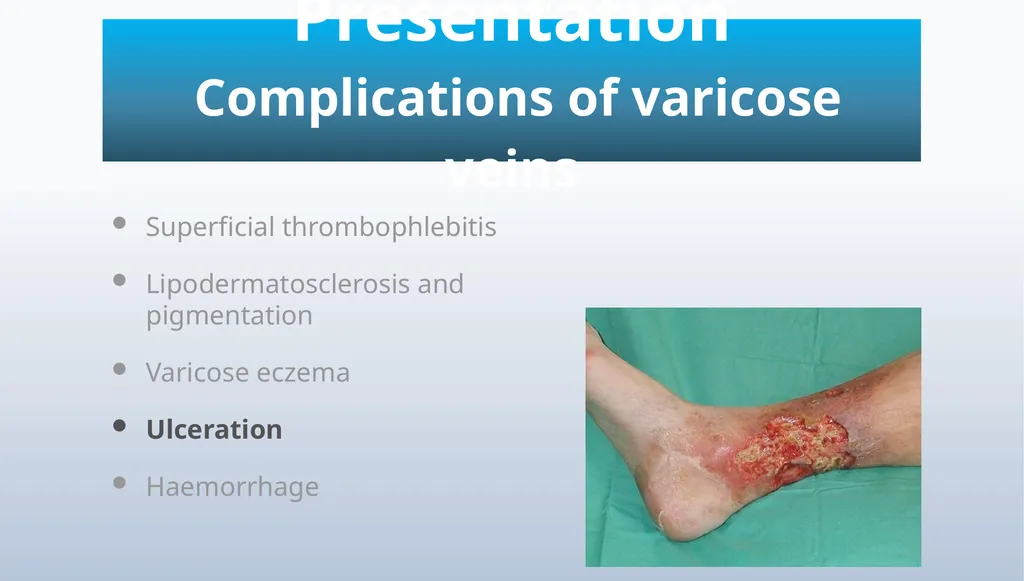
Ulceration
Haemorrhage<br>
slide13. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide14. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide15. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide16. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide17. Clinical Assessment History Are the symptoms due to venous disease
Is the presentation complicated or uncomplicated
Is there any other significant pathology such as previous DVT or arterial disease
Any other health problems
Previous varicose vein surgery?<br>
slide18. Clinical Assessment General examination Examination standing and adequately exposed
(leg and lower abdomen)
Inspection
Distribution of varicose veins (GSV/SSV)
Signs of chronic venous insufficiency
Scars<br>
slide19. Clinical Assessment Special tests Trendelenberg’s test
Perthes Test<br>
slide20. Clinical Assessment Special tests Trendelenberg’s test
Perthes Test<br>
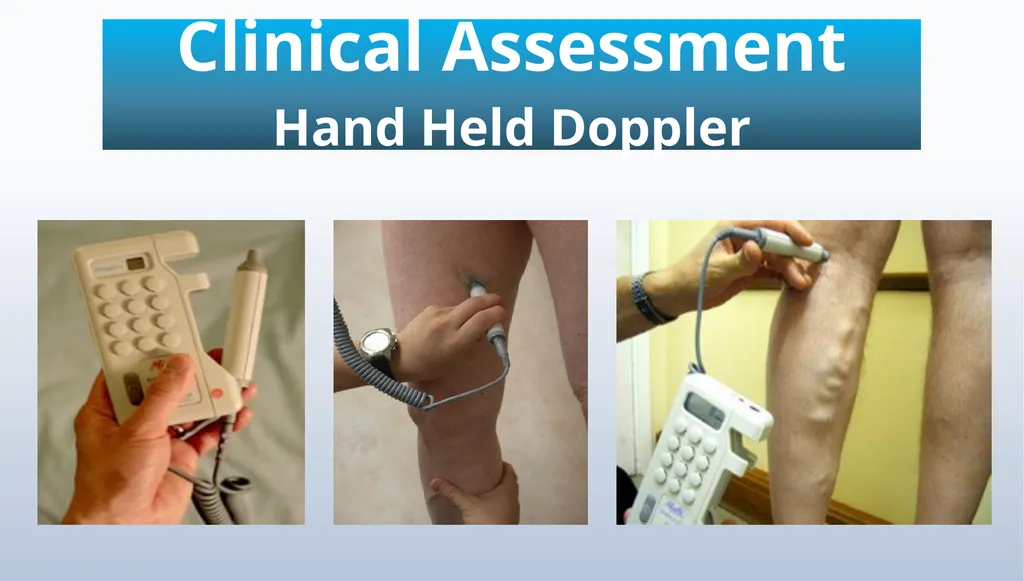
slide21. Clinical Assessment Hand Held Doppler<br>
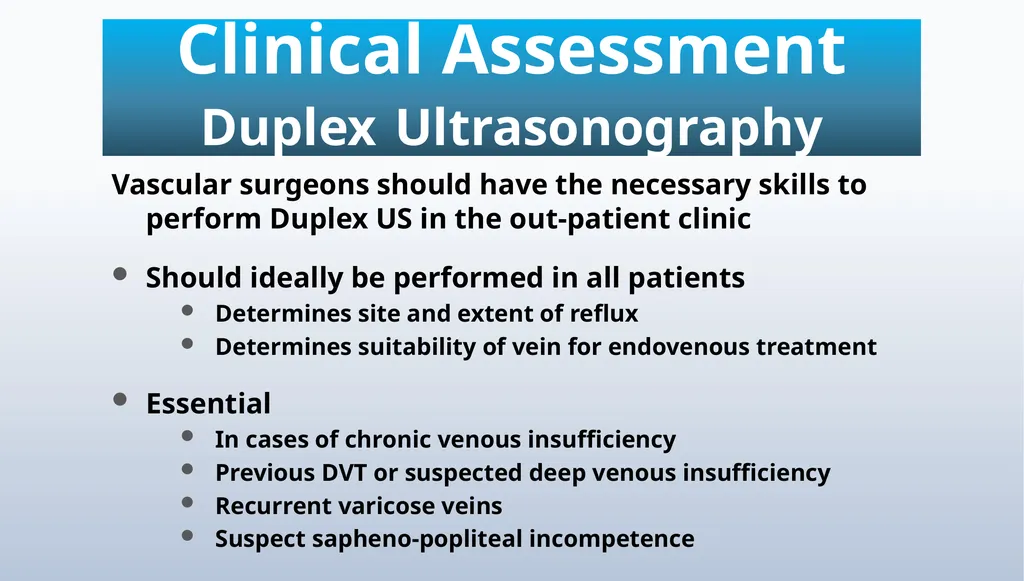
slide22. Clinical Assessment Duplex Ultrasonography Vascular surgeons should have the necessary skills to perform Duplex US in the out-patient clinic
Should ideally be performed in all patients
Determines site and extent of reflux
Determines suitability of vein for endovenous treatment
Essential
In cases of chronic venous insufficiency
Previous DVT or suspected deep venous insufficiency
Recurrent varicose veins
Suspect sapheno-popliteal incompetence<br>
slide23. Treatment Reassurance
Compression hosiery
Foam sclerotherapy
Endovenous ablation
Conventional surgery<br>
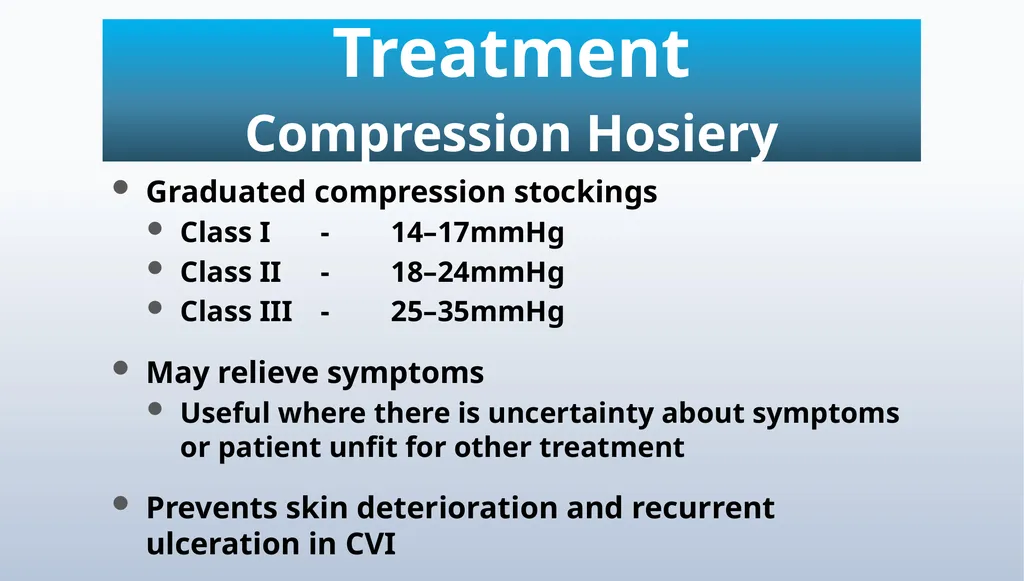
slide24. Treatment Compression Hosiery Graduated compression stockings
Class I - 14–17mmHg
Class II - 18–24mmHg
Class III - 25–35mmHg
May relieve symptoms
Useful where there is uncertainty about symptoms or patient unfit for other treatment
Prevents skin deterioration and recurrent ulceration in CVI<br>
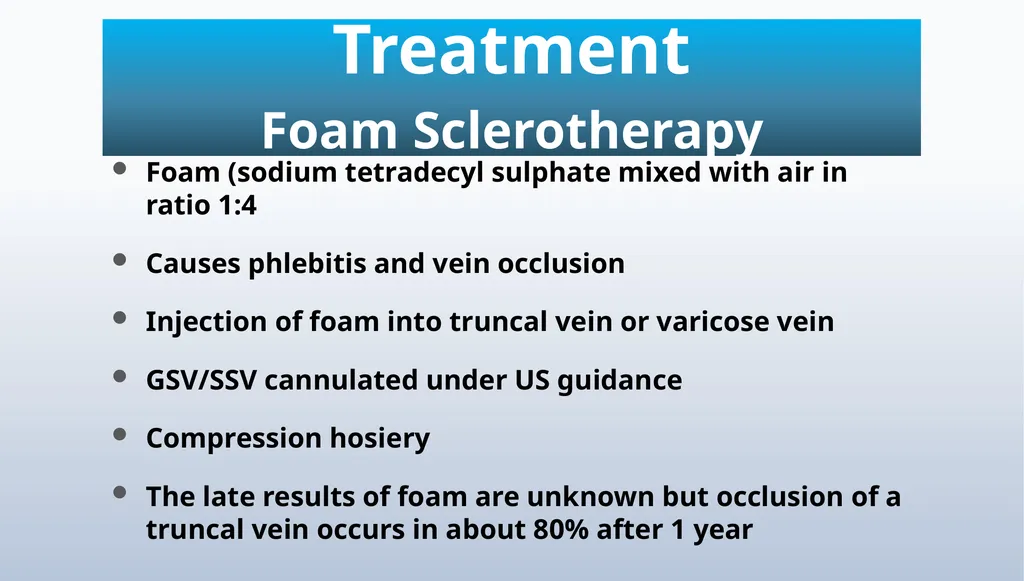
slide25. Treatment Foam Sclerotherapy Foam (sodium tetradecyl sulphate mixed with air in ratio 1:4
Causes phlebitis and vein occlusion
Injection of foam into truncal vein or varicose vein
GSV/SSV cannulated under US guidance
Compression hosiery
The late results of foam are unknown but occlusion of a truncal vein occurs in about 80% after 1 year<br>
slide26. Treatment Endovenous ablation Radiofrequency Ablation
delivery of thermal energy from an electric current to the vein wall
Generates temperatures of 85–120°C
Endovenous Laser Ablation
Delivery of light energy at 810–1470 nm
Thermal damage to vein wall
Both damage the vein wall causing subsequent thrombosis<br>
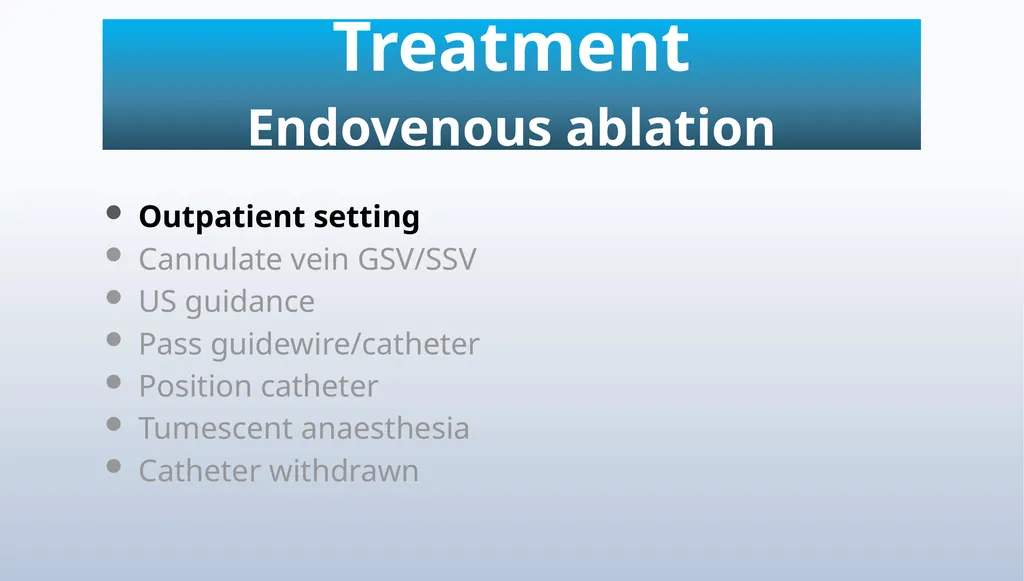
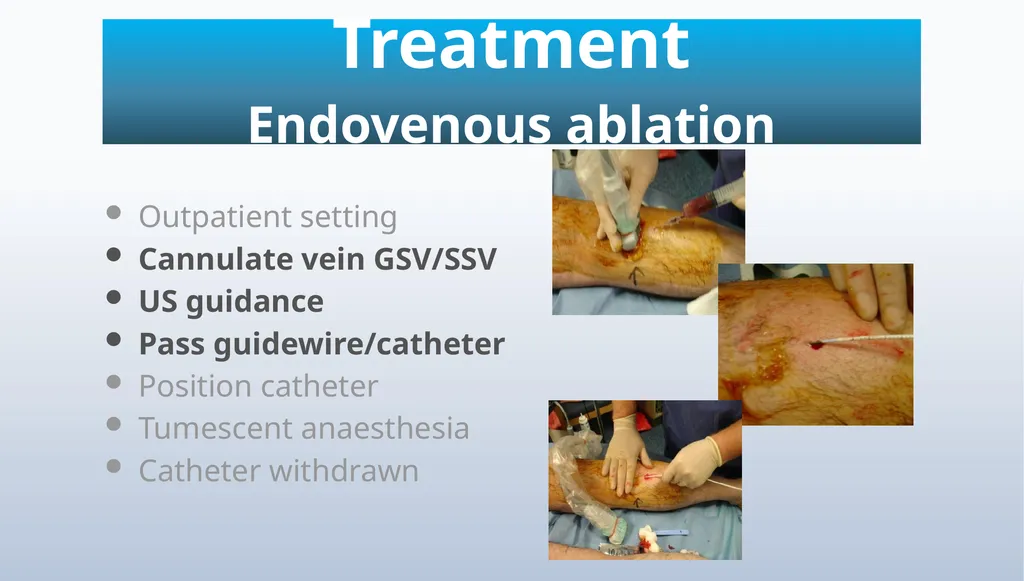
slide27. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
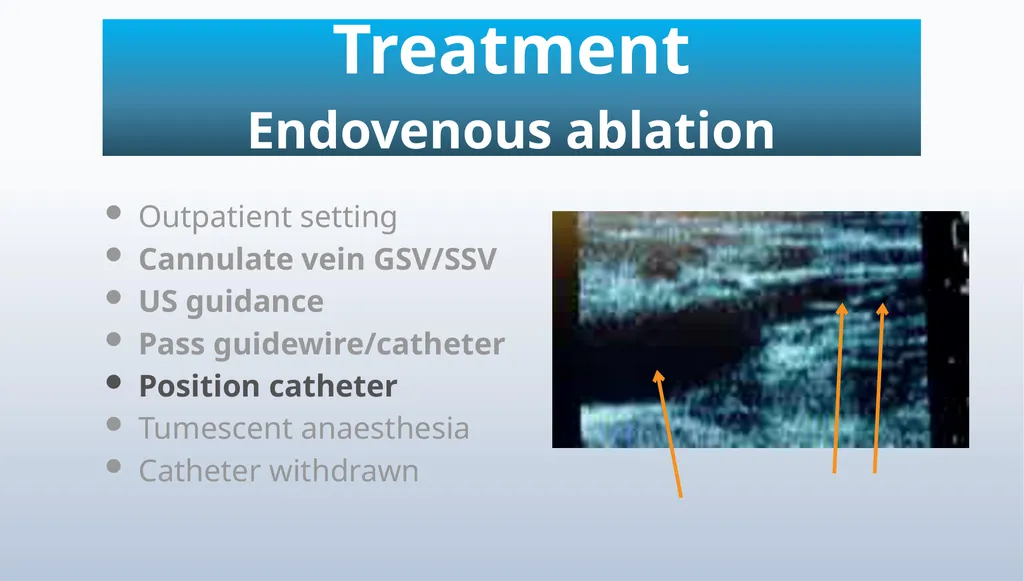
slide28. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
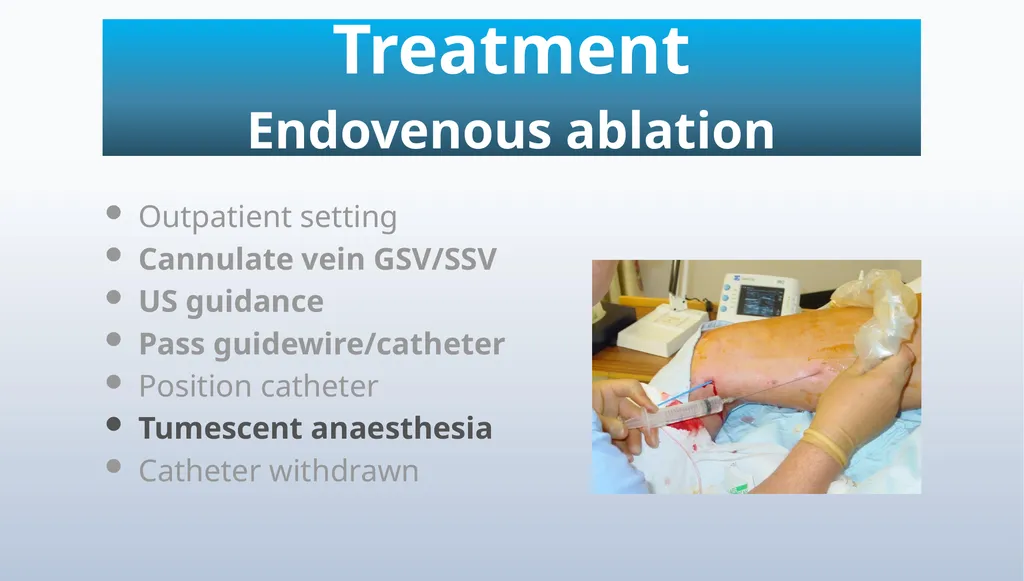
slide29. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide30. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide31. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide32. Treatment Endovenous ablation Compression hoisery for 6 weeks
Analgesia – NSAID
Review – 6 weeks
20% residual varicosities
Foam sclerotherapy<br>
slide33. Treatment Conventional Surgery Gold standard
Saphenofemoral ligation and stripping GSV
Saphenopopliteal ligation
Phlebectomies
Complications
Bruising, bleeding
Wound infection
Nerve injury
DVT<br>
Consultant Vascular Surgeon<br>
slide2. Objectives Know about the anatomy, epidemiology and pathophysiology of varicose veins
Know how to assess a patients with varicose veins
Know how to investigate a patient with varicose veins
Know about the management and outcomes of treatment for varicose veins<br>
slide3. Anatomy<br>
slide4. Epidemiology Venous disease – 80%
35% trunk varices
Women > men, 2:1
Prevalence increases with age
Positive family history
Obesity
Occupation<br>
slide5. Types of varicose vein Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide6. Types of varicose vein Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide7. Other venous disorders Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide8. Other venous disorders Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide9. Other venous disorders Primary trunk varicose veins
Secondary trunk varicose veins
Reticular veins
Spider veins/venous flares
Venous malformations<br>
slide10. Pathophysiology Primary valve failure
Primary degenerative changes in the valve leaflets
Secondary valve failure
Developmental weakness in vein wall and secondary vein widening and valve incompetence<br>
slide11. Presentation Uncomplicated veins Cosmesis
Symptoms
For reassurance<br>
slide12. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide13. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide14. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide15. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide16. Presentation Complications of varicose veins Superficial thrombophlebitis
Lipodermatosclerosis and pigmentation
Varicose eczema
Ulceration
Haemorrhage<br>
slide17. Clinical Assessment History Are the symptoms due to venous disease
Is the presentation complicated or uncomplicated
Is there any other significant pathology such as previous DVT or arterial disease
Any other health problems
Previous varicose vein surgery?<br>
slide18. Clinical Assessment General examination Examination standing and adequately exposed
(leg and lower abdomen)
Inspection
Distribution of varicose veins (GSV/SSV)
Signs of chronic venous insufficiency
Scars<br>
slide19. Clinical Assessment Special tests Trendelenberg’s test
Perthes Test<br>
slide20. Clinical Assessment Special tests Trendelenberg’s test
Perthes Test<br>
slide21. Clinical Assessment Hand Held Doppler<br>
slide22. Clinical Assessment Duplex Ultrasonography Vascular surgeons should have the necessary skills to perform Duplex US in the out-patient clinic
Should ideally be performed in all patients
Determines site and extent of reflux
Determines suitability of vein for endovenous treatment
Essential
In cases of chronic venous insufficiency
Previous DVT or suspected deep venous insufficiency
Recurrent varicose veins
Suspect sapheno-popliteal incompetence<br>
slide23. Treatment Reassurance
Compression hosiery
Foam sclerotherapy
Endovenous ablation
Conventional surgery<br>
slide24. Treatment Compression Hosiery Graduated compression stockings
Class I - 14–17mmHg
Class II - 18–24mmHg
Class III - 25–35mmHg
May relieve symptoms
Useful where there is uncertainty about symptoms or patient unfit for other treatment
Prevents skin deterioration and recurrent ulceration in CVI<br>
slide25. Treatment Foam Sclerotherapy Foam (sodium tetradecyl sulphate mixed with air in ratio 1:4
Causes phlebitis and vein occlusion
Injection of foam into truncal vein or varicose vein
GSV/SSV cannulated under US guidance
Compression hosiery
The late results of foam are unknown but occlusion of a truncal vein occurs in about 80% after 1 year<br>
slide26. Treatment Endovenous ablation Radiofrequency Ablation
delivery of thermal energy from an electric current to the vein wall
Generates temperatures of 85–120°C
Endovenous Laser Ablation
Delivery of light energy at 810–1470 nm
Thermal damage to vein wall
Both damage the vein wall causing subsequent thrombosis<br>
slide27. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide28. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide29. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide30. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide31. Treatment Endovenous ablation Outpatient setting
Cannulate vein GSV/SSV
US guidance
Pass guidewire/catheter
Position catheter
Tumescent anaesthesia
Catheter withdrawn<br>
slide32. Treatment Endovenous ablation Compression hoisery for 6 weeks
Analgesia – NSAID
Review – 6 weeks
20% residual varicosities
Foam sclerotherapy<br>
slide33. Treatment Conventional Surgery Gold standard
Saphenofemoral ligation and stripping GSV
Saphenopopliteal ligation
Phlebectomies
Complications
Bruising, bleeding
Wound infection
Nerve injury
DVT<br>