
District of Columbia’s Managed Care Annual

































Description: District of Columbias Managed Care Annual Performance Report (January 2017 December 2017) May 2018 Washington DC Issued by: Department of Health Care Finance Presentation Outline 2 Goals and Purpose of Managed Care Review Summary Of
Related Topics
Download Presentation
"District of Columbia’s Managed Care Annual" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. District of Columbia’s Managed Care Annual Performance Report
(January 2017 – December 2017) May 2018
Washington DC Issued by:
Department of Health Care Finance<br>
slide2. Presentation Outline 2 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s MCOs
The Administrative Performance of the District’s Health
Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide3. Managed Care Represents DHCF’s Largest Provider Expenditure Department of Health Care Finance’s (DHCF) managed care program is the largest single expenditure in the agency’s budget consisting of the Medicaid and Alliance publicly-funded health insurance programs.
As of December 2017, nearly 198,662 Medicaid beneficiaries and just over 16,005 Alliance enrollees were assigned to one of the following Managed Care Organizations (MCO):
Amerigroup DC, Inc. (Amerigroup)*
AmeriHealth Caritas DC (AmeriHealth)
MedStar Family Choice (MedStar)*
Trusted Health Plan (Trusted)
Health Services for Children With Special Needs (HSCSN)
In 2017, all five MCOs offered comprehensive benefits. Four of these MCOs – Amerigroup, AmeriHealth, MedStar, and Trusted -- operated under full risk-based contracts while HSCSN worked under a risk sharing arrangement with the District.
The MCOs incurred costs of over $1.1 billion on MCO services in 2017. A little more than $919 million of this amount funded the full risk-based contracts signed by Amerigroup, AmeriHealth, MedStar, and Trusted, while approximately $180 million funded the risk sharing contract with HSCSN. 3 *In 2017, DHCF awarded contracts for the upcoming FY18 contract year for the three full risk-based MCOs. Two of the three MCOs -- AmeriHealth and Trusted -- are returning MCOs, with one newly-awarded MCO as of October 2017 - Amerigroup.<br>
slide4. History of MCO Performance Review Following the award of the contracts for the three full risk-based plans in 2013, DHCF initiated the MCO performance review process as the first step towards reforming a troubled program.
Prior to this award, DHCF’s MCO program was hampered by ambiguous contract language, financially unstable providers, and de minimis reporting requirements that made it difficult to assess the performance of the plans.
Accordingly, to coincide with the new five-year MCO contracts, DHCF initiated the comprehensive review process in FY2014 to assess and evaluate the performance of its three full risk-based MCOs. 4<br>
slide5. FY18 MCO Contract Procurement In 2017, DHCF awarded contracts for the upcoming FY18 contract year for the three full risk-based MCOs. Two of the three MCOs -- AmeriHealth and Trusted -- are returning, with one newly-awarded MCO - Amerigroup. DHCF conducted a robust RFI and readiness review process for each of the MCOs, evaluating the MCO’s ability to perform services included in the MCOs’ contracts, identifying best practices and opportunities for improvement.
MedStar appealed the results of the procurement to the Contract Appeals Board and DHCF was ordered to conduct a re-evaluation of the proposals. That decision is being appealed to the District Superior Court.
The goal of DHCF’s managed care program through the FY17 contract procurement process is to promote healthy outcomes of the enrolled populations in the most cost-effective manner possible. For instance, the new contract encourages provider performance rewards through innovative approaches to compensation, such as value-based purchasing (VBP) payment models that link specific financial incentives to demonstrable improved health outcomes.
As a result, DHCF’s managed care program will have a clear focus on achieving better health outcomes, health care innovation and cost effective quality healthcare. 5<br>
slide6. Goals Of The Performance Review There are three primary goals of this performance review:
Evaluate the degree to which DHCF’s risk-based MCOs and the single risk sharing plan successfully ensure beneficiary access to an adequate network of providers while managing the appropriate utilization of health care services.
Provide objective data on the performance of the MCOs across a number of domains to inform decision making about possible policy changes for the managed care program.
Facilitate an assessment of each MCO to help guide decisions regarding contract renewals of each MCO. 6<br>
slide7. This annual report for 2017 addresses the following questions for each MCO.
What was the financial condition of the MCOs during 2017? Were the MCO revenues sufficient to cover claims and operating costs?
Did the MCOs successfully execute the administrative responsibilities required of a managed care plan – timely claims processing, robust member encounter systems, and appropriate use of claims denial procedures?
Did the full risk-based MCOs successfully meet the 85% Medical Loss Ratio (MLR) threshold while otherwise containing cost? What service levels were achieved for primary care visits as well as mental health penetration rates for children and adults?
As a risk-sharing plan, did HSCSN meet the 89% MLR threshold while otherwise containing cost? As a result what is the financial impact for DHCF?
What success -- as measured by performance against three established benchmarks -- did the full risk MCOs experience in coordinating care for its members in 2017? Focus Of The Performance Review 7<br>
slide8. Presentation Outline 8 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide9. Strong Overall Financial Conditions - Full Risk-Based Health Plans
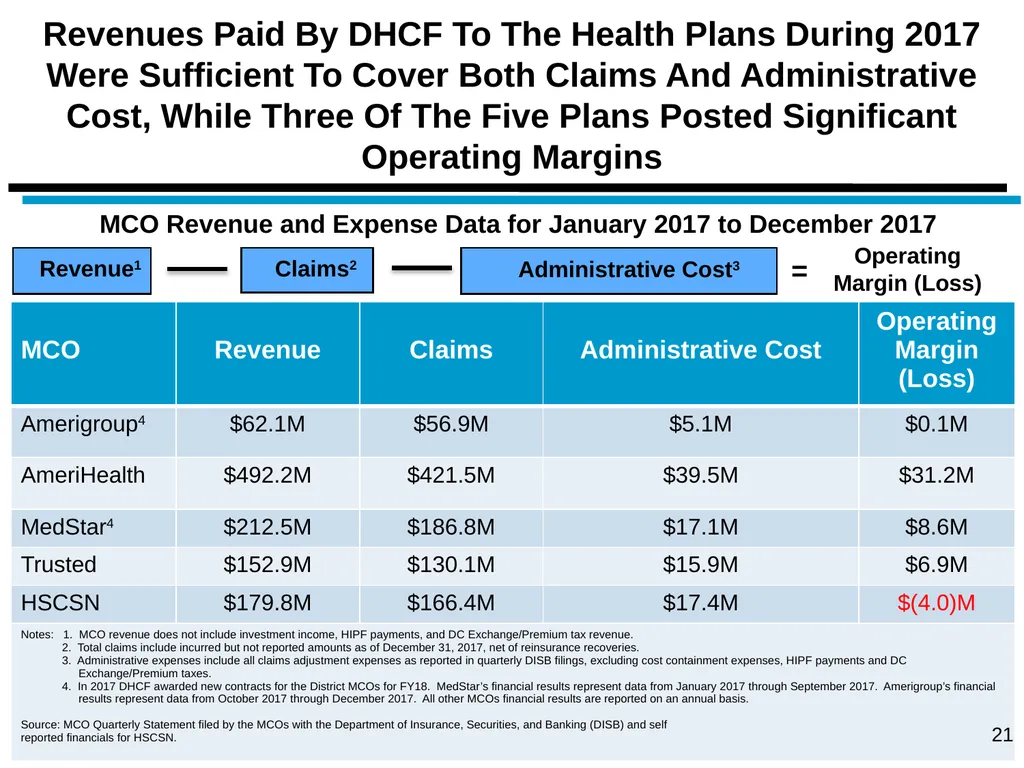
The District’s full-risk MCOs are generally in good financial condition at the end of 2017. Each of the full risk-based MCOs reports risk-based capital (RBC) positions that are above the required level of 200 percent, while posting profits ranging from 3 to 8 percent with ample cash reserves as protection against a sharp downturn in revenue. With respect to operating margins, Amerigroup was an exception - posting low margins during their first quarter of operations.
Amerigroup’s Low Margins
Given Amerigroup’s limited claims experience since convening operations in October 2017, Amerigroup employed a loss ratio approach to derive incurred but not reported (IBNR) claims expense for the period. Albeit this is an acceptable approach for estimating costs, this method may yield considerable variances with actual payments, resulting in high costs and low operating margins. Summary Of Key Findings 9<br>
slide10. HSCSN Declining Financial Position
After suffering huge losses in 2015, and temporarily stabilizing in 2016 as a result of the $13 million DHCF cash infusion in FY2016, HSCSN’s financial position has deteriorated resulting in the MCO operating a net loss for 2017. Though HSCSN’s cash position has improved, the plans total adjusted capital has decreased 42% while payables have increased, resulting in an RBC well below adequate solvency levels. If HSCSN was monitored through DISB, this level of RBC would require HSCSN to create a robust plan to rebuild capital to sufficient levels. DHCF is monitoring this situation closely and considering possible action.
Administrative Performance - All Health Plans
Four areas are typically evaluated to assess MCOs’ administrative performance – adequacy of provider network, timely payment of claims, appropriate management of the claims adjudication process, and successful execution of an encounter system. Data from this analysis indicates the MCOs are, on balance, properly managing these significant responsibilities. Notably in 2017:
The MCOs have maintained comprehensive and diverse provider networks to ensure access to a full range of services as well as robust systems to report patient encounters; Summary Of Key Findings (continued) 10<br>
slide11. HSCSN was the only MCO that did not exceed the District’s timely payment requirement in 2017, but their performance was only slightly less than the required standard. While HSCSN made significant improvements from its low 67 percent of claims paid within 30 days in 2016 to 89 percent in 2017, they are still not fully compliant with District law.
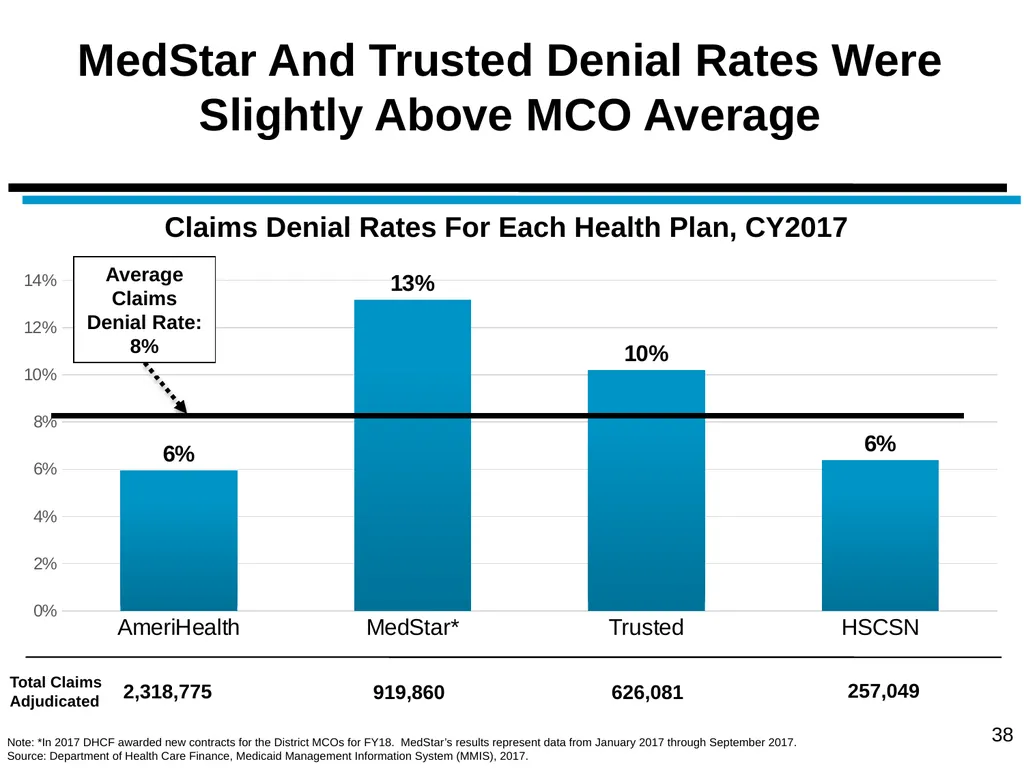
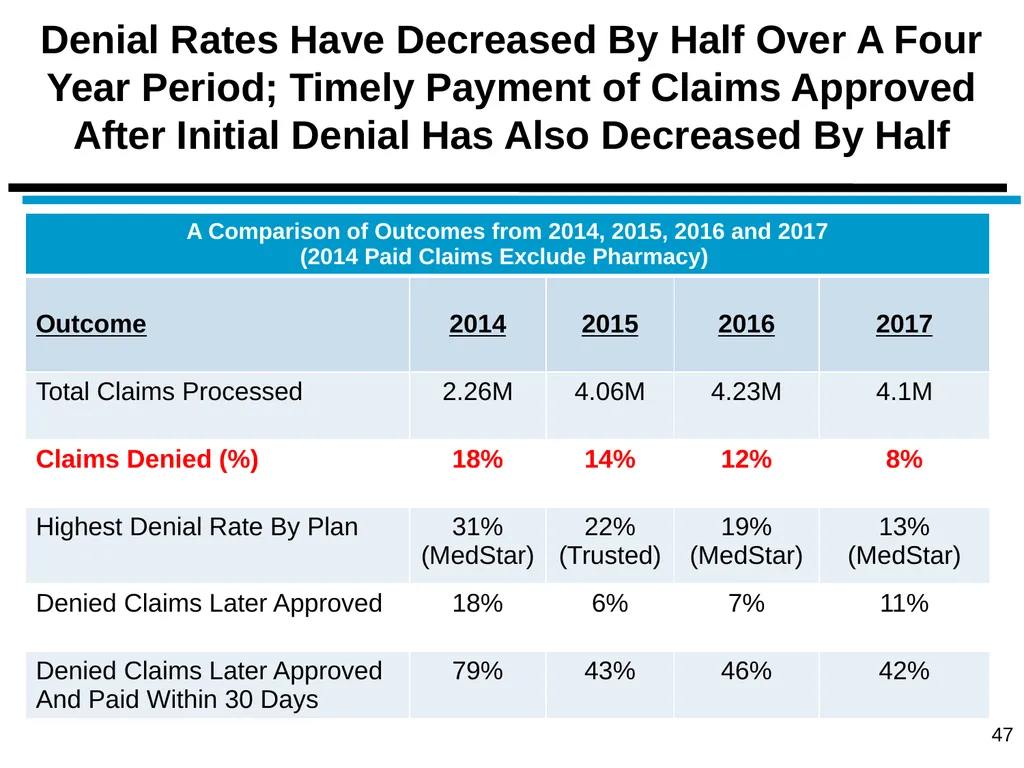
District MCO’s overall claims denial rate was eight percent, which is consistent with prior rates and suggests MCOs are not using claims adjudication as a cash management strategy.
Medical Expenses: Full-Risk-Based Health Plans
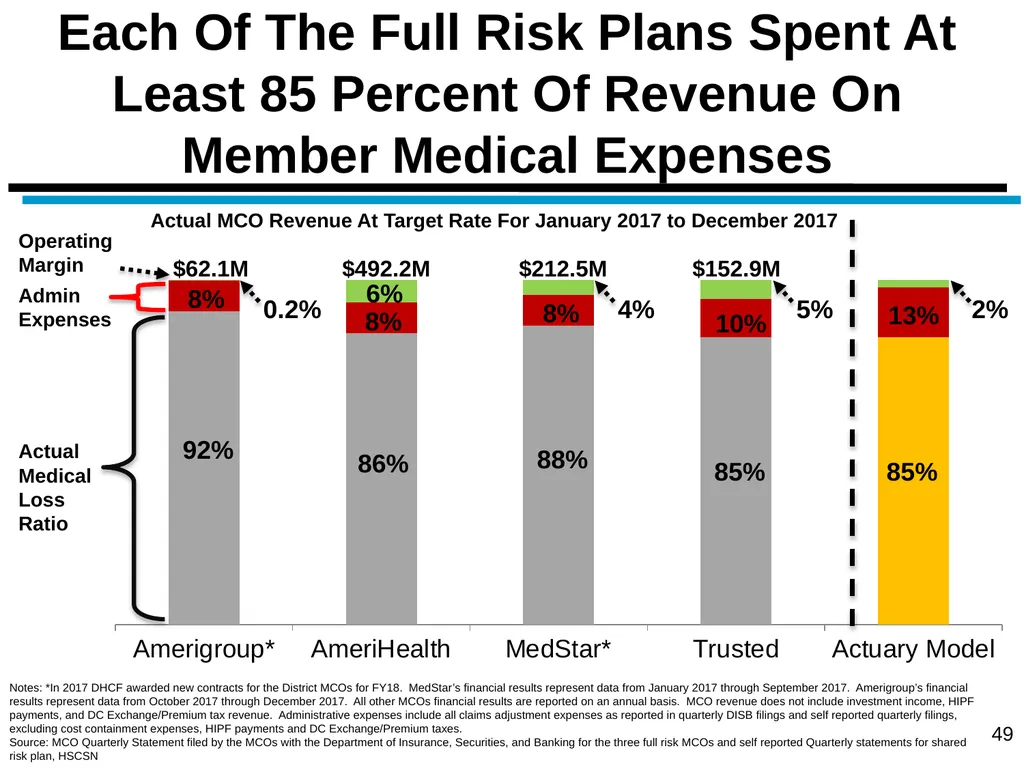
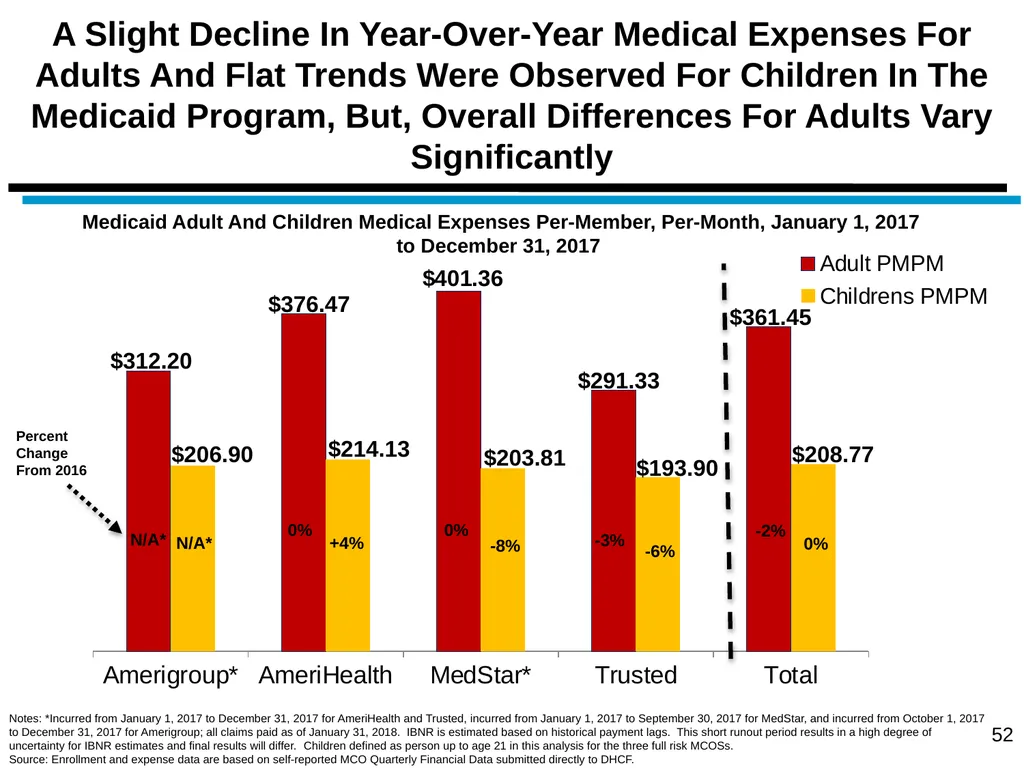
The MCOs in this program spend at least the required 85% of MCO revenue on beneficiary Medicaid medical expenses while generally avoiding spikes in their per-member, per-month (PMPM) costs. Specifically, the expense growth rate from 2016 to 2017 for Medicaid adults declined by 2 percent while the cost for children remained stable for the period. Summary Of Key Findings (continued) 11<br>
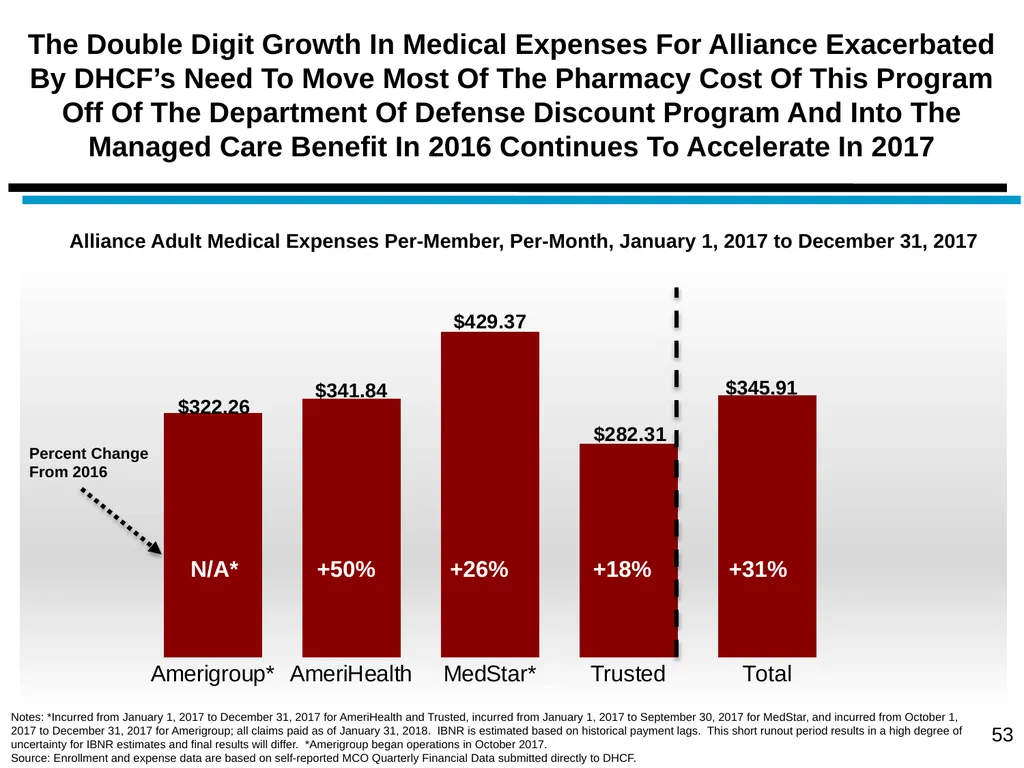
slide12. The PMPM cost of the Alliance program continued to be especially high for MedStar. However the other full-risk plans also experienced double digit increases in Alliance PMPM costs. The PMPM growth was most significant for AmeriHealth (50 percent), followed by MedStar (26 percent) and Trusted (18 percent).
Some of the growth was fueled by DHCF’s need to transition the pharmacy spending for the program off of the Department Of Defense Discount Program and into the MCO benefits in 2016. While enrollment growth is stable, the Alliance population is becoming slightly older with more complex medical problems. This has driven increased spending in pharmacy and outpatient hospital costs.
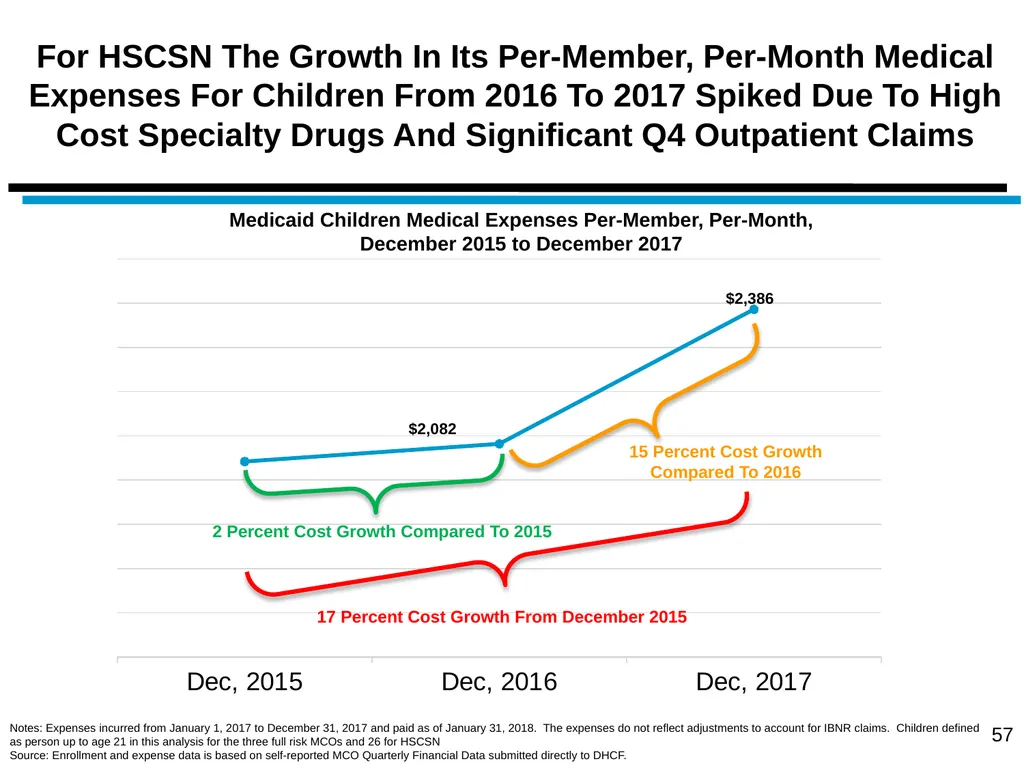
HSCSN’s 93 percent spending level on medical expenses for 2017 surpassed the threshold which provides the anchor for its rate. This reduced the operating margins for the plan and required DHCF to step in with risk corridor payments in 2017. The plan’s cost growth rate spiked at 15%, a sharp increase from the moderate 2% growth rate over the last year. This situation will be closely monitored in CY2018. Summary Of Key Findings (continued) 12<br>
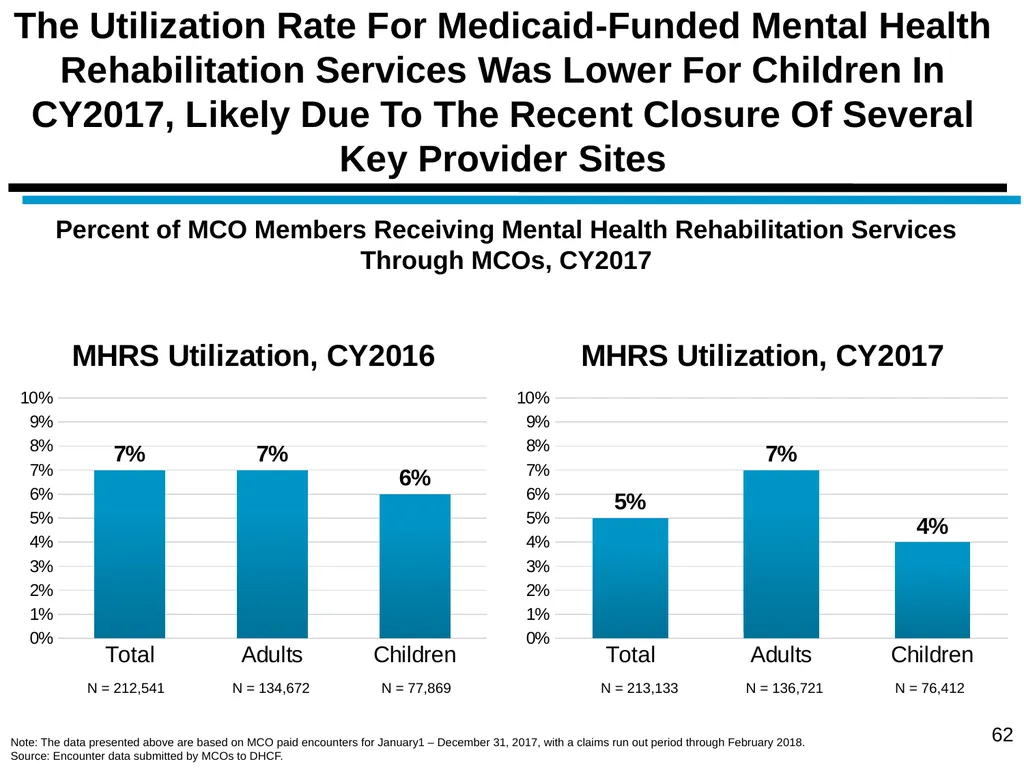
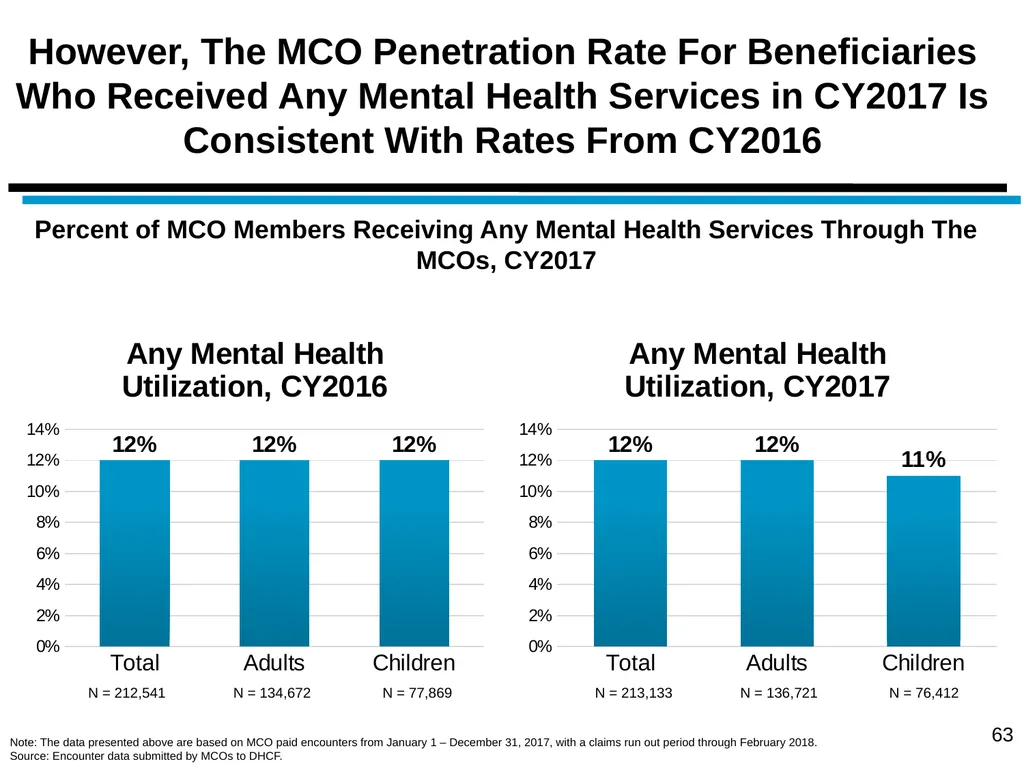
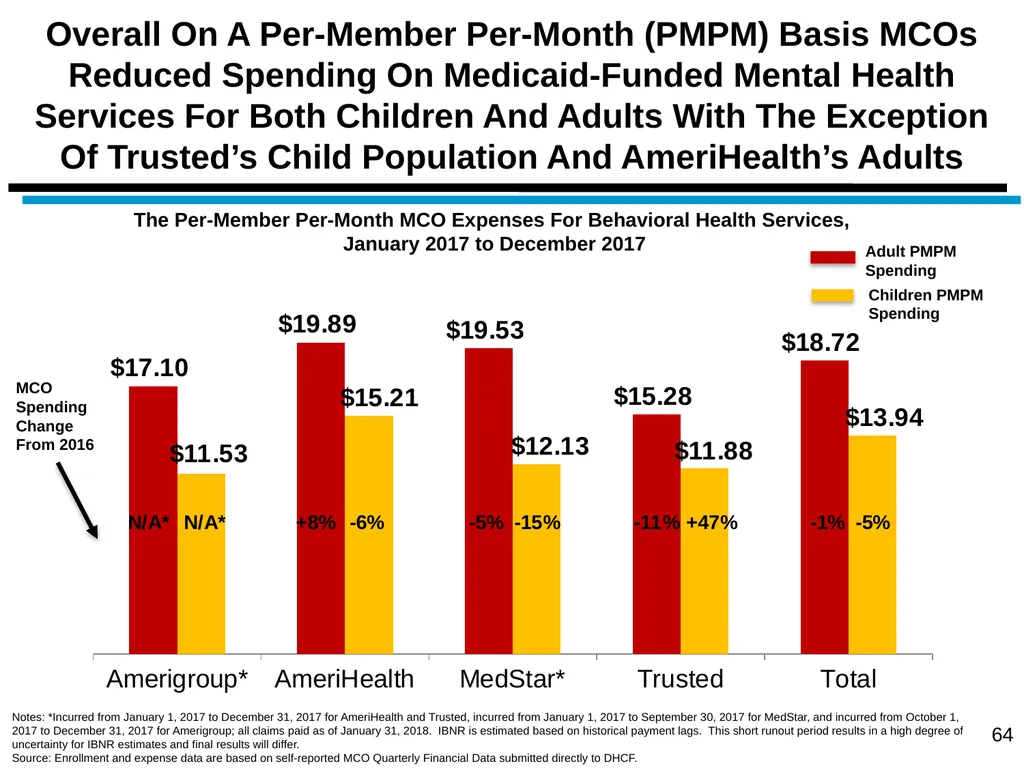
slide13. The mental health beneficiary utilizations rates for 2017 experienced a slight decrease for the Medicaid child population while remaining stable across the adult population, when compared to 2016 results. Mental health spending decreased slightly from $60.6 million in CY2016 to $57.8 million in CY2017, most likely due to the closure of several key MHRS provider sites in CY2017.
Beneficiary Utilization
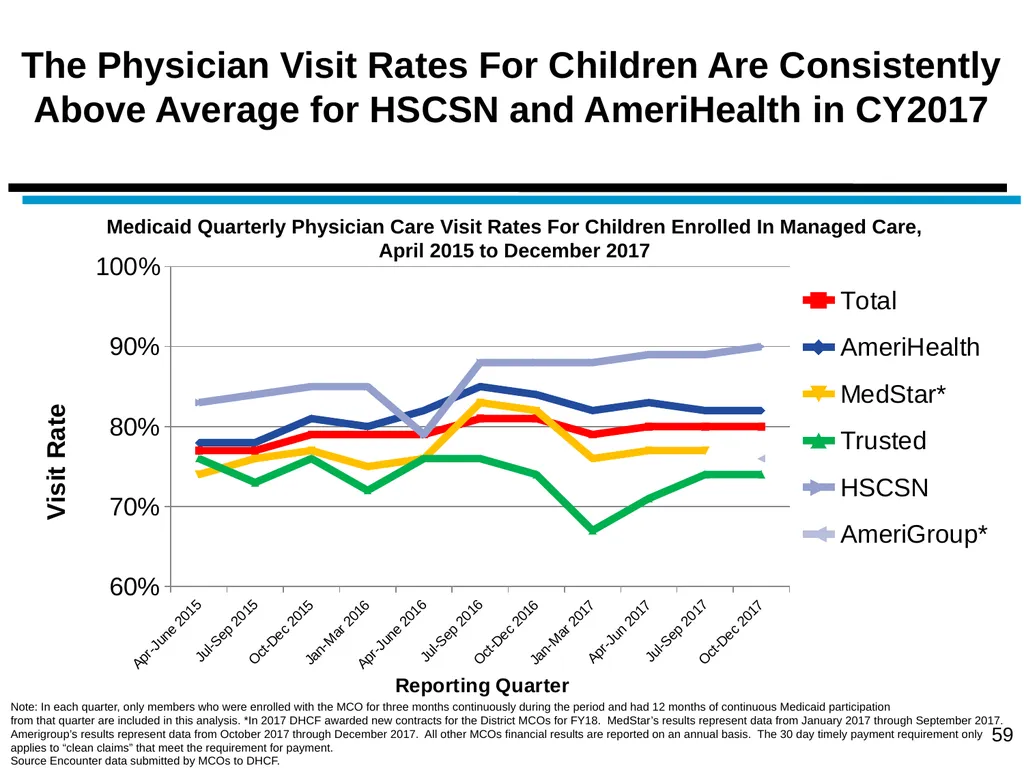
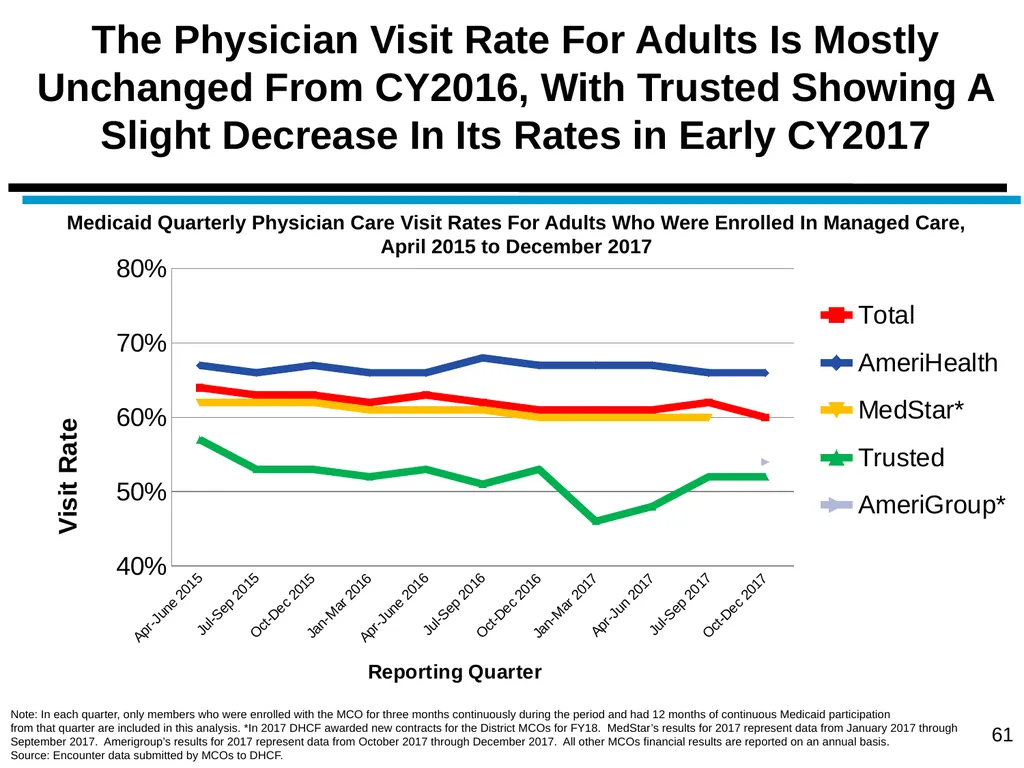
On average, the beneficiary physician visit rates are consistent with prior reporting periods, with the exception of a minor decrease in early 2017 for Trusted members, which was followed by a subsequent increase to prior levels in the second half of 2017.
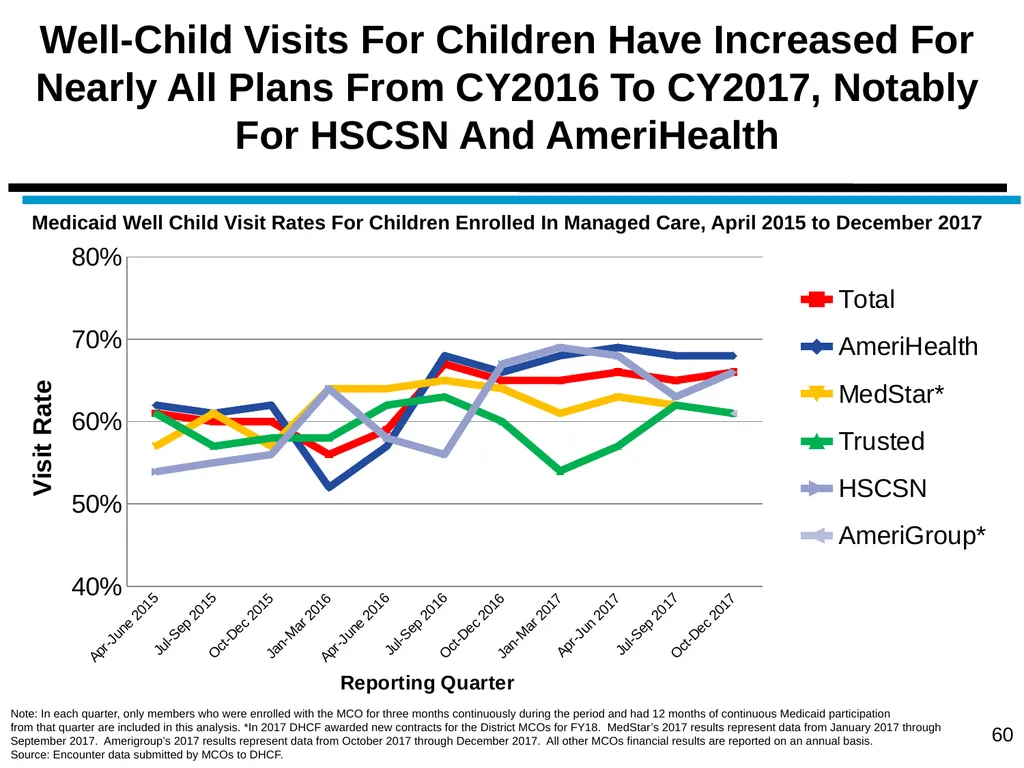
Well-Child visits for children increased for nearly all plans in CY2017, notably HSCSN and AmeriHealth. Summary Of Key Findings (continued) 13<br>
slide14. Care Coordination
The care coordination challenges that plagued the District’s three full-risk MCOs from 2014 through 2016 have been well documented -- members’ use of the emergency room for routine care, the repeated occurrences of potentially avoidable hospital admissions, the problem of hospital readmissions – and remain stubborn challenges, but with some improvement.
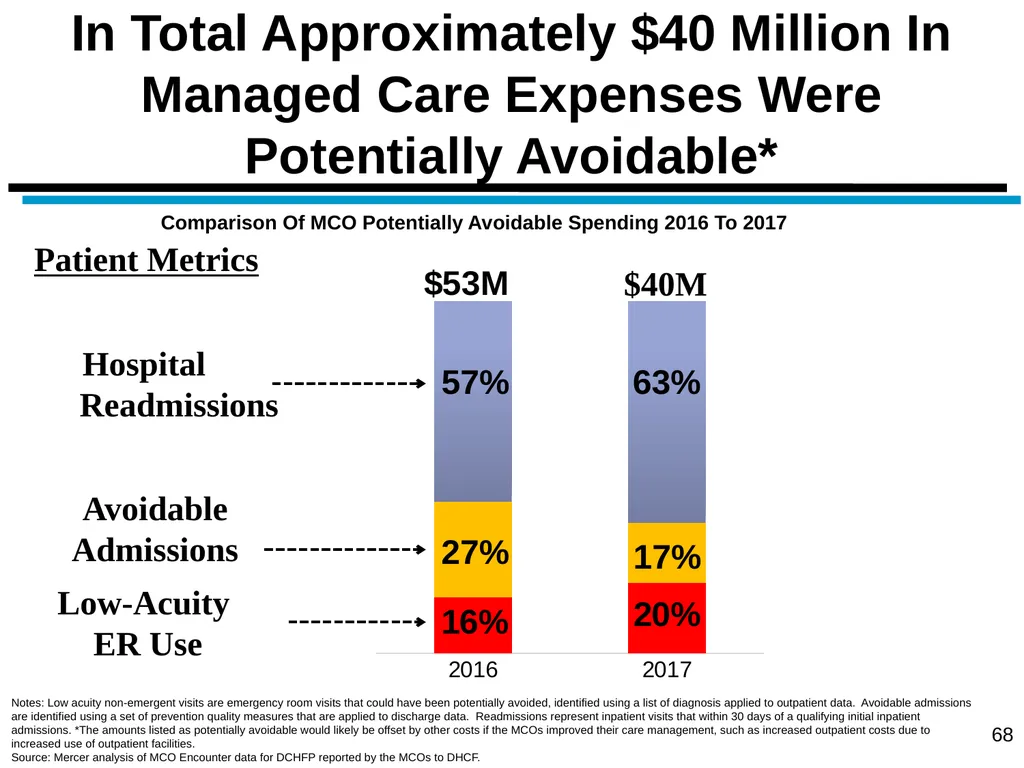
For 2017, the MCOs have spent approximately $40 million on patient care that may have been avoided through the use of more aggressive care coordination strategies. This, however; has declined from $53 million in avoidable spending in 2016.
CMS has now approved DHCF’s pay-for-performance (P4P) program. When comparing Year 1 (October 2016 – September 2017) of the P4P program to the baseline targets, only one MCO – Trusted – successfully earned back the full capitation withhold based on the MCO’s improvement achieved for all three of the performance goals. Summary Of Key Findings (continued) 14<br>
slide15. Presentation Outline 15 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide16. DHCF focuses on four key metrics when evaluating the financial stability of MCOs:
Medical loss ratio (MLR) – represents the portion of total revenue used by the MCOs to fund medical expenses, including expenses for cost containment.
Administrative loss ratio (ALR) – represents the portion of total revenue used by the MCOs to fund both claims processing and general administrative expenses.
Operating Margin (OM) – also referred to as profit margin and is defined as the sum of MLR and ALR subtracted from 100 percent. A positive OM indicates a financial gain while a negative indicates a loss. Mercer’s benchmark of the operating margin needed to sustain a strong financial position is approximately 2-4 percent annually over a 3-5 year time horizon.
Risk-based Capital (RBC) – represents a measure of the financial solvency of managed care plans and reflects the proportion of the required minimum capital that is maintained by a managed care plan as of the annual filing. There Are Several Key Metrics That Speak To The Financial Health Of MCOs 16<br>
slide17. Assuming adequacy in the base capitated payment rate, there are typically three important factors that impact whether an MCO will experience positive operating margins:
Risk-adjusted payment rates. With DHCF’s payment model, MCOs whose enrollees evince greater medical risk in the form of disease prevalence, receive higher risk scores and greater payments. MCOs with lower risk enrollees receive reduced rates. Thus, plans that properly align membership risk and utilization can gain a considerable advantage over others that do not.
Provider contract rates. Plans that negotiate contract rates that are adequate to build a solid network but lower than their competitors can realize significantly higher surpluses.
Patient utilization management. Relative differences across plans in the degree to which their enrollees unnecessarily access high end care as an alternative to less expensive treatment will drive variations in operating margins. Generally, Observed Differences In Health Plan Operating Margins Can Be Traced To A Few Key Factors 17<br>
slide18. Traditional concerns that patient care is being sacrificed are often expressed when MCOs report significant operating margins. Accordingly:
DHCF routinely tracks the MCOs’ performance against the 85% Medical Loss Ratio (MLR) requirement for full the risk based plans and 89% for the shared risk plan.
MCOs that fall short of this standard face detailed scrutiny and possible financial penalties if warranted.
Health plans can also artificially (and temporarily) inflate operating margins by repeatedly denying claims that should be paid.
DHCF monitored and reported on the MCOs’ management of the denied claims process starting in 2016. This report provides a comparative analysis for the year 2017 and the corresponding period in 2016. Some Strategies Can Increase Operating Margins But Are Not Reflective Of A Properly Operated Health Plan 18<br>
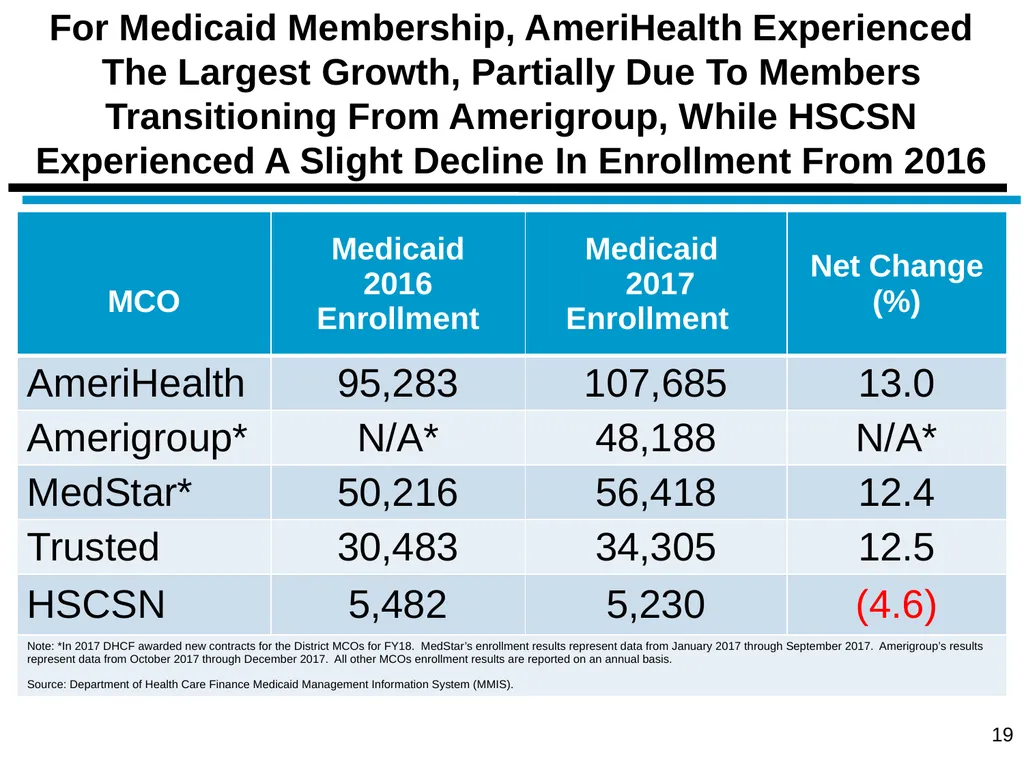
slide19. For Medicaid Membership, AmeriHealth Experienced The Largest Growth, Partially Due To Members Transitioning From Amerigroup, While HSCSN Experienced A Slight Decline In Enrollment From 2016 19<br>
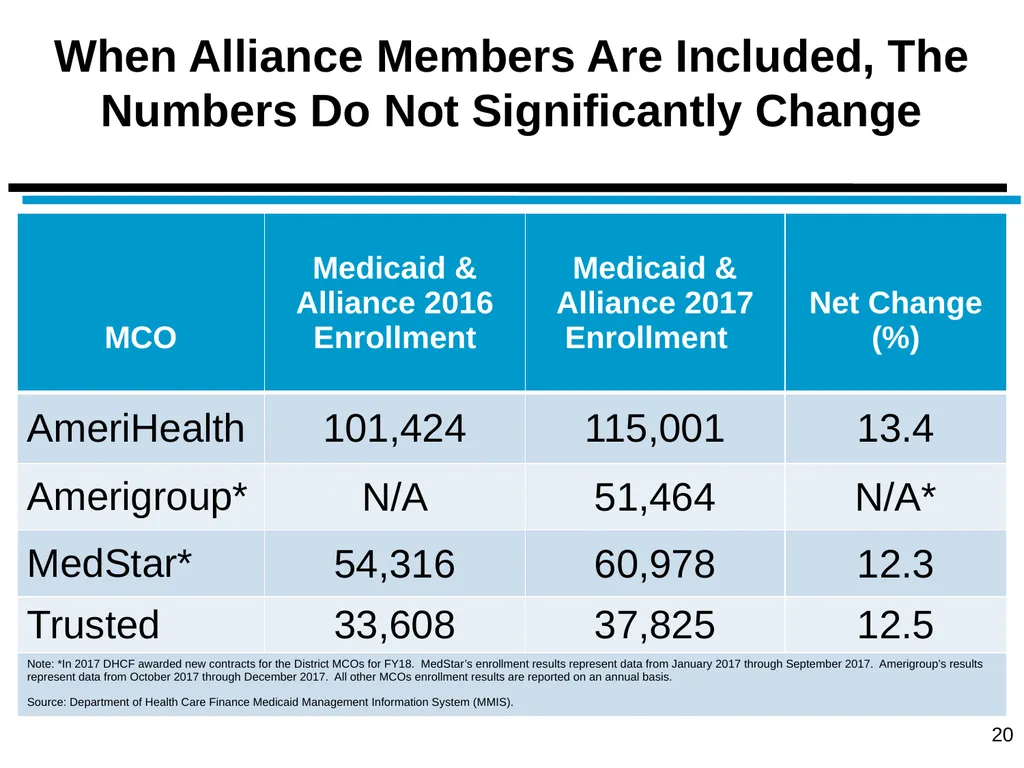
slide20. When Alliance Members Are Included, The Numbers Do Not Significantly Change 20<br>
slide21. Revenues Paid By DHCF To The Health Plans During 2017 Were Sufficient To Cover Both Claims And Administrative Cost, While Three Of The Five Plans Posted Significant Operating Margins Operating Margin (Loss) Revenue1 Claims2 Administrative Cost3 = MCO Revenue and Expense Data for January 2017 to December 2017 21<br>
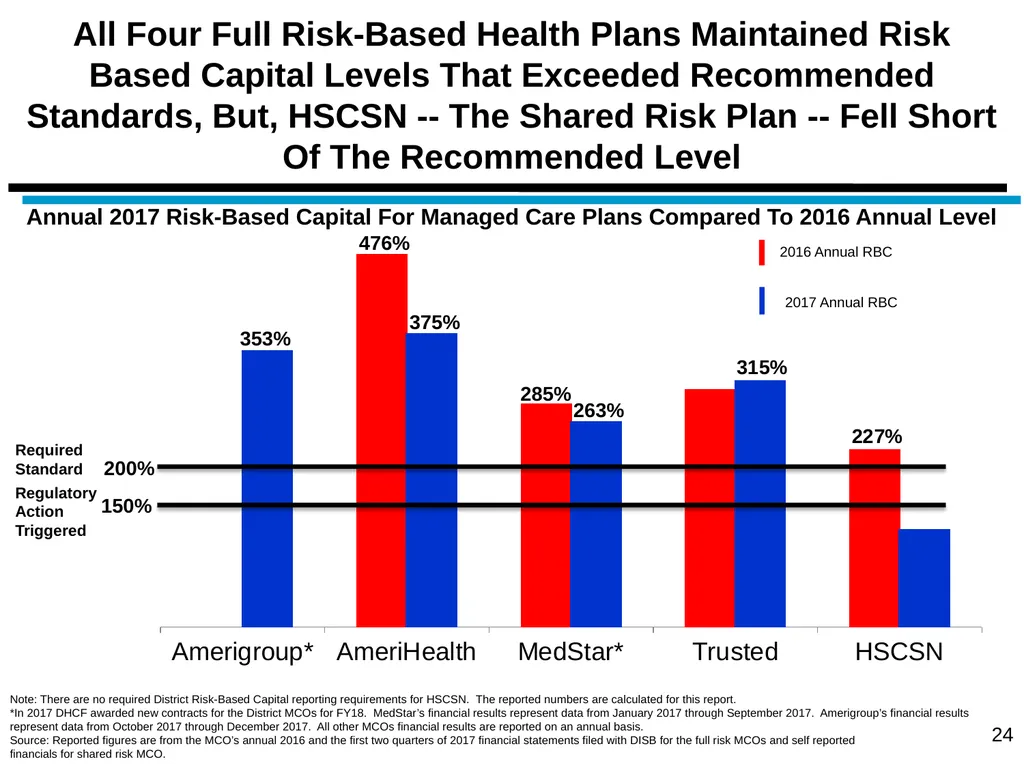
slide22. The MCO’s Risk-based Capital (RBC) levels can be seen as a proxy for whether an MCO has the assets to pay claims.
MCOs conduct this complicated calculation annually for each MCO using end-of-year financial data (as well as some information that is not publically disclosed) that is provided to the Department of Insurance, Securities and Banking (DISB) for review.
Health plans with RBC levels that fall below 200% face greater scrutiny from DISB and DHCF (as described on the next slide) to ensure that they raise their capital level above 200% RBC.
This report compares the annual RBC measures reported by the plans in their official 2016 financial statement filed with DISB to more recent 2017 RBC proxy calculated by Mercer Consulting. Estimated Risk-Based Capital Measures Provide A Reliable Indicator Of MCO Solvency 22<br>
slide23. Regulators Track Insurers Risk-Based Capital Levels And Have Guidelines For Taking Action 23 Based on the level of reported risk, the National Association of Insurance Commissioners indicates that a number of actions (described below) are available if warranted:
No action - Total Adjusted Capital of 200 percent or more of Authorized Control Level.
Company Action Level - Total Adjusted Capital of 150 to 200 percent of Authorized Control Level. Insurer must prepare a report to the regulator outlining a comprehensive financial plan that identifies the conditions that contributed to the company’s financial condition and a corrective action plan.
Regulatory Action Level - Total Adjusted Capital of 100 to 150 percent of Authorized Control Level. Company is required to file an action plan and the Insurance Commissioner issues appropriate corrective orders to address the company’s financial problems.
Authorized Control Level - Total Adjusted Capital 70 to 100 percent of the Authorized Control Level triggers an action in which the regulator takes control of the insurer even though the insurer may technically be solvent.
Mandatory Control Level - Total Adjusted Capital of less than 70 percent triggers a Mandatory Control Level that requires the regulator to take steps to place the insurer under control. Most companies that trigger this action level are technically insolvent (liabilities exceed assets).<br>
slide24. All Four Full Risk-Based Health Plans Maintained Risk Based Capital Levels That Exceeded Recommended Standards, But, HSCSN -- The Shared Risk Plan -- Fell Short Of The Recommended Level 24 Required Standard 200% Regulatory Action
Triggered 150% Annual 2017 Risk-Based Capital For Managed Care Plans Compared To 2016 Annual Level 353% 375% 476% 263% 285% 2016 Annual RBC 2017 Annual RBC Note: There are no required District Risk-Based Capital reporting requirements for HSCSN. The reported numbers are calculated for this report.
*In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Reported figures are from the MCO’s annual 2016 and the first two quarters of 2017 financial statements filed with DISB for the full risk MCOs and self reported
financials for shared risk MCO.<br>
slide25. It is paramount in managed care that MCOs maintain a reserve to pay for services that have been provided but not yet reimbursed.
This claims liability represents an accrued expense or short-term liability for the MCOs each month and MCOs that fail to build a sufficient reserve may not be able to pay claims when they eventually clear the billing pipeline.
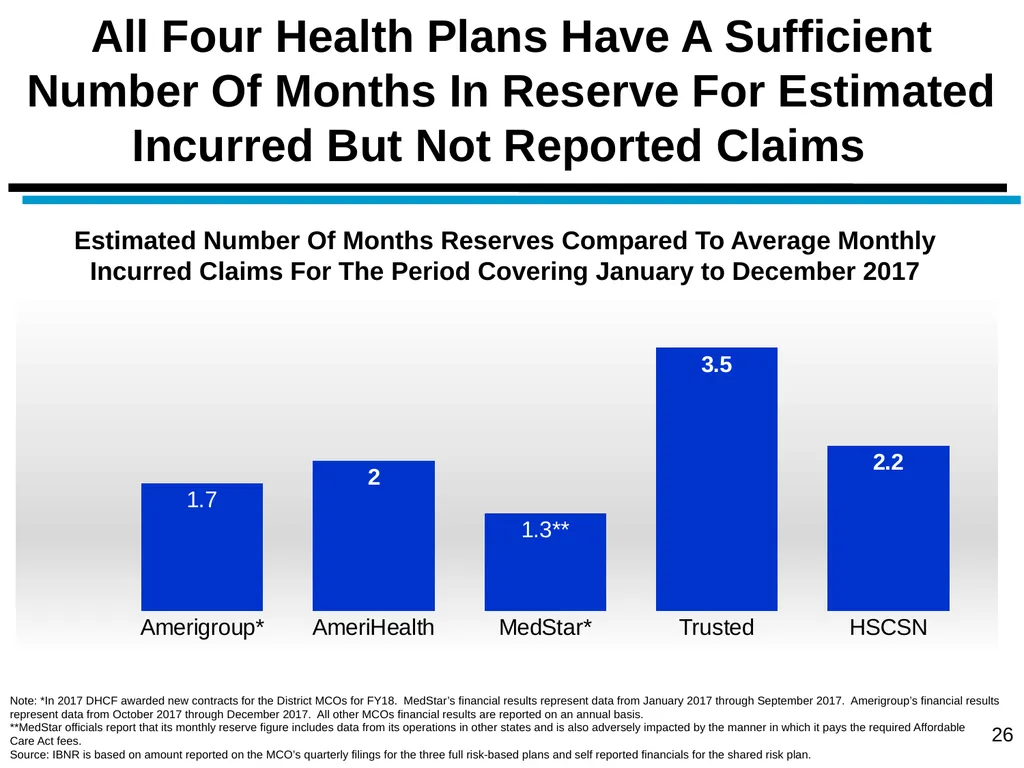
Typically, MCOs are expected to retain a reserve equal to between one to two months’ worth of claims, depending on how quickly claims are processed.
In this report, DHCF reports the reserves MCO’s have available to satisfy incurred but not reported claims. This analysis is based on calculations provided by Mercer using data on the monthly claim’s experience for each plan to calculate the reserves on hand.
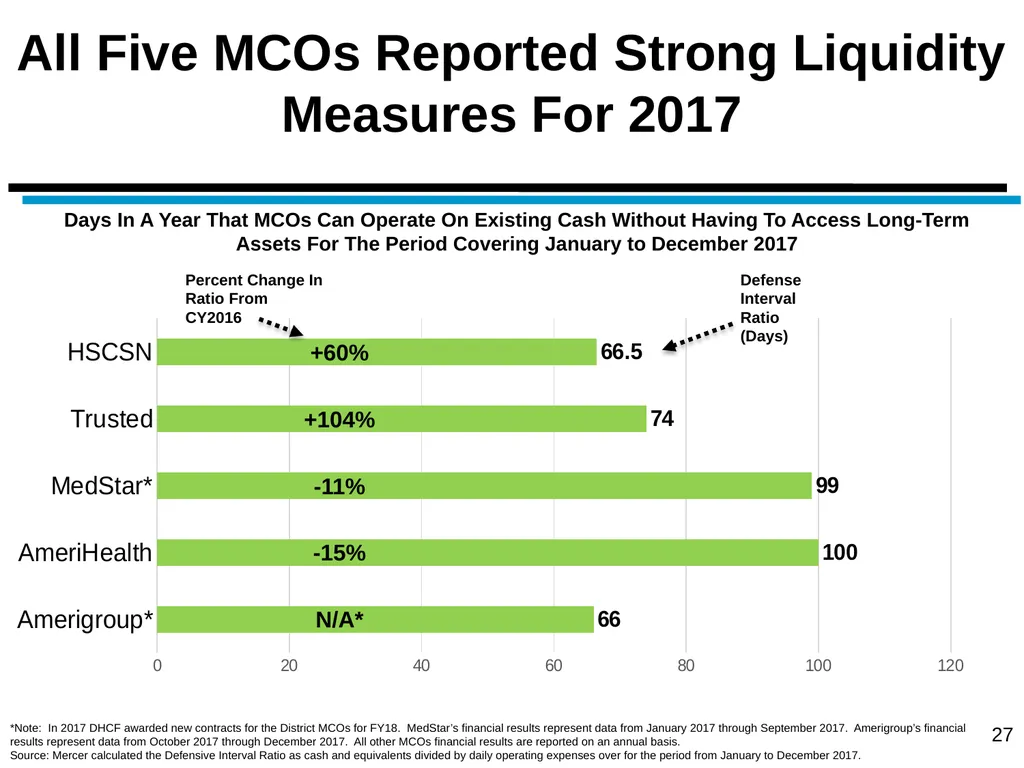
We also provide an analysis of the number of days the MCOs can operate without accessing long-term assets. This is described as a Defensive Interval Ratio which is, in essence, a liquidity measure -- the degree to which the MCOs can survive on liquid assets without having to make use of either investments from the market or by selling long term assets. MCOs Must Maintain Adequate Reserves To Pay “Pipeline” Claims 25<br>
slide26. All Four Health Plans Have A Sufficient Number Of Months In Reserve For Estimated Incurred But Not Reported Claims 26 Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
**MedStar officials report that its monthly reserve figure includes data from its operations in other states and is also adversely impacted by the manner in which it pays the required Affordable
Care Act fees.
Source: IBNR is based on amount reported on the MCO’s quarterly filings for the three full risk-based plans and self reported financials for the shared risk plan. Estimated Number Of Months Reserves Compared To Average Monthly Incurred Claims For The Period Covering January to December 2017<br>
slide27. All Five MCOs Reported Strong Liquidity Measures For 2017 27 Days In A Year That MCOs Can Operate On Existing Cash Without Having To Access Long-Term Assets For The Period Covering January to December 2017 +60% N/A* Defense Interval Ratio (Days) Percent Change In
Ratio From CY2016 -15% *Note: In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Mercer calculated the Defensive Interval Ratio as cash and equivalents divided by daily operating expenses over for the period from January to December 2017. +104% -11%<br>
slide28. Presentation Outline 28 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health
Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide29. As a part of its core mission, MCOs must accomplish the following:
Build an adequate network of providers and pay health care claims to service providers on time and through an electronic claims process with documentation to facilitate reconciliation of payments.
Create an accurate electronic record of all patient health care encounters and transmit the files containing this information to DHCF with a minimal error rate.
Establish a system of care management and care coordination to identify MCO enrollees with special or chronic health care issues and ensure that these enrollees each receives access to appropriate care, while managing the delivery of health care services for all enrollees. There Are Several Administrative Requirements Which Are Critical To The Successful Operation Of MCOs 29<br>
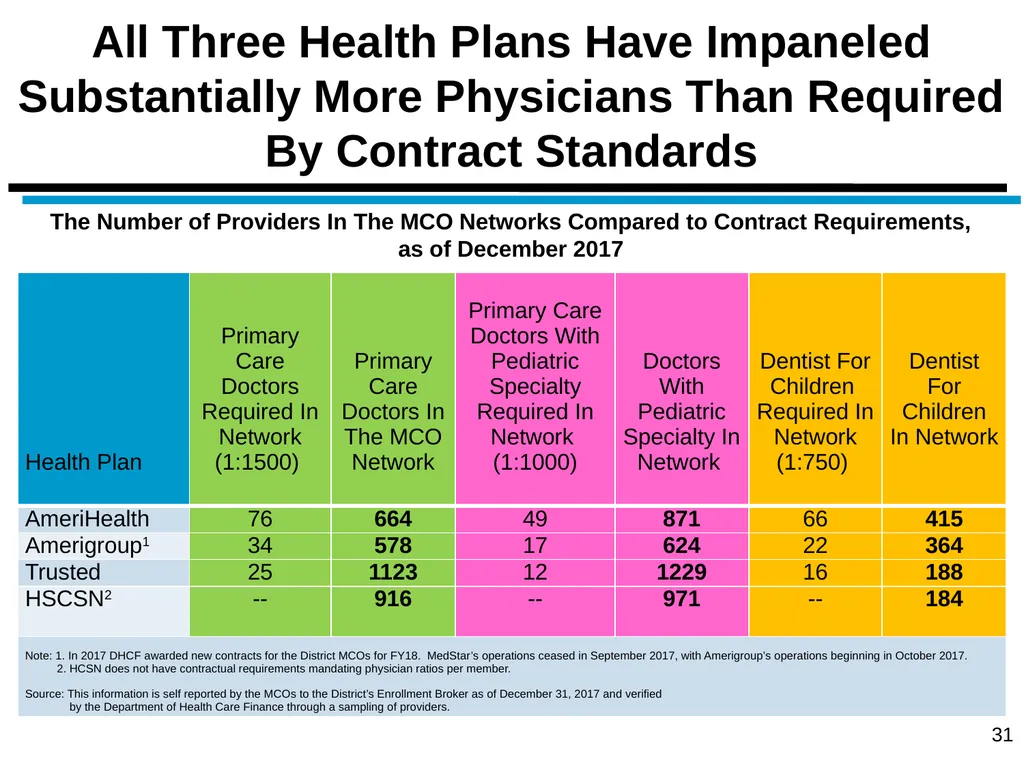
slide30. The five-year MCO contracts contain specific provisions to ensure Medicaid and Alliance enrollees have reasonable access to care. The MCOs must have:
1 primary care physician for every 1,500 enrollees
1 primary care physician with pediatric training for children through age 20 for every 1,000 enrollees
1 dentist for every 750 children in their networks
Additionally plan networks must include:
At least 2 hospitals that specialize in pediatric care
Department of Behavioral Health core service agencies
Laboratories within 30 minutes travel time from the enrollees’ residence
For pharmacies, each plan must have:
2 pharmacies within 2 miles of the enrollees’ residence
1 24-hour, seven (7) day per week pharmacy
1 pharmacy that provides home delivery service within 4 hours
1 mail order pharmacy Contractual Requirements Exist To Ensure Adequate Health Care Provider Networks 30<br>
slide31. All Three Health Plans Have Impaneled Substantially More Physicians Than Required By Contract Standards 31 The Number of Providers In The MCO Networks Compared to Contract Requirements, as of December 2017<br>
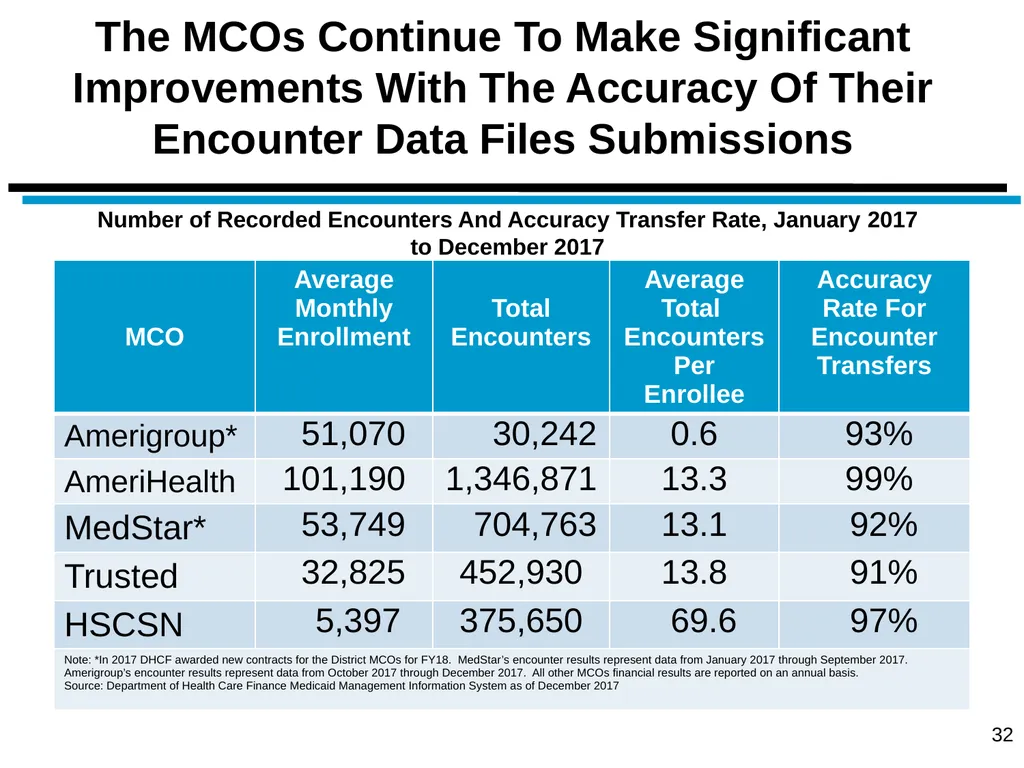
slide32. The MCOs Continue To Make Significant Improvements With The Accuracy Of Their Encounter Data Files Submissions 32 Number of Recorded Encounters And Accuracy Transfer Rate, January 2017
to December 2017<br>
slide33. 33 Timely Payment Of Health Care Claims Is Core Requirement For The District’s Managed Care Plans Claims processing is a central administrative function that MCOs must effectively execute to avoid payment problems for providers.
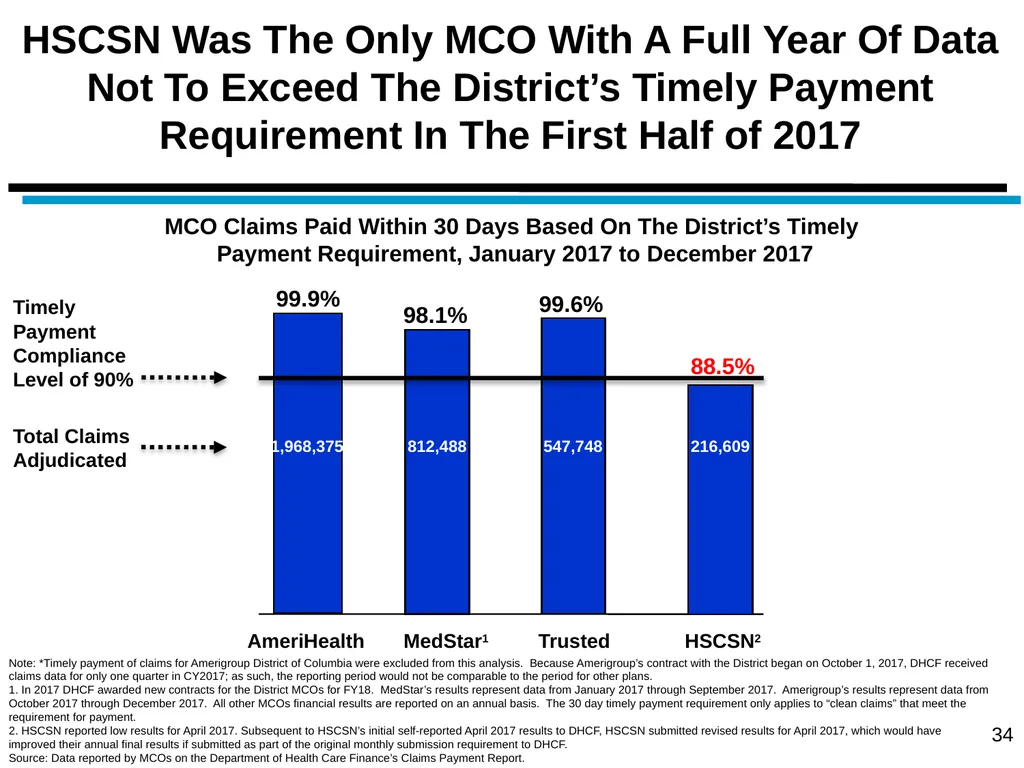
Through electronic claims processing, the District’s three managed care organizations are required to pay or deny clean claims within 30 days to satisfy timely filing requirements.
Like most MCOs, the District’s MCOs employ a series of automated edit checks on all claims submitted for payment by healthcare providers in the Medicaid and Alliance programs.
Included among the numerous potential problems this system of edit checks is designed to eliminate are:
Duplicate or overpayments
Payments to out-of-network or otherwise ineligible providers
Payments for services delivered to non-eligible patients<br>
slide34. HSCSN Was The Only MCO With A Full Year Of Data Not To Exceed The District’s Timely Payment Requirement In The First Half of 2017 34 99.9% 99.6% Total Claims Adjudicated 170,371 812,488 Timely Payment Compliance Level of 90% MCO Claims Paid Within 30 Days Based On The District’s Timely
Payment Requirement, January 2017 to December 2017 547,748 216,609 88.5% Note: *Timely payment of claims for Amerigroup District of Columbia were excluded from this analysis. Because Amerigroup’s contract with the District began on October 1, 2017, DHCF received claims data for only one quarter in CY2017; as such, the reporting period would not be comparable to the period for other plans.
1. In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017. Amerigroup’s results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. The 30 day timely payment requirement only applies to “clean claims” that meet the requirement for payment.
2. HSCSN reported low results for April 2017. Subsequent to HSCSN’s initial self-reported April 2017 results to DHCF, HSCSN submitted revised results for April 2017, which would have improved their annual final results if submitted as part of the original monthly submission requirement to DHCF.
Source: Data reported by MCOs on the Department of Health Care Finance’s Claims Payment Report. 1,968,375 98.1%<br>
slide35. 35 Claims Adjudication Review Focuses On Whether MCOs Are Acting In Good Faith Because the District’s 30-day timely payment requirement does not apply to claims that are initially denied, some providers expressed concern that managed care plans were unjustifiably denying a high rate of claims as a cash management strategy.
Such a practice would obviously violate the tenets of good faith claims processing, create significant revenue issues for some of the providers in the MCOs’ networks, and potentially cause access to care issues.
This report addresses this issue by reporting on the incidence of denied claims in the managed care program and the reasons for the denials for the period covering calendar year 2017. Additionally, outcomes for claims that were initially denied but subsequently approved and repaid are also examined.<br>
slide36. Methodology For Denied Claims Review 36 The key steps executed for this analysis were as follows:
First, all MCO denied claims with dates of service between January 1, 2017 and December 31, 2017 were obtained from the District’s four MCOs* and established as the master dataset. This data extraction yielded approximately 340,000 claims.
Second, this master dataset was used to categorize provider types to match DHCF naming schemes and search for all claims with missing identifiers.
Third, using DHCF’s MMIS, all paid patient encounters with dates of service between January 1, 2017 and December 31, 2017 were extracted, yielding nearly 4.1 million records.
Fourth, the dataset containing denied MCO claims (Step 1) was then merged with the dataset containing accepted encounters from MMIS (Step 2), using the beneficiaries’ Medicaid ID, first date of service, last date of service, and billing provider NPI as the matching variables. This established in the same dataset, claims that were paid, denied, and those that were initially denied but paid at a later date. Note: *Paid and denied claims submitted by Amerigroup District of Columbia were excluded from this analysis. Because Amerigroup’s contract with the District began on October 1, 2017, DHCF received claims data for only one quarter in CY2017; as such, the reporting period would not be comparable to the period for other plans.<br>
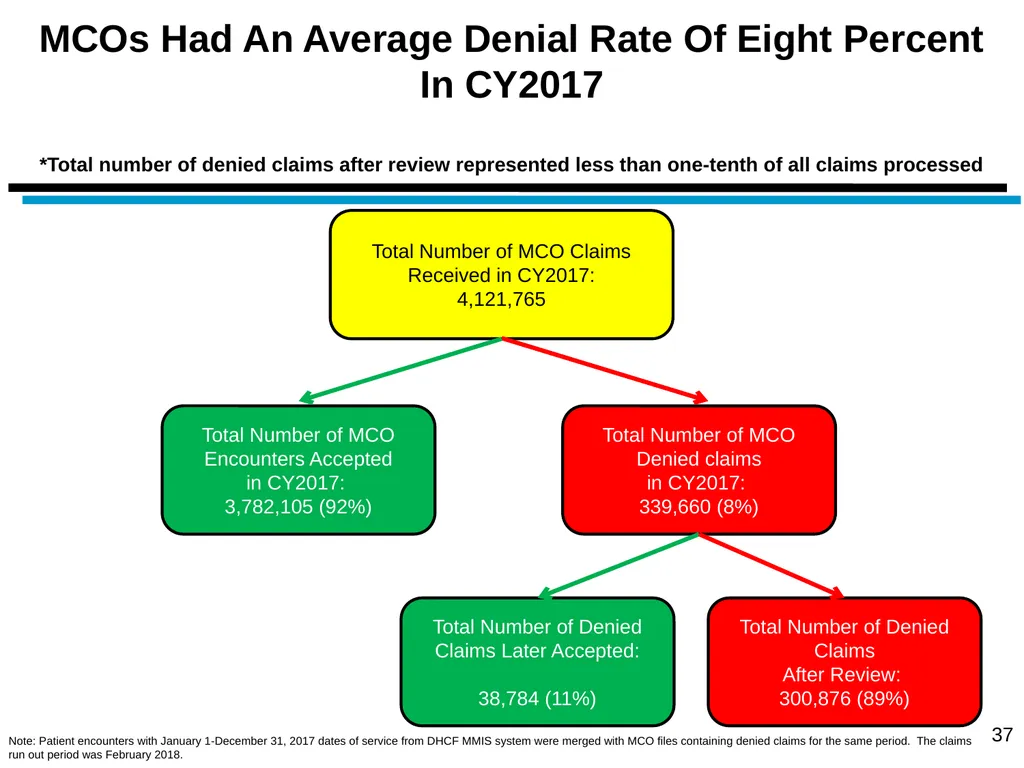
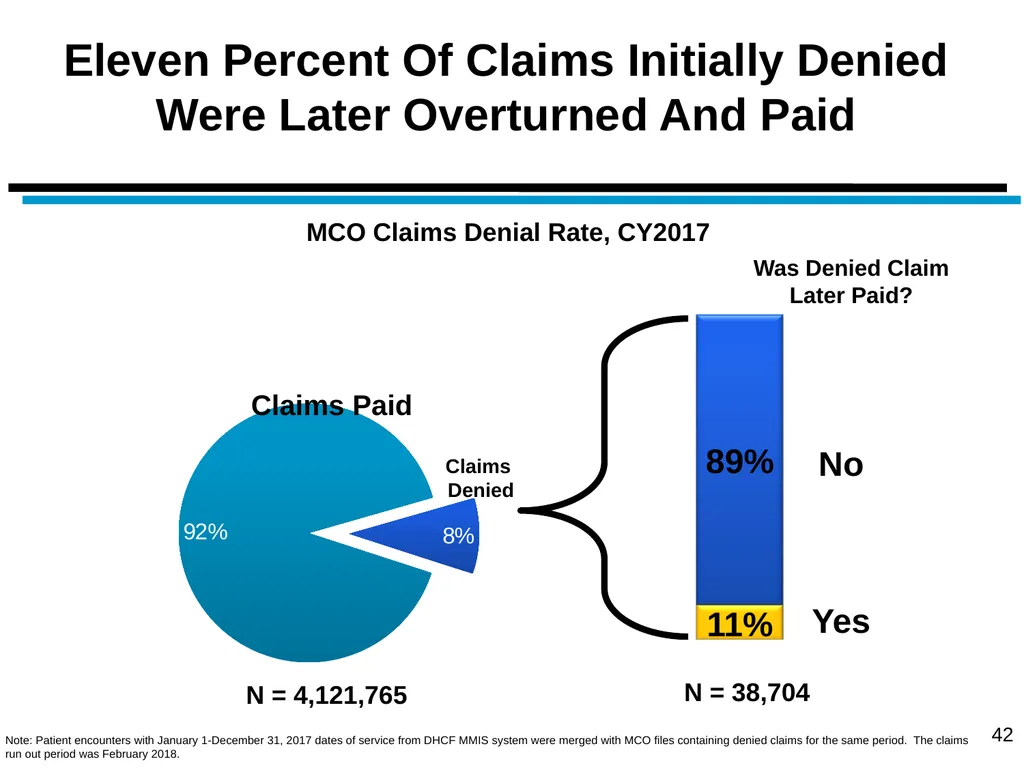
slide37. MCOs Had An Average Denial Rate Of Eight Percent In CY2017 *Total number of denied claims after review represented less than one-tenth of all claims processed Total Number of MCO Encounters Accepted
in CY2017:
3,782,105 (92%) Total Number of Denied Claims Later Accepted:
38,784 (11%) 37 Total Number of MCO Claims
Received in CY2017:
4,121,765 Total Number of MCO Denied claims
in CY2017:
339,660 (8%) Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Total Number of Denied Claims
After Review:
300,876 (89%)<br>
slide38. 38 MedStar And Trusted Denial Rates Were Slightly Above MCO Average Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. Claims Denial Rates For Each Health Plan, CY2017 Total Claims Adjudicated 257,049 626,081 2,318,775 919,860 Average Claims Denial Rate: 8%<br>
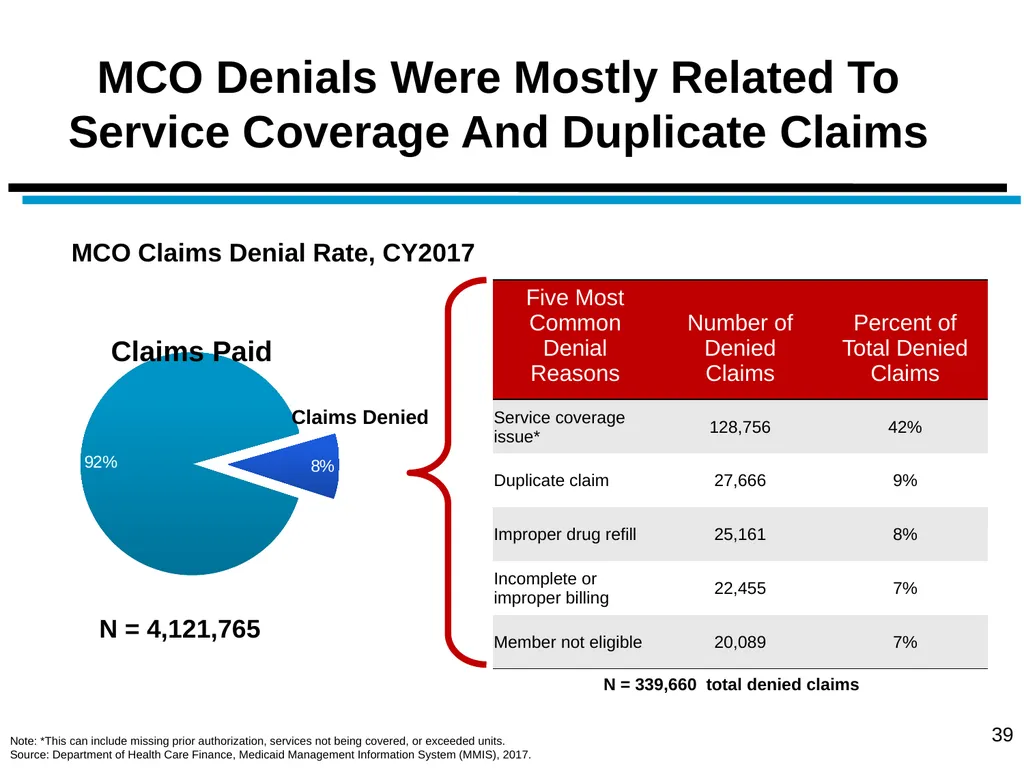
slide39. MCO Denials Were Mostly Related To Service Coverage And Duplicate Claims 39 Note: *This can include missing prior authorization, services not being covered, or exceeded units.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MCO Claims Denial Rate, CY2017 N = 339,660 total denied claims N = 4,121,765 Claims Paid Claims Denied<br>
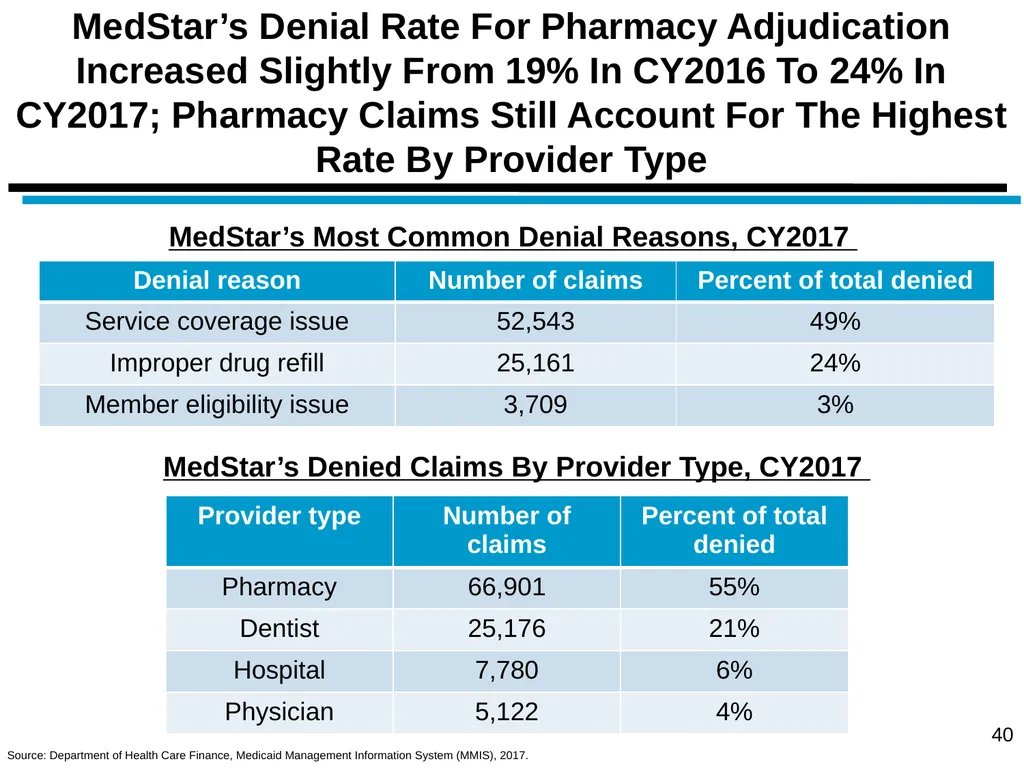
slide40. 40 MedStar’s Denial Rate For Pharmacy Adjudication Increased Slightly From 19% In CY2016 To 24% In CY2017; Pharmacy Claims Still Account For The Highest Rate By Provider Type Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MedStar’s Denied Claims By Provider Type, CY2017 MedStar’s Most Common Denial Reasons, CY2017<br>
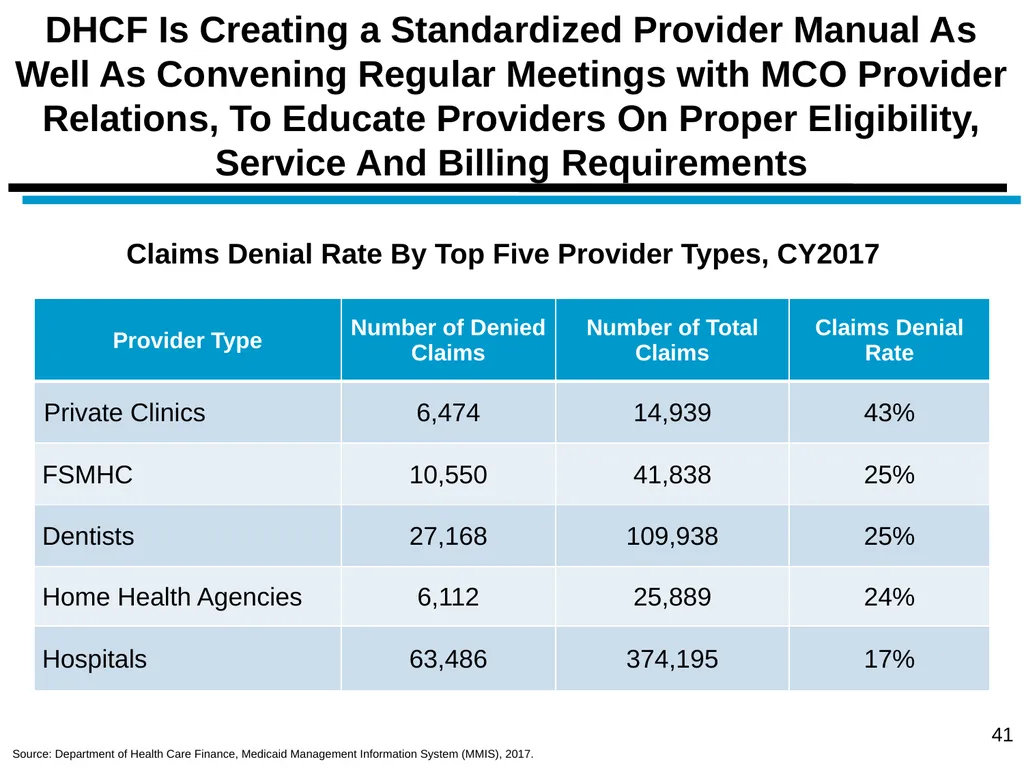
slide41. DHCF Is Creating a Standardized Provider Manual As Well As Convening Regular Meetings with MCO Provider Relations, To Educate Providers On Proper Eligibility, Service And Billing Requirements 41 Claims Denial Rate By Top Five Provider Types, CY2017 Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017.<br>
slide42. Eleven Percent Of Claims Initially Denied Were Later Overturned And Paid 42 MCO Claims Denial Rate, CY2017 N = 4,121,765 N = 38,704 11% 89% Was Denied Claim
Later Paid? No Yes Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Claims Paid Claims
Denied<br>
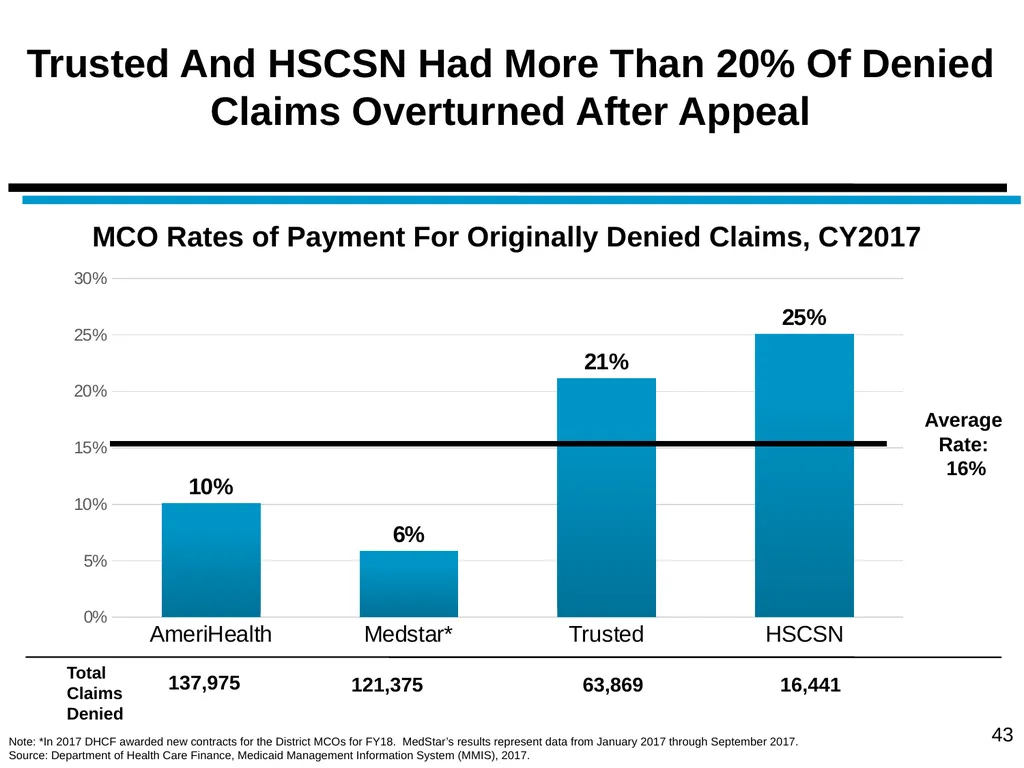
slide43. 43 Trusted And HSCSN Had More Than 20% Of Denied Claims Overturned After Appeal Total Claims
Denied 137,975 121,375 Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MCO Rates of Payment For Originally Denied Claims, CY2017 63,869 16,441 Average
Rate:
16%<br>
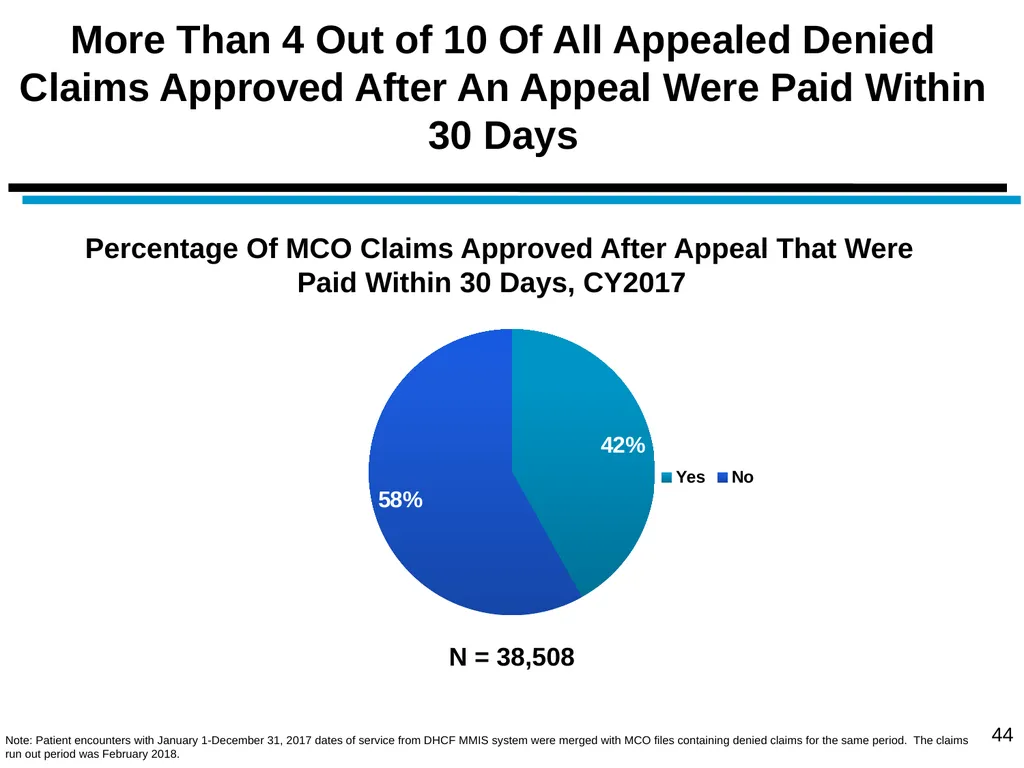
slide44. More Than 4 Out of 10 Of All Appealed Denied Claims Approved After An Appeal Were Paid Within 30 Days 44 N = 38,508 Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Percentage Of MCO Claims Approved After Appeal That Were
Paid Within 30 Days, CY2017<br>
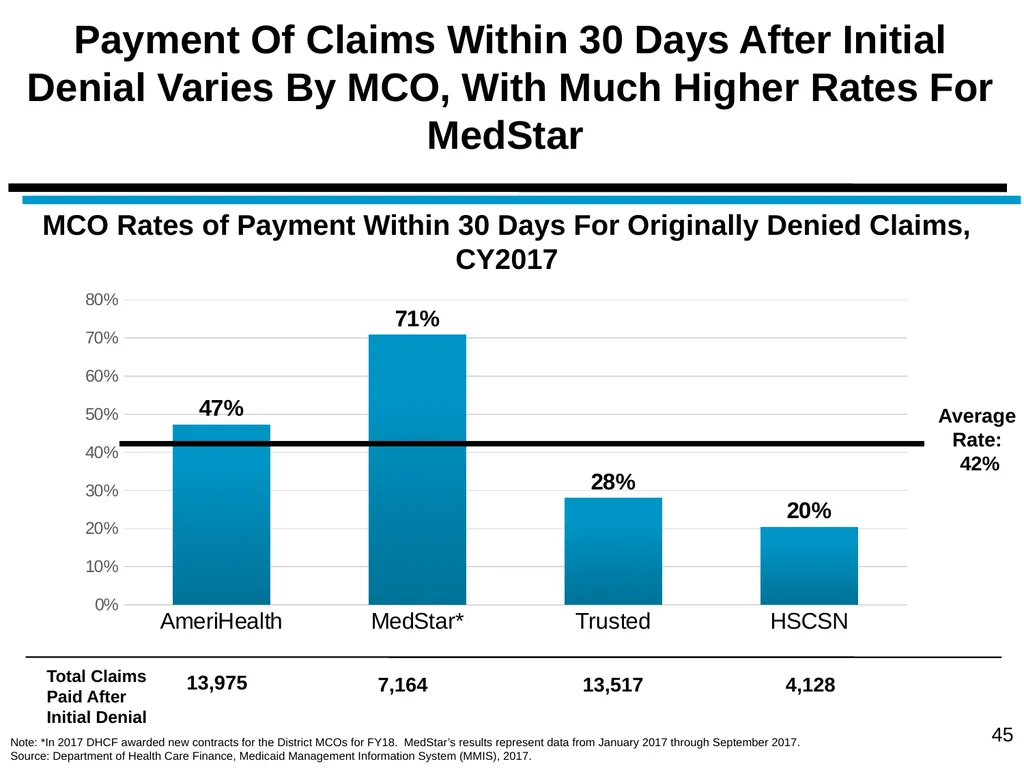
slide45. 45 Payment Of Claims Within 30 Days After Initial Denial Varies By MCO, With Much Higher Rates For MedStar Total Claims Paid After Initial Denial 13,975 7,164 Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MCO Rates of Payment Within 30 Days For Originally Denied Claims, CY2017 13,517 4,128 Average
Rate:
42%<br>
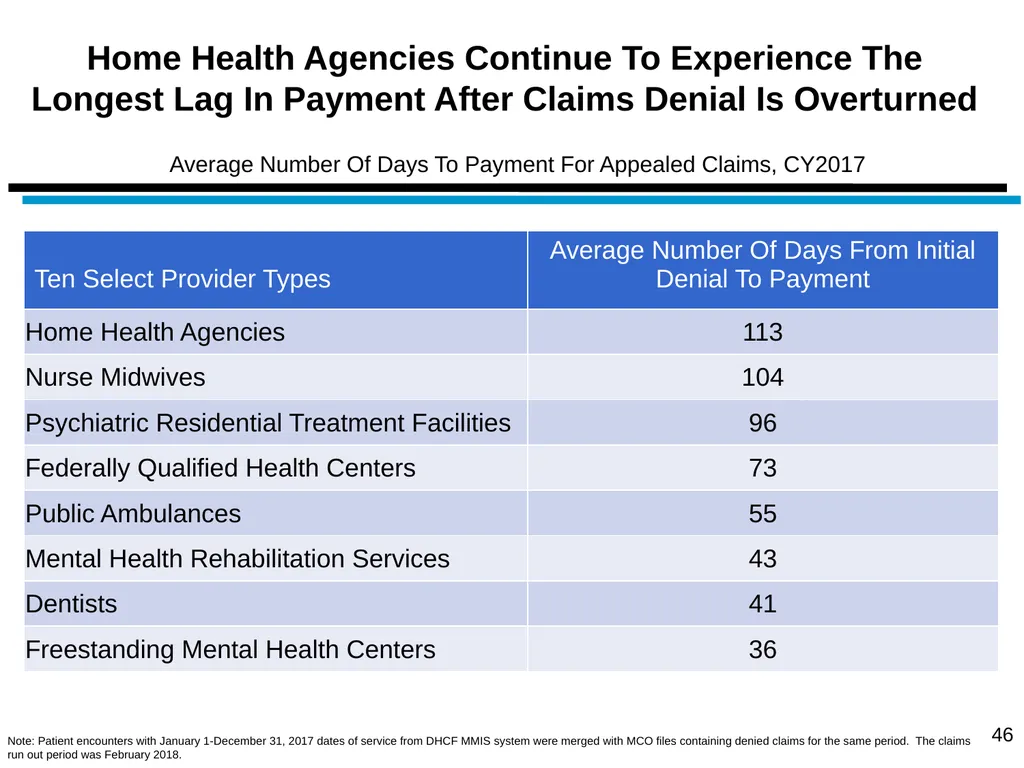
slide46. Home Health Agencies Continue To Experience The Longest Lag In Payment After Claims Denial Is Overturned 46 Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Average Number Of Days To Payment For Appealed Claims, CY2017<br>
slide47. Denial Rates Have Decreased By Half Over A Four Year Period; Timely Payment of Claims Approved After Initial Denial Has Also Decreased By Half 47<br>
slide48. Presentation Outline 48 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization
Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide49. Each Of The Full Risk Plans Spent At Least 85 Percent Of Revenue On Member Medical Expenses 49 Actual MCO Revenue At Target Rate For January 2017 to December 2017 Actual Medical Loss Ratio 92% 86% 8% 6% 8% Admin Expenses Notes: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. MCO revenue does not include investment income, HIPF payments, and DC Exchange/Premium tax revenue. Administrative expenses include all claims adjustment expenses as reported in quarterly DISB filings and self reported quarterly filings, excluding cost containment expenses, HIPF payments and DC Exchange/Premium taxes.
Source: MCO Quarterly Statement filed by the MCOs with the Department of Insurance, Securities, and Banking for the three full risk MCOs and self reported Quarterly statements for shared risk plan, HSCSN 85% 13% Operating
Margin 0.2% 2% 8% 88% 5% 4% 85% 10% $152.9M<br>
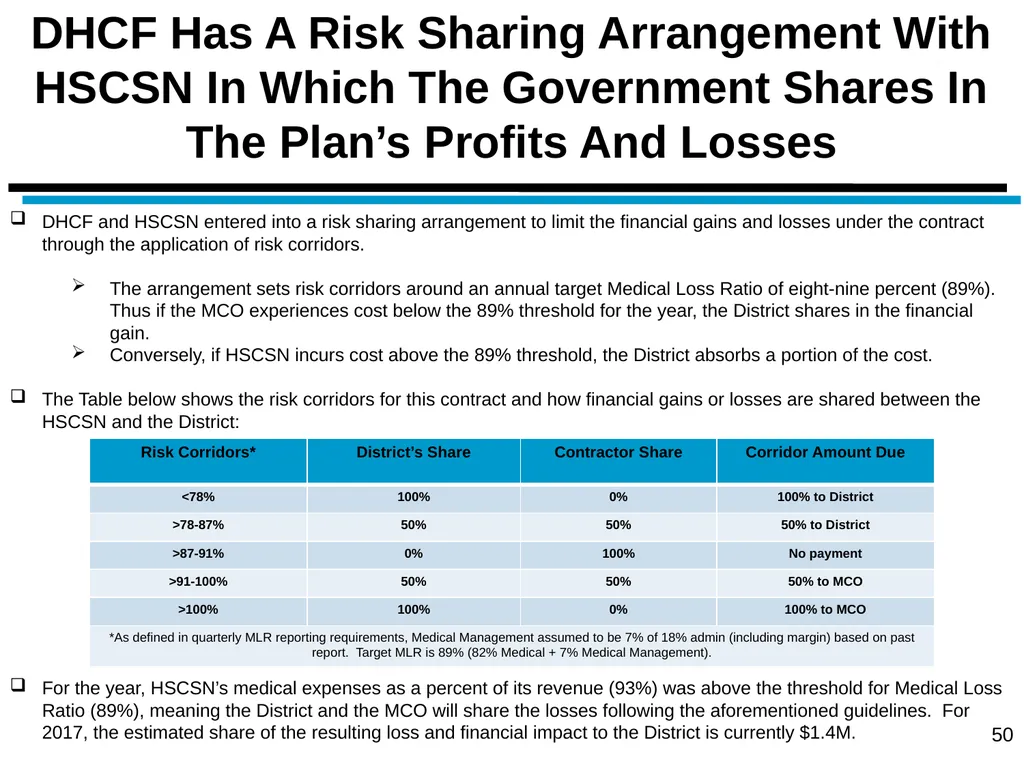
slide50. DHCF Has A Risk Sharing Arrangement With HSCSN In Which The Government Shares In The Plan’s Profits And Losses 50 DHCF and HSCSN entered into a risk sharing arrangement to limit the financial gains and losses under the contract through the application of risk corridors.
The arrangement sets risk corridors around an annual target Medical Loss Ratio of eight-nine percent (89%). Thus if the MCO experiences cost below the 89% threshold for the year, the District shares in the financial gain.
Conversely, if HSCSN incurs cost above the 89% threshold, the District absorbs a portion of the cost.
The Table below shows the risk corridors for this contract and how financial gains or losses are shared between the HSCSN and the District:
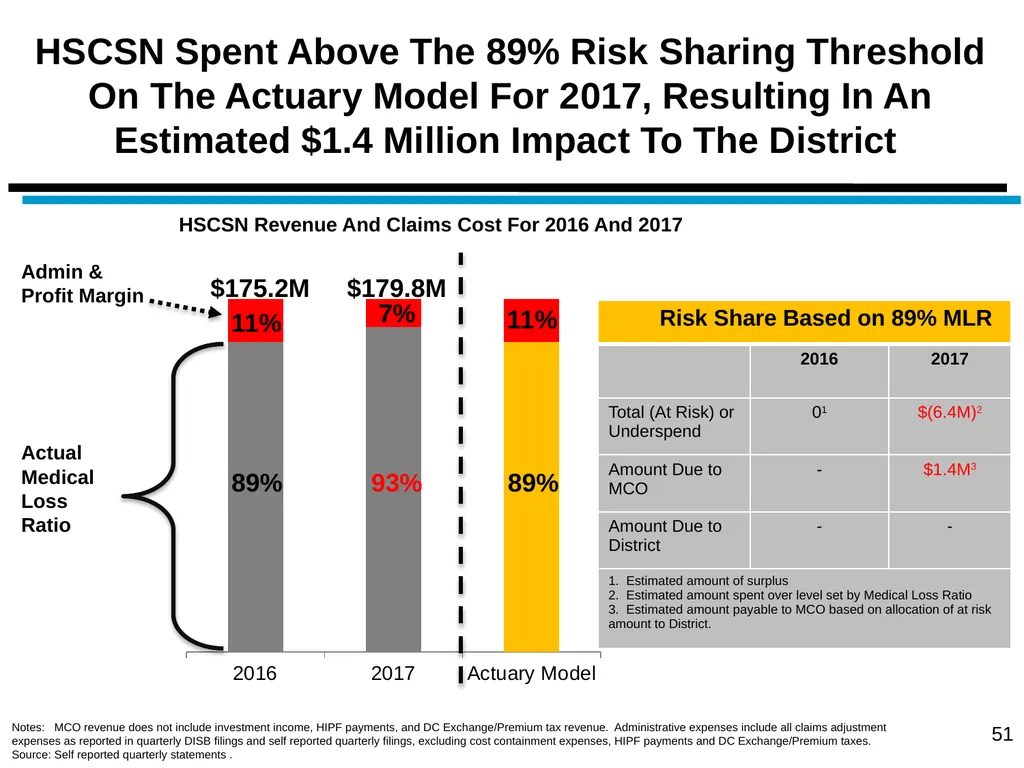
For the year, HSCSN’s medical expenses as a percent of its revenue (93%) was above the threshold for Medical Loss Ratio (89%), meaning the District and the MCO will share the losses following the aforementioned guidelines. For 2017, the estimated share of the resulting loss and financial impact to the District is currently $1.4M.<br>
slide51. HSCSN Spent Above The 89% Risk Sharing Threshold On The Actuary Model For 2017, Resulting In An Estimated $1.4 Million Impact To The District 51 HSCSN Revenue And Claims Cost For 2016 And 2017 Actual Medical Loss Ratio 93% Admin & Profit Margin Notes: MCO revenue does not include investment income, HIPF payments, and DC Exchange/Premium tax revenue. Administrative expenses include all claims adjustment expenses as reported in quarterly DISB filings and self reported quarterly filings, excluding cost containment expenses, HIPF payments and DC Exchange/Premium taxes.
Source: Self reported quarterly statements . 89% 7% 89% $179.8M $175.2M<br>
slide52. A Slight Decline In Year-Over-Year Medical Expenses For Adults And Flat Trends Were Observed For Children In The Medicaid Program, But, Overall Differences For Adults Vary Significantly 52 $312.20 $376.47 $206.90 $214.13 $203.81 Medicaid Adult And Children Medical Expenses Per-Member, Per-Month, January 1, 2017
to December 31, 2017 Notes: *Incurred from January 1, 2017 to December 31, 2017 for AmeriHealth and Trusted, incurred from January 1, 2017 to September 30, 2017 for MedStar, and incurred from October 1, 2017 to December 31, 2017 for Amerigroup; all claims paid as of January 31, 2018. IBNR is estimated based on historical payment lags. This short runout period results in a high degree of uncertainty for IBNR estimates and final results will differ. Children defined as person up to age 21 in this analysis for the three full risk MCOSs.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Percent Change From 2016 N/A* 0% -8% N/A* +4% 0% $361.45 -2% $208.77 0% $291.33 $193.90 -3% -6%<br>
slide53. The Double Digit Growth In Medical Expenses For Alliance Exacerbated By DHCF’s Need To Move Most Of The Pharmacy Cost Of This Program Off Of The Department Of Defense Discount Program And Into The Managed Care Benefit In 2016 Continues To Accelerate In 2017 53 $322.26 $341.84 Alliance Adult Medical Expenses Per-Member, Per-Month, January 1, 2017 to December 31, 2017 Notes: *Incurred from January 1, 2017 to December 31, 2017 for AmeriHealth and Trusted, incurred from January 1, 2017 to September 30, 2017 for MedStar, and incurred from October 1, 2017 to December 31, 2017 for Amerigroup; all claims paid as of January 31, 2018. IBNR is estimated based on historical payment lags. This short runout period results in a high degree of uncertainty for IBNR estimates and final results will differ. *Amerigroup began operations in October 2017.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Percent Change From 2016 N/A* +50% +26% $345.91 +31% +18%<br>
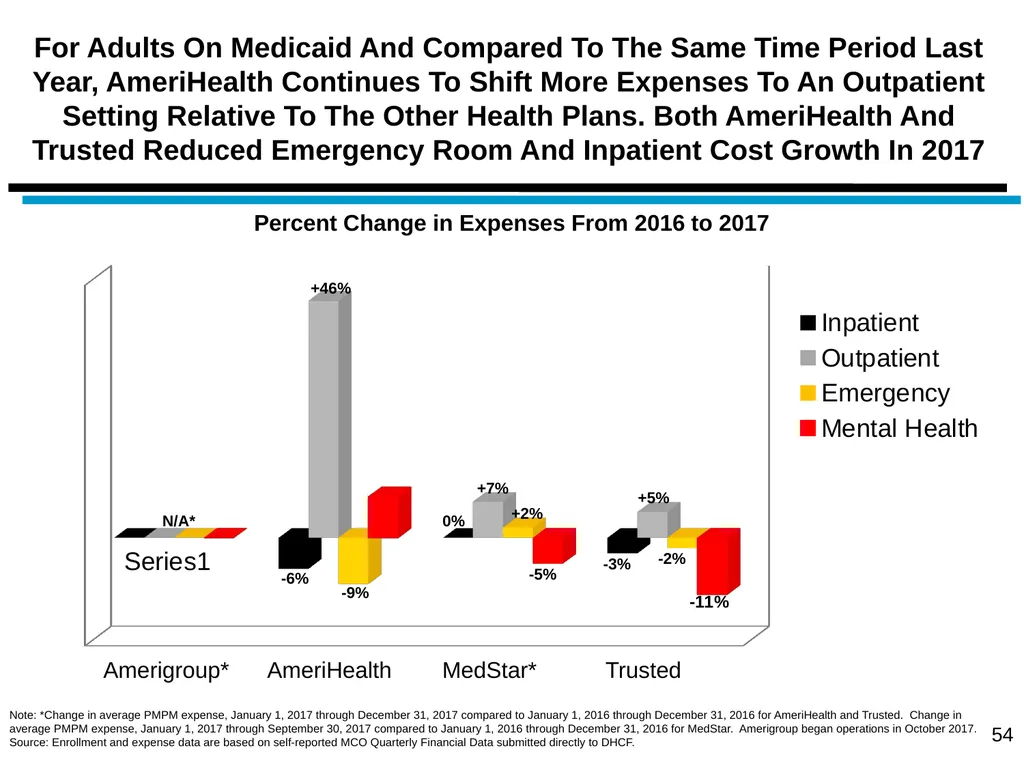
slide54. For Adults On Medicaid And Compared To The Same Time Period Last Year, AmeriHealth Continues To Shift More Expenses To An Outpatient Setting Relative To The Other Health Plans. Both AmeriHealth And Trusted Reduced Emergency Room And Inpatient Cost Growth In 2017 54 AmeriHealth MedStar* Trusted N/A* -9% +2% +46% +5% -6% 0% -2% +7% -5% Percent Change in Expenses From 2016 to 2017 Note: *Change in average PMPM expense, January 1, 2017 through December 31, 2017 compared to January 1, 2016 through December 31, 2016 for AmeriHealth and Trusted. Change in average PMPM expense, January 1, 2017 through September 30, 2017 compared to January 1, 2016 through December 31, 2016 for MedStar. Amerigroup began operations in October 2017.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Amerigroup* -3%<br>
slide55. For Children On Medicaid, As Compared To Prior Years, Trusted Reported Significant Reductions In Inpatient Costs While AmeriHealth Reduced Its Emergency Costs In 2017 55 AmeriHealth MedStar* Trusted N/A* -12% +28% +17% -14% Percent Change in Expenses From 2016 to 2017 Notes: *Change in average PMPM expense, January 1, 2017 through December 31, 2017 compared to January 1, 2016 through December 31, 2016 for AmeriHealth and Trusted. Change in average PMPM expense, January 1, 2017 through September 30, 2017 compared to January 1, 2016 through December 31, 2016 for MedStar. Children defined as person up to age 21 in this analysis for the three full risk MCOSs and age 26 for HSCSN. Amerigroup began operations in October 2017.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. HSCSN +21% +5% -24% +15% -9% -6% +6% -1% -15% +23% +8% -13% +47% +17% -5% +8% Amerigroup*<br>
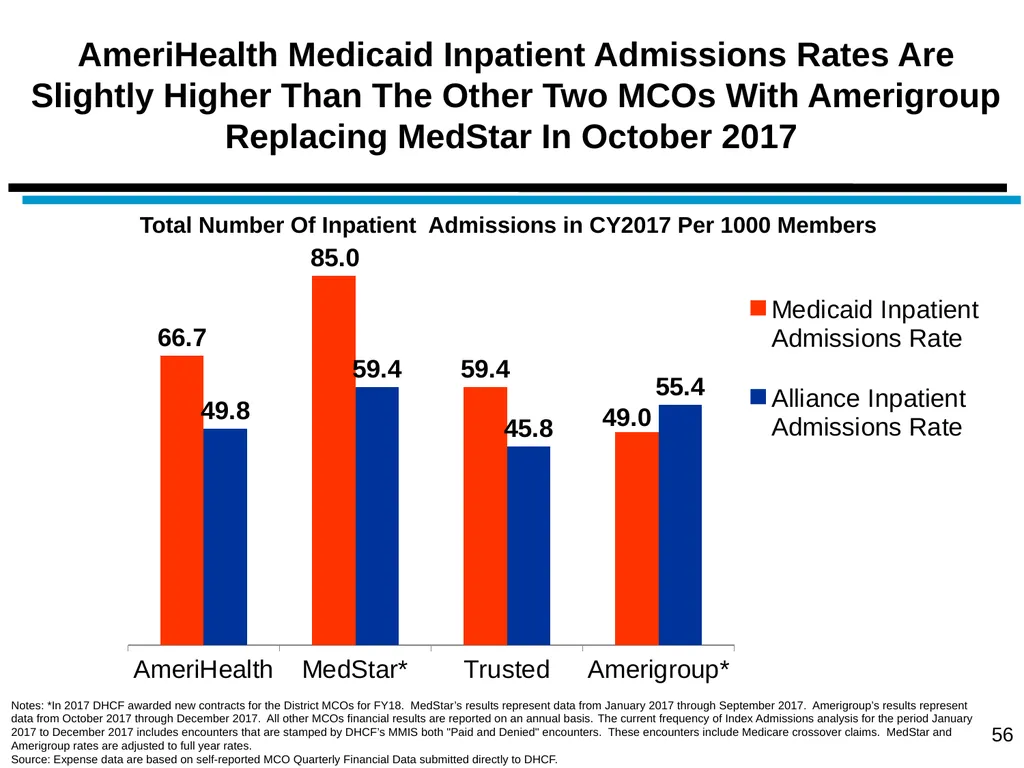
slide56. AmeriHealth Medicaid Inpatient Admissions Rates Are Slightly Higher Than The Other Two MCOs With Amerigroup Replacing MedStar In October 2017 56 Total Number Of Inpatient Admissions in CY2017 Per 1000 Members Notes: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017. Amerigroup’s results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. The current frequency of Index Admissions analysis for the period January 2017 to December 2017 includes encounters that are stamped by DHCF’s MMIS both "Paid and Denied" encounters. These encounters include Medicare crossover claims. MedStar and Amerigroup rates are adjusted to full year rates.
Source: Expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF.<br>
slide57. For HSCSN The Growth In Its Per-Member, Per-Month Medical Expenses For Children From 2016 To 2017 Spiked Due To High Cost Specialty Drugs And Significant Q4 Outpatient Claims 57 Medicaid Children Medical Expenses Per-Member, Per-Month,
December 2015 to December 2017 Notes: Expenses incurred from January 1, 2017 to December 31, 2017 and paid as of January 31, 2018. The expenses do not reflect adjustments to account for IBNR claims. Children defined as person up to age 21 in this analysis for the three full risk MCOs and 26 for HSCSN
Source: Enrollment and expense data is based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. 2 Percent Cost Growth Compared To 2015 $2,082 17 Percent Cost Growth From December 2015 $2,386 15 Percent Cost Growth Compared To 2016<br>
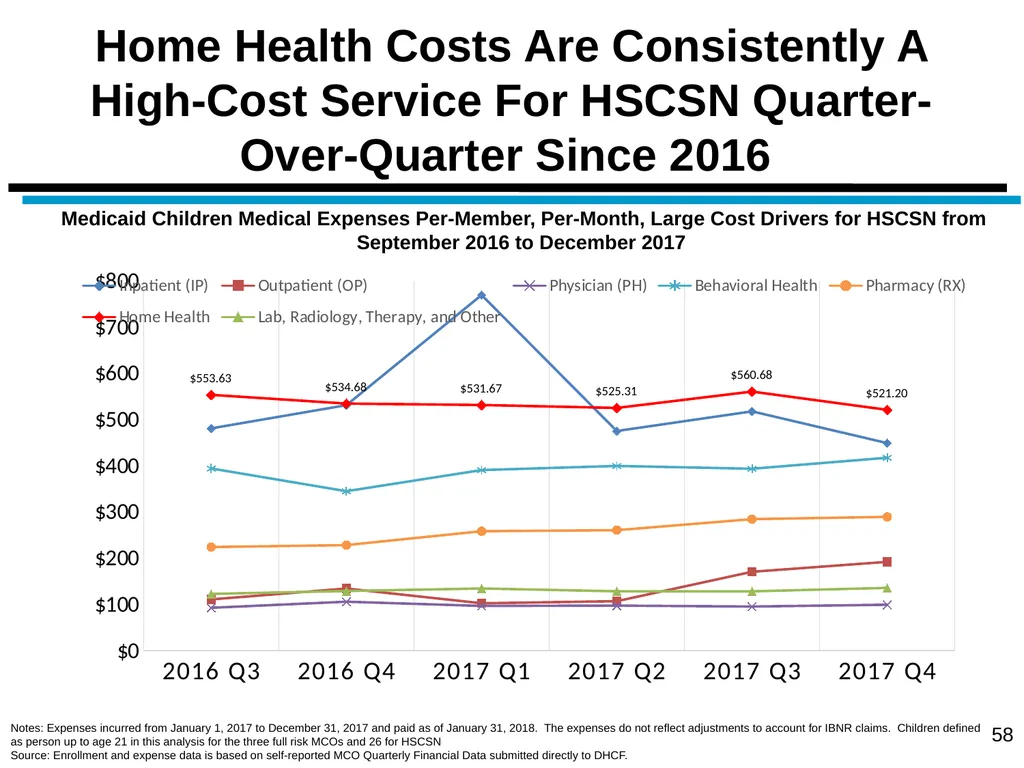
slide58. Home Health Costs Are Consistently A High-Cost Service For HSCSN Quarter-Over-Quarter Since 2016 58 Medicaid Children Medical Expenses Per-Member, Per-Month, Large Cost Drivers for HSCSN from
September 2016 to December 2017 Notes: Expenses incurred from January 1, 2017 to December 31, 2017 and paid as of January 31, 2018. The expenses do not reflect adjustments to account for IBNR claims. Children defined as person up to age 21 in this analysis for the three full risk MCOs and 26 for HSCSN
Source: Enrollment and expense data is based on self-reported MCO Quarterly Financial Data submitted directly to DHCF.<br>
slide59. The Physician Visit Rates For Children Are Consistently Above Average for HSCSN and AmeriHealth in CY2017 59 Medicaid Quarterly Physician Care Visit Rates For Children Enrolled In Managed Care,
April 2015 to December 2017 Note: In each quarter, only members who were enrolled with the MCO for three months continuously during the period and had 12 months of continuous Medicaid participation
from that quarter are included in this analysis. *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017. Amerigroup’s results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. The 30 day timely payment requirement only applies to “clean claims” that meet the requirement for payment.
Source Encounter data submitted by MCOs to DHCF.<br>
slide60. Well-Child Visits For Children Have Increased For Nearly All Plans From CY2016 To CY2017, Notably For HSCSN And AmeriHealth 60 Medicaid Well Child Visit Rates For Children Enrolled In Managed Care, April 2015 to December 2017 Note: In each quarter, only members who were enrolled with the MCO for three months continuously during the period and had 12 months of continuous Medicaid participation
from that quarter are included in this analysis. *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s 2017 results represent data from January 2017 through
September 2017. Amerigroup’s 2017 results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Encounter data submitted by MCOs to DHCF.<br>
slide61. The Physician Visit Rate For Adults Is Mostly Unchanged From CY2016, With Trusted Showing A Slight Decrease In Its Rates in Early CY2017 61 Medicaid Quarterly Physician Care Visit Rates For Adults Who Were Enrolled In Managed Care,
April 2015 to December 2017 Note: In each quarter, only members who were enrolled with the MCO for three months continuously during the period and had 12 months of continuous Medicaid participation
from that quarter are included in this analysis. *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results for 2017 represent data from January 2017 through September 2017. Amerigroup’s results for 2017 represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Encounter data submitted by MCOs to DHCF.<br>
slide62. The Utilization Rate For Medicaid-Funded Mental Health Rehabilitation Services Was Lower For Children In CY2017, Likely Due To The Recent Closure Of Several Key Provider Sites 62 Percent of MCO Members Receiving Mental Health Rehabilitation Services Through MCOs, CY2017 Note: The data presented above are based on MCO paid encounters for January1 – December 31, 2017, with a claims run out period through February 2018.
Source: Encounter data submitted by MCOs to DHCF. N = 212,541 N = 134,672 N = 77,869 N = 213,133 N = 136,721 N = 76,412<br>
slide63. However, The MCO Penetration Rate For Beneficiaries Who Received Any Mental Health Services in CY2017 Is Consistent With Rates From CY2016 63 Percent of MCO Members Receiving Any Mental Health Services Through The MCOs, CY2017 Note: The data presented above are based on MCO paid encounters from January 1 – December 31, 2017, with a claims run out period through February 2018.
Source: Encounter data submitted by MCOs to DHCF. N = 212,541 N = 134,672 N = 77,869 N = 213,133 N = 136,721 N = 76,412<br>
slide64. Overall On A Per-Member Per-Month (PMPM) Basis MCOs Reduced Spending On Medicaid-Funded Mental Health Services For Both Children And Adults With The Exception Of Trusted’s Child Population And AmeriHealth’s Adults 64 Adult PMPM Spending The Per-Member Per-Month MCO Expenses For Behavioral Health Services,
January 2017 to December 2017 Notes: *Incurred from January 1, 2017 to December 31, 2017 for AmeriHealth and Trusted, incurred from January 1, 2017 to September 30, 2017 for MedStar, and incurred from October 1, 2017 to December 31, 2017 for Amerigroup; all claims paid as of January 31, 2018. IBNR is estimated based on historical payment lags. This short runout period results in a high degree of uncertainty for IBNR estimates and final results will differ.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Children PMPM Spending MCO Spending Change From 2016<br>
slide65. Presentation Outline 65 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program
P4P Benchmarks<br>
slide66. Achieving high value in health care for Medicaid and Alliance beneficiaries is a preeminent goal of DHCF’s managed care program.
The District’s three managed care plans are expected to increase their members’ health care and improve outcomes per dollar spent through aggressive care coordination and health care management.
After reviewing several years worth of data, DHCF can now more closely examine the following performance indicators for each of the District’s three MCOs:
Emergency room utilization for non-emergency conditions.
Potentially preventable hospitalizations – admissions which could have been avoided with access to quality primary and preventative care.
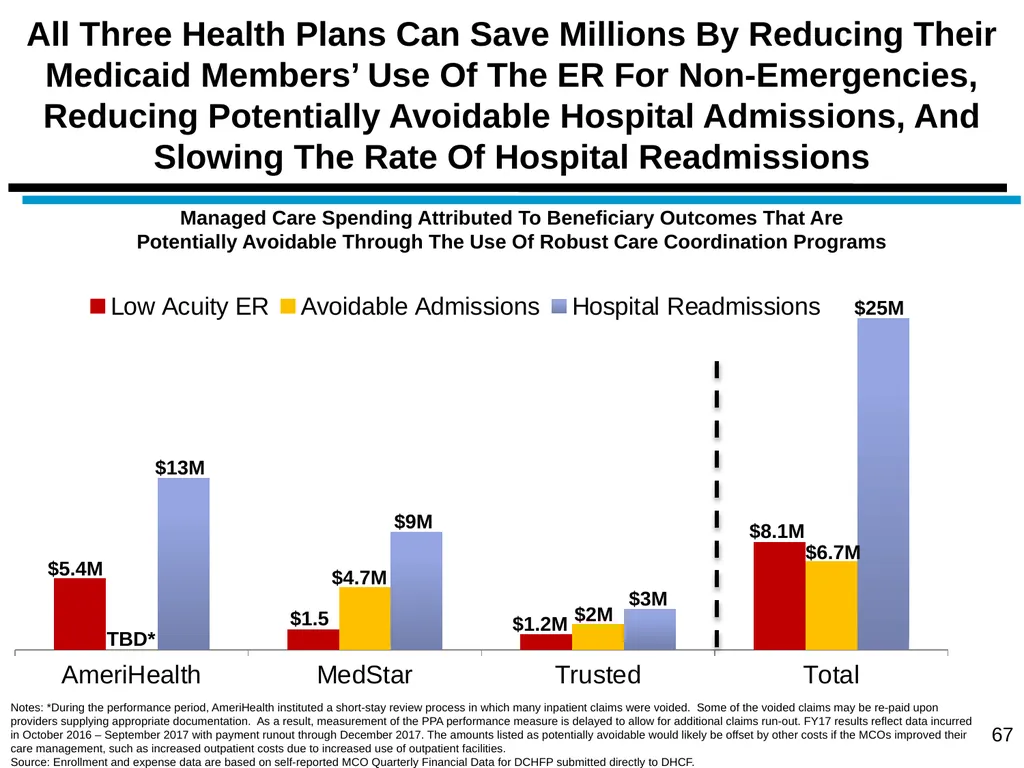
Hospital readmissions for problems related to the diagnosis which prompted a previous and recent – within 30 days – hospitalization. DHCF Relies Upon Several Metrics To Quantitatively Assess The Efforts By The Health Plans To Coordinate Enrollee Care 66<br>
slide67. All Three Health Plans Can Save Millions By Reducing Their Medicaid Members’ Use Of The ER For Non-Emergencies, Reducing Potentially Avoidable Hospital Admissions, And Slowing The Rate Of Hospital Readmissions 67 $5.4M Notes: *During the performance period, AmeriHealth instituted a short-stay review process in which many inpatient claims were voided. Some of the voided claims may be re-paid upon providers supplying appropriate documentation. As a result, measurement of the PPA performance measure is delayed to allow for additional claims run-out. FY17 results reflect data incurred in October 2016 – September 2017 with payment runout through December 2017. The amounts listed as potentially avoidable would likely be offset by other costs if the MCOs improved their care management, such as increased outpatient costs due to increased use of outpatient facilities.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data for DCHFP submitted directly to DHCF. TBD* $13M $1.5 $4.7M $9M $1.2M $2M $3M $8.1M $6.7M $25M Managed Care Spending Attributed To Beneficiary Outcomes That Are Potentially Avoidable Through The Use Of Robust Care Coordination Programs<br>
slide68. In Total Approximately $40 Million In Managed Care Expenses Were Potentially Avoidable* 68 Notes: Low acuity non-emergent visits are emergency room visits that could have been potentially avoided, identified using a list of diagnosis applied to outpatient data. Avoidable admissions are identified using a set of prevention quality measures that are applied to discharge data. Readmissions represent inpatient visits that within 30 days of a qualifying initial inpatient admissions. *The amounts listed as potentially avoidable would likely be offset by other costs if the MCOs improved their care management, such as increased outpatient costs due to increased use of outpatient facilities.
Source: Mercer analysis of MCO Encounter data for DCHFP reported by the MCOs to DHCF. Patient Metrics Low-Acuity
ER Use Avoidable
Admissions Hospital
Readmissions 63% 17% 57% 27% Comparison Of MCO Potentially Avoidable Spending 2016 To 2017<br>
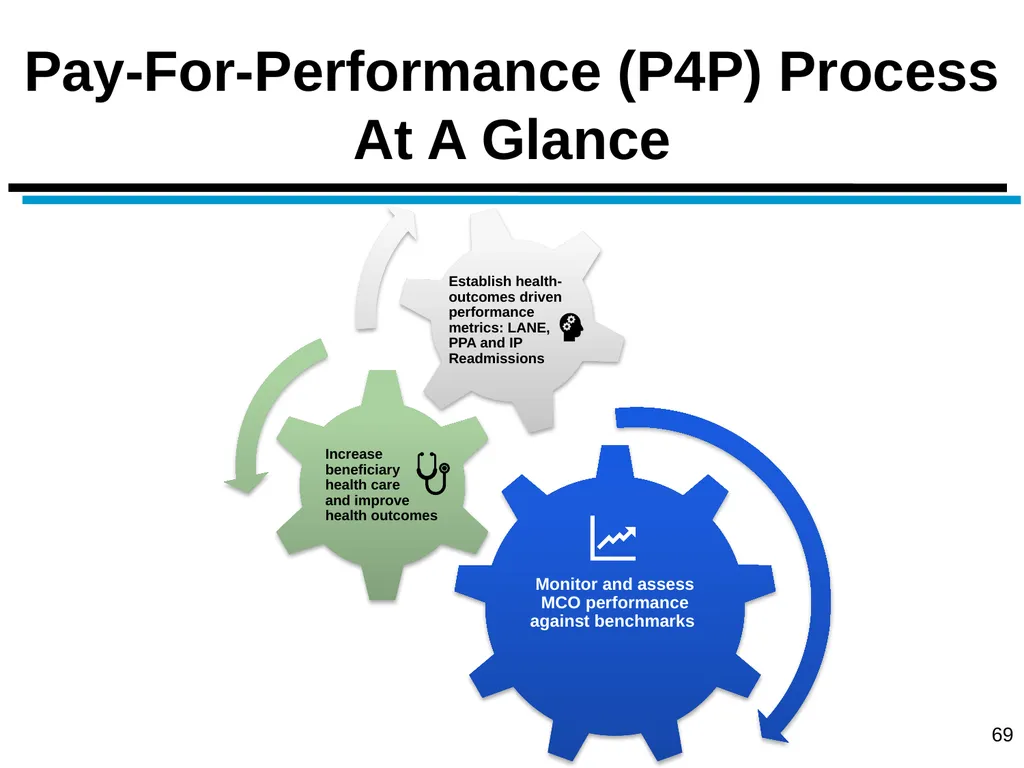
slide69. Pay-For-Performance (P4P) Process At A Glance 69<br>
slide70. Beginning in October 2016, DHCF’s three full-risk MCOs were required to meet performance goals in order to receive their full capitated payment rate.
These performance goals require the MCOs to reduce the incidence of the following three patient outcomes for the DCHFP population:
Potentially preventable admissions (PPA).
Low acuity non-emergent (LANE) visits.
30-day hospital readmissions for all-causes. In FY2017, DHCF Launched Pay-For-Performance Program As An Incentive For MCOs To Address Care Coordination Problems 70<br>
slide71. The program is funded through a two-percent (2%) withhold of each MCO’s actuarially sound capitation payments for non-delivery DCHFP rate cells for the corresponding period.
The 2% withhold is the profit margin for each MCO that is factored into the base per-member, per-month payment rate. Year 1 P4P results are based on FY17 (October 2016 – September 2017) experience compared to the Year 1 baseline.
The baseline period used to set the target remains April 1, 2015 through March 31, 2016, with runout through September 2016. MCOs must meet the minimum threshold for improvement for all three performance measures in order to earn any portion of the withhold. Program Structure Is Based On Cash Withhold 71<br>
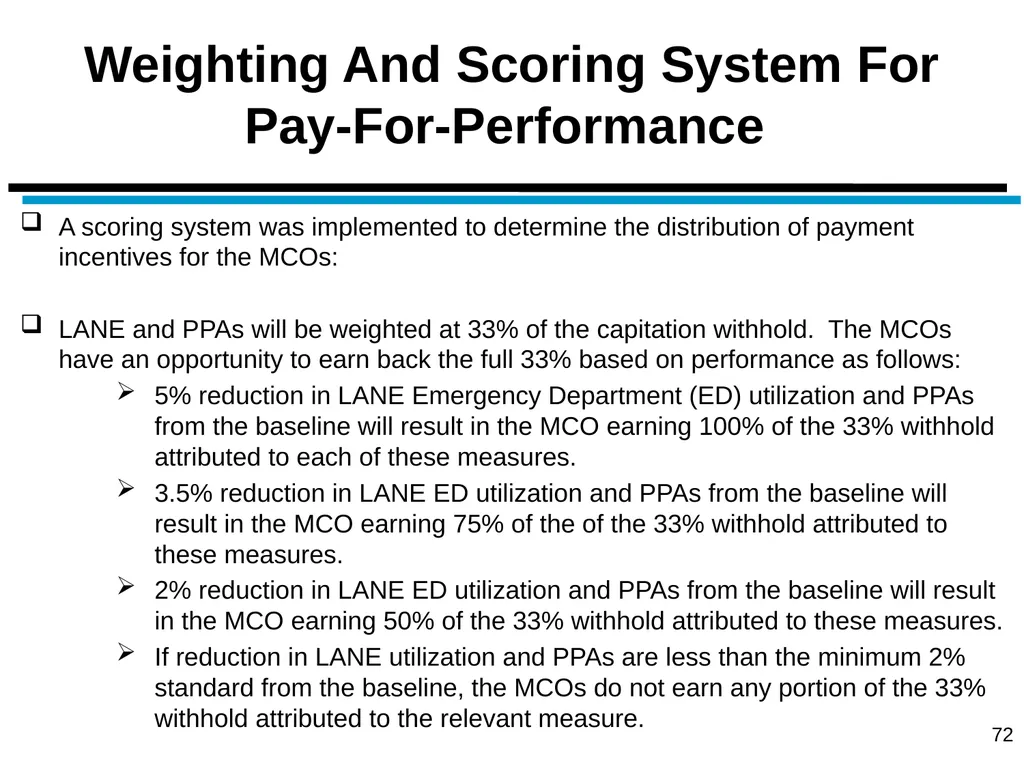
slide72. A scoring system was implemented to determine the distribution of payment incentives for the MCOs:
LANE and PPAs will be weighted at 33% of the capitation withhold. The MCOs have an opportunity to earn back the full 33% based on performance as follows:
5% reduction in LANE Emergency Department (ED) utilization and PPAs from the baseline will result in the MCO earning 100% of the 33% withhold attributed to each of these measures.
3.5% reduction in LANE ED utilization and PPAs from the baseline will result in the MCO earning 75% of the of the 33% withhold attributed to these measures.
2% reduction in LANE ED utilization and PPAs from the baseline will result in the MCO earning 50% of the 33% withhold attributed to these measures.
If reduction in LANE utilization and PPAs are less than the minimum 2% standard from the baseline, the MCOs do not earn any portion of the 33% withhold attributed to the relevant measure. Weighting And Scoring System For Pay-For-Performance 72<br>
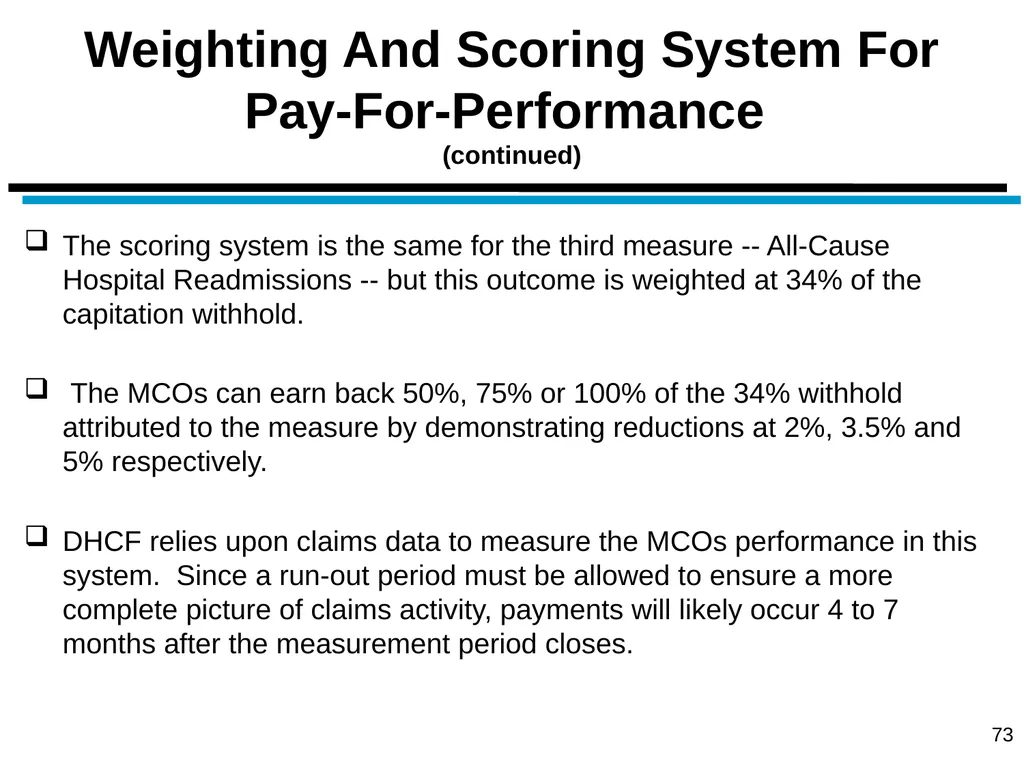
slide73. The scoring system is the same for the third measure -- All-Cause Hospital Readmissions -- but this outcome is weighted at 34% of the capitation withhold.
The MCOs can earn back 50%, 75% or 100% of the 34% withhold attributed to the measure by demonstrating reductions at 2%, 3.5% and 5% respectively.
DHCF relies upon claims data to measure the MCOs performance in this system. Since a run-out period must be allowed to ensure a more complete picture of claims activity, payments will likely occur 4 to 7 months after the measurement period closes. Weighting And Scoring System For Pay-For-Performance (continued) 73<br>
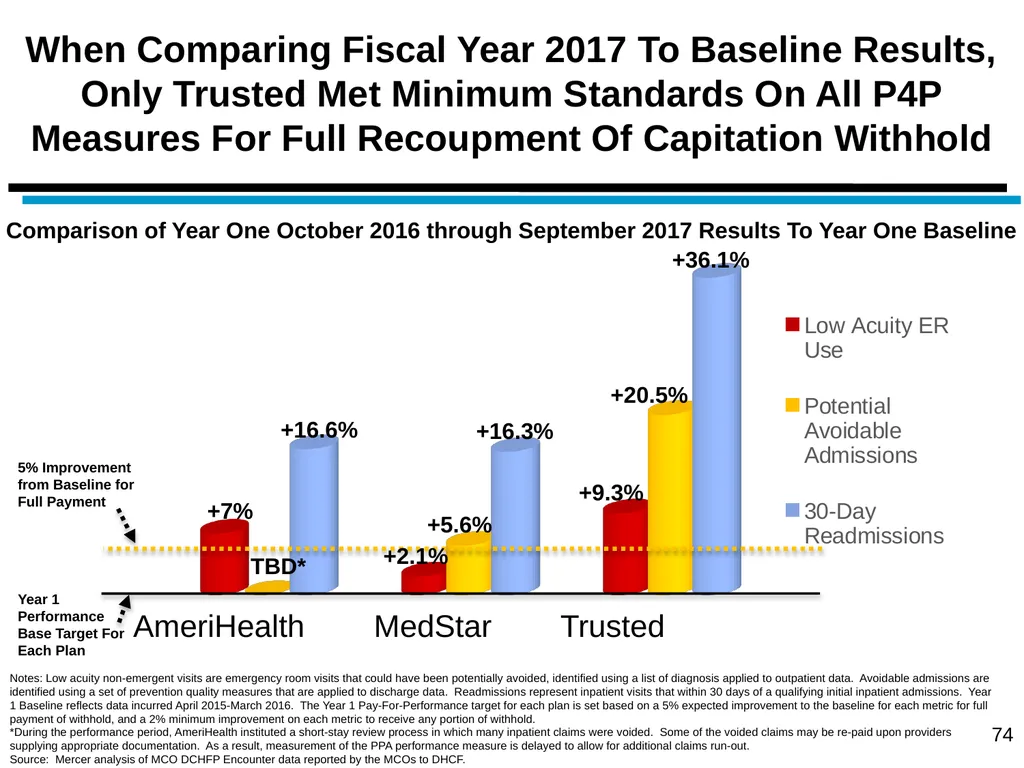
slide74. When Comparing Fiscal Year 2017 To Baseline Results, Only Trusted Met Minimum Standards On All P4P Measures For Full Recoupment Of Capitation Withhold 74 AmeriHealth MedStar Trusted +7% Comparison of Year One October 2016 through September 2017 Results To Year One Baseline Notes: Low acuity non-emergent visits are emergency room visits that could have been potentially avoided, identified using a list of diagnosis applied to outpatient data. Avoidable admissions are identified using a set of prevention quality measures that are applied to discharge data. Readmissions represent inpatient visits that within 30 days of a qualifying initial inpatient admissions. Year 1 Baseline reflects data incurred April 2015-March 2016. The Year 1 Pay-For-Performance target for each plan is set based on a 5% expected improvement to the baseline for each metric for full payment of withhold, and a 2% minimum improvement on each metric to receive any portion of withhold.
*During the performance period, AmeriHealth instituted a short-stay review process in which many inpatient claims were voided. Some of the voided claims may be re-paid upon providers supplying appropriate documentation. As a result, measurement of the PPA performance measure is delayed to allow for additional claims run-out.
Source: Mercer analysis of MCO DCHFP Encounter data reported by the MCOs to DHCF. TBD* +16.6% +5.6% +16.3% +9.3% +20.5% +36.1% Year 1 Performance Base Target For Each Plan 5% Improvement from Baseline for Full Payment +2.1%<br>
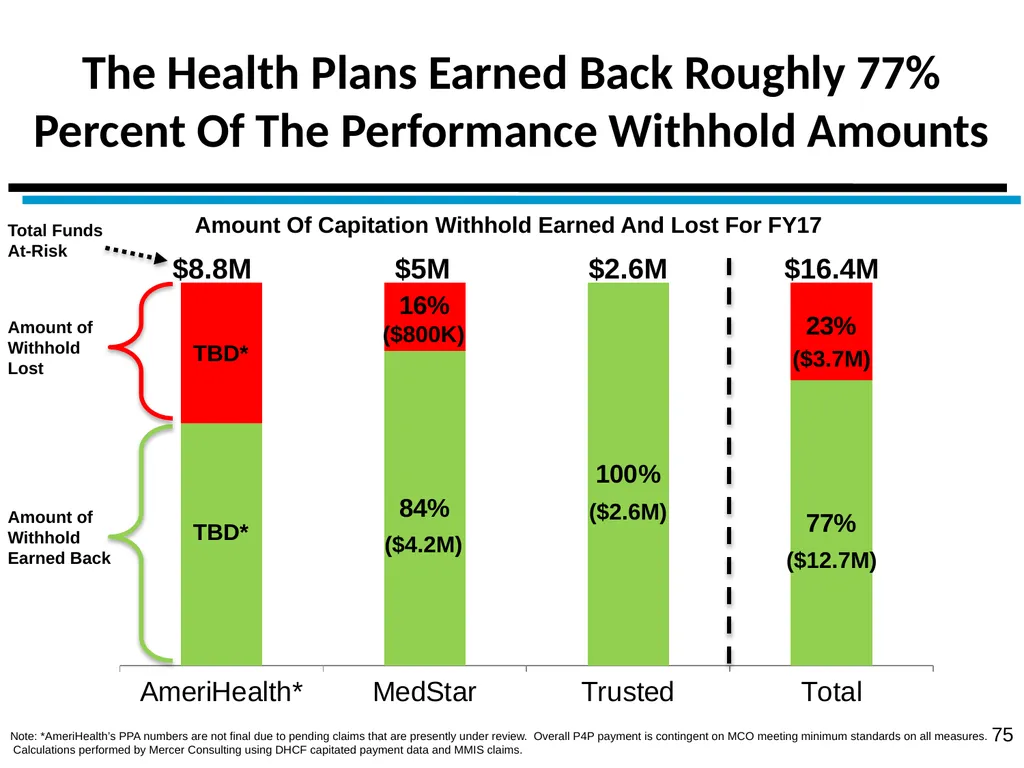
slide75. Amount of Withhold Earned Back Amount of Withhold Lost Note: *AmeriHealth’s PPA numbers are not final due to pending claims that are presently under review. Overall P4P payment is contingent on MCO meeting minimum standards on all measures. Calculations performed by Mercer Consulting using DHCF capitated payment data and MMIS claims. The Health Plans Earned Back Roughly 77% Percent Of The Performance Withhold Amounts $8.8M $5M $2.6M $16.4M TBD* ($4.2M) ($2.6M) ($12.7M) TBD* ($800K) ($3.7M) Total Funds At-Risk 75 Amount Of Capitation Withhold Earned And Lost For FY17<br>
slide76. Questions and Comments<br>
Washington DC Issued by:
Department of Health Care Finance<br>
slide2. Presentation Outline 2 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s MCOs
The Administrative Performance of the District’s Health
Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide3. Managed Care Represents DHCF’s Largest Provider Expenditure Department of Health Care Finance’s (DHCF) managed care program is the largest single expenditure in the agency’s budget consisting of the Medicaid and Alliance publicly-funded health insurance programs.
As of December 2017, nearly 198,662 Medicaid beneficiaries and just over 16,005 Alliance enrollees were assigned to one of the following Managed Care Organizations (MCO):
Amerigroup DC, Inc. (Amerigroup)*
AmeriHealth Caritas DC (AmeriHealth)
MedStar Family Choice (MedStar)*
Trusted Health Plan (Trusted)
Health Services for Children With Special Needs (HSCSN)
In 2017, all five MCOs offered comprehensive benefits. Four of these MCOs – Amerigroup, AmeriHealth, MedStar, and Trusted -- operated under full risk-based contracts while HSCSN worked under a risk sharing arrangement with the District.
The MCOs incurred costs of over $1.1 billion on MCO services in 2017. A little more than $919 million of this amount funded the full risk-based contracts signed by Amerigroup, AmeriHealth, MedStar, and Trusted, while approximately $180 million funded the risk sharing contract with HSCSN. 3 *In 2017, DHCF awarded contracts for the upcoming FY18 contract year for the three full risk-based MCOs. Two of the three MCOs -- AmeriHealth and Trusted -- are returning MCOs, with one newly-awarded MCO as of October 2017 - Amerigroup.<br>
slide4. History of MCO Performance Review Following the award of the contracts for the three full risk-based plans in 2013, DHCF initiated the MCO performance review process as the first step towards reforming a troubled program.
Prior to this award, DHCF’s MCO program was hampered by ambiguous contract language, financially unstable providers, and de minimis reporting requirements that made it difficult to assess the performance of the plans.
Accordingly, to coincide with the new five-year MCO contracts, DHCF initiated the comprehensive review process in FY2014 to assess and evaluate the performance of its three full risk-based MCOs. 4<br>
slide5. FY18 MCO Contract Procurement In 2017, DHCF awarded contracts for the upcoming FY18 contract year for the three full risk-based MCOs. Two of the three MCOs -- AmeriHealth and Trusted -- are returning, with one newly-awarded MCO - Amerigroup. DHCF conducted a robust RFI and readiness review process for each of the MCOs, evaluating the MCO’s ability to perform services included in the MCOs’ contracts, identifying best practices and opportunities for improvement.
MedStar appealed the results of the procurement to the Contract Appeals Board and DHCF was ordered to conduct a re-evaluation of the proposals. That decision is being appealed to the District Superior Court.
The goal of DHCF’s managed care program through the FY17 contract procurement process is to promote healthy outcomes of the enrolled populations in the most cost-effective manner possible. For instance, the new contract encourages provider performance rewards through innovative approaches to compensation, such as value-based purchasing (VBP) payment models that link specific financial incentives to demonstrable improved health outcomes.
As a result, DHCF’s managed care program will have a clear focus on achieving better health outcomes, health care innovation and cost effective quality healthcare. 5<br>
slide6. Goals Of The Performance Review There are three primary goals of this performance review:
Evaluate the degree to which DHCF’s risk-based MCOs and the single risk sharing plan successfully ensure beneficiary access to an adequate network of providers while managing the appropriate utilization of health care services.
Provide objective data on the performance of the MCOs across a number of domains to inform decision making about possible policy changes for the managed care program.
Facilitate an assessment of each MCO to help guide decisions regarding contract renewals of each MCO. 6<br>
slide7. This annual report for 2017 addresses the following questions for each MCO.
What was the financial condition of the MCOs during 2017? Were the MCO revenues sufficient to cover claims and operating costs?
Did the MCOs successfully execute the administrative responsibilities required of a managed care plan – timely claims processing, robust member encounter systems, and appropriate use of claims denial procedures?
Did the full risk-based MCOs successfully meet the 85% Medical Loss Ratio (MLR) threshold while otherwise containing cost? What service levels were achieved for primary care visits as well as mental health penetration rates for children and adults?
As a risk-sharing plan, did HSCSN meet the 89% MLR threshold while otherwise containing cost? As a result what is the financial impact for DHCF?
What success -- as measured by performance against three established benchmarks -- did the full risk MCOs experience in coordinating care for its members in 2017? Focus Of The Performance Review 7<br>
slide8. Presentation Outline 8 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide9. Strong Overall Financial Conditions - Full Risk-Based Health Plans
The District’s full-risk MCOs are generally in good financial condition at the end of 2017. Each of the full risk-based MCOs reports risk-based capital (RBC) positions that are above the required level of 200 percent, while posting profits ranging from 3 to 8 percent with ample cash reserves as protection against a sharp downturn in revenue. With respect to operating margins, Amerigroup was an exception - posting low margins during their first quarter of operations.
Amerigroup’s Low Margins
Given Amerigroup’s limited claims experience since convening operations in October 2017, Amerigroup employed a loss ratio approach to derive incurred but not reported (IBNR) claims expense for the period. Albeit this is an acceptable approach for estimating costs, this method may yield considerable variances with actual payments, resulting in high costs and low operating margins. Summary Of Key Findings 9<br>
slide10. HSCSN Declining Financial Position
After suffering huge losses in 2015, and temporarily stabilizing in 2016 as a result of the $13 million DHCF cash infusion in FY2016, HSCSN’s financial position has deteriorated resulting in the MCO operating a net loss for 2017. Though HSCSN’s cash position has improved, the plans total adjusted capital has decreased 42% while payables have increased, resulting in an RBC well below adequate solvency levels. If HSCSN was monitored through DISB, this level of RBC would require HSCSN to create a robust plan to rebuild capital to sufficient levels. DHCF is monitoring this situation closely and considering possible action.
Administrative Performance - All Health Plans
Four areas are typically evaluated to assess MCOs’ administrative performance – adequacy of provider network, timely payment of claims, appropriate management of the claims adjudication process, and successful execution of an encounter system. Data from this analysis indicates the MCOs are, on balance, properly managing these significant responsibilities. Notably in 2017:
The MCOs have maintained comprehensive and diverse provider networks to ensure access to a full range of services as well as robust systems to report patient encounters; Summary Of Key Findings (continued) 10<br>
slide11. HSCSN was the only MCO that did not exceed the District’s timely payment requirement in 2017, but their performance was only slightly less than the required standard. While HSCSN made significant improvements from its low 67 percent of claims paid within 30 days in 2016 to 89 percent in 2017, they are still not fully compliant with District law.
District MCO’s overall claims denial rate was eight percent, which is consistent with prior rates and suggests MCOs are not using claims adjudication as a cash management strategy.
Medical Expenses: Full-Risk-Based Health Plans
The MCOs in this program spend at least the required 85% of MCO revenue on beneficiary Medicaid medical expenses while generally avoiding spikes in their per-member, per-month (PMPM) costs. Specifically, the expense growth rate from 2016 to 2017 for Medicaid adults declined by 2 percent while the cost for children remained stable for the period. Summary Of Key Findings (continued) 11<br>
slide12. The PMPM cost of the Alliance program continued to be especially high for MedStar. However the other full-risk plans also experienced double digit increases in Alliance PMPM costs. The PMPM growth was most significant for AmeriHealth (50 percent), followed by MedStar (26 percent) and Trusted (18 percent).
Some of the growth was fueled by DHCF’s need to transition the pharmacy spending for the program off of the Department Of Defense Discount Program and into the MCO benefits in 2016. While enrollment growth is stable, the Alliance population is becoming slightly older with more complex medical problems. This has driven increased spending in pharmacy and outpatient hospital costs.
HSCSN’s 93 percent spending level on medical expenses for 2017 surpassed the threshold which provides the anchor for its rate. This reduced the operating margins for the plan and required DHCF to step in with risk corridor payments in 2017. The plan’s cost growth rate spiked at 15%, a sharp increase from the moderate 2% growth rate over the last year. This situation will be closely monitored in CY2018. Summary Of Key Findings (continued) 12<br>
slide13. The mental health beneficiary utilizations rates for 2017 experienced a slight decrease for the Medicaid child population while remaining stable across the adult population, when compared to 2016 results. Mental health spending decreased slightly from $60.6 million in CY2016 to $57.8 million in CY2017, most likely due to the closure of several key MHRS provider sites in CY2017.
Beneficiary Utilization
On average, the beneficiary physician visit rates are consistent with prior reporting periods, with the exception of a minor decrease in early 2017 for Trusted members, which was followed by a subsequent increase to prior levels in the second half of 2017.
Well-Child visits for children increased for nearly all plans in CY2017, notably HSCSN and AmeriHealth. Summary Of Key Findings (continued) 13<br>
slide14. Care Coordination
The care coordination challenges that plagued the District’s three full-risk MCOs from 2014 through 2016 have been well documented -- members’ use of the emergency room for routine care, the repeated occurrences of potentially avoidable hospital admissions, the problem of hospital readmissions – and remain stubborn challenges, but with some improvement.
For 2017, the MCOs have spent approximately $40 million on patient care that may have been avoided through the use of more aggressive care coordination strategies. This, however; has declined from $53 million in avoidable spending in 2016.
CMS has now approved DHCF’s pay-for-performance (P4P) program. When comparing Year 1 (October 2016 – September 2017) of the P4P program to the baseline targets, only one MCO – Trusted – successfully earned back the full capitation withhold based on the MCO’s improvement achieved for all three of the performance goals. Summary Of Key Findings (continued) 14<br>
slide15. Presentation Outline 15 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide16. DHCF focuses on four key metrics when evaluating the financial stability of MCOs:
Medical loss ratio (MLR) – represents the portion of total revenue used by the MCOs to fund medical expenses, including expenses for cost containment.
Administrative loss ratio (ALR) – represents the portion of total revenue used by the MCOs to fund both claims processing and general administrative expenses.
Operating Margin (OM) – also referred to as profit margin and is defined as the sum of MLR and ALR subtracted from 100 percent. A positive OM indicates a financial gain while a negative indicates a loss. Mercer’s benchmark of the operating margin needed to sustain a strong financial position is approximately 2-4 percent annually over a 3-5 year time horizon.
Risk-based Capital (RBC) – represents a measure of the financial solvency of managed care plans and reflects the proportion of the required minimum capital that is maintained by a managed care plan as of the annual filing. There Are Several Key Metrics That Speak To The Financial Health Of MCOs 16<br>
slide17. Assuming adequacy in the base capitated payment rate, there are typically three important factors that impact whether an MCO will experience positive operating margins:
Risk-adjusted payment rates. With DHCF’s payment model, MCOs whose enrollees evince greater medical risk in the form of disease prevalence, receive higher risk scores and greater payments. MCOs with lower risk enrollees receive reduced rates. Thus, plans that properly align membership risk and utilization can gain a considerable advantage over others that do not.
Provider contract rates. Plans that negotiate contract rates that are adequate to build a solid network but lower than their competitors can realize significantly higher surpluses.
Patient utilization management. Relative differences across plans in the degree to which their enrollees unnecessarily access high end care as an alternative to less expensive treatment will drive variations in operating margins. Generally, Observed Differences In Health Plan Operating Margins Can Be Traced To A Few Key Factors 17<br>
slide18. Traditional concerns that patient care is being sacrificed are often expressed when MCOs report significant operating margins. Accordingly:
DHCF routinely tracks the MCOs’ performance against the 85% Medical Loss Ratio (MLR) requirement for full the risk based plans and 89% for the shared risk plan.
MCOs that fall short of this standard face detailed scrutiny and possible financial penalties if warranted.
Health plans can also artificially (and temporarily) inflate operating margins by repeatedly denying claims that should be paid.
DHCF monitored and reported on the MCOs’ management of the denied claims process starting in 2016. This report provides a comparative analysis for the year 2017 and the corresponding period in 2016. Some Strategies Can Increase Operating Margins But Are Not Reflective Of A Properly Operated Health Plan 18<br>
slide19. For Medicaid Membership, AmeriHealth Experienced The Largest Growth, Partially Due To Members Transitioning From Amerigroup, While HSCSN Experienced A Slight Decline In Enrollment From 2016 19<br>
slide20. When Alliance Members Are Included, The Numbers Do Not Significantly Change 20<br>
slide21. Revenues Paid By DHCF To The Health Plans During 2017 Were Sufficient To Cover Both Claims And Administrative Cost, While Three Of The Five Plans Posted Significant Operating Margins Operating Margin (Loss) Revenue1 Claims2 Administrative Cost3 = MCO Revenue and Expense Data for January 2017 to December 2017 21<br>
slide22. The MCO’s Risk-based Capital (RBC) levels can be seen as a proxy for whether an MCO has the assets to pay claims.
MCOs conduct this complicated calculation annually for each MCO using end-of-year financial data (as well as some information that is not publically disclosed) that is provided to the Department of Insurance, Securities and Banking (DISB) for review.
Health plans with RBC levels that fall below 200% face greater scrutiny from DISB and DHCF (as described on the next slide) to ensure that they raise their capital level above 200% RBC.
This report compares the annual RBC measures reported by the plans in their official 2016 financial statement filed with DISB to more recent 2017 RBC proxy calculated by Mercer Consulting. Estimated Risk-Based Capital Measures Provide A Reliable Indicator Of MCO Solvency 22<br>
slide23. Regulators Track Insurers Risk-Based Capital Levels And Have Guidelines For Taking Action 23 Based on the level of reported risk, the National Association of Insurance Commissioners indicates that a number of actions (described below) are available if warranted:
No action - Total Adjusted Capital of 200 percent or more of Authorized Control Level.
Company Action Level - Total Adjusted Capital of 150 to 200 percent of Authorized Control Level. Insurer must prepare a report to the regulator outlining a comprehensive financial plan that identifies the conditions that contributed to the company’s financial condition and a corrective action plan.
Regulatory Action Level - Total Adjusted Capital of 100 to 150 percent of Authorized Control Level. Company is required to file an action plan and the Insurance Commissioner issues appropriate corrective orders to address the company’s financial problems.
Authorized Control Level - Total Adjusted Capital 70 to 100 percent of the Authorized Control Level triggers an action in which the regulator takes control of the insurer even though the insurer may technically be solvent.
Mandatory Control Level - Total Adjusted Capital of less than 70 percent triggers a Mandatory Control Level that requires the regulator to take steps to place the insurer under control. Most companies that trigger this action level are technically insolvent (liabilities exceed assets).<br>
slide24. All Four Full Risk-Based Health Plans Maintained Risk Based Capital Levels That Exceeded Recommended Standards, But, HSCSN -- The Shared Risk Plan -- Fell Short Of The Recommended Level 24 Required Standard 200% Regulatory Action
Triggered 150% Annual 2017 Risk-Based Capital For Managed Care Plans Compared To 2016 Annual Level 353% 375% 476% 263% 285% 2016 Annual RBC 2017 Annual RBC Note: There are no required District Risk-Based Capital reporting requirements for HSCSN. The reported numbers are calculated for this report.
*In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Reported figures are from the MCO’s annual 2016 and the first two quarters of 2017 financial statements filed with DISB for the full risk MCOs and self reported
financials for shared risk MCO.<br>
slide25. It is paramount in managed care that MCOs maintain a reserve to pay for services that have been provided but not yet reimbursed.
This claims liability represents an accrued expense or short-term liability for the MCOs each month and MCOs that fail to build a sufficient reserve may not be able to pay claims when they eventually clear the billing pipeline.
Typically, MCOs are expected to retain a reserve equal to between one to two months’ worth of claims, depending on how quickly claims are processed.
In this report, DHCF reports the reserves MCO’s have available to satisfy incurred but not reported claims. This analysis is based on calculations provided by Mercer using data on the monthly claim’s experience for each plan to calculate the reserves on hand.
We also provide an analysis of the number of days the MCOs can operate without accessing long-term assets. This is described as a Defensive Interval Ratio which is, in essence, a liquidity measure -- the degree to which the MCOs can survive on liquid assets without having to make use of either investments from the market or by selling long term assets. MCOs Must Maintain Adequate Reserves To Pay “Pipeline” Claims 25<br>
slide26. All Four Health Plans Have A Sufficient Number Of Months In Reserve For Estimated Incurred But Not Reported Claims 26 Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
**MedStar officials report that its monthly reserve figure includes data from its operations in other states and is also adversely impacted by the manner in which it pays the required Affordable
Care Act fees.
Source: IBNR is based on amount reported on the MCO’s quarterly filings for the three full risk-based plans and self reported financials for the shared risk plan. Estimated Number Of Months Reserves Compared To Average Monthly Incurred Claims For The Period Covering January to December 2017<br>
slide27. All Five MCOs Reported Strong Liquidity Measures For 2017 27 Days In A Year That MCOs Can Operate On Existing Cash Without Having To Access Long-Term Assets For The Period Covering January to December 2017 +60% N/A* Defense Interval Ratio (Days) Percent Change In
Ratio From CY2016 -15% *Note: In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Mercer calculated the Defensive Interval Ratio as cash and equivalents divided by daily operating expenses over for the period from January to December 2017. +104% -11%<br>
slide28. Presentation Outline 28 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health
Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide29. As a part of its core mission, MCOs must accomplish the following:
Build an adequate network of providers and pay health care claims to service providers on time and through an electronic claims process with documentation to facilitate reconciliation of payments.
Create an accurate electronic record of all patient health care encounters and transmit the files containing this information to DHCF with a minimal error rate.
Establish a system of care management and care coordination to identify MCO enrollees with special or chronic health care issues and ensure that these enrollees each receives access to appropriate care, while managing the delivery of health care services for all enrollees. There Are Several Administrative Requirements Which Are Critical To The Successful Operation Of MCOs 29<br>
slide30. The five-year MCO contracts contain specific provisions to ensure Medicaid and Alliance enrollees have reasonable access to care. The MCOs must have:
1 primary care physician for every 1,500 enrollees
1 primary care physician with pediatric training for children through age 20 for every 1,000 enrollees
1 dentist for every 750 children in their networks
Additionally plan networks must include:
At least 2 hospitals that specialize in pediatric care
Department of Behavioral Health core service agencies
Laboratories within 30 minutes travel time from the enrollees’ residence
For pharmacies, each plan must have:
2 pharmacies within 2 miles of the enrollees’ residence
1 24-hour, seven (7) day per week pharmacy
1 pharmacy that provides home delivery service within 4 hours
1 mail order pharmacy Contractual Requirements Exist To Ensure Adequate Health Care Provider Networks 30<br>
slide31. All Three Health Plans Have Impaneled Substantially More Physicians Than Required By Contract Standards 31 The Number of Providers In The MCO Networks Compared to Contract Requirements, as of December 2017<br>
slide32. The MCOs Continue To Make Significant Improvements With The Accuracy Of Their Encounter Data Files Submissions 32 Number of Recorded Encounters And Accuracy Transfer Rate, January 2017
to December 2017<br>
slide33. 33 Timely Payment Of Health Care Claims Is Core Requirement For The District’s Managed Care Plans Claims processing is a central administrative function that MCOs must effectively execute to avoid payment problems for providers.
Through electronic claims processing, the District’s three managed care organizations are required to pay or deny clean claims within 30 days to satisfy timely filing requirements.
Like most MCOs, the District’s MCOs employ a series of automated edit checks on all claims submitted for payment by healthcare providers in the Medicaid and Alliance programs.
Included among the numerous potential problems this system of edit checks is designed to eliminate are:
Duplicate or overpayments
Payments to out-of-network or otherwise ineligible providers
Payments for services delivered to non-eligible patients<br>
slide34. HSCSN Was The Only MCO With A Full Year Of Data Not To Exceed The District’s Timely Payment Requirement In The First Half of 2017 34 99.9% 99.6% Total Claims Adjudicated 170,371 812,488 Timely Payment Compliance Level of 90% MCO Claims Paid Within 30 Days Based On The District’s Timely
Payment Requirement, January 2017 to December 2017 547,748 216,609 88.5% Note: *Timely payment of claims for Amerigroup District of Columbia were excluded from this analysis. Because Amerigroup’s contract with the District began on October 1, 2017, DHCF received claims data for only one quarter in CY2017; as such, the reporting period would not be comparable to the period for other plans.
1. In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017. Amerigroup’s results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. The 30 day timely payment requirement only applies to “clean claims” that meet the requirement for payment.
2. HSCSN reported low results for April 2017. Subsequent to HSCSN’s initial self-reported April 2017 results to DHCF, HSCSN submitted revised results for April 2017, which would have improved their annual final results if submitted as part of the original monthly submission requirement to DHCF.
Source: Data reported by MCOs on the Department of Health Care Finance’s Claims Payment Report. 1,968,375 98.1%<br>
slide35. 35 Claims Adjudication Review Focuses On Whether MCOs Are Acting In Good Faith Because the District’s 30-day timely payment requirement does not apply to claims that are initially denied, some providers expressed concern that managed care plans were unjustifiably denying a high rate of claims as a cash management strategy.
Such a practice would obviously violate the tenets of good faith claims processing, create significant revenue issues for some of the providers in the MCOs’ networks, and potentially cause access to care issues.
This report addresses this issue by reporting on the incidence of denied claims in the managed care program and the reasons for the denials for the period covering calendar year 2017. Additionally, outcomes for claims that were initially denied but subsequently approved and repaid are also examined.<br>
slide36. Methodology For Denied Claims Review 36 The key steps executed for this analysis were as follows:
First, all MCO denied claims with dates of service between January 1, 2017 and December 31, 2017 were obtained from the District’s four MCOs* and established as the master dataset. This data extraction yielded approximately 340,000 claims.
Second, this master dataset was used to categorize provider types to match DHCF naming schemes and search for all claims with missing identifiers.
Third, using DHCF’s MMIS, all paid patient encounters with dates of service between January 1, 2017 and December 31, 2017 were extracted, yielding nearly 4.1 million records.
Fourth, the dataset containing denied MCO claims (Step 1) was then merged with the dataset containing accepted encounters from MMIS (Step 2), using the beneficiaries’ Medicaid ID, first date of service, last date of service, and billing provider NPI as the matching variables. This established in the same dataset, claims that were paid, denied, and those that were initially denied but paid at a later date. Note: *Paid and denied claims submitted by Amerigroup District of Columbia were excluded from this analysis. Because Amerigroup’s contract with the District began on October 1, 2017, DHCF received claims data for only one quarter in CY2017; as such, the reporting period would not be comparable to the period for other plans.<br>
slide37. MCOs Had An Average Denial Rate Of Eight Percent In CY2017 *Total number of denied claims after review represented less than one-tenth of all claims processed Total Number of MCO Encounters Accepted
in CY2017:
3,782,105 (92%) Total Number of Denied Claims Later Accepted:
38,784 (11%) 37 Total Number of MCO Claims
Received in CY2017:
4,121,765 Total Number of MCO Denied claims
in CY2017:
339,660 (8%) Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Total Number of Denied Claims
After Review:
300,876 (89%)<br>
slide38. 38 MedStar And Trusted Denial Rates Were Slightly Above MCO Average Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. Claims Denial Rates For Each Health Plan, CY2017 Total Claims Adjudicated 257,049 626,081 2,318,775 919,860 Average Claims Denial Rate: 8%<br>
slide39. MCO Denials Were Mostly Related To Service Coverage And Duplicate Claims 39 Note: *This can include missing prior authorization, services not being covered, or exceeded units.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MCO Claims Denial Rate, CY2017 N = 339,660 total denied claims N = 4,121,765 Claims Paid Claims Denied<br>
slide40. 40 MedStar’s Denial Rate For Pharmacy Adjudication Increased Slightly From 19% In CY2016 To 24% In CY2017; Pharmacy Claims Still Account For The Highest Rate By Provider Type Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MedStar’s Denied Claims By Provider Type, CY2017 MedStar’s Most Common Denial Reasons, CY2017<br>
slide41. DHCF Is Creating a Standardized Provider Manual As Well As Convening Regular Meetings with MCO Provider Relations, To Educate Providers On Proper Eligibility, Service And Billing Requirements 41 Claims Denial Rate By Top Five Provider Types, CY2017 Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017.<br>
slide42. Eleven Percent Of Claims Initially Denied Were Later Overturned And Paid 42 MCO Claims Denial Rate, CY2017 N = 4,121,765 N = 38,704 11% 89% Was Denied Claim
Later Paid? No Yes Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Claims Paid Claims
Denied<br>
slide43. 43 Trusted And HSCSN Had More Than 20% Of Denied Claims Overturned After Appeal Total Claims
Denied 137,975 121,375 Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MCO Rates of Payment For Originally Denied Claims, CY2017 63,869 16,441 Average
Rate:
16%<br>
slide44. More Than 4 Out of 10 Of All Appealed Denied Claims Approved After An Appeal Were Paid Within 30 Days 44 N = 38,508 Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Percentage Of MCO Claims Approved After Appeal That Were
Paid Within 30 Days, CY2017<br>
slide45. 45 Payment Of Claims Within 30 Days After Initial Denial Varies By MCO, With Much Higher Rates For MedStar Total Claims Paid After Initial Denial 13,975 7,164 Note: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017.
Source: Department of Health Care Finance, Medicaid Management Information System (MMIS), 2017. MCO Rates of Payment Within 30 Days For Originally Denied Claims, CY2017 13,517 4,128 Average
Rate:
42%<br>
slide46. Home Health Agencies Continue To Experience The Longest Lag In Payment After Claims Denial Is Overturned 46 Note: Patient encounters with January 1-December 31, 2017 dates of service from DHCF MMIS system were merged with MCO files containing denied claims for the same period. The claims run out period was February 2018. Average Number Of Days To Payment For Appealed Claims, CY2017<br>
slide47. Denial Rates Have Decreased By Half Over A Four Year Period; Timely Payment of Claims Approved After Initial Denial Has Also Decreased By Half 47<br>
slide48. Presentation Outline 48 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization
Patterns
Care Coordination and Performance Against Program P4P
Benchmarks<br>
slide49. Each Of The Full Risk Plans Spent At Least 85 Percent Of Revenue On Member Medical Expenses 49 Actual MCO Revenue At Target Rate For January 2017 to December 2017 Actual Medical Loss Ratio 92% 86% 8% 6% 8% Admin Expenses Notes: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s financial results represent data from January 2017 through September 2017. Amerigroup’s financial results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. MCO revenue does not include investment income, HIPF payments, and DC Exchange/Premium tax revenue. Administrative expenses include all claims adjustment expenses as reported in quarterly DISB filings and self reported quarterly filings, excluding cost containment expenses, HIPF payments and DC Exchange/Premium taxes.
Source: MCO Quarterly Statement filed by the MCOs with the Department of Insurance, Securities, and Banking for the three full risk MCOs and self reported Quarterly statements for shared risk plan, HSCSN 85% 13% Operating
Margin 0.2% 2% 8% 88% 5% 4% 85% 10% $152.9M<br>
slide50. DHCF Has A Risk Sharing Arrangement With HSCSN In Which The Government Shares In The Plan’s Profits And Losses 50 DHCF and HSCSN entered into a risk sharing arrangement to limit the financial gains and losses under the contract through the application of risk corridors.
The arrangement sets risk corridors around an annual target Medical Loss Ratio of eight-nine percent (89%). Thus if the MCO experiences cost below the 89% threshold for the year, the District shares in the financial gain.
Conversely, if HSCSN incurs cost above the 89% threshold, the District absorbs a portion of the cost.
The Table below shows the risk corridors for this contract and how financial gains or losses are shared between the HSCSN and the District:
For the year, HSCSN’s medical expenses as a percent of its revenue (93%) was above the threshold for Medical Loss Ratio (89%), meaning the District and the MCO will share the losses following the aforementioned guidelines. For 2017, the estimated share of the resulting loss and financial impact to the District is currently $1.4M.<br>
slide51. HSCSN Spent Above The 89% Risk Sharing Threshold On The Actuary Model For 2017, Resulting In An Estimated $1.4 Million Impact To The District 51 HSCSN Revenue And Claims Cost For 2016 And 2017 Actual Medical Loss Ratio 93% Admin & Profit Margin Notes: MCO revenue does not include investment income, HIPF payments, and DC Exchange/Premium tax revenue. Administrative expenses include all claims adjustment expenses as reported in quarterly DISB filings and self reported quarterly filings, excluding cost containment expenses, HIPF payments and DC Exchange/Premium taxes.
Source: Self reported quarterly statements . 89% 7% 89% $179.8M $175.2M<br>
slide52. A Slight Decline In Year-Over-Year Medical Expenses For Adults And Flat Trends Were Observed For Children In The Medicaid Program, But, Overall Differences For Adults Vary Significantly 52 $312.20 $376.47 $206.90 $214.13 $203.81 Medicaid Adult And Children Medical Expenses Per-Member, Per-Month, January 1, 2017
to December 31, 2017 Notes: *Incurred from January 1, 2017 to December 31, 2017 for AmeriHealth and Trusted, incurred from January 1, 2017 to September 30, 2017 for MedStar, and incurred from October 1, 2017 to December 31, 2017 for Amerigroup; all claims paid as of January 31, 2018. IBNR is estimated based on historical payment lags. This short runout period results in a high degree of uncertainty for IBNR estimates and final results will differ. Children defined as person up to age 21 in this analysis for the three full risk MCOSs.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Percent Change From 2016 N/A* 0% -8% N/A* +4% 0% $361.45 -2% $208.77 0% $291.33 $193.90 -3% -6%<br>
slide53. The Double Digit Growth In Medical Expenses For Alliance Exacerbated By DHCF’s Need To Move Most Of The Pharmacy Cost Of This Program Off Of The Department Of Defense Discount Program And Into The Managed Care Benefit In 2016 Continues To Accelerate In 2017 53 $322.26 $341.84 Alliance Adult Medical Expenses Per-Member, Per-Month, January 1, 2017 to December 31, 2017 Notes: *Incurred from January 1, 2017 to December 31, 2017 for AmeriHealth and Trusted, incurred from January 1, 2017 to September 30, 2017 for MedStar, and incurred from October 1, 2017 to December 31, 2017 for Amerigroup; all claims paid as of January 31, 2018. IBNR is estimated based on historical payment lags. This short runout period results in a high degree of uncertainty for IBNR estimates and final results will differ. *Amerigroup began operations in October 2017.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Percent Change From 2016 N/A* +50% +26% $345.91 +31% +18%<br>
slide54. For Adults On Medicaid And Compared To The Same Time Period Last Year, AmeriHealth Continues To Shift More Expenses To An Outpatient Setting Relative To The Other Health Plans. Both AmeriHealth And Trusted Reduced Emergency Room And Inpatient Cost Growth In 2017 54 AmeriHealth MedStar* Trusted N/A* -9% +2% +46% +5% -6% 0% -2% +7% -5% Percent Change in Expenses From 2016 to 2017 Note: *Change in average PMPM expense, January 1, 2017 through December 31, 2017 compared to January 1, 2016 through December 31, 2016 for AmeriHealth and Trusted. Change in average PMPM expense, January 1, 2017 through September 30, 2017 compared to January 1, 2016 through December 31, 2016 for MedStar. Amerigroup began operations in October 2017.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Amerigroup* -3%<br>
slide55. For Children On Medicaid, As Compared To Prior Years, Trusted Reported Significant Reductions In Inpatient Costs While AmeriHealth Reduced Its Emergency Costs In 2017 55 AmeriHealth MedStar* Trusted N/A* -12% +28% +17% -14% Percent Change in Expenses From 2016 to 2017 Notes: *Change in average PMPM expense, January 1, 2017 through December 31, 2017 compared to January 1, 2016 through December 31, 2016 for AmeriHealth and Trusted. Change in average PMPM expense, January 1, 2017 through September 30, 2017 compared to January 1, 2016 through December 31, 2016 for MedStar. Children defined as person up to age 21 in this analysis for the three full risk MCOSs and age 26 for HSCSN. Amerigroup began operations in October 2017.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. HSCSN +21% +5% -24% +15% -9% -6% +6% -1% -15% +23% +8% -13% +47% +17% -5% +8% Amerigroup*<br>
slide56. AmeriHealth Medicaid Inpatient Admissions Rates Are Slightly Higher Than The Other Two MCOs With Amerigroup Replacing MedStar In October 2017 56 Total Number Of Inpatient Admissions in CY2017 Per 1000 Members Notes: *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017. Amerigroup’s results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. The current frequency of Index Admissions analysis for the period January 2017 to December 2017 includes encounters that are stamped by DHCF’s MMIS both "Paid and Denied" encounters. These encounters include Medicare crossover claims. MedStar and Amerigroup rates are adjusted to full year rates.
Source: Expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF.<br>
slide57. For HSCSN The Growth In Its Per-Member, Per-Month Medical Expenses For Children From 2016 To 2017 Spiked Due To High Cost Specialty Drugs And Significant Q4 Outpatient Claims 57 Medicaid Children Medical Expenses Per-Member, Per-Month,
December 2015 to December 2017 Notes: Expenses incurred from January 1, 2017 to December 31, 2017 and paid as of January 31, 2018. The expenses do not reflect adjustments to account for IBNR claims. Children defined as person up to age 21 in this analysis for the three full risk MCOs and 26 for HSCSN
Source: Enrollment and expense data is based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. 2 Percent Cost Growth Compared To 2015 $2,082 17 Percent Cost Growth From December 2015 $2,386 15 Percent Cost Growth Compared To 2016<br>
slide58. Home Health Costs Are Consistently A High-Cost Service For HSCSN Quarter-Over-Quarter Since 2016 58 Medicaid Children Medical Expenses Per-Member, Per-Month, Large Cost Drivers for HSCSN from
September 2016 to December 2017 Notes: Expenses incurred from January 1, 2017 to December 31, 2017 and paid as of January 31, 2018. The expenses do not reflect adjustments to account for IBNR claims. Children defined as person up to age 21 in this analysis for the three full risk MCOs and 26 for HSCSN
Source: Enrollment and expense data is based on self-reported MCO Quarterly Financial Data submitted directly to DHCF.<br>
slide59. The Physician Visit Rates For Children Are Consistently Above Average for HSCSN and AmeriHealth in CY2017 59 Medicaid Quarterly Physician Care Visit Rates For Children Enrolled In Managed Care,
April 2015 to December 2017 Note: In each quarter, only members who were enrolled with the MCO for three months continuously during the period and had 12 months of continuous Medicaid participation
from that quarter are included in this analysis. *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results represent data from January 2017 through September 2017. Amerigroup’s results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis. The 30 day timely payment requirement only applies to “clean claims” that meet the requirement for payment.
Source Encounter data submitted by MCOs to DHCF.<br>
slide60. Well-Child Visits For Children Have Increased For Nearly All Plans From CY2016 To CY2017, Notably For HSCSN And AmeriHealth 60 Medicaid Well Child Visit Rates For Children Enrolled In Managed Care, April 2015 to December 2017 Note: In each quarter, only members who were enrolled with the MCO for three months continuously during the period and had 12 months of continuous Medicaid participation
from that quarter are included in this analysis. *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s 2017 results represent data from January 2017 through
September 2017. Amerigroup’s 2017 results represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Encounter data submitted by MCOs to DHCF.<br>
slide61. The Physician Visit Rate For Adults Is Mostly Unchanged From CY2016, With Trusted Showing A Slight Decrease In Its Rates in Early CY2017 61 Medicaid Quarterly Physician Care Visit Rates For Adults Who Were Enrolled In Managed Care,
April 2015 to December 2017 Note: In each quarter, only members who were enrolled with the MCO for three months continuously during the period and had 12 months of continuous Medicaid participation
from that quarter are included in this analysis. *In 2017 DHCF awarded new contracts for the District MCOs for FY18. MedStar’s results for 2017 represent data from January 2017 through September 2017. Amerigroup’s results for 2017 represent data from October 2017 through December 2017. All other MCOs financial results are reported on an annual basis.
Source: Encounter data submitted by MCOs to DHCF.<br>
slide62. The Utilization Rate For Medicaid-Funded Mental Health Rehabilitation Services Was Lower For Children In CY2017, Likely Due To The Recent Closure Of Several Key Provider Sites 62 Percent of MCO Members Receiving Mental Health Rehabilitation Services Through MCOs, CY2017 Note: The data presented above are based on MCO paid encounters for January1 – December 31, 2017, with a claims run out period through February 2018.
Source: Encounter data submitted by MCOs to DHCF. N = 212,541 N = 134,672 N = 77,869 N = 213,133 N = 136,721 N = 76,412<br>
slide63. However, The MCO Penetration Rate For Beneficiaries Who Received Any Mental Health Services in CY2017 Is Consistent With Rates From CY2016 63 Percent of MCO Members Receiving Any Mental Health Services Through The MCOs, CY2017 Note: The data presented above are based on MCO paid encounters from January 1 – December 31, 2017, with a claims run out period through February 2018.
Source: Encounter data submitted by MCOs to DHCF. N = 212,541 N = 134,672 N = 77,869 N = 213,133 N = 136,721 N = 76,412<br>
slide64. Overall On A Per-Member Per-Month (PMPM) Basis MCOs Reduced Spending On Medicaid-Funded Mental Health Services For Both Children And Adults With The Exception Of Trusted’s Child Population And AmeriHealth’s Adults 64 Adult PMPM Spending The Per-Member Per-Month MCO Expenses For Behavioral Health Services,
January 2017 to December 2017 Notes: *Incurred from January 1, 2017 to December 31, 2017 for AmeriHealth and Trusted, incurred from January 1, 2017 to September 30, 2017 for MedStar, and incurred from October 1, 2017 to December 31, 2017 for Amerigroup; all claims paid as of January 31, 2018. IBNR is estimated based on historical payment lags. This short runout period results in a high degree of uncertainty for IBNR estimates and final results will differ.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data submitted directly to DHCF. Children PMPM Spending MCO Spending Change From 2016<br>
slide65. Presentation Outline 65 Goals and Purpose of Managed Care Review
Summary Of Key Findings
The Financial Performance of the District’s Health Plans
The Administrative Performance of the District’s Health Plans
MCO Medical Spending and Beneficiary Utilization Patterns
Care Coordination and Performance Against Program
P4P Benchmarks<br>
slide66. Achieving high value in health care for Medicaid and Alliance beneficiaries is a preeminent goal of DHCF’s managed care program.
The District’s three managed care plans are expected to increase their members’ health care and improve outcomes per dollar spent through aggressive care coordination and health care management.
After reviewing several years worth of data, DHCF can now more closely examine the following performance indicators for each of the District’s three MCOs:
Emergency room utilization for non-emergency conditions.
Potentially preventable hospitalizations – admissions which could have been avoided with access to quality primary and preventative care.
Hospital readmissions for problems related to the diagnosis which prompted a previous and recent – within 30 days – hospitalization. DHCF Relies Upon Several Metrics To Quantitatively Assess The Efforts By The Health Plans To Coordinate Enrollee Care 66<br>
slide67. All Three Health Plans Can Save Millions By Reducing Their Medicaid Members’ Use Of The ER For Non-Emergencies, Reducing Potentially Avoidable Hospital Admissions, And Slowing The Rate Of Hospital Readmissions 67 $5.4M Notes: *During the performance period, AmeriHealth instituted a short-stay review process in which many inpatient claims were voided. Some of the voided claims may be re-paid upon providers supplying appropriate documentation. As a result, measurement of the PPA performance measure is delayed to allow for additional claims run-out. FY17 results reflect data incurred in October 2016 – September 2017 with payment runout through December 2017. The amounts listed as potentially avoidable would likely be offset by other costs if the MCOs improved their care management, such as increased outpatient costs due to increased use of outpatient facilities.
Source: Enrollment and expense data are based on self-reported MCO Quarterly Financial Data for DCHFP submitted directly to DHCF. TBD* $13M $1.5 $4.7M $9M $1.2M $2M $3M $8.1M $6.7M $25M Managed Care Spending Attributed To Beneficiary Outcomes That Are Potentially Avoidable Through The Use Of Robust Care Coordination Programs<br>
slide68. In Total Approximately $40 Million In Managed Care Expenses Were Potentially Avoidable* 68 Notes: Low acuity non-emergent visits are emergency room visits that could have been potentially avoided, identified using a list of diagnosis applied to outpatient data. Avoidable admissions are identified using a set of prevention quality measures that are applied to discharge data. Readmissions represent inpatient visits that within 30 days of a qualifying initial inpatient admissions. *The amounts listed as potentially avoidable would likely be offset by other costs if the MCOs improved their care management, such as increased outpatient costs due to increased use of outpatient facilities.
Source: Mercer analysis of MCO Encounter data for DCHFP reported by the MCOs to DHCF. Patient Metrics Low-Acuity
ER Use Avoidable
Admissions Hospital
Readmissions 63% 17% 57% 27% Comparison Of MCO Potentially Avoidable Spending 2016 To 2017<br>
slide69. Pay-For-Performance (P4P) Process At A Glance 69<br>
slide70. Beginning in October 2016, DHCF’s three full-risk MCOs were required to meet performance goals in order to receive their full capitated payment rate.
These performance goals require the MCOs to reduce the incidence of the following three patient outcomes for the DCHFP population:
Potentially preventable admissions (PPA).
Low acuity non-emergent (LANE) visits.
30-day hospital readmissions for all-causes. In FY2017, DHCF Launched Pay-For-Performance Program As An Incentive For MCOs To Address Care Coordination Problems 70<br>
slide71. The program is funded through a two-percent (2%) withhold of each MCO’s actuarially sound capitation payments for non-delivery DCHFP rate cells for the corresponding period.
The 2% withhold is the profit margin for each MCO that is factored into the base per-member, per-month payment rate. Year 1 P4P results are based on FY17 (October 2016 – September 2017) experience compared to the Year 1 baseline.
The baseline period used to set the target remains April 1, 2015 through March 31, 2016, with runout through September 2016. MCOs must meet the minimum threshold for improvement for all three performance measures in order to earn any portion of the withhold. Program Structure Is Based On Cash Withhold 71<br>
slide72. A scoring system was implemented to determine the distribution of payment incentives for the MCOs:
LANE and PPAs will be weighted at 33% of the capitation withhold. The MCOs have an opportunity to earn back the full 33% based on performance as follows:
5% reduction in LANE Emergency Department (ED) utilization and PPAs from the baseline will result in the MCO earning 100% of the 33% withhold attributed to each of these measures.
3.5% reduction in LANE ED utilization and PPAs from the baseline will result in the MCO earning 75% of the of the 33% withhold attributed to these measures.
2% reduction in LANE ED utilization and PPAs from the baseline will result in the MCO earning 50% of the 33% withhold attributed to these measures.
If reduction in LANE utilization and PPAs are less than the minimum 2% standard from the baseline, the MCOs do not earn any portion of the 33% withhold attributed to the relevant measure. Weighting And Scoring System For Pay-For-Performance 72<br>
slide73. The scoring system is the same for the third measure -- All-Cause Hospital Readmissions -- but this outcome is weighted at 34% of the capitation withhold.
The MCOs can earn back 50%, 75% or 100% of the 34% withhold attributed to the measure by demonstrating reductions at 2%, 3.5% and 5% respectively.
DHCF relies upon claims data to measure the MCOs performance in this system. Since a run-out period must be allowed to ensure a more complete picture of claims activity, payments will likely occur 4 to 7 months after the measurement period closes. Weighting And Scoring System For Pay-For-Performance (continued) 73<br>
slide74. When Comparing Fiscal Year 2017 To Baseline Results, Only Trusted Met Minimum Standards On All P4P Measures For Full Recoupment Of Capitation Withhold 74 AmeriHealth MedStar Trusted +7% Comparison of Year One October 2016 through September 2017 Results To Year One Baseline Notes: Low acuity non-emergent visits are emergency room visits that could have been potentially avoided, identified using a list of diagnosis applied to outpatient data. Avoidable admissions are identified using a set of prevention quality measures that are applied to discharge data. Readmissions represent inpatient visits that within 30 days of a qualifying initial inpatient admissions. Year 1 Baseline reflects data incurred April 2015-March 2016. The Year 1 Pay-For-Performance target for each plan is set based on a 5% expected improvement to the baseline for each metric for full payment of withhold, and a 2% minimum improvement on each metric to receive any portion of withhold.
*During the performance period, AmeriHealth instituted a short-stay review process in which many inpatient claims were voided. Some of the voided claims may be re-paid upon providers supplying appropriate documentation. As a result, measurement of the PPA performance measure is delayed to allow for additional claims run-out.
Source: Mercer analysis of MCO DCHFP Encounter data reported by the MCOs to DHCF. TBD* +16.6% +5.6% +16.3% +9.3% +20.5% +36.1% Year 1 Performance Base Target For Each Plan 5% Improvement from Baseline for Full Payment +2.1%<br>
slide75. Amount of Withhold Earned Back Amount of Withhold Lost Note: *AmeriHealth’s PPA numbers are not final due to pending claims that are presently under review. Overall P4P payment is contingent on MCO meeting minimum standards on all measures. Calculations performed by Mercer Consulting using DHCF capitated payment data and MMIS claims. The Health Plans Earned Back Roughly 77% Percent Of The Performance Withhold Amounts $8.8M $5M $2.6M $16.4M TBD* ($4.2M) ($2.6M) ($12.7M) TBD* ($800K) ($3.7M) Total Funds At-Risk 75 Amount Of Capitation Withhold Earned And Lost For FY17<br>
slide76. Questions and Comments<br>