
The Evolution of the Healthcare System Module 3































Description: The Evolution of the Healthcare System Module 3 Cynthia M. Wiford, MRC, CCS, LCAS Addiction Consulting and Training Associates (ACT), LLC Learning Objectives Draw a comparison between the US healthcare system to healthcare in other
Related Topics
Download Presentation
"The Evolution of the Healthcare System Module 3" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. The Evolution of the
Healthcare System Module 3
Cynthia M. Wiford, MRC, CCS, LCAS
Addiction Consulting and Training Associates (ACT), LLC<br>
slide2. Learning Objectives Draw a comparison between the US healthcare system to healthcare in other countries
Introduce the historical context for US healthcare reform efforts
Develop an awareness of the bifurcated healthcare system currently in existence
Provide a summary of the issues regarding patient protections and electronic records<br>
slide3. How the U.S. Health Care System Compares The US continues to outspend all other industrialized countries on healthcare
In 2008, medical expenses were $7538 per capita
Spent 16% of its gross domestic product on healthcare
Has far more private source funding on healthcare than any of the other countries which rely on government or social service models rather than private insurance<br>
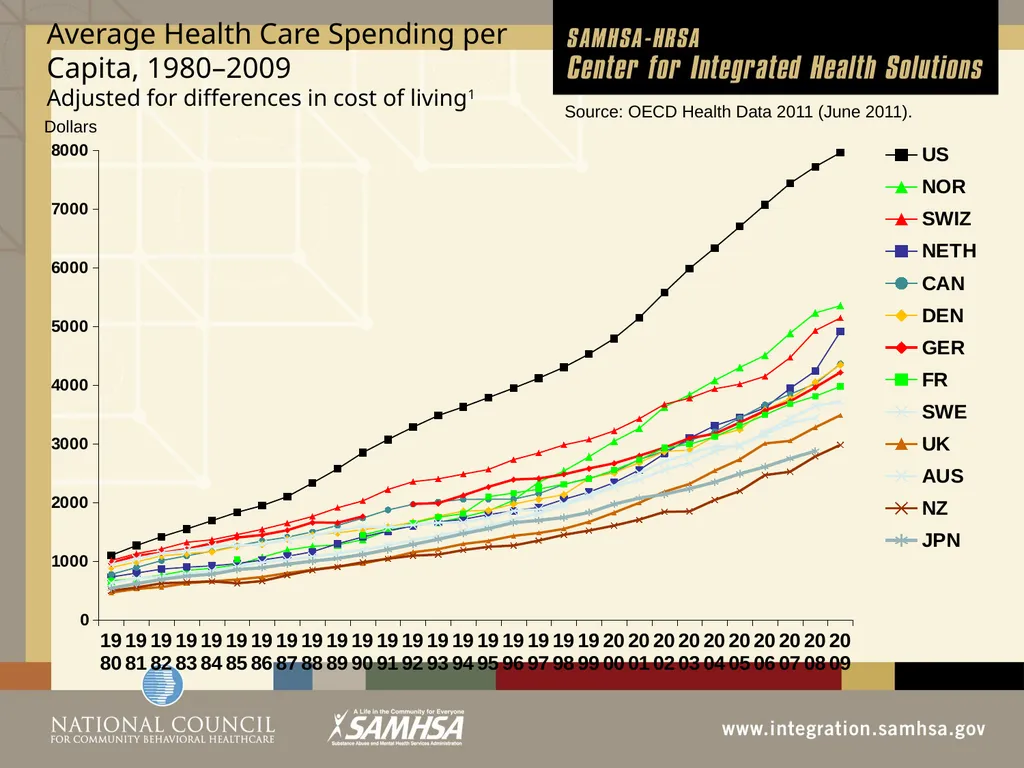
slide4. Source: OECD Health Data 2011 (June 2011). Average Health Care Spending per Capita, 1980–2009 Adjusted for differences in cost of living1 Dollars<br>
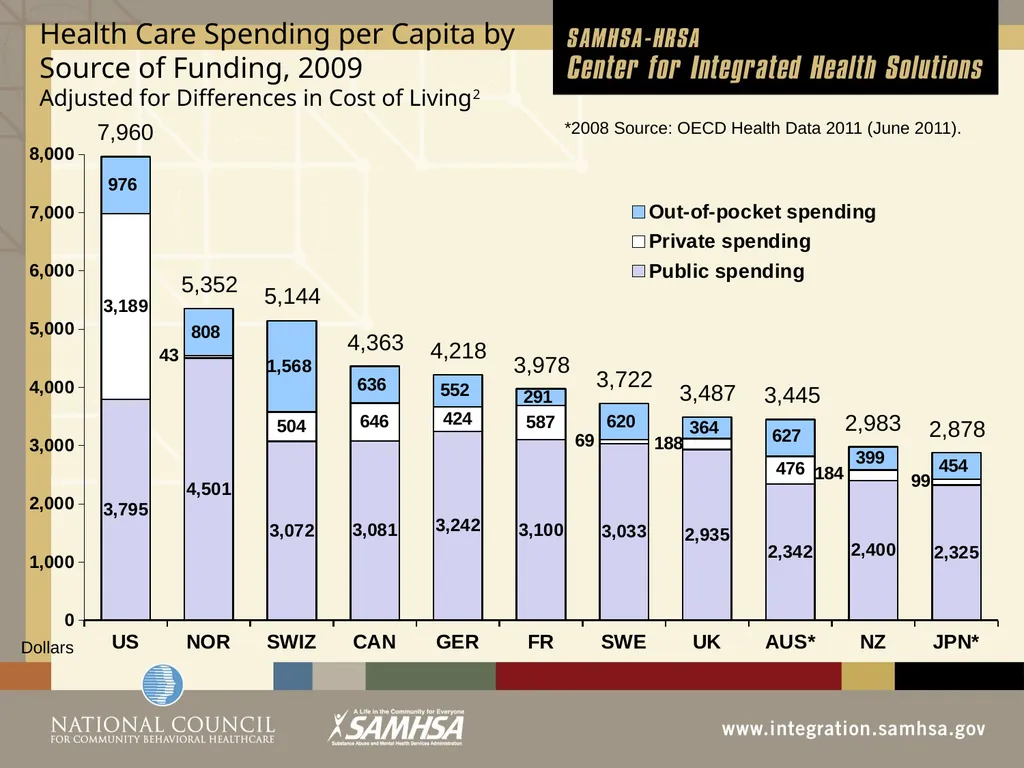
slide5. 5 Health Care Spending per Capita by Source of Funding, 2009 Adjusted for Differences in Cost of Living2 Dollars 7,960 4,363 4,218 3,978 3,722 3,487 3,445 2,878 2,983 5,352 5,144 *2008 Source: OECD Health Data 2011 (June 2011).<br>
slide6. Comparing Service Patterns3 The United States
has the fewest practicing physicians and lowest physician visits among any of the 12 nations in the study
Hospital admission rates are lower, stays shorter and costs higher
Has the highest drug utilization, prices and spending
More hospital admissions for chronic conditions<br>
slide7. Why U.S. Spends More on its Healthcare4 The usually cited reasons:
Aging population
Complexity of health care administrative system
Defensive as opposed to preventive healthcare
High rates of mal-practice insurance
The reality:
The US population is substantially younger in age than populations from other countries
The US has average or below average rates of chronic conditions
But these are not substantiated in the research as the reasons for the distinct discrepancies when drawing a comparison between the US and other healthcare systems<br>
slide8. Challenges to the U.S. Health Care System5 The US has substantially higher healthcare prices compared to the other 12 countries
Has a fragmented care delivery system which
Promotes the duplication of resources and
Has an extensive use of poorly coordinated healthcare specialists<br>
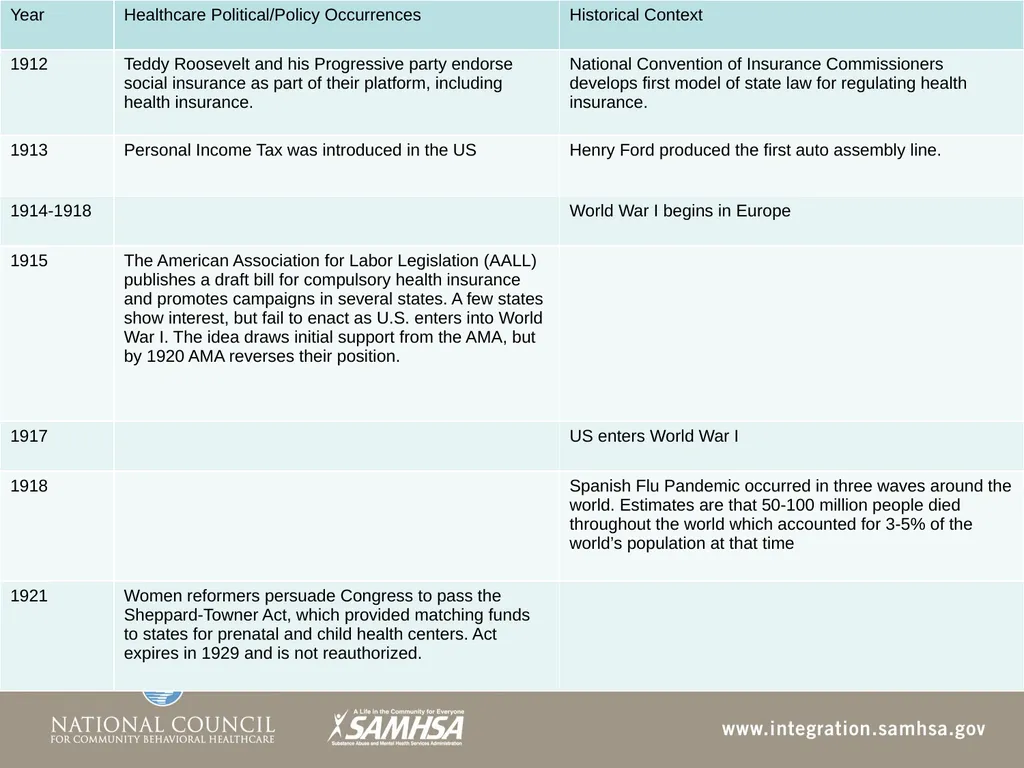
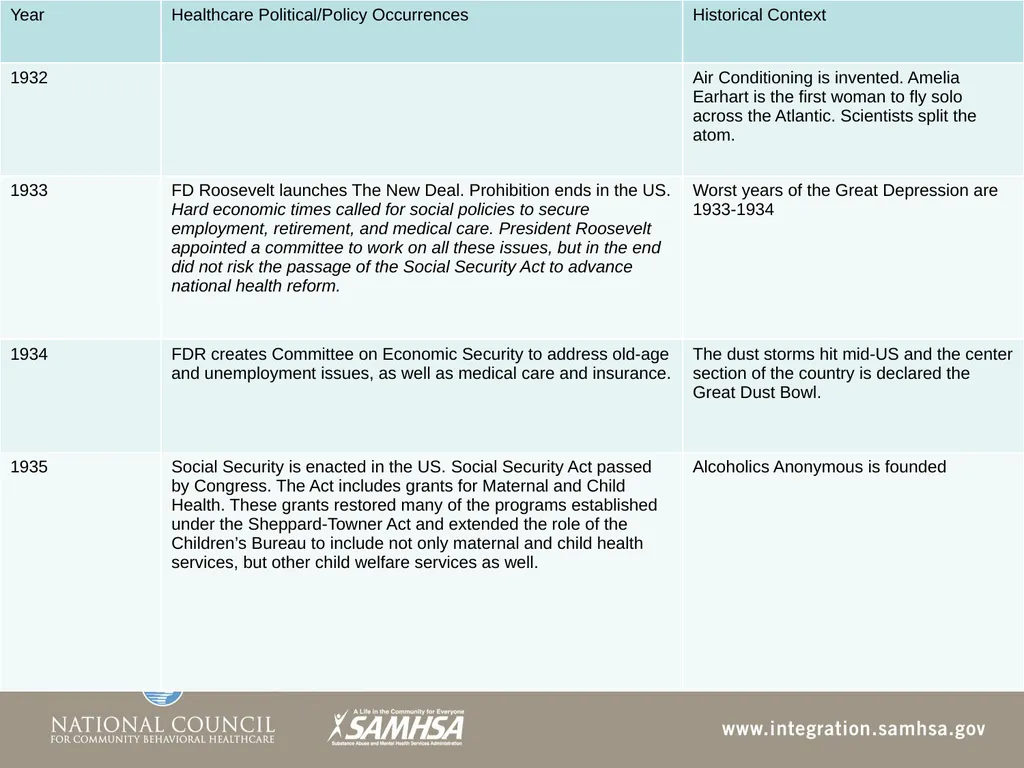
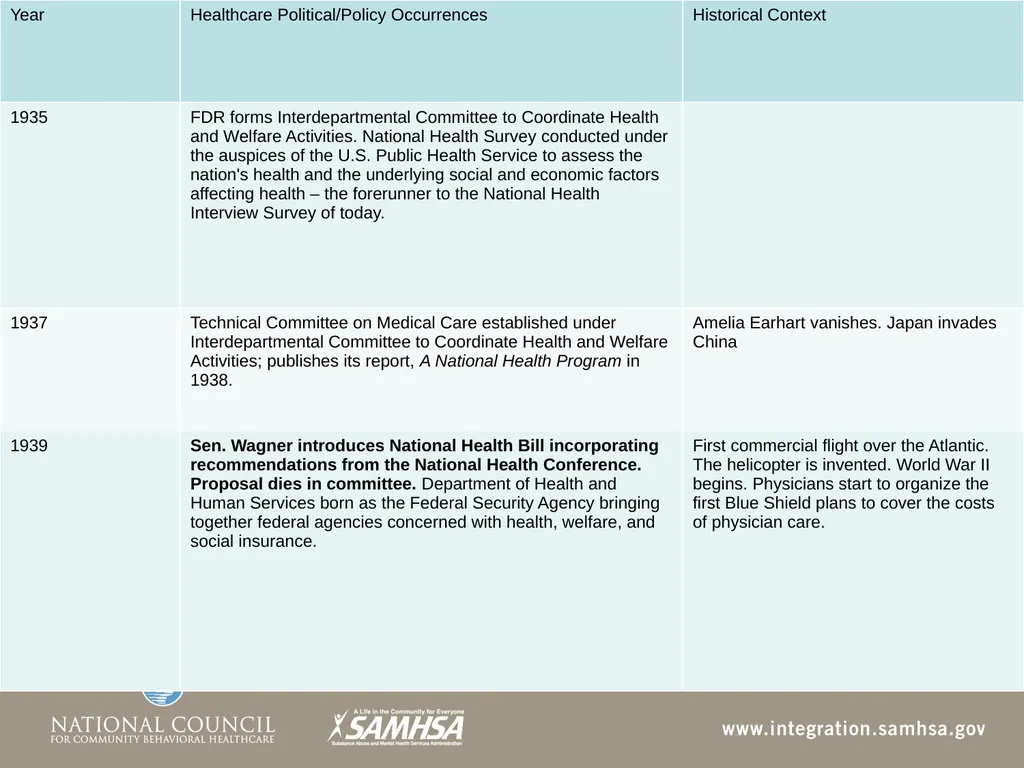
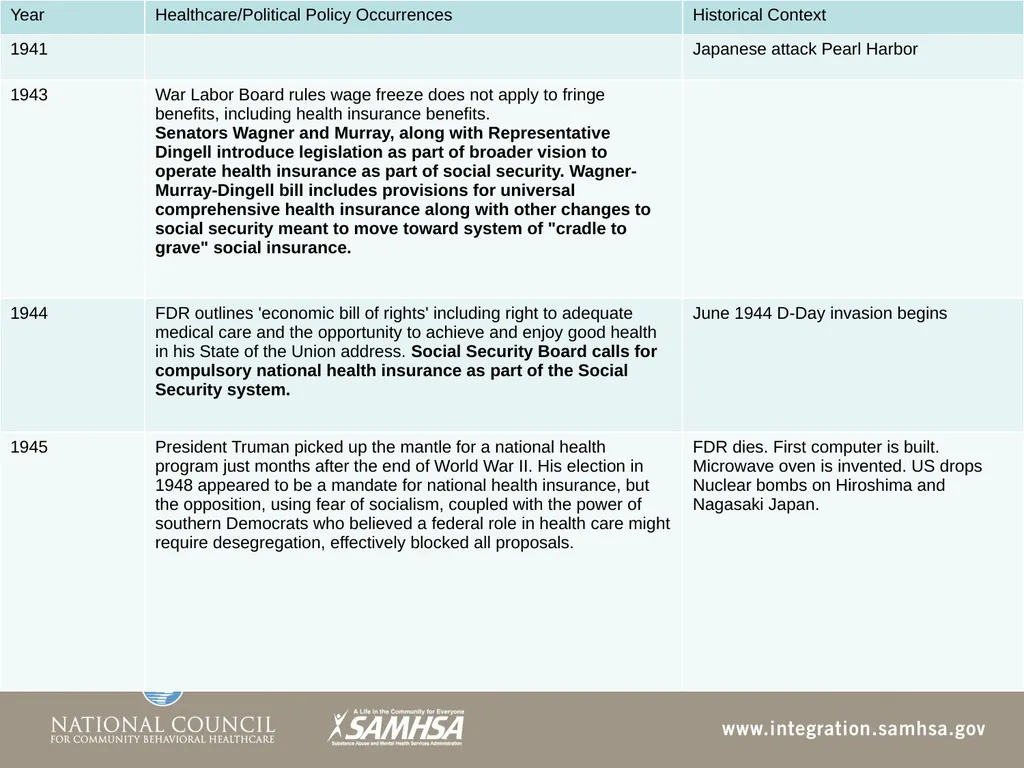
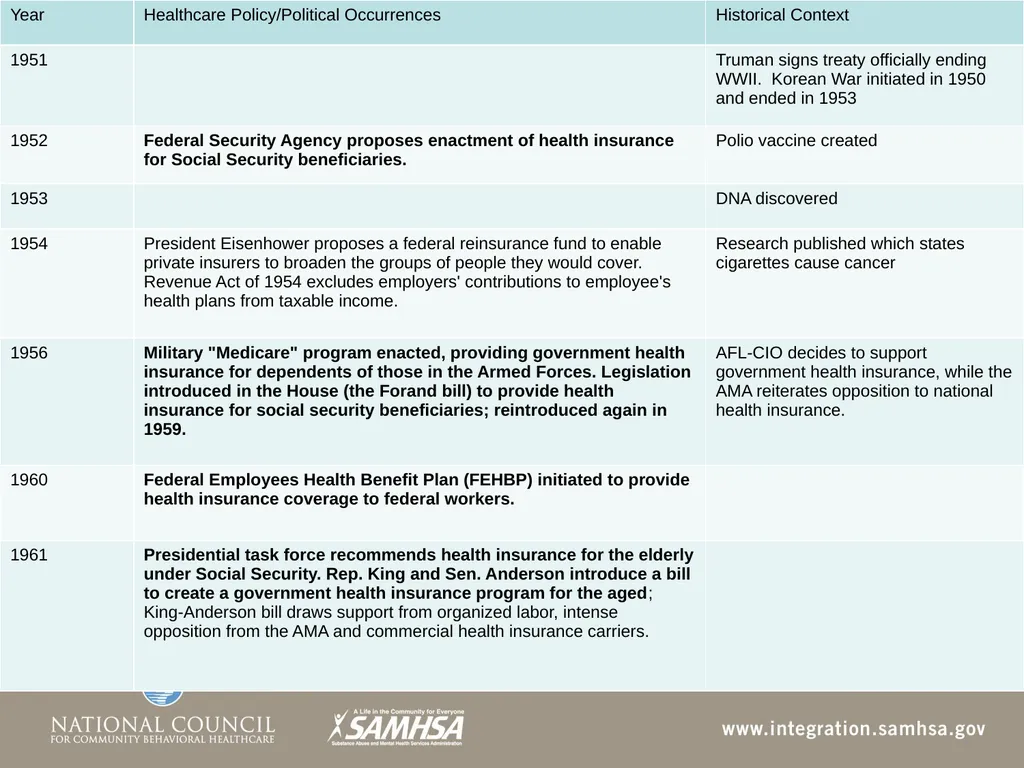
slide9. 100 Years in the Making In 1912, Teddy Roosevelt advocated for the concept of Social Insurance, which included healthcare insurance
As world events and US events unfolded through time, healthcare in various iterations has been a topic of national interest, gained and lost political attention
After the results of nearly 100 years of discourse on the topic, the Affordable Healthcare Act was passed into law in 2010 and upheld by the Supreme Court in 2012<br>
slide10. Timeline – Political context for health care reform<br>
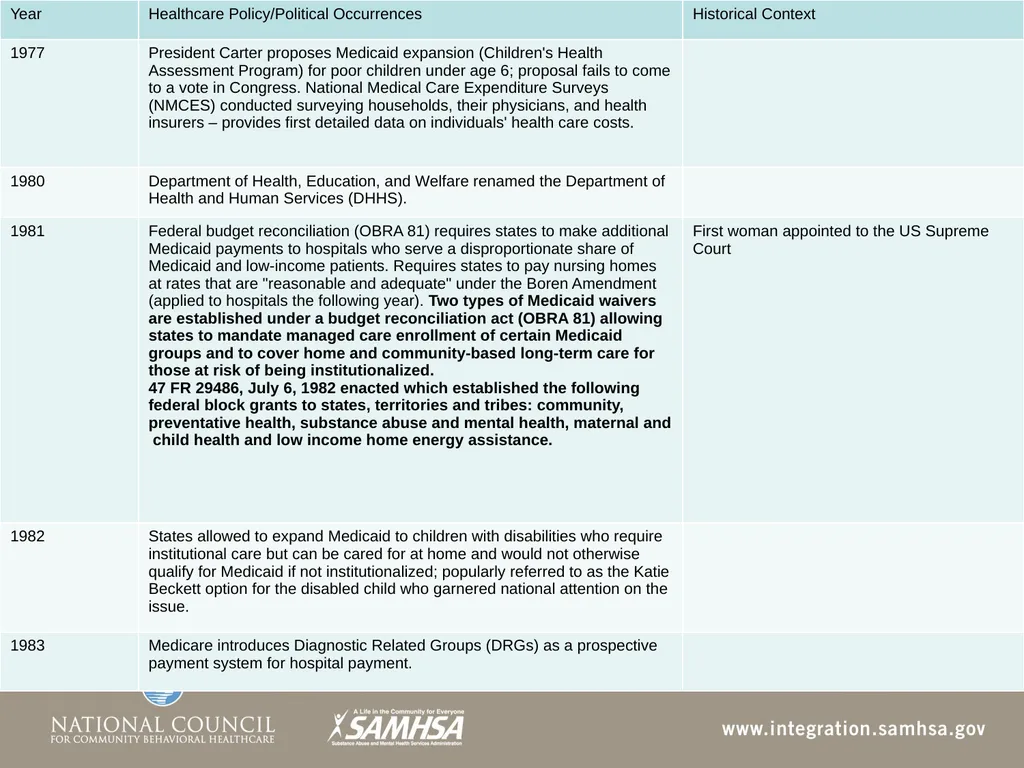
slide27. TIMELINE: Significant US Healthcare Policy Changes<br>
slide28. Bi-furcated System The “haves” and the “have not's” Prior to 1981, coverage for health care was paid for by individuals in the following manner:
Health insurance was a benefit paid for by employers
Individuals who did not have employer sponsored healthcare and could afford to pay for healthcare paid cash
Individuals who could not afford healthcare were served in social service programs, charities or ended up in hospitals when their conditions out of necessity
Out of necessity to cover healthcare costs for medically indigent and low income, the federal government created the range of federal block grants to the state
This action, which occurred in 1981 marked the beginning of a two tiered payment system for healthcare in the US
Public/private<br>
slide29. Patient Protections and Electronic Records Existing laws influence how PPACA handles issues of confidentiality and patient protections with regards to their health records
Three major federal laws which govern the sharing of patient information
HIPAA applies to the information sharing for all medical records. 1995
HITECH ACT applies to health information technology including hardware, software and integrated technologies or licenses, intellectual property, upgrades or packaged solutions sold as services that are designed for or support the use by health care entities or patients for the electronic creation, maintenance, access or exchange of health information 42 U.S.C. § 300jj(5). 2009
42 CFR, Part 2 applies only to alcohol and drug abuse patient records. 1975
Each state also has specific administrative rules and laws governing the sharing of private healthcare information and specifically information contained in alcohol and drug abuse records<br>
slide30. HITECH Health Information Technology for Economic and Clinical Health Act, or the HITECH Act was passed in 2009 as a part of the American Reinvestment and Recovery Act
Provided $18 billion through the Medicare and Medicaid reimbursement systems as incentives for hospitals and physicians who are “meaningful users” of EHR systems.
HITECH preserves the patient’s right to receive an electronic copy of their protected patient information from entities that use electronic health records and have restrictions on use and disclosure of protected health information
Stronger enforcement and penalties for those entities who violate HIPAA
Requirement that covered entities must notify individuals and in some cases, governmental officials when a breach of protected health information has occurred
Covered entities must revise their Notice of Privacy Practices to bring them into compliance with HITECH requirements.
Business Associate agreements must be updated to include the HITECH requirements<br>
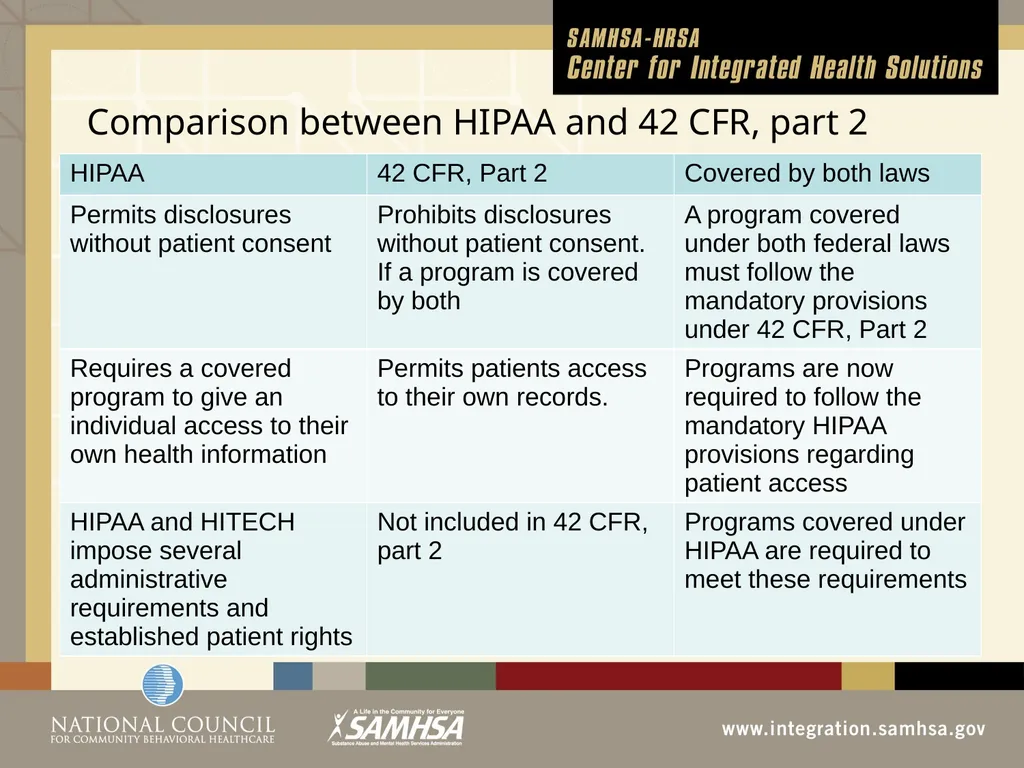
slide31. When is it HIPAA and when is it 42 CFR, Part 2? HIPAA covers any health information that identifies an individual
42 CFR, Part 2 only protects information that identifies an individual as having an alcohol or drug abuse issue.
Additionally, 42 CFR, Part 2 only applies to programs that accept any government funds.<br>
slide32. Comparison between HIPAA and 42 CFR, part 2<br>
slide33. Determining if a Program is Covered Under HIPAA, 42 CFR, part 2 or Both<br>
slide34. What Information is Protected?<br>
slide35. Defining Disclosure<br>
slide36. Relationship to State Law<br>
slide37. When Information can be Disclosed<br>
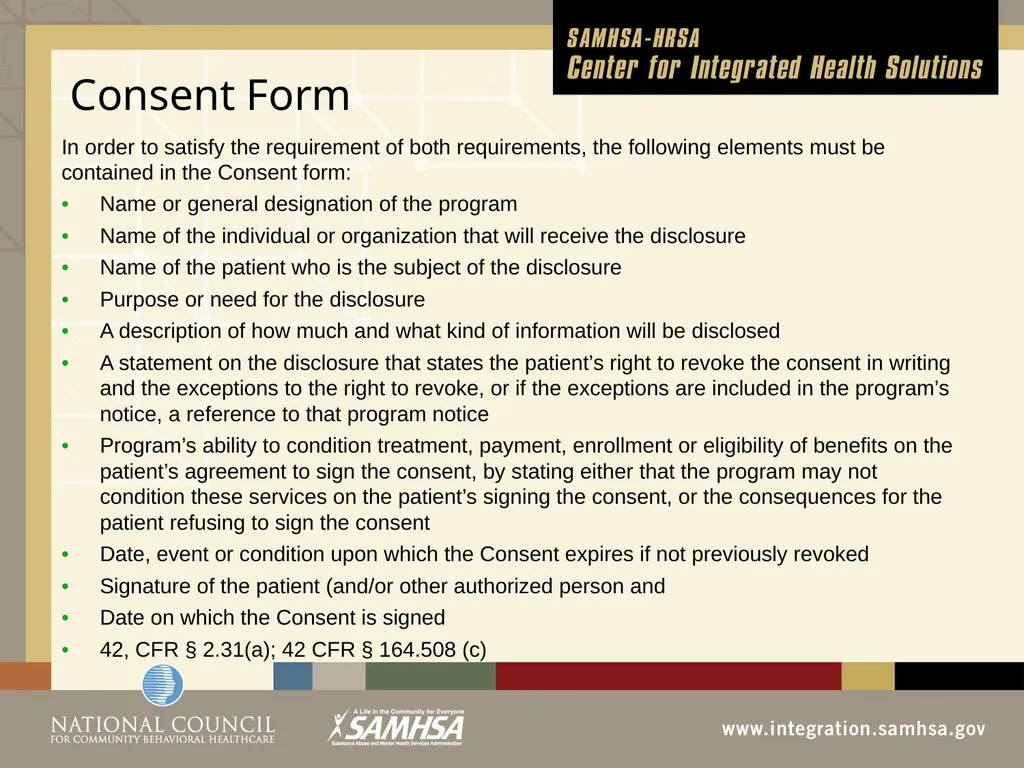
slide38. Consent Form In order to satisfy the requirement of both requirements, the following elements must be contained in the Consent form:
Name or general designation of the program
Name of the individual or organization that will receive the disclosure
Name of the patient who is the subject of the disclosure
Purpose or need for the disclosure
A description of how much and what kind of information will be disclosed
A statement on the disclosure that states the patient’s right to revoke the consent in writing and the exceptions to the right to revoke, or if the exceptions are included in the program’s notice, a reference to that program notice
Program’s ability to condition treatment, payment, enrollment or eligibility of benefits on the patient’s agreement to sign the consent, by stating either that the program may not condition these services on the patient’s signing the consent, or the consequences for the patient refusing to sign the consent
Date, event or condition upon which the Consent expires if not previously revoked
Signature of the patient (and/or other authorized person and
Date on which the Consent is signed
42, CFR § 2.31(a); 42 CFR § 164.508 (c)<br>
slide39. More Differences Between HIPAA and 42 CFR, Part 2 Special rules when a patient’s participation in a program is an official condition of probation, parole, sentence, dismissal of charges, release from prison or other criminal disposition:
Proper consent form is required to be signed by the patient but Consent can be made irrevocable until a certain specified disposition of the criminal proceedings
Information obtained related to a treatment stay can be used only in connection with the recipient’s official duty with respect to the specific criminal situation and cannot be used by anyone else to pursue new charges or to charge new individuals in new cases<br>
slide40. Managed Care Challenges<br>
slide41. Protecting SA Records<br>
slide42. References Code of Federal Regulations, 42 CFR, Part 2. Retrieved from http://ecfr.gpoaccess.gov/cgi/t/text/text-idx?c=ecfr&tpl=/ecfrbrowse/Title42/42cfr2_main_02.tpl
Conover, L.O., Tarasoff vs. California Board of Regents. Public Health Law and Ethics: A Reader, Copyright © 2002. Retrieved from http://www.publichealthlaw.net/Reader/docs/Tarasoff.pdf
HHS, HS settles HIPAA case with BCBST for $1.5 million, March 2012. Retrieved from http://www.hhs.gov/news/press/2012pres/03/20120313a.html
HIPAA regulations. Retrieved from http://ecfr.gpoaccess.gov/cgi/t/text/text-idx?c=ecfr&tpl=/ecfrbrowse/Title45/45cfr164_main_02.tpl
HITECH ACT. Retrieved from: http://www.hipaasurvivalguide.com/hitech-act-text.php
Legal Action Center (2012). Confidentiality and Communication, 2012 Edition, Legal Action Center of the City of New York, Inc. Copyright, 2012.
Squires, D.A. (2011). The US health system in perspective: A comparison of 12 industrialized nations, Issues in International Health Policy, Commonwealth Fund pub. 1532, 16.
Supreme Court decision on the Patient Protection and the Affordable Healthcare Act (2012). Retrieved from http://www.supremecourt.gov/opinions/11pdf/11-393c3a2.pdf
Tarasoff vs. California Board of Regents. Retrieved from http://www.publichealthlaw.net/Reader/docs/Tarasoff.pdf<br>
Cynthia M. Wiford, MRC, CCS, LCAS
Addiction Consulting and Training Associates (ACT), LLC<br>
slide2. Learning Objectives Draw a comparison between the US healthcare system to healthcare in other countries
Introduce the historical context for US healthcare reform efforts
Develop an awareness of the bifurcated healthcare system currently in existence
Provide a summary of the issues regarding patient protections and electronic records<br>
slide3. How the U.S. Health Care System Compares The US continues to outspend all other industrialized countries on healthcare
In 2008, medical expenses were $7538 per capita
Spent 16% of its gross domestic product on healthcare
Has far more private source funding on healthcare than any of the other countries which rely on government or social service models rather than private insurance<br>
slide4. Source: OECD Health Data 2011 (June 2011). Average Health Care Spending per Capita, 1980–2009 Adjusted for differences in cost of living1 Dollars<br>
slide5. 5 Health Care Spending per Capita by Source of Funding, 2009 Adjusted for Differences in Cost of Living2 Dollars 7,960 4,363 4,218 3,978 3,722 3,487 3,445 2,878 2,983 5,352 5,144 *2008 Source: OECD Health Data 2011 (June 2011).<br>
slide6. Comparing Service Patterns3 The United States
has the fewest practicing physicians and lowest physician visits among any of the 12 nations in the study
Hospital admission rates are lower, stays shorter and costs higher
Has the highest drug utilization, prices and spending
More hospital admissions for chronic conditions<br>
slide7. Why U.S. Spends More on its Healthcare4 The usually cited reasons:
Aging population
Complexity of health care administrative system
Defensive as opposed to preventive healthcare
High rates of mal-practice insurance
The reality:
The US population is substantially younger in age than populations from other countries
The US has average or below average rates of chronic conditions
But these are not substantiated in the research as the reasons for the distinct discrepancies when drawing a comparison between the US and other healthcare systems<br>
slide8. Challenges to the U.S. Health Care System5 The US has substantially higher healthcare prices compared to the other 12 countries
Has a fragmented care delivery system which
Promotes the duplication of resources and
Has an extensive use of poorly coordinated healthcare specialists<br>
slide9. 100 Years in the Making In 1912, Teddy Roosevelt advocated for the concept of Social Insurance, which included healthcare insurance
As world events and US events unfolded through time, healthcare in various iterations has been a topic of national interest, gained and lost political attention
After the results of nearly 100 years of discourse on the topic, the Affordable Healthcare Act was passed into law in 2010 and upheld by the Supreme Court in 2012<br>
slide10. Timeline – Political context for health care reform<br>
slide27. TIMELINE: Significant US Healthcare Policy Changes<br>
slide28. Bi-furcated System The “haves” and the “have not's” Prior to 1981, coverage for health care was paid for by individuals in the following manner:
Health insurance was a benefit paid for by employers
Individuals who did not have employer sponsored healthcare and could afford to pay for healthcare paid cash
Individuals who could not afford healthcare were served in social service programs, charities or ended up in hospitals when their conditions out of necessity
Out of necessity to cover healthcare costs for medically indigent and low income, the federal government created the range of federal block grants to the state
This action, which occurred in 1981 marked the beginning of a two tiered payment system for healthcare in the US
Public/private<br>
slide29. Patient Protections and Electronic Records Existing laws influence how PPACA handles issues of confidentiality and patient protections with regards to their health records
Three major federal laws which govern the sharing of patient information
HIPAA applies to the information sharing for all medical records. 1995
HITECH ACT applies to health information technology including hardware, software and integrated technologies or licenses, intellectual property, upgrades or packaged solutions sold as services that are designed for or support the use by health care entities or patients for the electronic creation, maintenance, access or exchange of health information 42 U.S.C. § 300jj(5). 2009
42 CFR, Part 2 applies only to alcohol and drug abuse patient records. 1975
Each state also has specific administrative rules and laws governing the sharing of private healthcare information and specifically information contained in alcohol and drug abuse records<br>
slide30. HITECH Health Information Technology for Economic and Clinical Health Act, or the HITECH Act was passed in 2009 as a part of the American Reinvestment and Recovery Act
Provided $18 billion through the Medicare and Medicaid reimbursement systems as incentives for hospitals and physicians who are “meaningful users” of EHR systems.
HITECH preserves the patient’s right to receive an electronic copy of their protected patient information from entities that use electronic health records and have restrictions on use and disclosure of protected health information
Stronger enforcement and penalties for those entities who violate HIPAA
Requirement that covered entities must notify individuals and in some cases, governmental officials when a breach of protected health information has occurred
Covered entities must revise their Notice of Privacy Practices to bring them into compliance with HITECH requirements.
Business Associate agreements must be updated to include the HITECH requirements<br>
slide31. When is it HIPAA and when is it 42 CFR, Part 2? HIPAA covers any health information that identifies an individual
42 CFR, Part 2 only protects information that identifies an individual as having an alcohol or drug abuse issue.
Additionally, 42 CFR, Part 2 only applies to programs that accept any government funds.<br>
slide32. Comparison between HIPAA and 42 CFR, part 2<br>
slide33. Determining if a Program is Covered Under HIPAA, 42 CFR, part 2 or Both<br>
slide34. What Information is Protected?<br>
slide35. Defining Disclosure<br>
slide36. Relationship to State Law<br>
slide37. When Information can be Disclosed<br>
slide38. Consent Form In order to satisfy the requirement of both requirements, the following elements must be contained in the Consent form:
Name or general designation of the program
Name of the individual or organization that will receive the disclosure
Name of the patient who is the subject of the disclosure
Purpose or need for the disclosure
A description of how much and what kind of information will be disclosed
A statement on the disclosure that states the patient’s right to revoke the consent in writing and the exceptions to the right to revoke, or if the exceptions are included in the program’s notice, a reference to that program notice
Program’s ability to condition treatment, payment, enrollment or eligibility of benefits on the patient’s agreement to sign the consent, by stating either that the program may not condition these services on the patient’s signing the consent, or the consequences for the patient refusing to sign the consent
Date, event or condition upon which the Consent expires if not previously revoked
Signature of the patient (and/or other authorized person and
Date on which the Consent is signed
42, CFR § 2.31(a); 42 CFR § 164.508 (c)<br>
slide39. More Differences Between HIPAA and 42 CFR, Part 2 Special rules when a patient’s participation in a program is an official condition of probation, parole, sentence, dismissal of charges, release from prison or other criminal disposition:
Proper consent form is required to be signed by the patient but Consent can be made irrevocable until a certain specified disposition of the criminal proceedings
Information obtained related to a treatment stay can be used only in connection with the recipient’s official duty with respect to the specific criminal situation and cannot be used by anyone else to pursue new charges or to charge new individuals in new cases<br>
slide40. Managed Care Challenges<br>
slide41. Protecting SA Records<br>
slide42. References Code of Federal Regulations, 42 CFR, Part 2. Retrieved from http://ecfr.gpoaccess.gov/cgi/t/text/text-idx?c=ecfr&tpl=/ecfrbrowse/Title42/42cfr2_main_02.tpl
Conover, L.O., Tarasoff vs. California Board of Regents. Public Health Law and Ethics: A Reader, Copyright © 2002. Retrieved from http://www.publichealthlaw.net/Reader/docs/Tarasoff.pdf
HHS, HS settles HIPAA case with BCBST for $1.5 million, March 2012. Retrieved from http://www.hhs.gov/news/press/2012pres/03/20120313a.html
HIPAA regulations. Retrieved from http://ecfr.gpoaccess.gov/cgi/t/text/text-idx?c=ecfr&tpl=/ecfrbrowse/Title45/45cfr164_main_02.tpl
HITECH ACT. Retrieved from: http://www.hipaasurvivalguide.com/hitech-act-text.php
Legal Action Center (2012). Confidentiality and Communication, 2012 Edition, Legal Action Center of the City of New York, Inc. Copyright, 2012.
Squires, D.A. (2011). The US health system in perspective: A comparison of 12 industrialized nations, Issues in International Health Policy, Commonwealth Fund pub. 1532, 16.
Supreme Court decision on the Patient Protection and the Affordable Healthcare Act (2012). Retrieved from http://www.supremecourt.gov/opinions/11pdf/11-393c3a2.pdf
Tarasoff vs. California Board of Regents. Retrieved from http://www.publichealthlaw.net/Reader/docs/Tarasoff.pdf<br>