
The Great Recession & Fiscal Allocation for Public











Description: The Great Recession Fiscal Allocation for Public Health: How Has Our Slice of The Pie Changed? Authors J. Mac McCullough, PhD, MPH Assistant Professor School for the Science of Health Care Delivery Arizona State University JP Leider, PhD
Related Topics
Download Presentation
"The Great Recession & Fiscal Allocation for Public" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. The Great Recession &
Fiscal Allocation for Public Health:
How Has Our Slice of The Pie Changed?<br>
slide2. Authors J. Mac McCullough, PhD, MPH Assistant Professor School for the Science of Health Care Delivery Arizona State University
JP Leider, PhD Consultant, JP Leider Consulting LLC
Gulzar Shah, PhD, MStat, MS Associate Dean for Research & Associate Professor Jiann-Ping Hsu College of Public Health Georgia Southern University<br>
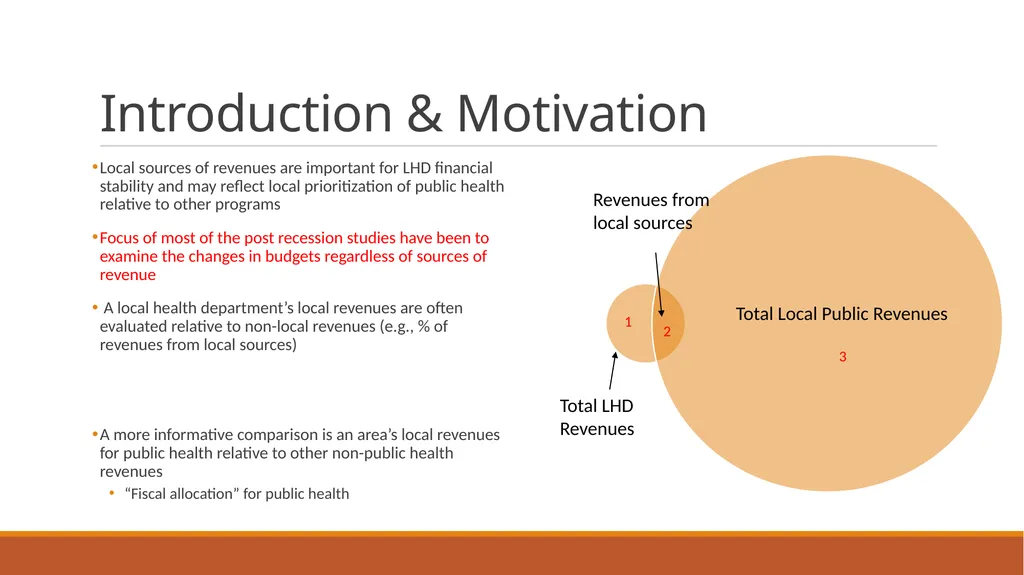
slide3. Introduction & Motivation Local sources of revenues are important for LHD financial stability and may reflect local prioritization of public health relative to other programs
Focus of most of the post recession studies have been to examine the changes in budgets regardless of sources of revenue
A local health department’s local revenues are often evaluated relative to non-local revenues (e.g., % of revenues from local sources)
A more informative comparison is an area’s local revenues for public health relative to other non-public health revenues
“Fiscal allocation” for public health Total LHD Revenues Revenues from local sources Total Local Public Revenues 1 2 3<br>
slide4. Research Question What is the local fiscal allocation for public health as of 2008?
What organizational or jurisdictional factors are associated with higher fiscal allocation?
How has fiscal allocation for public health changed since before the Great Recession?
What organizational or jurisdictional factors are associated with higher levels of fiscal allocation retention?
Especially important at the extremes (what separates the big gains from the big declines?)<br>
slide5. Methods Data sources:
Local governmental revenue data from U.S. Census of Local Governments (2007 & 2012)
Contains geographic and financial data on 87,000 local governments (cities, counties, school districts, special districts, etc.)
LHD data from NACCHO Profile survey (2008 & 2013)
Matched using FIPS codes, excluded LHDs with missing/unreliable expenditure data
# LHDs in sample in both years: n = 983 LHDs
Outcome of interest:
Fiscal Allocation = (Total LHD Local Revenue) ÷ (Total Local taxes for corresponding local governments)
Local revenue expenditure data self-reported to NACCHO by LHDs
Local taxes include: property taxes, other collected taxes, fees, fines
2007, 2012, and change between 07-12
Univariate, bivariate, multivariate analyses
Also compute models stratified by level of long-term debt<br>
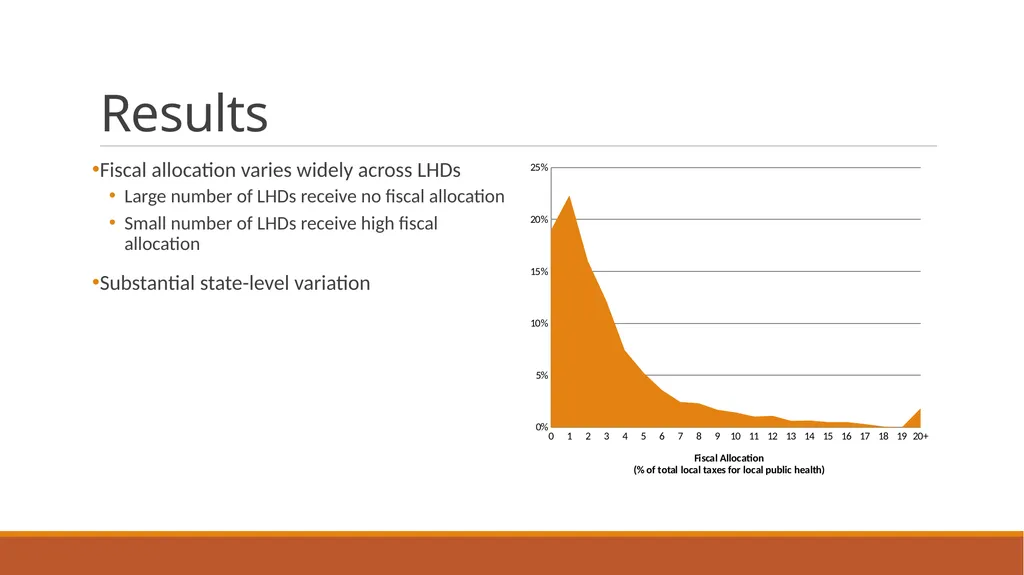
slide6. Results Fiscal allocation varies widely across LHDs
Large number of LHDs receive no fiscal allocation
Small number of LHDs receive high fiscal allocation
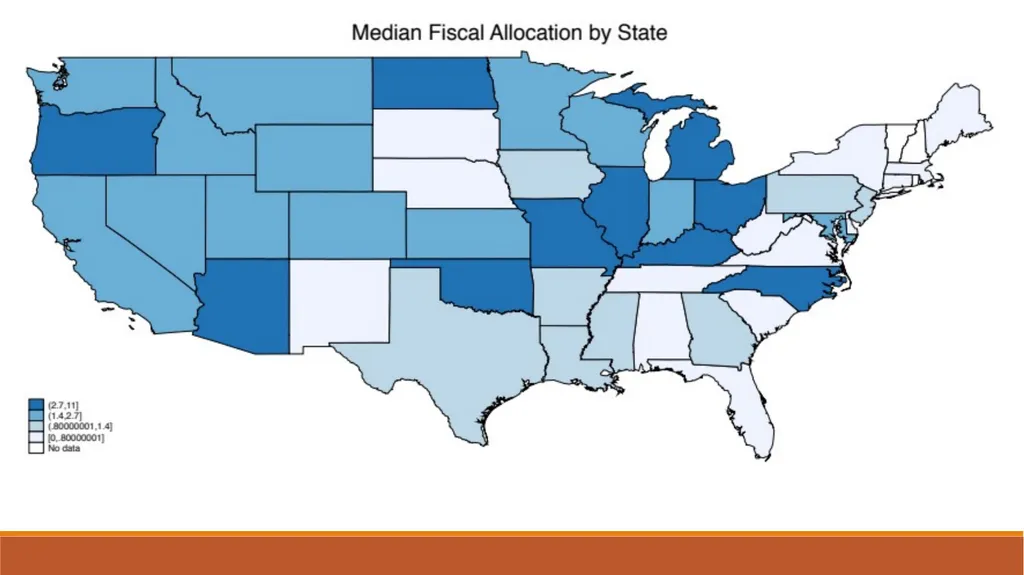
Substantial state-level variation<br>
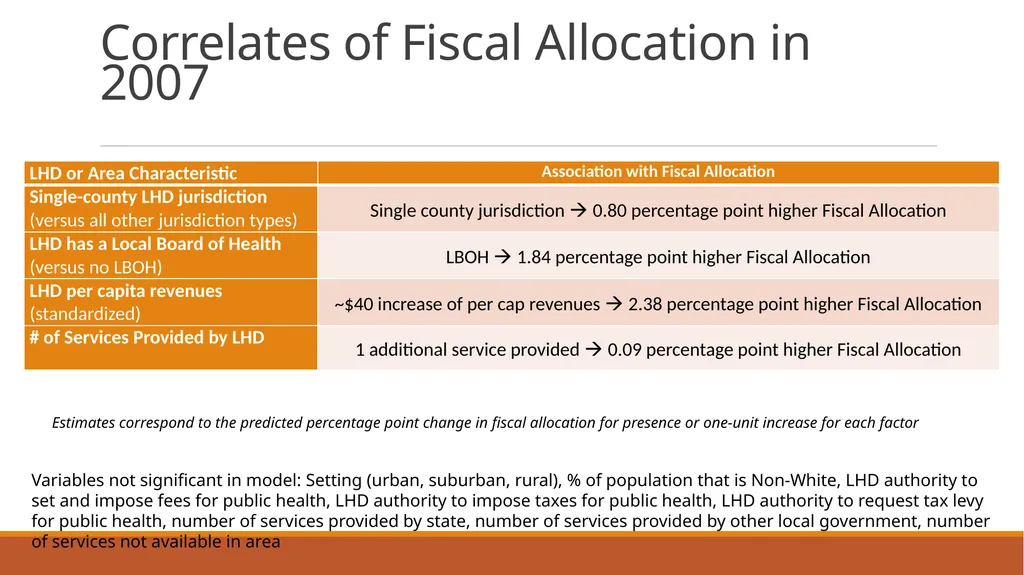
slide7. Correlates of Fiscal Allocation in 2007 Variables not significant in model: Setting (urban, suburban, rural), % of population that is Non-White, LHD authority to set and impose fees for public health, LHD authority to impose taxes for public health, LHD authority to request tax levy for public health, number of services provided by state, number of services provided by other local government, number of services not available in area Estimates correspond to the predicted percentage point change in fiscal allocation for presence or one-unit increase for each factor<br>
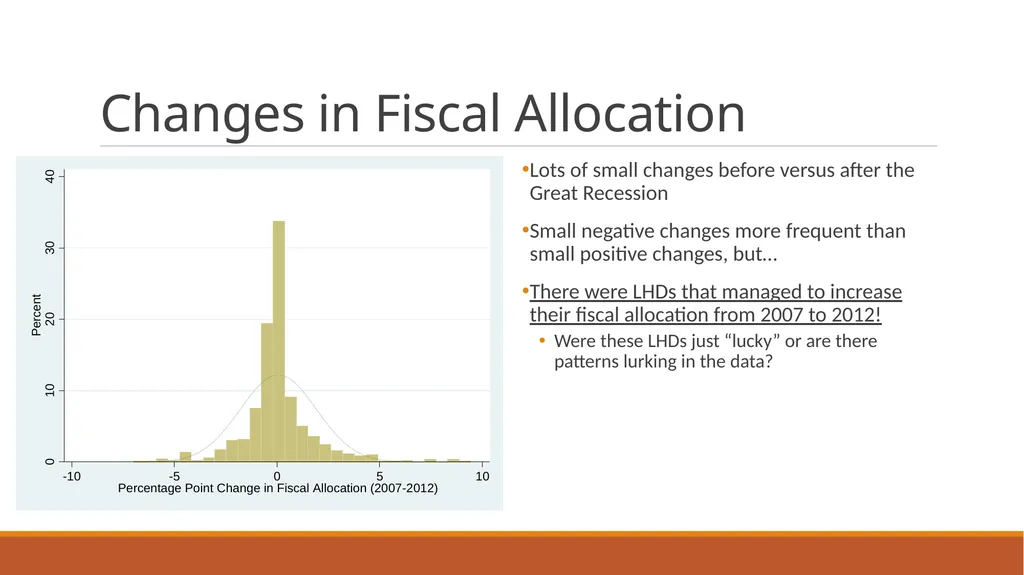
slide8. Changes in Fiscal Allocation Lots of small changes before versus after the Great Recession
Small negative changes more frequent than small positive changes, but…
There were LHDs that managed to increase their fiscal allocation from 2007 to 2012!
Were these LHDs just “lucky” or are there patterns lurking in the data?<br>
slide9. Correlates of Changes in Fiscal Allocation Factors associated with increased likelihood of having a “large” decline in FA from 2007-12:
Higher percent population served that is non-white (OR = 1.02*)
Greater number of public health activities provided by the state health department (OR = 1.05**)
Higher baseline fiscal allocation (OR = 1.09**)
Factors associated with lower likelihood of having a “large” decline in FA from 2007-12:
Greater number of public health activities provided by the local health department (OR = 0.97**)
Other factors included in the model (not significantly associated)
Urban/Suburban/Rural; Population served; Single-county jurisdiction; Presence of LBOH; Per capita expenditures; Jurisdictional authority to levy taxes for public health; Number of public health activities provided by other entities; Number of public health activities not available in jurisdiction.<br>
slide10. Correlates of Changes in Fiscal Allocation Previous slide discussed likelihood of “large” changes (> |25%|). What about smaller changes?
In addition to previous (% jurisdiction that is non-white, # PH activities provided by LHD and by state): Compared to rural LHDs, urban LHDs had larger declines
BUT, area’s Long-Term Debt serves as moderator to many of these relationships!
Association between percent non-white and decline in FA only holds in areas with high debt
Associations between state and local service provision and changes in FA only hold in areas with low debt
In addition, suburban LHDs and jurisdictions with the ability to set and impose fees for public health saw gains in FA compared to their counterparts.<br>
slide11. Implications & Next Steps<br>
slide12. Fiscal Allocation for LHDs Fiscal allocation for public health averages approximately 3.3% of all local governmental “own revenues”
High variation within and between states
The Great Recession not only resulted in a smaller overall pie, but public health now receives a smaller piece of that pie.<br>
slide13. Takeaways for Practitioners & Implications for Health Equity A range of factors are associated with levels of fiscal allocation for public health
LHD jurisdiction type, governance, expenditures, service provision
Some are amenable to LHD leadership intervention (e.g., service provision), others are harder to impact
From health equity and disparities perspective:
Findings that areas with high proportion of non-white population and high levels of long-term debt were prone to declines in FA during the Great Recession may be concerning.
Suburban LHDs, those able to set their own fees, and those providing higher number of direct services tended to fare better.<br>
slide14. Impacts of Long-Term Debt on LHDs Anecdotally, we generally understand that very high levels of long-term debt is bad
Less room for other priorities
Less flexibility to match current needs
Public health is not immune An area’s long-term debt level is extremely important
Areas with high long-term debt tend to have lower fiscal allocation for public health
Only know which levers are relevant/effective after considering long-term debt
Take Away
Researchers: also consider additional financial measures beyond per capita revenue
Policy Makers: what local tax and debt conditions are most conducive to advocacy for increased funding? What areas may be especially prone to erosion of local funding during future economic recessions?<br>
slide15. Thank You Questions? mccullough@asu.edu<br>
slide2. Authors J. Mac McCullough, PhD, MPH Assistant Professor School for the Science of Health Care Delivery Arizona State University
JP Leider, PhD Consultant, JP Leider Consulting LLC
Gulzar Shah, PhD, MStat, MS Associate Dean for Research & Associate Professor Jiann-Ping Hsu College of Public Health Georgia Southern University<br>
slide3. Introduction & Motivation Local sources of revenues are important for LHD financial stability and may reflect local prioritization of public health relative to other programs
Focus of most of the post recession studies have been to examine the changes in budgets regardless of sources of revenue
A local health department’s local revenues are often evaluated relative to non-local revenues (e.g., % of revenues from local sources)
A more informative comparison is an area’s local revenues for public health relative to other non-public health revenues
“Fiscal allocation” for public health Total LHD Revenues Revenues from local sources Total Local Public Revenues 1 2 3<br>
slide4. Research Question What is the local fiscal allocation for public health as of 2008?
What organizational or jurisdictional factors are associated with higher fiscal allocation?
How has fiscal allocation for public health changed since before the Great Recession?
What organizational or jurisdictional factors are associated with higher levels of fiscal allocation retention?
Especially important at the extremes (what separates the big gains from the big declines?)<br>
slide5. Methods Data sources:
Local governmental revenue data from U.S. Census of Local Governments (2007 & 2012)
Contains geographic and financial data on 87,000 local governments (cities, counties, school districts, special districts, etc.)
LHD data from NACCHO Profile survey (2008 & 2013)
Matched using FIPS codes, excluded LHDs with missing/unreliable expenditure data
# LHDs in sample in both years: n = 983 LHDs
Outcome of interest:
Fiscal Allocation = (Total LHD Local Revenue) ÷ (Total Local taxes for corresponding local governments)
Local revenue expenditure data self-reported to NACCHO by LHDs
Local taxes include: property taxes, other collected taxes, fees, fines
2007, 2012, and change between 07-12
Univariate, bivariate, multivariate analyses
Also compute models stratified by level of long-term debt<br>
slide6. Results Fiscal allocation varies widely across LHDs
Large number of LHDs receive no fiscal allocation
Small number of LHDs receive high fiscal allocation
Substantial state-level variation<br>
slide7. Correlates of Fiscal Allocation in 2007 Variables not significant in model: Setting (urban, suburban, rural), % of population that is Non-White, LHD authority to set and impose fees for public health, LHD authority to impose taxes for public health, LHD authority to request tax levy for public health, number of services provided by state, number of services provided by other local government, number of services not available in area Estimates correspond to the predicted percentage point change in fiscal allocation for presence or one-unit increase for each factor<br>
slide8. Changes in Fiscal Allocation Lots of small changes before versus after the Great Recession
Small negative changes more frequent than small positive changes, but…
There were LHDs that managed to increase their fiscal allocation from 2007 to 2012!
Were these LHDs just “lucky” or are there patterns lurking in the data?<br>
slide9. Correlates of Changes in Fiscal Allocation Factors associated with increased likelihood of having a “large” decline in FA from 2007-12:
Higher percent population served that is non-white (OR = 1.02*)
Greater number of public health activities provided by the state health department (OR = 1.05**)
Higher baseline fiscal allocation (OR = 1.09**)
Factors associated with lower likelihood of having a “large” decline in FA from 2007-12:
Greater number of public health activities provided by the local health department (OR = 0.97**)
Other factors included in the model (not significantly associated)
Urban/Suburban/Rural; Population served; Single-county jurisdiction; Presence of LBOH; Per capita expenditures; Jurisdictional authority to levy taxes for public health; Number of public health activities provided by other entities; Number of public health activities not available in jurisdiction.<br>
slide10. Correlates of Changes in Fiscal Allocation Previous slide discussed likelihood of “large” changes (> |25%|). What about smaller changes?
In addition to previous (% jurisdiction that is non-white, # PH activities provided by LHD and by state): Compared to rural LHDs, urban LHDs had larger declines
BUT, area’s Long-Term Debt serves as moderator to many of these relationships!
Association between percent non-white and decline in FA only holds in areas with high debt
Associations between state and local service provision and changes in FA only hold in areas with low debt
In addition, suburban LHDs and jurisdictions with the ability to set and impose fees for public health saw gains in FA compared to their counterparts.<br>
slide11. Implications & Next Steps<br>
slide12. Fiscal Allocation for LHDs Fiscal allocation for public health averages approximately 3.3% of all local governmental “own revenues”
High variation within and between states
The Great Recession not only resulted in a smaller overall pie, but public health now receives a smaller piece of that pie.<br>
slide13. Takeaways for Practitioners & Implications for Health Equity A range of factors are associated with levels of fiscal allocation for public health
LHD jurisdiction type, governance, expenditures, service provision
Some are amenable to LHD leadership intervention (e.g., service provision), others are harder to impact
From health equity and disparities perspective:
Findings that areas with high proportion of non-white population and high levels of long-term debt were prone to declines in FA during the Great Recession may be concerning.
Suburban LHDs, those able to set their own fees, and those providing higher number of direct services tended to fare better.<br>
slide14. Impacts of Long-Term Debt on LHDs Anecdotally, we generally understand that very high levels of long-term debt is bad
Less room for other priorities
Less flexibility to match current needs
Public health is not immune An area’s long-term debt level is extremely important
Areas with high long-term debt tend to have lower fiscal allocation for public health
Only know which levers are relevant/effective after considering long-term debt
Take Away
Researchers: also consider additional financial measures beyond per capita revenue
Policy Makers: what local tax and debt conditions are most conducive to advocacy for increased funding? What areas may be especially prone to erosion of local funding during future economic recessions?<br>
slide15. Thank You Questions? mccullough@asu.edu<br>