Search Results for 'date patient'
date patient published presentations and documents on DocSlides.


Patient Priorities / Issues
by faustina-dinatale
Comments
Agreed Actions
By Whom
Target date
Date...
de112 Sultanate of Oman OUT PATIENT REIMBURSEMENT CLAIM FORMPlease giv
by hanah
2 Name of the Patient 3 Name of the Employer 4 E...

x0000x00001 xMCIxD 0 xMCIxD 0 PATIENT INFORMATIONPlease take a few
by ava
FirstName Last NameHome PhoneCell PhoneEmailSex ...

VIDEOELECTRONYSTAGMOGRAPHY PATIENT INSTRUCTIONS
by molly
You have been referred to our office for an assess...

Annexure NSW Victoria Civil Interstate Apprehension Order REQUEST TO APPREHEND Date of birth GIVEN NAMES OF PATIENT FAMILY NAME BLOCK LETTERS OF PATIENT STATUS OF PATIENT Patient subject to the
by lois-ondreau
48 U Liable to apprehension under s43 Patient is a...
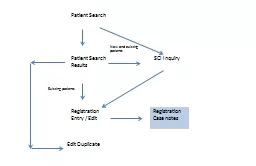
Patient Search Patient Search Results
by mitsue-stanley
Registration Entry / Edit. Registration Case note...

A Date of Initial Diagnosis Approach to Health Insurance
by mitsue-stanley
Presented to the SOUTHWEST ACTUARIAL FORUM. DECem...

Intake form last updated: 10//2019
by bubbleba
OR
Lung Injury
Caller Name
Organization
Phone Numb...




Camille A Graham MD Neil M Vora MD WhaJoon Lee MDName LastFirstDOB
by linda
Patient InformationSocial Security TDL Marital...


Spinraza Authorizatio FormPrescriptio Madication Required
by tremblay
to O Hom Ne Ne Healt Pla o Oregon Inc Ne Lit Insu...

Introduction Todays iNiOiniMlONPreferred Name CityStateZipAddressGend
by riley
History UisiOHY Major When /What Major Location Qu...


Reportable Diseases and Events are declared to be communicable andor
by barbara
ocal health department by all hospitals physicians...


I Date PATIENT REGISTRATION INFORMATION PLEASE PRINT D Mr O Mrs 0 Mi
by emmy
HEALTH HISTORY FORM FO GASTROENTEROLOGY ASSOCIATES...

TEXAS Health and Human Services Texas Department of State Health Servi
by osullivan
Infectious Disease Control Unit Texas Department o...

DENTAL CLAIM FORM FOR USE IF DENTAL PROVIDER WILL NOT Eligibility
by jordyn
EMPLOYEE AND PATIENT PORTION EMPLOYEES CONTRACT ...


Template for Ankle MRI-without contrast (italicized
by emmy
text indicates merged . fields). Patient . name. :...

Glasgow Clinical Trial Unit NHS GG&C Clinical Research Imaging Facility MANDATORY
by Princecharming
GUI 58.007A: CRIF Review of Incidental Findings (...


The Checklist must be completed fully and signed by both yourself and
by esther
The completed document should
be forwarded to uni...

x0000x0000Page of CLINICAL POLICYCare of the Mohs Surgery Patien
by callie
EFFECTIVE DATE:
April 9, 2021
B.PURPOSE
define the...
Tickborne Rickettsial Disease Case Report
by madison
Use for Spotted Fever Rickettsiosis (SFR) includin...




AUTHORIZATION TO RELEASEOBTAIN PATIENT INFORMATION
by dorothy
Form 01022HIM PatientLevel0921Page 1of 2200401AUTH...

PATIENT INFORMATION PATIENT146S LAST NAMEFIRSTMIDDLE NO HOME PHONE CE
by obrien
What is the chief complaint for which you came to ...