Innovative Health Financing in India: A Comparative Study of Three States Montu Bose TERI University Email: monbosegmail.com Arijita Dutta University of Calcutta Email: dutta.arijitagmail.com 6th IGC-Jadavpur University-ISI West Bengal
Related Topics
Share
Embed code
Download this presentation From Below
"Innovative Health Financing in India: A" is the property of its rightful owner. Permission is granted to
download and print the materials on this website for personal, non-commercial use only, and to display it
on your personal computer provided you do not modify the materials and that you retain all copyright
notices contained in the materials. By downloading content from our website, you accept the terms of this
agreement.
Presentation Transcript
01
Innovative Health Financing in India: A Comparative Study of Three States Montu Bose
TERI University
Email: monbose@gmail.com
&
Arijita Dutta
University of Calcutta
Email: dutta.arijita@gmail.com 6th IGC-Jadavpur University-ISI West Bengal Growth Conference, JU, 28th December 2016<br>
02
Background Over the years, public health spending has been low
NHA 2013-14: public spending on health is only 1.15% of GDP
A large share of OOP expenditure in total health spending
Medicine has the maximum share in total OOP spending 2<br>
03
Contd… NHM: strengthen the health system, universal access to affordable, equitable and quality health care
RSBY (CMCHIS): financial protection against high OOP expenditure, improve the access to quality healthcare service
Medicine: Tamil Nadu Medical Services Corporation (TNMSC), Rajasthan Medical Services Corporation (RMSC) & Fair Price Medicine Shop, West Bengal (FPMS) 3<br>
04
Nature of the Medicine Distribution Schemes Similarities:
All of them primarily aim to reduce OOPE on medicine and total OOPE
Target to increase utilization of medical services
Dissimilarities:
TN & Rajasthan offers huge subsidies on medicine supply in public sector, while in FPMS, there is no financial burden on the government
The former targets utilization only in public sector hospitals, while the latter has no such specifications. 4<br>
05
Objectives Study the utilization pattern of public in-patient care facilities for the three states
Examine the effectiveness of the strategies adopted by the states to arrest high OOP expenditure and
Analyze the extent of equity in public in-patient care services in the states 5<br>
06
Data National Sample Survey:
NSS 71st round (2014) – Social Consumption: Health
NSS 60th round (2004) – Morbidity & Health Care
DDGs – State Government (2015-16 Expenditure Budget – Department of Health & Family Welfare)
PIP – NHM (2013-14) 6<br>
07
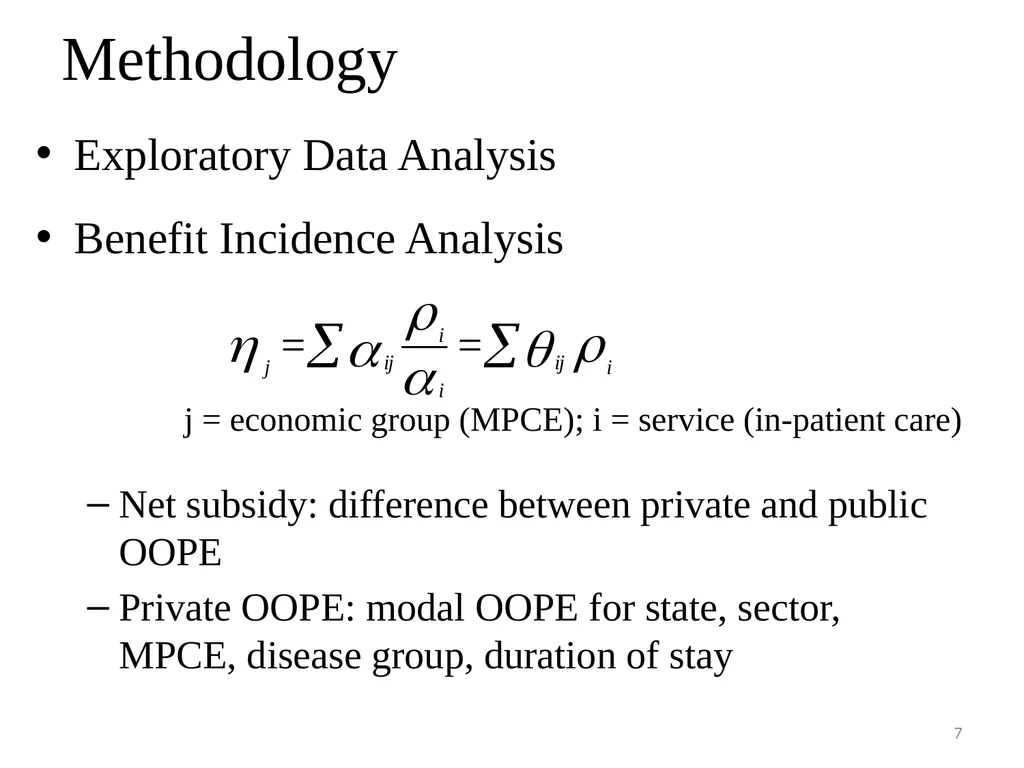
Methodology Exploratory Data Analysis
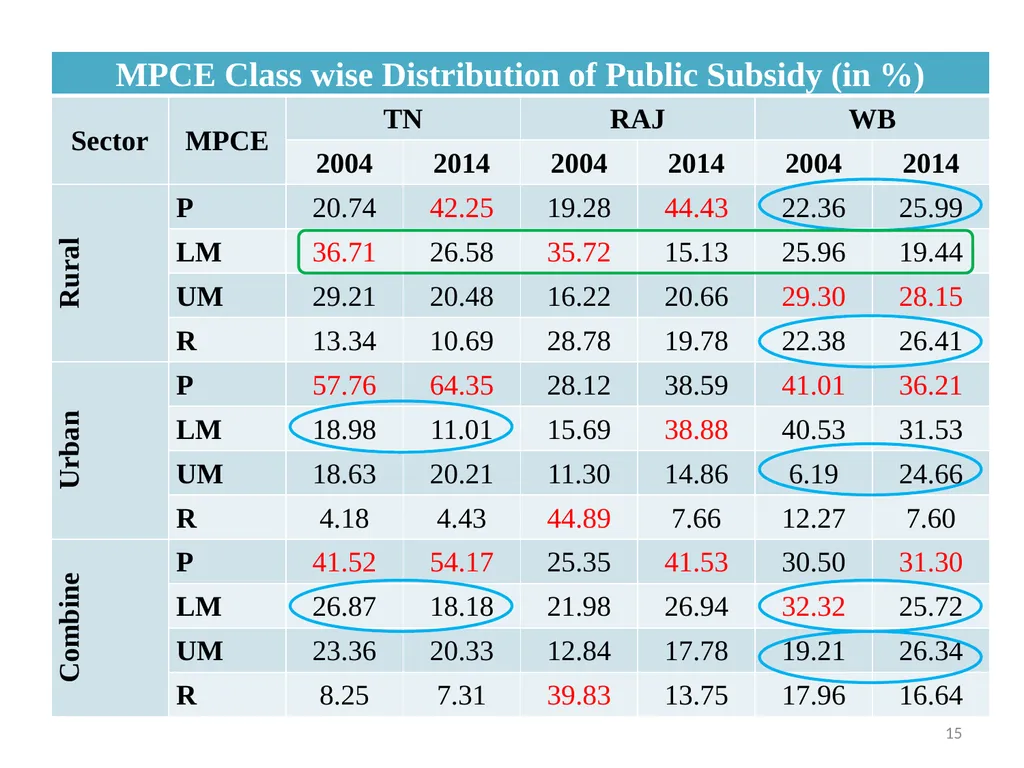
Benefit Incidence Analysis
j = economic group (MPCE); i = service (in-patient care)
Net subsidy: difference between private and public OOPE
Private OOPE: modal OOPE for state, sector, MPCE, disease group, duration of stay 7<br>
08
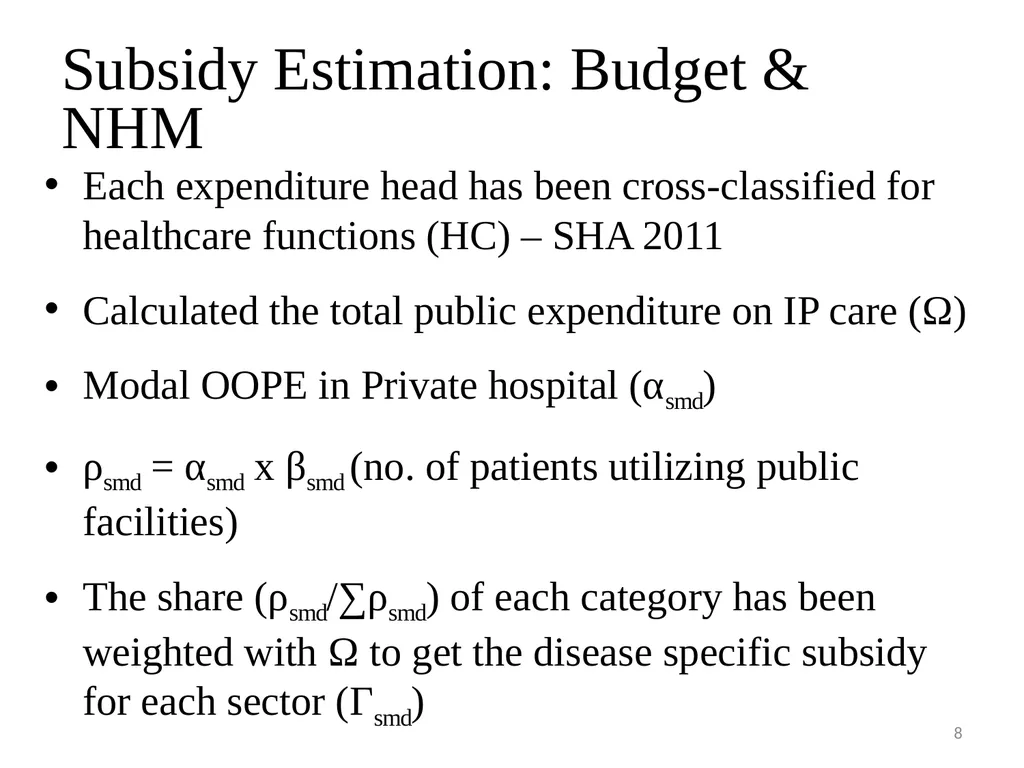
Subsidy Estimation: Budget & NHM Each expenditure head has been cross-classified for healthcare functions (HC) – SHA 2011
Calculated the total public expenditure on IP care (Ω)
Modal OOPE in Private hospital (αsmd)
ρsmd = αsmd x βsmd (no. of patients utilizing public facilities)
The share (ρsmd/∑ρsmd) of each category has been weighted with Ω to get the disease specific subsidy for each sector (Гsmd) 8<br>
09
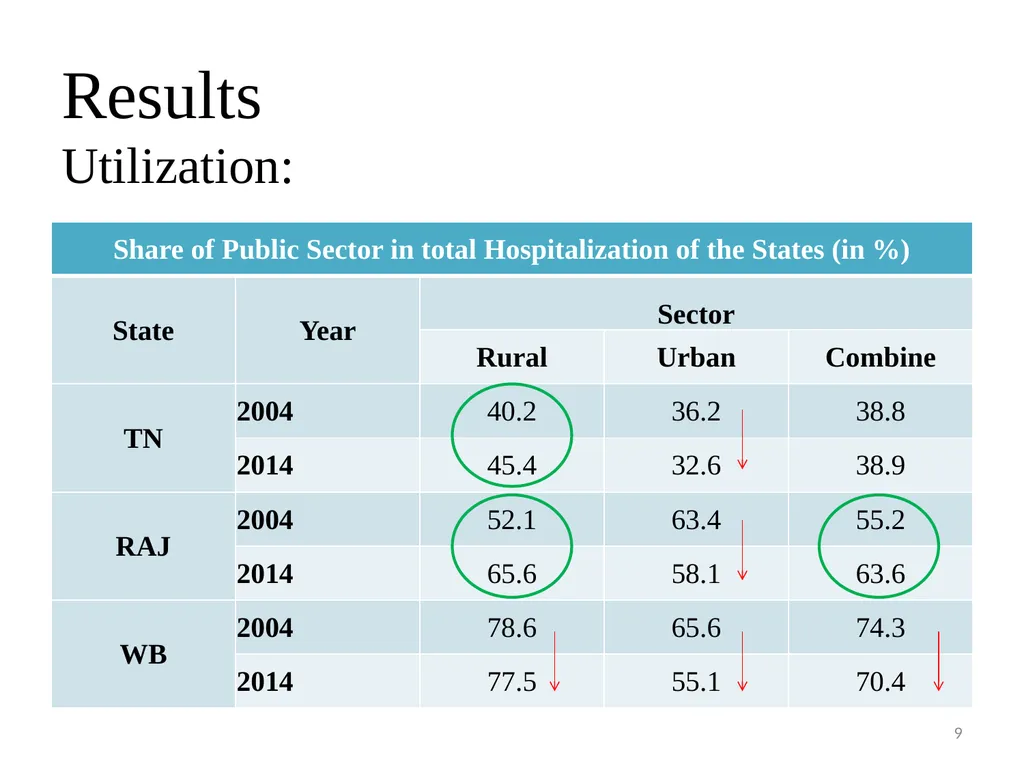
Results Utilization: 9<br>
10
10<br>
11
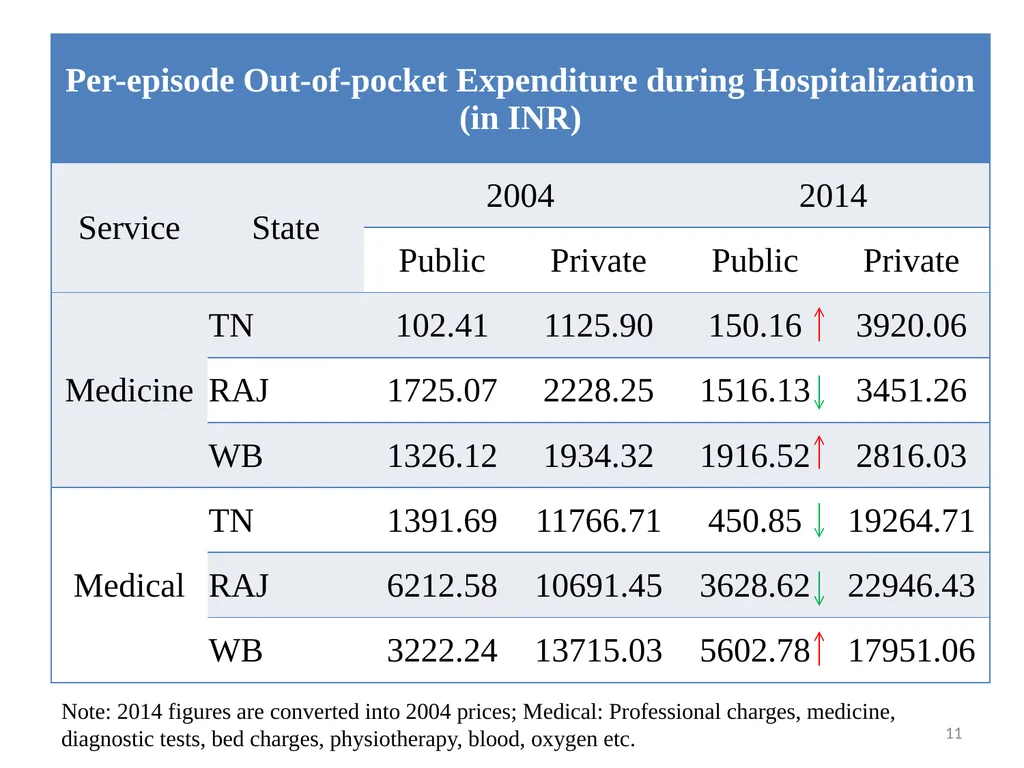
11 Note: 2014 figures are converted into 2004 prices; Medical: Professional charges, medicine, diagnostic tests, bed charges, physiotherapy, blood, oxygen etc.<br>
12
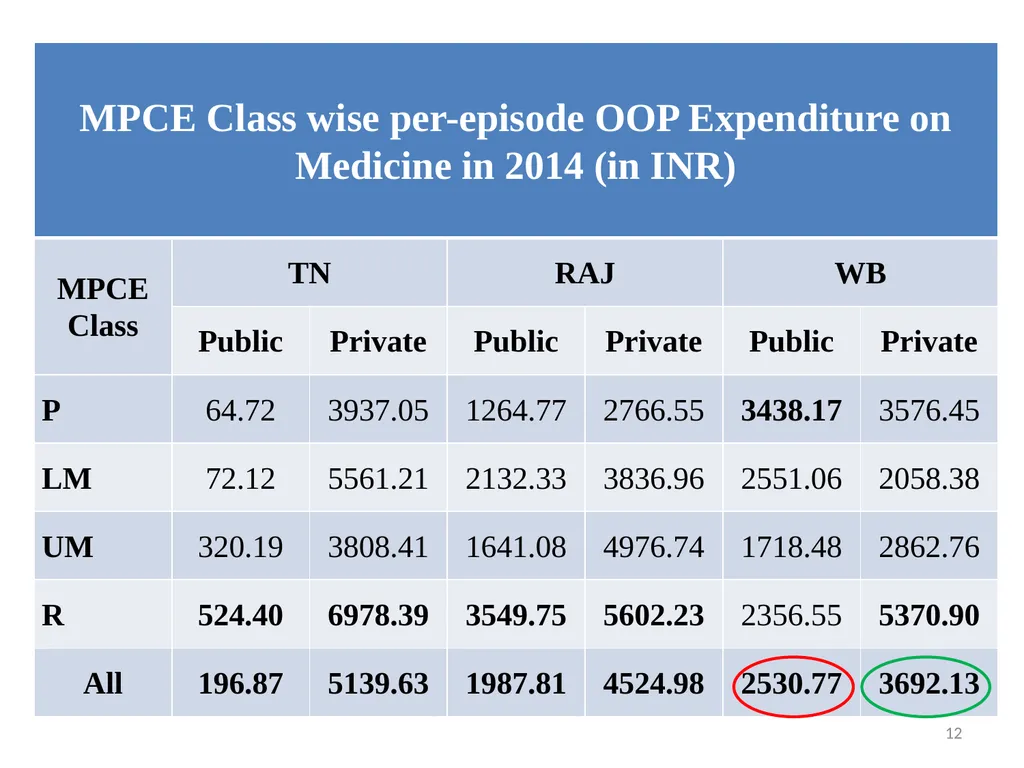
12<br>
13
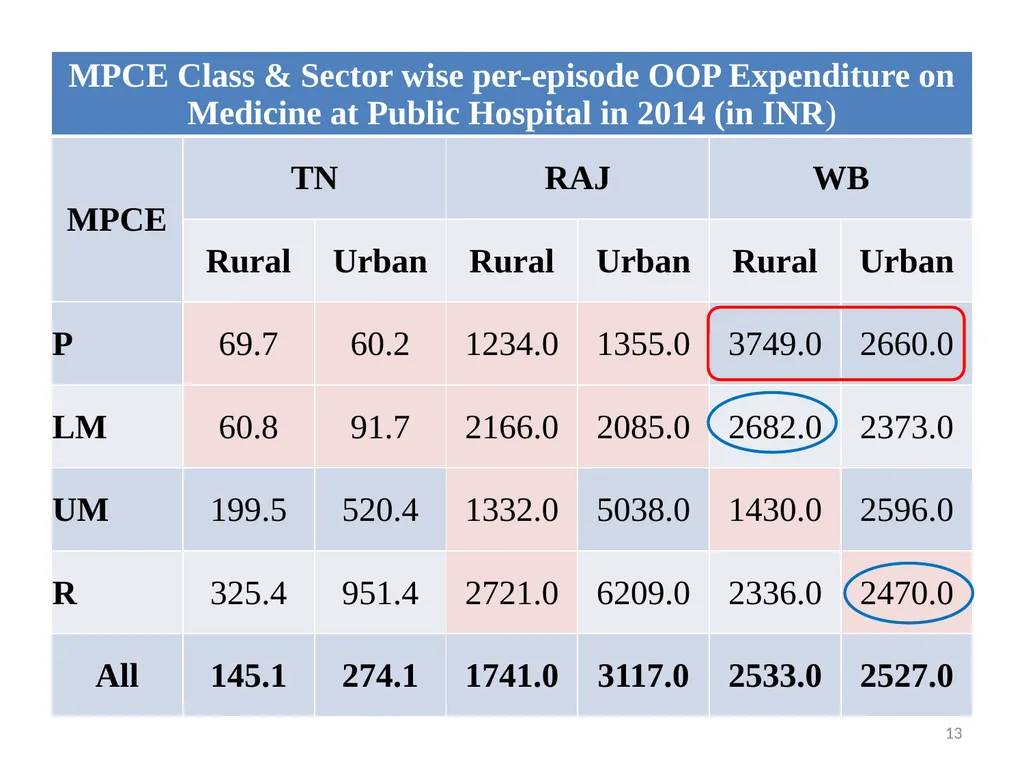
13<br>
14
Why is it so? Access to free medicine and diagnostic tests have increased marginally in WB but still its very low compared to TN and RAJ
Share of NCDs, Injury and disabilities have increased substantially among all income groups
Majority of the patients rely on the public facilities for treatment of NCDs, Injury and disabilities
Mismatch between actual need of the patients and EDL 14<br>
15
15<br>
16
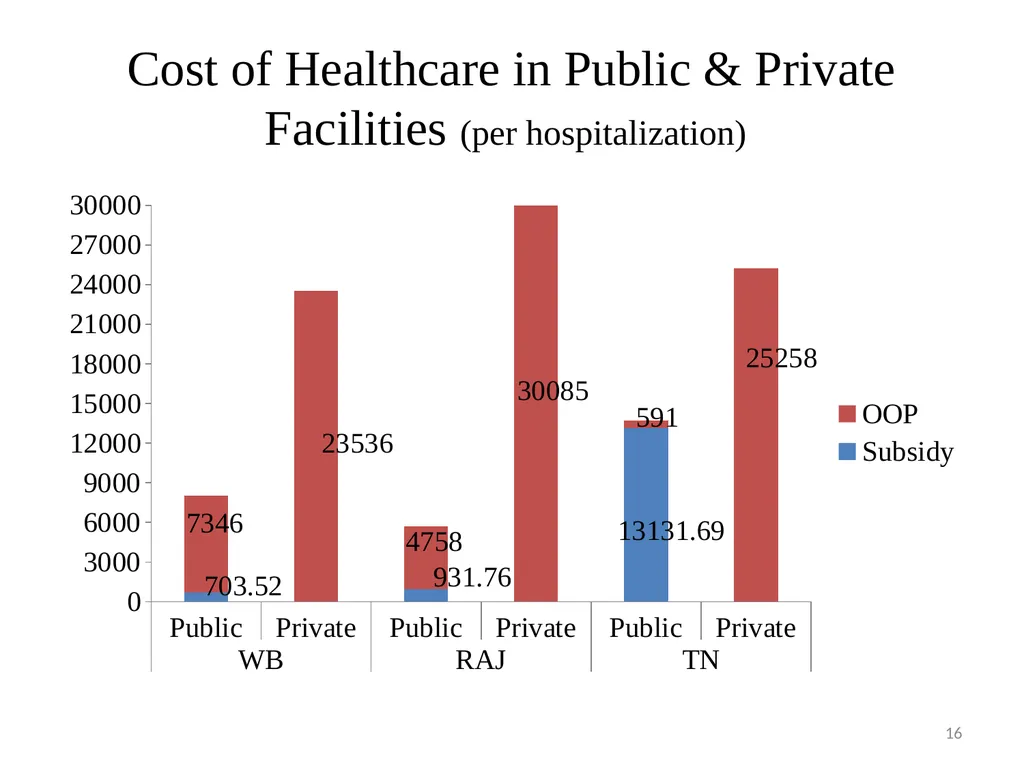
Cost of Healthcare in Public & Private Facilities (per hospitalization) 16<br>
17
Conclusions Focused policies are required to increase public sector hospitalization by the poor in WB
Procuring (or changing EDL) medicine according to need of the patients are urgently needed in WB
Provision of other healthcare services would reduce the OOP burden on the household in WB
TN should also focus on LM groups
Focus on urban poor would give better health outcome to Rajasthan
However, the question of fiscal space remains crucial. WB may not be in a position to attain this apparently first best policy and would be forced to settle down for alternative policy options. 17<br>