Presentation for the Mental Health Victoria Conference What we believe Our clients and their families should get all the help they want and need, from ONE team in ONE place. Everybody deserves every chance to turn their lives around. Six
"Presentation for the Mental Health Victoria" is the property of its rightful owner. Permission is granted to
download and print the materials on this website for personal, non-commercial use only, and to display it
on your personal computer provided you do not modify the materials and that you retain all copyright
notices contained in the materials. By downloading content from our website, you accept the terms of this
agreement.
Presentation Transcript
01
Presentation for the Mental Health Victoria Conference<br>
02
What we believe Our clients and their families should get all the help they want and need,
from ONE team in ONE place. Everybody deserves every chance to turn their lives around.<br>
03
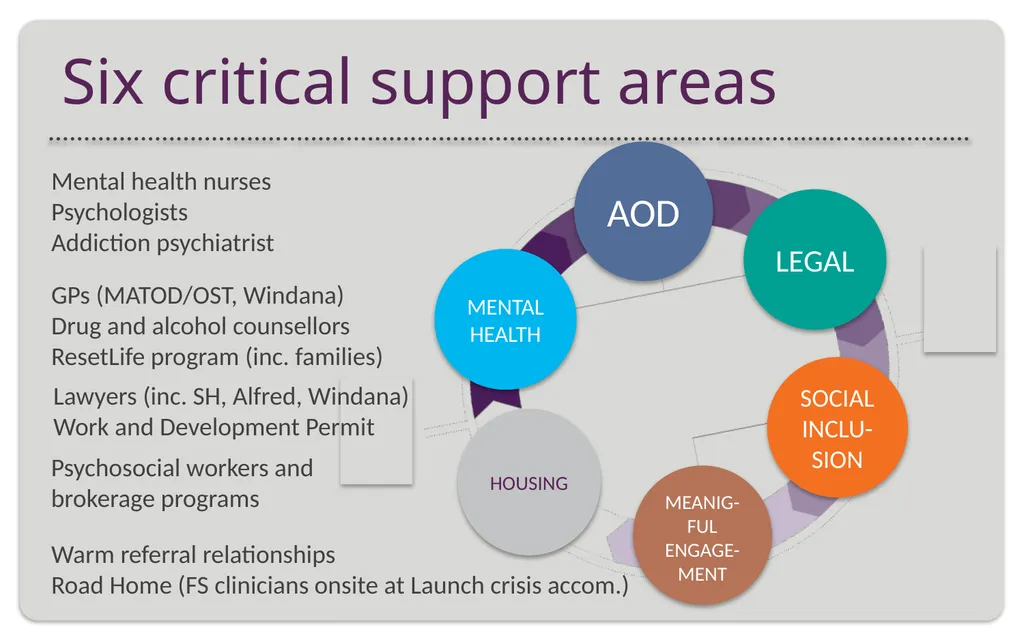
Six critical support areas Mental health nurses
Psychologists
Addiction psychiatrist GPs (MATOD/OST, Windana)
Drug and alcohol counsellors
ResetLife program (inc. families) Lawyers (inc. SH, Alfred, Windana)
Work and Development Permit Psychosocial workers and brokerage programs Warm referral relationships
Road Home (FS clinicians onsite at Launch crisis accom.) AOD MEANIG-FUL ENGAGE-MENT SOCIAL INCLU-SION LEGAL MENTAL HEALTH HOUSING<br>
04
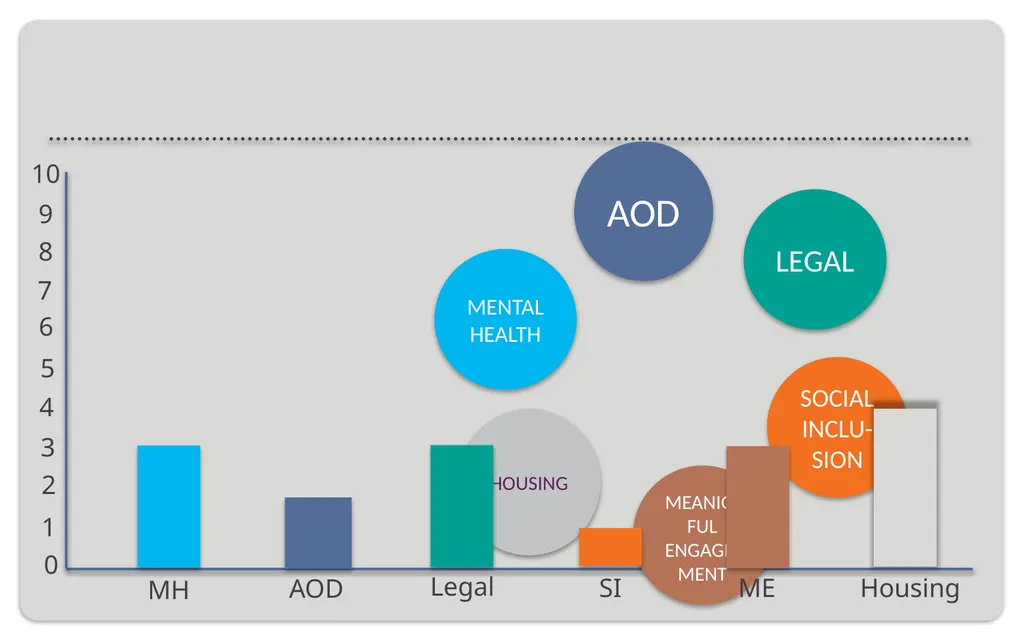
AOD MEANIG-FUL ENGAGE-MENT SOCIAL INCLU-SION LEGAL MENTAL HEALTH HOUSING 10 0 7 8 1 4 3 5 6 2 9 MH AOD Legal SI ME Housing<br>
05
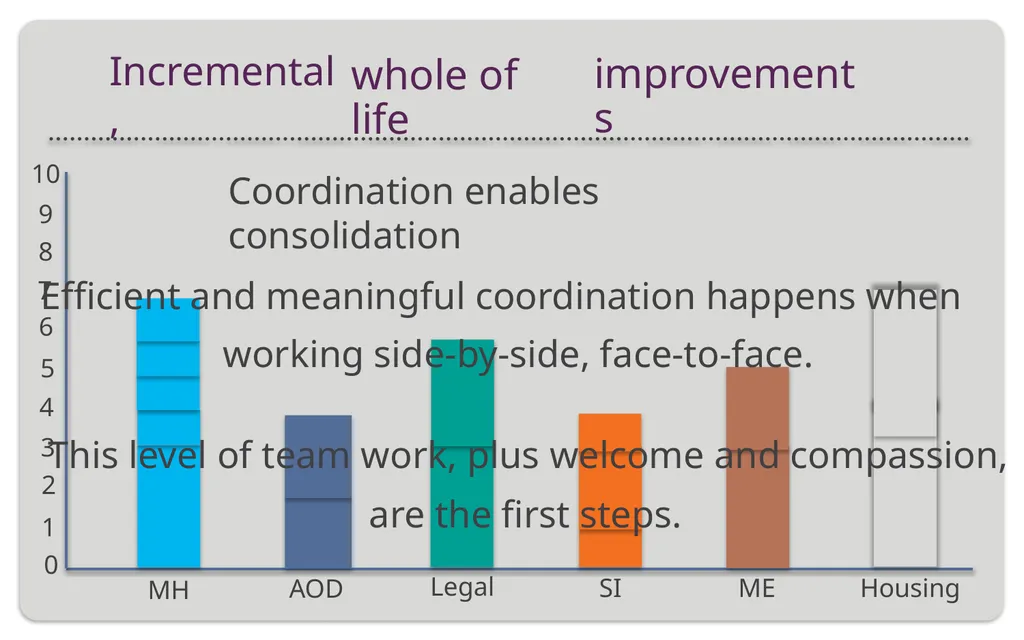
10 0 7 8 1 4 3 5 6 2 9 MH AOD Legal SI ME Housing Coordination enables consolidation Efficient and meaningful coordination happens when working side-by-side, face-to-face. Incremental, whole of life improvements This level of team work, plus welcome and compassion, are the first steps.<br>
06
11 of 33 First Step staff Lawyers Mgt/exec Mgt/ exec GP GP FAChAM Clinic nurse MH nurse Add: Skilled reception Care coordinators Psychology Psychosocial worker + $ Psychiatry And more AOD Group therapists/educators Medicare: MBS, Better Access, PNIP SEMPHN commissions State Gov grants Unfunded Philanthropy (Projects and Philanthropy Mgr) Integrated Care Pilot<br>
07
Maximise accessibility of care (no fees , no catchment, reception skilled to manage tricky clients, any entry point is the right one)
Ensure a positive first engagement with and ‘no wrong door.’ ‘We are in the welcoming business’ (Zia Partners CCISC model)
Ask ‘How can we help this person?’
Relent follow-up when people don’t attend
View complex comorbidity as the norm (inc.traumatic childhoods) CULTURE<br>
08
Prioritise communication in highest order
Recruit ‘team players’ from the top down
‘Train’ staff on team care (induction and periodically).
Balance a belief in diagnosis (clinical) with psycho-social (non-clinical) understanding of clients. TEAM CULTURE<br>
09
STRUCTURE If a large org, build smaller multi-disciplinary teams of your most skilled staff to work with complex clients
Abolish the concept of ‘internal referrals.’ Talk about ‘building a care team’ for each
Include collocated or ‘built-in’ community legal centre CLC lawyers are ‘health workers’ in the broader sense.
Include a Work and Development Permit worker (unfunded).<br>
10
Build incentives for case conferencing of all types
Schedule weekly ‘all team’ meetings.
With complex clients, do not organise care in ‘streams’, ‘stepping’ up or down or ‘episodes’. Everybody should have access to all the help they want and need from one team in one place.
Allow long-term relationships with clients where needed. People recover in the context of relationships. Continuity of care is crucial. STRUCTURE<br>
11
It’s reform time. Let’s push for what is so desperately needed!<br>