
10th CRM Report of Andhra Pradesh - Good practices















Description: 10th CRM Report of Andhra Pradesh - Good practices Concerns Recommendations Dr P.Saxena, Additional DDG and 17 other Team members Good practices Strong political commitment for various Health Family Welfare activities under NHM
Related Topics
Download Presentation
"10th CRM Report of Andhra Pradesh - Good practices" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. 10th CRM Report of Andhra Pradesh
- Good practices / Concerns / Recommendations Dr P.Saxena,
Additional DDG
and 17 other Team members<br>
slide2. Good practices Strong political commitment for various Health & Family Welfare activities under NHM driving community awareness about healthy lifestyle and family welfare measures.
2nd ANM is in position under NHM in almost all Subcentres, with only 3% vacancies.
85% children born (0-11 months age) are fully immunised, as against 65% reported in NFHS-4.
High level of use of I.T. in implementation of NHM activities.
Free Drugs scheme e-aushadi operational, free Diagnostics available -19 tests in PHCs, 40 in CHCs, 63 in Area and District Hospitals.
277 Mobile Medical Units providing Fixed day health services - taking healthcare closer to the community - especially continuum of care for HT, DM.<br>
slide3. Pradhan Mantri Surakhsit Matritva Abhiyan (PMSMA) being effectively rolled out with high utilization.
TB Care:- mandatory TB notification being done, CBNAAT services and PMDT services available.
Special campaign “Domalpai Dandayatra” to create awareness in the community about mosquito control. Every Friday is observed as ‘Dry Day’ for Vector control and every Saturday as ‘Sanitation Day’. ‘Mosquito breeding prevention act’ has been approved by State Cabinet.
80% blood collection in State is from Voluntary blood donors.<br>
slide4. Concerns In spite of good RCH initiatives under JSY/ JSSK, deliveries in govt. health facilities consistently below 50% of the total institutional deliveries - 42% in 2013-14 to 45% in 2016-17 (upto Sept 2016).
Only 112 out of 265 identified First Referral Units are functional.
Low expenditure under NUHM – Urban PHC being converted to e-UPHC in PPP mode but service delivery not planned as per NHM Guidelines.
Delays in payments for JSY and ASHA incentives.
All 13 districts covered under NPCDS however NCD Cells and Clinics yet to become fully operational.
Lack of proper training sites at district and state level- Trainings are conducted at DM&H office.
Delay in transfer of funds available for 2016-17 under RCH and Health System Strengthening from State Treasury to State Health Society.<br>
slide5. Recommendations Need for strengthening of State and District teams for Community Processes with essential basic support viz, mobility and internet support.
State needs to take initiatives for improving Institutional deliveries in Govt. Health facilities and take measures to make timely payments for JSY and ASHA incentives.
Vulnerability assessment with comprehensive mapping of urban slums and slum like settlements should be undertaken at the e- UPHC level.
e-UPHCs should provide outreach services through Urban- Health & Nutrition Days and special outreach sessions for Immunisation/ Health check ups/ IEC etc.
Many of the services being dispensed in a PPP mode - but for long term sustainability, State should also focus on strengthening its own public health system.
C-DAC needs to review the e Aushadhi software to address State-District disconnect and improve inventory management.
IDSP data needs to be reviewed on monthly basis at block and district level to improve data quality.
State may conduct systematic financial training at District level for fund management, Expenditure filing and Direct Bank Transfer through PFMS.
Training infrastructure development (including skill labs) is critical - District Hospitals and Medical Colleges can be developed as training centres under NHM.<br>
slide6. Action Taken by State<br>
slide7. With the introduction of several new initiatives Free Drugs, Free Diagnostics, drop back services, Mother & Baby kit, the institutional deliveries will cross 50 % this year
Only 112 out of 265 identified First Referral Units are functional.
As per latest HMIS report 81 % of FRUs are functional
Low expenditure under NUHM – Urban PHC being converted to e-UPHC in PPP mode but service delivery not planned as per NHM Guidelines.
All the Primary care services as envisaged in NHM guidelines have been incorporated and additional services also being provided in eUPHCs
Vulnerability mapping is being done in coordination with MEPMA
Out reach services started in eUPHCs .
All the PPP services are only complimentary, the internal strength is being retained and being strengthened
All the PPP partners are being intensively monitored by the concerned Nodal Officers, Knowledge Partners , Principal Secretary to Government, Hon’ble Health Minister and Hon’ble Chief Minister<br>
slide8. Delays in payments for JSY and ASHA incentives.
As per directions of GOI ,7 districts migrated to DBT payment of JSY & ASHA incentives, in coming three months remaining districts will implement DBT
Payments are being done through Direct Beneficiary Transfer (DBT) for JSY Beneficiaries in Visakhapatnam, West Godavari, Krishna, Chittoor & Anantapur Districts and Asha Incentives are being paid through PFMS in Srikakulam, Vizianagaram, Visakhapatnam, East Godavari, West Godavari, Krishna, Anantapur & Kurnool Districts on timely basis. 100 % of the expenditure in State and District is through PFMS
Delay in transfer of funds available for 2016-17 under RCH and Health System Strengthening from State Treasury to State Health Society.
The procedure of credit of grants into State Health Society include issue of BRO by the Finance Department, Administrative sanction by HM&FW Department, Budget Authorization by the DTA, Drawl of the bill at PAO, then the grants will be credited in to SHS Account by Ways and Means wing of Finance Department, this requires 60 days.<br>
slide9. All 13 districts covered under NPCDS however NCD Cells and Clinics yet to become fully operational.
National Programme for Prevention and Control of Cancer, Diabetes, CVDs and Stroke Programme
Screening for Diabetes and Hypertension is going on in all 13 Districts.
CCUs were established at Srikakulam, Vizianagaram, Vijayawada, Ongole, Nellore and Kurnool Recruitment of staff has been completed in Srikakulam, Vizianagaram, Visakhapatnam, Guntur.
Screening is going on to all the people who are 30+. In Vizianagaram, Ananthapur, Nellore districts and the cities of Vijayawada and Visakhapatnam municipal corporations are identified for the screening.
As a State Programme under Mahila Master Health Check-up wherein special focus was made for the health of Women, all the ANMs, Gynaecologists were imparted trainings in identifying common cancers of Oral, Breast and Cervical. A total of 6.51 Lakhs women already screened.
Mobile Medical Units are screening approximately 500 women every day
National Programme for Health Care of Elderly.
In each District Hospital, 10 beds were identified for Senior Citizens and a separate ‘Q’ at OP and Pharmacy are being maintained.
Physiotherapy equipment has been supplied to Srikakulam, Vizianagaram, Krishna, Prakasam, Nellore, Kurnool, Kadapa and Chittoor Districts.<br>
slide10. National Iodine Deficiency Disorders Control Programme
In Andhra Pradesh out of 13 Districts, Six (6)Districts were endemic to Iodine Deficiency Disorders Those are Srikakulam, Visakhapatnam, East Godavari, West Godavari, Krishna and Nellore Districts.
National Tobacco Control Programme The programme was launched in the year 2008-09 in Guntur District as a pilot project. Subsequently, it was extended to Prakasam, Kadapa and Nellore Districts in the year 2014-15 and to Srikakulam, Vizianagaram, East Godavari, West Godavari, Chittoor and Ananthapur in the year 2015-16. Tobacco banned in the State as per Act
National Oral Health Programme
The Programme is implementing in all 13 districts of AP.
The Dental Units in the District Hospitals of Vizianagaram, Guntur, Kurnool, Krishna and West Godavari were strengthened from the funds provided under NOHP in the year 2015-16.
An amount of Rs.36.92 lakhs were released to all the District Co-ordinator of Hospital Services for repairs of the existing equipment and consumables inthe month of March, 2017.
National Programme for Prevention and Control of Fluorosis:
The programme has been launched in the year 2009 - 10 in Nellore District and it was extended to Prakasam in the year 2012-13 and to Guntur 2013-14.
The programme further extended to Kurnool, Ananthapur, Chittoor, Krishna, Kadapa and Vizianagaram Districts during the year 2016-17.<br>
slide11. Lack of proper training sites at district and state level- Trainings are conducted at DM&H office.
In residual state of Andhra Pradesh there is no State Institute of Health & Family Welfare and the existing state institute IIHFW in the erstwhile state is in Telangana State by virtue of its location in Hyderabad.
Government of Andhra Pradesh, has issued orders establishing the State Institute of Health & Family Welfare (SIHFW), by amalgamating the Regional Training Centers (Male & Female) located at Visakhapatnam .positions of one Director and additional HR (i.e. 3 Consultants each for Maternal Health Trainings, Child Health Trainings and for other trainings respectively) to support the existing faculty and staff of SIHFW has been proposed in the PIP 2017-18.
All the District Training centres in the state are equipped with PODTT 2. DPHNO 3. CHO 4. HEEO and Senior Assistant for conducting various training Programmes in the Districts. State level and District level TOTs along with the subject specialists from Medical Colleges/ District & Area Hospitals in the districts are involved to act as Trainers so as to conduct the Trainings. The subject experts from other states and other knowledge partners are also invited as guest faculty.<br>
slide12. THANK YOU<br>
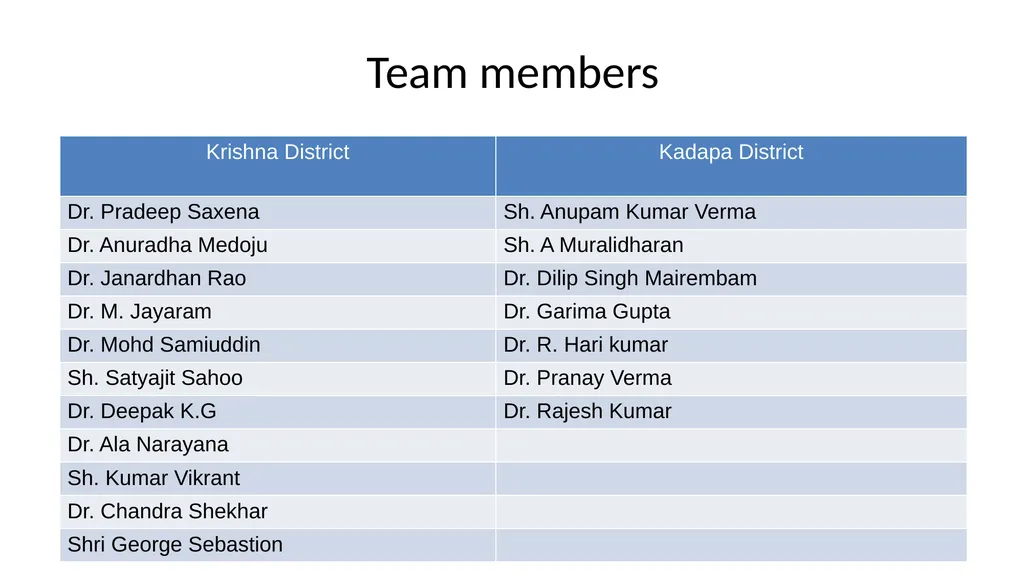
slide13. Team members<br>
slide14. Facilities visited-Krishna district<br>
slide15. Facilities visited-Kadapa district<br>
Additional DDG
and 17 other Team members<br>
slide2. Good practices Strong political commitment for various Health & Family Welfare activities under NHM driving community awareness about healthy lifestyle and family welfare measures.
2nd ANM is in position under NHM in almost all Subcentres, with only 3% vacancies.
85% children born (0-11 months age) are fully immunised, as against 65% reported in NFHS-4.
High level of use of I.T. in implementation of NHM activities.
Free Drugs scheme e-aushadi operational, free Diagnostics available -19 tests in PHCs, 40 in CHCs, 63 in Area and District Hospitals.
277 Mobile Medical Units providing Fixed day health services - taking healthcare closer to the community - especially continuum of care for HT, DM.<br>
slide3. Pradhan Mantri Surakhsit Matritva Abhiyan (PMSMA) being effectively rolled out with high utilization.
TB Care:- mandatory TB notification being done, CBNAAT services and PMDT services available.
Special campaign “Domalpai Dandayatra” to create awareness in the community about mosquito control. Every Friday is observed as ‘Dry Day’ for Vector control and every Saturday as ‘Sanitation Day’. ‘Mosquito breeding prevention act’ has been approved by State Cabinet.
80% blood collection in State is from Voluntary blood donors.<br>
slide4. Concerns In spite of good RCH initiatives under JSY/ JSSK, deliveries in govt. health facilities consistently below 50% of the total institutional deliveries - 42% in 2013-14 to 45% in 2016-17 (upto Sept 2016).
Only 112 out of 265 identified First Referral Units are functional.
Low expenditure under NUHM – Urban PHC being converted to e-UPHC in PPP mode but service delivery not planned as per NHM Guidelines.
Delays in payments for JSY and ASHA incentives.
All 13 districts covered under NPCDS however NCD Cells and Clinics yet to become fully operational.
Lack of proper training sites at district and state level- Trainings are conducted at DM&H office.
Delay in transfer of funds available for 2016-17 under RCH and Health System Strengthening from State Treasury to State Health Society.<br>
slide5. Recommendations Need for strengthening of State and District teams for Community Processes with essential basic support viz, mobility and internet support.
State needs to take initiatives for improving Institutional deliveries in Govt. Health facilities and take measures to make timely payments for JSY and ASHA incentives.
Vulnerability assessment with comprehensive mapping of urban slums and slum like settlements should be undertaken at the e- UPHC level.
e-UPHCs should provide outreach services through Urban- Health & Nutrition Days and special outreach sessions for Immunisation/ Health check ups/ IEC etc.
Many of the services being dispensed in a PPP mode - but for long term sustainability, State should also focus on strengthening its own public health system.
C-DAC needs to review the e Aushadhi software to address State-District disconnect and improve inventory management.
IDSP data needs to be reviewed on monthly basis at block and district level to improve data quality.
State may conduct systematic financial training at District level for fund management, Expenditure filing and Direct Bank Transfer through PFMS.
Training infrastructure development (including skill labs) is critical - District Hospitals and Medical Colleges can be developed as training centres under NHM.<br>
slide6. Action Taken by State<br>
slide7. With the introduction of several new initiatives Free Drugs, Free Diagnostics, drop back services, Mother & Baby kit, the institutional deliveries will cross 50 % this year
Only 112 out of 265 identified First Referral Units are functional.
As per latest HMIS report 81 % of FRUs are functional
Low expenditure under NUHM – Urban PHC being converted to e-UPHC in PPP mode but service delivery not planned as per NHM Guidelines.
All the Primary care services as envisaged in NHM guidelines have been incorporated and additional services also being provided in eUPHCs
Vulnerability mapping is being done in coordination with MEPMA
Out reach services started in eUPHCs .
All the PPP services are only complimentary, the internal strength is being retained and being strengthened
All the PPP partners are being intensively monitored by the concerned Nodal Officers, Knowledge Partners , Principal Secretary to Government, Hon’ble Health Minister and Hon’ble Chief Minister<br>
slide8. Delays in payments for JSY and ASHA incentives.
As per directions of GOI ,7 districts migrated to DBT payment of JSY & ASHA incentives, in coming three months remaining districts will implement DBT
Payments are being done through Direct Beneficiary Transfer (DBT) for JSY Beneficiaries in Visakhapatnam, West Godavari, Krishna, Chittoor & Anantapur Districts and Asha Incentives are being paid through PFMS in Srikakulam, Vizianagaram, Visakhapatnam, East Godavari, West Godavari, Krishna, Anantapur & Kurnool Districts on timely basis. 100 % of the expenditure in State and District is through PFMS
Delay in transfer of funds available for 2016-17 under RCH and Health System Strengthening from State Treasury to State Health Society.
The procedure of credit of grants into State Health Society include issue of BRO by the Finance Department, Administrative sanction by HM&FW Department, Budget Authorization by the DTA, Drawl of the bill at PAO, then the grants will be credited in to SHS Account by Ways and Means wing of Finance Department, this requires 60 days.<br>
slide9. All 13 districts covered under NPCDS however NCD Cells and Clinics yet to become fully operational.
National Programme for Prevention and Control of Cancer, Diabetes, CVDs and Stroke Programme
Screening for Diabetes and Hypertension is going on in all 13 Districts.
CCUs were established at Srikakulam, Vizianagaram, Vijayawada, Ongole, Nellore and Kurnool Recruitment of staff has been completed in Srikakulam, Vizianagaram, Visakhapatnam, Guntur.
Screening is going on to all the people who are 30+. In Vizianagaram, Ananthapur, Nellore districts and the cities of Vijayawada and Visakhapatnam municipal corporations are identified for the screening.
As a State Programme under Mahila Master Health Check-up wherein special focus was made for the health of Women, all the ANMs, Gynaecologists were imparted trainings in identifying common cancers of Oral, Breast and Cervical. A total of 6.51 Lakhs women already screened.
Mobile Medical Units are screening approximately 500 women every day
National Programme for Health Care of Elderly.
In each District Hospital, 10 beds were identified for Senior Citizens and a separate ‘Q’ at OP and Pharmacy are being maintained.
Physiotherapy equipment has been supplied to Srikakulam, Vizianagaram, Krishna, Prakasam, Nellore, Kurnool, Kadapa and Chittoor Districts.<br>
slide10. National Iodine Deficiency Disorders Control Programme
In Andhra Pradesh out of 13 Districts, Six (6)Districts were endemic to Iodine Deficiency Disorders Those are Srikakulam, Visakhapatnam, East Godavari, West Godavari, Krishna and Nellore Districts.
National Tobacco Control Programme The programme was launched in the year 2008-09 in Guntur District as a pilot project. Subsequently, it was extended to Prakasam, Kadapa and Nellore Districts in the year 2014-15 and to Srikakulam, Vizianagaram, East Godavari, West Godavari, Chittoor and Ananthapur in the year 2015-16. Tobacco banned in the State as per Act
National Oral Health Programme
The Programme is implementing in all 13 districts of AP.
The Dental Units in the District Hospitals of Vizianagaram, Guntur, Kurnool, Krishna and West Godavari were strengthened from the funds provided under NOHP in the year 2015-16.
An amount of Rs.36.92 lakhs were released to all the District Co-ordinator of Hospital Services for repairs of the existing equipment and consumables inthe month of March, 2017.
National Programme for Prevention and Control of Fluorosis:
The programme has been launched in the year 2009 - 10 in Nellore District and it was extended to Prakasam in the year 2012-13 and to Guntur 2013-14.
The programme further extended to Kurnool, Ananthapur, Chittoor, Krishna, Kadapa and Vizianagaram Districts during the year 2016-17.<br>
slide11. Lack of proper training sites at district and state level- Trainings are conducted at DM&H office.
In residual state of Andhra Pradesh there is no State Institute of Health & Family Welfare and the existing state institute IIHFW in the erstwhile state is in Telangana State by virtue of its location in Hyderabad.
Government of Andhra Pradesh, has issued orders establishing the State Institute of Health & Family Welfare (SIHFW), by amalgamating the Regional Training Centers (Male & Female) located at Visakhapatnam .positions of one Director and additional HR (i.e. 3 Consultants each for Maternal Health Trainings, Child Health Trainings and for other trainings respectively) to support the existing faculty and staff of SIHFW has been proposed in the PIP 2017-18.
All the District Training centres in the state are equipped with PODTT 2. DPHNO 3. CHO 4. HEEO and Senior Assistant for conducting various training Programmes in the Districts. State level and District level TOTs along with the subject specialists from Medical Colleges/ District & Area Hospitals in the districts are involved to act as Trainers so as to conduct the Trainings. The subject experts from other states and other knowledge partners are also invited as guest faculty.<br>
slide12. THANK YOU<br>
slide13. Team members<br>
slide14. Facilities visited-Krishna district<br>
slide15. Facilities visited-Kadapa district<br>