01
“Bones in lonely places” Corresponding author:
- Dr Anna Blackburn, ST2 Radiology Registrar, Northern Ireland Medical and Dental Training Agency. ablackburn01@qub.ac.uk
Further authors:
- Dr Shauna McGarry, ST4 Radiology Registrar, Northern Ireland Medical and Dental Training Agency. smcgarry@doctors.org.uk
-Dr Michael Pyper, Consultant Radiologist, Royal Victoria Hospital, Belfast Health and Social Care Trust, Northern Ireland. michael.pyper@belfasttrust.hscni.net<br>
02
Case Synopsis 39 year-old male presented following high-speed road traffic collision and underwent trauma protocol whole body CT. Multiple life-threatening injuries demonstrated on emergency imaging, including; aortic arch intimal tear, traumatic left abdominal wall hernia, liver laceration, enteric/ colonic injuries and multiple fractures. The patient proceeded to emergency laparotomy.
Colonic and enteric Ischaemia confirmed at laparotomy, requiring open left hemicolectomy. Aortic injury managed conservatively. Following clinical deterioration in Intensive Care, ileo-caecal resection with end colostomy performed at second laparotomy. Post-operative recovery complicated by multiple abdomino-pelvic collections.
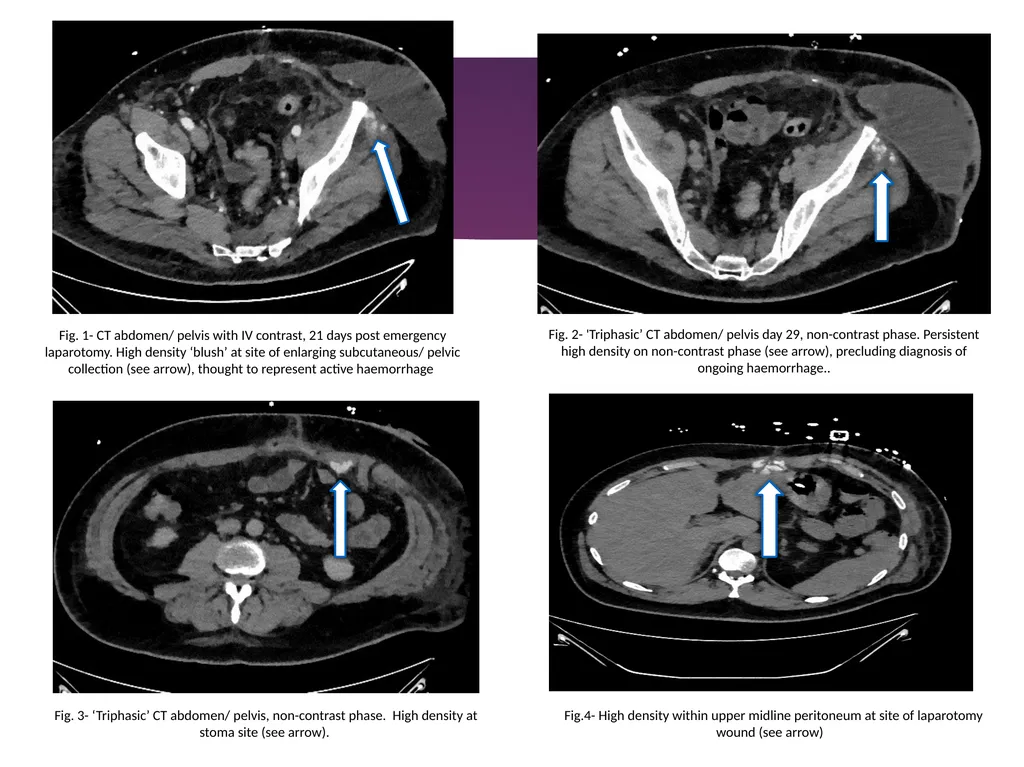
Follow-up whole body CT performed 21 days later to reassess aortic injury and abdominal collections. Enlarging left lower quadrant collection with “contrast blush” and suspected ongoing haemorrhage demonstrated. Clinical assessment and Interventional Radiology input recommended if appropriate.
Targeted contrast enhanced ultrasound scan revealed no evidence of acute haemorrhage. 1 ml of degraded haematoma aspirated with ultrasound guidance.
Tri-phasic abdomino-pelvic CT performed 29 days following presentation to assess for ongoing haemorrhage. Non-contrast phase demonstrated multiple foci of high density (HU 135-145) at sites of soft tissue trauma and surgical intervention. This included the left lower quadrant collection, throughout the laparotomy wound and adjacent to the stoma site. None of these areas showed appreciable enhancement post-contrast. No evidence of ongoing haemorrhage demonstrated.
Final diagnosis: Intra-abdominal heterotopic ossification. WORD COUNT: 211<br>
03
Fig. 1- CT abdomen/ pelvis with IV contrast, 21 days post emergency laparotomy. High density ‘blush’ at site of enlarging subcutaneous/ pelvic collection (see arrow), thought to represent active haemorrhage. Fig. 2- 'Triphasic’ CT abdomen/ pelvis day 29, non-contrast phase. Persistent high density on non-contrast phase (see arrow), precluding diagnosis of ongoing haemorrhage.. Fig. 3- ‘Triphasic’ CT abdomen/ pelvis, non-contrast phase. High density at stoma site (see arrow). Fig.4- High density within upper midline peritoneum at site of laparotomy wound (see arrow)).<br>