
Chapter 52 Ground and Air Ambulance Operations


































Description: Chapter 52 Ground and Air Ambulance Operations Focused Lecture Ambulance Standards (1 of 3) In 1968, the National Academy of SciencesNational Research Council (NAS-NRC) recommended ambulance design standards that covered size, shape,
Related Topics
Download Presentation
"Chapter 52 Ground and Air Ambulance Operations" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Chapter 52
Ground and Air Ambulance Operations
Focused Lecture<br>
slide2. Ambulance Standards (1 of 3) In 1968, the National Academy of Sciences–National Research Council (NAS-NRC) recommended ambulance design standards that covered size, shape, color, electrical systems, and emergency equipment to be carried on these vehicles.<br>
slide3. Ambulance Standards (2 of 3) Federal Specifications
Eventually led to development of federal specifications many states use as ambulance standards
Collectively known as the federal standards
Provide the basis for uniformity in the design of ambulance vehicles
Three basic ambulance designs
Include additional-duty (AD) vehicles<br>
slide4. Ambulance Standards (3 of 3) National Standards
Federal standards replaced by other national standards of design and performance for ambulance vehicles, October 2016
NFPA 1917, Standard for Automotive Ambulances of the National Fire Protection Association (NFPA)
Ground Vehicle Standard for Ambulances (GVS v.1.0) of the Commission on Accreditation of Ambulance Services.<br>
slide5. Checking Ambulances Completing equipment and supply checklist at beginning of every work shift is essential for safety, patient care, and risk management.
Helps to ensure proper handling and safekeeping of scheduled medications
Routine maintenance, testing, and cleaning<br>
slide6. Ambulance Stationing (1 of 2) 1970s: methods for estimating need for ambulance service and where these vehicles should be stationed in a community were based on availability of ambulances as well as average response time to emergency scene
Methods for estimating needs have shifted toward determining percentage of compliance in providing EMS within time frames that meet national guidelines.<br>
slide7. Ambulance Stationing (2 of 2) Strategies for ambulance stationing often are based on which areas have the highest volume of calls
Deployment strategies vary by EMS agency.
Simple to comprehensive<br>
slide8. Safe Ambulance Operation (1 of 18) Estimated 4,500 vehicle crashes involving an ambulance occur each year
2015: 28 fatalities in crashes involving occupied ambulances<br>
slide9. Safe Ambulance Operation (2 of 18) Estimated 4,500 vehicle crashes involving an ambulance occur each year (cont.)
Safe operation of ambulances is essential for the safety of patients, the EMS crew, and others in the vicinity of a response
Most EMS agencies require their personnel to take an emergency driving course
Numerous factors influence the safe operation of an ambulance<br>
slide10. Safe Ambulance Operation (3 of 18) Estimated 4,500 vehicle crashes involving an ambulance occur each year (cont.)
Maintaining ambulance safety for the EMS provider and the patient is complex and multifactorial.<br>
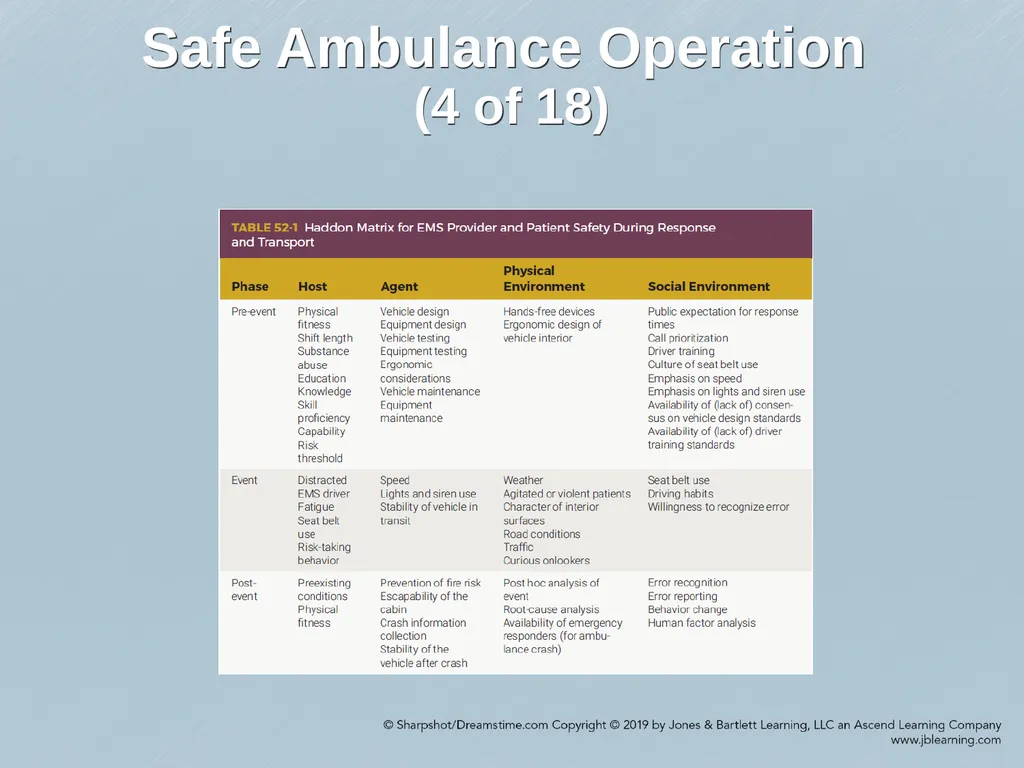
slide11. Safe Ambulance Operation (4 of 18)<br>
slide12. Safe Ambulance Operation (5 of 18) Appropriate Use of Personal Restraints
84% of EMS providers in patient compartment were not restrained
Many EMS agencies incorporate guidelines into their standard procedures in an effort to protect patients, passengers, and EMS personnel during transports<br>
slide13. Safe Ambulance Operation (6 of 18) Appropriate Use of Escorts
Police escorts during an emergency response Can sometimes be dangerous
Collisions can occur as a result of confusion
Use escorts only when responding to a scene in an unfamiliar area
Tiered response system
Safer emergency response
Proper resources and personnel are available during emergency<br>
slide14. Safe Ambulance Operation (7 of 18) Environmental Conditions
Include poor road and weather condition.
Proceed at a safe speed
Dry roads and clear weather do not guarantee a safe response<br>
slide15. Safe Ambulance Operation (8 of 18) Appropriate Use of Warning Devices
Lights and siren should be used according the agency’s protocol and state’s motor vehicle laws
Based on the patient’s condition and the benefit that may be derived from potential time saved by using lights and siren.<br>
slide16. Safe Ambulance Operation (9 of 18) Appropriate Use of Warning Devices (cont.)
When using lights and siren, motorists who drive with the car windows rolled up or who are using an audio device, air conditioning, or the heating system may not be able to hear the sirens or air horns.
Never assume vehicle’s lights, sirens, and air horns provide an absolute right-of-way or privileged immunity to proceed<br>
slide17. Safe Ambulance Operation (10 of 18) Appropriate Use of Warning Devices (cont.)
EMS agencies using a lights and siren response should avoid using continuous siren tones when traveling unimpeded and not asking for emergency vehicle privileges.
It is important to recognize situations when, regardless of the patient’s condition or the use of lights and siren, the ambulance does not have privileges for the right-of-way in most states.<br>
slide18. Safe Ambulance Operation (11 of 18) Proceeding Safely Through Intersections
Between 43% and 53% of ambulance crashes in the United States occur in intersections where an ambulance proceeds against a red light
Important that the driver of an emergency vehicle stop at all controlled intersections.
Driver should try to make eye contact with all motorists before proceeding through intersection
Alternating the siren’s “yelp” and “wail” modes<br>
slide19. Safe Ambulance Operation (12 of 18) Proceeding Safely Through Intersections (cont.)
Similar strategies should be employed when proceeding against flow of traffic
Speed limited to less than 20 miles per hour (32 km/h).<br>
slide20. Safe Ambulance Operation (13 of 18) Parking at the Emergency Scene
If law enforcement and fire service personnel have secured the scene
Position about 100 feet (30 m) past scene, on same side of road
Positioned uphill (about 200 feet [60 m]). upwind
If law enforcement and fire service personnel have NOT secured the scene
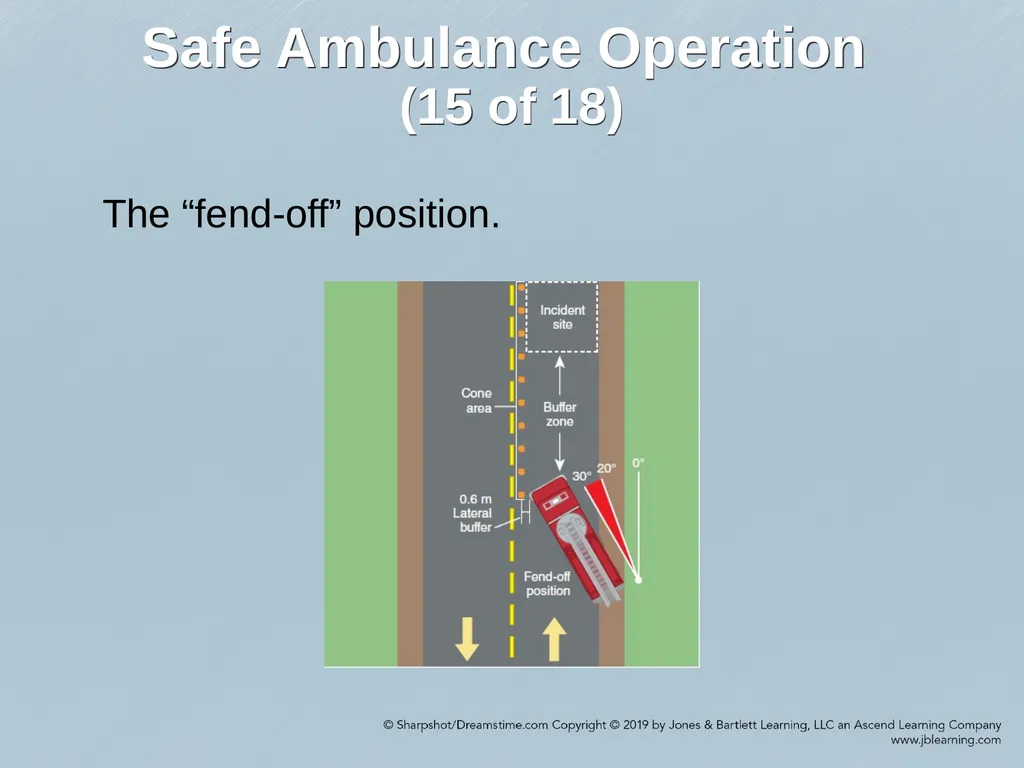
Position diagonally about 50 feet (15 m) in front of scene in the fend-off position
Deflect and avert from scene other vehicles that may strike<br>
slide21. Safe Ambulance Operation (14 of 18) Parking at the Emergency Scene (cont.)
Other safety precautions
Set the parking brake
Help guide the vehicle when it is backing up
Wear reflective gear<br>
slide22. Safe Ambulance Operation (15 of 18) The “fend-off” position.<br>
slide23. Safe Ambulance Operation (16 of 18) Operating With Due Regard for the Safety of All Others
Most states allow privileges for drivers of emergency vehicles, must take into consideration safety of all people using roads
Includes maintaining a safe following distance to avoid rear-end collisions
“Due regard for the safety of all others” carries legal responsibility
Paramedic and EMS agency can incur liability if damage, injury, or death results from failure to observe this principle<br>
slide24. Safe Ambulance Operation (17 of 18) Safely Moving a Patient Into and Out of an Ambulance
After initial stabilization at scene, patient must be packaged and safely placed in emergency vehicle for transport
Safe lifting practices
Ensure patient is positioned securely
Locking devices
Unnecessary equipment should be stowed before transport.<br>
slide25. Safe Ambulance Operation (18 of 18) Safely Moving a Patient Into and Out of an Ambulance (cont.)
During transport, the patient should be closely monitored for any changes in status.
On arrival at the hospital, the ambulance should come to a full stop.
Personal restraints can be removed
All patient care equipment must be secured before stretcher is released from locking device.
Using safe lifting techniques, patient’s stretcher should be removed from ambulance.<br>
slide26. Aeromedical Transport (1 of 12) Like many other aspects of prehospital emergency care, air evacuation is rooted in military history.
More than 300 air medical service programs using fixed-wing aircraft and/or rotary-wing aircraft have been established throughout the United States.<br>
slide27. Aeromedical Transport (2 of 12) Aeromedical Crew Members and Training
Staffing of air ambulances includes a pilot and various health care professionals
Specialized training in flight physiology and advanced medical equipment and procedures<br>
slide28. Aeromedical Transport (3 of 12) Use of Aeromedical Services
Local EMS system develops the criteria for requesting aeromedical services’ response to the scene of an emergency.
Decision should be supported by appropriate triage and evaluation of the scene
Considerations for air transport<br>
slide29. Aeromedical Transport (4 of 12) Notification of Aeromedical Services
If paramedics request air service for medical, trauma, or search and rescue events, they should advise the flight crew of:
The type of emergency response
The number of patients
The location of a landing zone (LZ)
Any prominent landmarks and hazards<br>
slide30. Aeromedical Transport (5 of 12) Notification of Aeromedical Services (cont.)
Direct ground-to-air communication must be available between a designated LZ officer and the aeromedical staff on the responding aircraft.
If possible, the fire department should be dispatched to the LZ to provide fire-suppression support.
Law enforcement personnel should be available for securing the scene.<br>
slide31. Aeromedical Transport (6 of 12) Landing Site Preparation
If a nighttime LZ is used, emergency vehicles with lighted bar lights should be situated at the perimeters of the LZ.
If white lights are used, should be directed down toward the center of LZ as spotlights, because white lights directed toward the aircraft can temporarily blind the pilot.
Rescue personnel should never be used to identify the LZ
Flares should not be used
Wet down dusty LZs<br>
slide32. Aeromedical Transport (7 of 12) Landing Site Preparation (cont.)
Helpful radio communications with the pilot include notification of wind direction and any possible obstructions or hazards.
Patient status and clinical information should not be relayed to the aeromedical crew<br>
slide33. Aeromedical Transport (8 of 12) Landing Site Preparation (cont.)
Pilot generally does not land the aircraft until all danger of fire or explosion has been eliminated.
One emergency responder should stand facing the LZ so that the pilot will see the landing area.
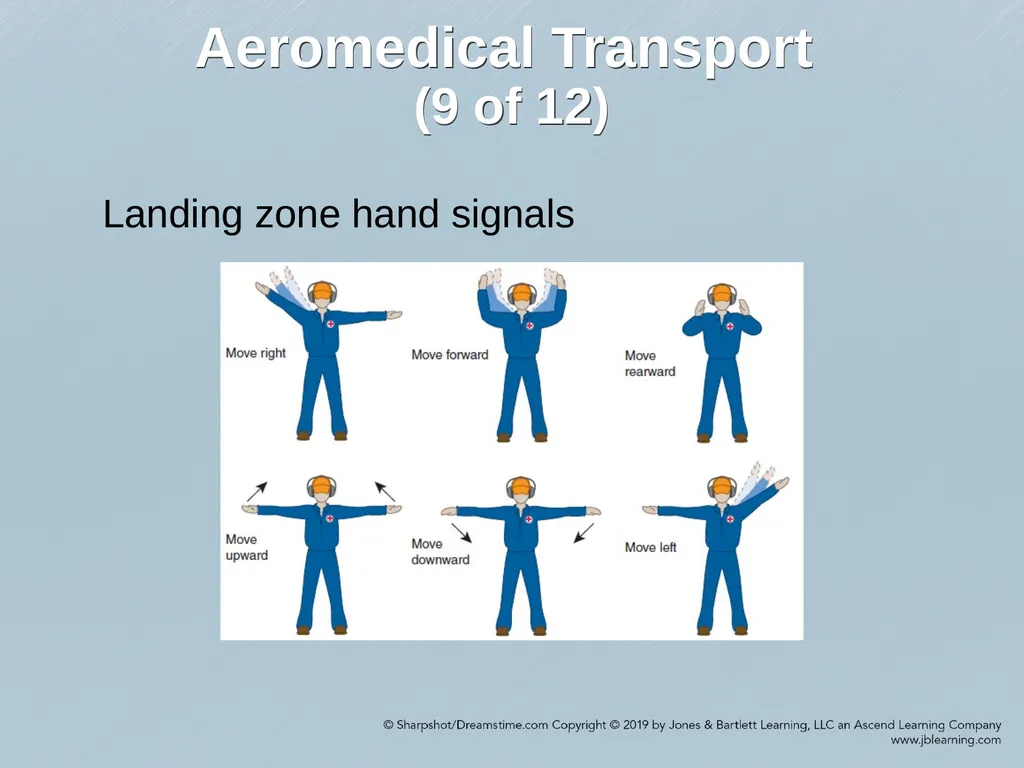
LZ hand signals that may be useful to the pilot<br>
slide34. Aeromedical Transport (9 of 12) Landing zone hand signals<br>
slide35. Aeromedical Transport (10 of 12) Safety Precautions
Everyone should be clear of the landing area during takeoffs and landings
A distance of 100 to 200 feet (30 to 60 m) is best
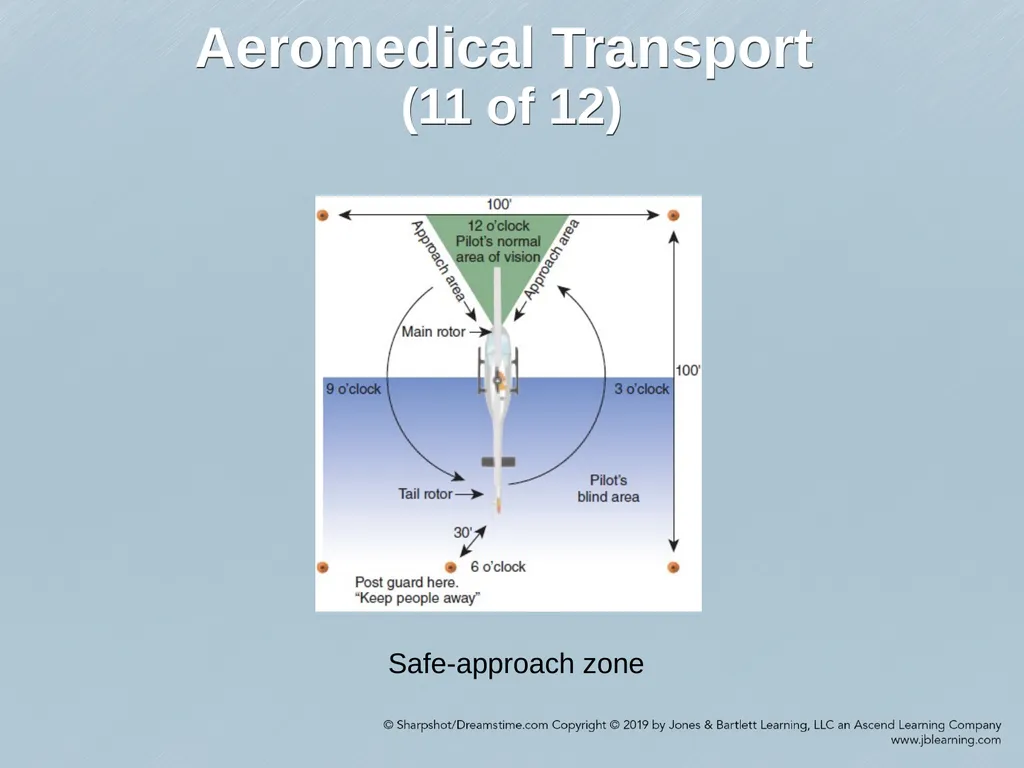
Take precautions<br>
slide36. Aeromedical Transport (11 of 12) Safe-approach zone<br>
slide37. Aeromedical Transport (12 of 12) Patient Preparation
Preparing a patient for air transport requires special measures.
Medical procedures must be done before the patient is loaded into the aircraft.
Special equipment must be positioned according to the aircraft’s configuration
Most aeromedical crews perform a brief patient assessment before liftoff to verify the patient’s condition.
Patients who are combative may require physical or chemical restraint during flight.<br>
Focused Lecture<br>
slide2. Ambulance Standards (1 of 3) In 1968, the National Academy of Sciences–National Research Council (NAS-NRC) recommended ambulance design standards that covered size, shape, color, electrical systems, and emergency equipment to be carried on these vehicles.<br>
slide3. Ambulance Standards (2 of 3) Federal Specifications
Eventually led to development of federal specifications many states use as ambulance standards
Collectively known as the federal standards
Provide the basis for uniformity in the design of ambulance vehicles
Three basic ambulance designs
Include additional-duty (AD) vehicles<br>
slide4. Ambulance Standards (3 of 3) National Standards
Federal standards replaced by other national standards of design and performance for ambulance vehicles, October 2016
NFPA 1917, Standard for Automotive Ambulances of the National Fire Protection Association (NFPA)
Ground Vehicle Standard for Ambulances (GVS v.1.0) of the Commission on Accreditation of Ambulance Services.<br>
slide5. Checking Ambulances Completing equipment and supply checklist at beginning of every work shift is essential for safety, patient care, and risk management.
Helps to ensure proper handling and safekeeping of scheduled medications
Routine maintenance, testing, and cleaning<br>
slide6. Ambulance Stationing (1 of 2) 1970s: methods for estimating need for ambulance service and where these vehicles should be stationed in a community were based on availability of ambulances as well as average response time to emergency scene
Methods for estimating needs have shifted toward determining percentage of compliance in providing EMS within time frames that meet national guidelines.<br>
slide7. Ambulance Stationing (2 of 2) Strategies for ambulance stationing often are based on which areas have the highest volume of calls
Deployment strategies vary by EMS agency.
Simple to comprehensive<br>
slide8. Safe Ambulance Operation (1 of 18) Estimated 4,500 vehicle crashes involving an ambulance occur each year
2015: 28 fatalities in crashes involving occupied ambulances<br>
slide9. Safe Ambulance Operation (2 of 18) Estimated 4,500 vehicle crashes involving an ambulance occur each year (cont.)
Safe operation of ambulances is essential for the safety of patients, the EMS crew, and others in the vicinity of a response
Most EMS agencies require their personnel to take an emergency driving course
Numerous factors influence the safe operation of an ambulance<br>
slide10. Safe Ambulance Operation (3 of 18) Estimated 4,500 vehicle crashes involving an ambulance occur each year (cont.)
Maintaining ambulance safety for the EMS provider and the patient is complex and multifactorial.<br>
slide11. Safe Ambulance Operation (4 of 18)<br>
slide12. Safe Ambulance Operation (5 of 18) Appropriate Use of Personal Restraints
84% of EMS providers in patient compartment were not restrained
Many EMS agencies incorporate guidelines into their standard procedures in an effort to protect patients, passengers, and EMS personnel during transports<br>
slide13. Safe Ambulance Operation (6 of 18) Appropriate Use of Escorts
Police escorts during an emergency response Can sometimes be dangerous
Collisions can occur as a result of confusion
Use escorts only when responding to a scene in an unfamiliar area
Tiered response system
Safer emergency response
Proper resources and personnel are available during emergency<br>
slide14. Safe Ambulance Operation (7 of 18) Environmental Conditions
Include poor road and weather condition.
Proceed at a safe speed
Dry roads and clear weather do not guarantee a safe response<br>
slide15. Safe Ambulance Operation (8 of 18) Appropriate Use of Warning Devices
Lights and siren should be used according the agency’s protocol and state’s motor vehicle laws
Based on the patient’s condition and the benefit that may be derived from potential time saved by using lights and siren.<br>
slide16. Safe Ambulance Operation (9 of 18) Appropriate Use of Warning Devices (cont.)
When using lights and siren, motorists who drive with the car windows rolled up or who are using an audio device, air conditioning, or the heating system may not be able to hear the sirens or air horns.
Never assume vehicle’s lights, sirens, and air horns provide an absolute right-of-way or privileged immunity to proceed<br>
slide17. Safe Ambulance Operation (10 of 18) Appropriate Use of Warning Devices (cont.)
EMS agencies using a lights and siren response should avoid using continuous siren tones when traveling unimpeded and not asking for emergency vehicle privileges.
It is important to recognize situations when, regardless of the patient’s condition or the use of lights and siren, the ambulance does not have privileges for the right-of-way in most states.<br>
slide18. Safe Ambulance Operation (11 of 18) Proceeding Safely Through Intersections
Between 43% and 53% of ambulance crashes in the United States occur in intersections where an ambulance proceeds against a red light
Important that the driver of an emergency vehicle stop at all controlled intersections.
Driver should try to make eye contact with all motorists before proceeding through intersection
Alternating the siren’s “yelp” and “wail” modes<br>
slide19. Safe Ambulance Operation (12 of 18) Proceeding Safely Through Intersections (cont.)
Similar strategies should be employed when proceeding against flow of traffic
Speed limited to less than 20 miles per hour (32 km/h).<br>
slide20. Safe Ambulance Operation (13 of 18) Parking at the Emergency Scene
If law enforcement and fire service personnel have secured the scene
Position about 100 feet (30 m) past scene, on same side of road
Positioned uphill (about 200 feet [60 m]). upwind
If law enforcement and fire service personnel have NOT secured the scene
Position diagonally about 50 feet (15 m) in front of scene in the fend-off position
Deflect and avert from scene other vehicles that may strike<br>
slide21. Safe Ambulance Operation (14 of 18) Parking at the Emergency Scene (cont.)
Other safety precautions
Set the parking brake
Help guide the vehicle when it is backing up
Wear reflective gear<br>
slide22. Safe Ambulance Operation (15 of 18) The “fend-off” position.<br>
slide23. Safe Ambulance Operation (16 of 18) Operating With Due Regard for the Safety of All Others
Most states allow privileges for drivers of emergency vehicles, must take into consideration safety of all people using roads
Includes maintaining a safe following distance to avoid rear-end collisions
“Due regard for the safety of all others” carries legal responsibility
Paramedic and EMS agency can incur liability if damage, injury, or death results from failure to observe this principle<br>
slide24. Safe Ambulance Operation (17 of 18) Safely Moving a Patient Into and Out of an Ambulance
After initial stabilization at scene, patient must be packaged and safely placed in emergency vehicle for transport
Safe lifting practices
Ensure patient is positioned securely
Locking devices
Unnecessary equipment should be stowed before transport.<br>
slide25. Safe Ambulance Operation (18 of 18) Safely Moving a Patient Into and Out of an Ambulance (cont.)
During transport, the patient should be closely monitored for any changes in status.
On arrival at the hospital, the ambulance should come to a full stop.
Personal restraints can be removed
All patient care equipment must be secured before stretcher is released from locking device.
Using safe lifting techniques, patient’s stretcher should be removed from ambulance.<br>
slide26. Aeromedical Transport (1 of 12) Like many other aspects of prehospital emergency care, air evacuation is rooted in military history.
More than 300 air medical service programs using fixed-wing aircraft and/or rotary-wing aircraft have been established throughout the United States.<br>
slide27. Aeromedical Transport (2 of 12) Aeromedical Crew Members and Training
Staffing of air ambulances includes a pilot and various health care professionals
Specialized training in flight physiology and advanced medical equipment and procedures<br>
slide28. Aeromedical Transport (3 of 12) Use of Aeromedical Services
Local EMS system develops the criteria for requesting aeromedical services’ response to the scene of an emergency.
Decision should be supported by appropriate triage and evaluation of the scene
Considerations for air transport<br>
slide29. Aeromedical Transport (4 of 12) Notification of Aeromedical Services
If paramedics request air service for medical, trauma, or search and rescue events, they should advise the flight crew of:
The type of emergency response
The number of patients
The location of a landing zone (LZ)
Any prominent landmarks and hazards<br>
slide30. Aeromedical Transport (5 of 12) Notification of Aeromedical Services (cont.)
Direct ground-to-air communication must be available between a designated LZ officer and the aeromedical staff on the responding aircraft.
If possible, the fire department should be dispatched to the LZ to provide fire-suppression support.
Law enforcement personnel should be available for securing the scene.<br>
slide31. Aeromedical Transport (6 of 12) Landing Site Preparation
If a nighttime LZ is used, emergency vehicles with lighted bar lights should be situated at the perimeters of the LZ.
If white lights are used, should be directed down toward the center of LZ as spotlights, because white lights directed toward the aircraft can temporarily blind the pilot.
Rescue personnel should never be used to identify the LZ
Flares should not be used
Wet down dusty LZs<br>
slide32. Aeromedical Transport (7 of 12) Landing Site Preparation (cont.)
Helpful radio communications with the pilot include notification of wind direction and any possible obstructions or hazards.
Patient status and clinical information should not be relayed to the aeromedical crew<br>
slide33. Aeromedical Transport (8 of 12) Landing Site Preparation (cont.)
Pilot generally does not land the aircraft until all danger of fire or explosion has been eliminated.
One emergency responder should stand facing the LZ so that the pilot will see the landing area.
LZ hand signals that may be useful to the pilot<br>
slide34. Aeromedical Transport (9 of 12) Landing zone hand signals<br>
slide35. Aeromedical Transport (10 of 12) Safety Precautions
Everyone should be clear of the landing area during takeoffs and landings
A distance of 100 to 200 feet (30 to 60 m) is best
Take precautions<br>
slide36. Aeromedical Transport (11 of 12) Safe-approach zone<br>
slide37. Aeromedical Transport (12 of 12) Patient Preparation
Preparing a patient for air transport requires special measures.
Medical procedures must be done before the patient is loaded into the aircraft.
Special equipment must be positioned according to the aircraft’s configuration
Most aeromedical crews perform a brief patient assessment before liftoff to verify the patient’s condition.
Patients who are combative may require physical or chemical restraint during flight.<br>