Emergency Department Patient Flow Maximizing Patient Throughput and Addressing Patient Satisfaction J. Scheulen, Johns Hopkins L. Davis-Moon, Thomas Jefferson 492013 1 AACEM and AAAEM Panel Discussion Patient Throughput Panel Discussants
"Emergency Department Patient Flow Maximizing" is the property of its rightful owner. Permission is granted to
download and print the materials on this website for personal, non-commercial use only, and to display it
on your personal computer provided you do not modify the materials and that you retain all copyright
notices contained in the materials. By downloading content from our website, you accept the terms of this
agreement.
Presentation Transcript
01
Emergency Department Patient Flow Maximizing Patient Throughput and Addressing Patient Satisfaction
J. Scheulen, Johns Hopkins
L. Davis-Moon, Thomas Jefferson 4/9/2013 1 AACEM and AAAEM
Panel Discussion<br>
02
Patient Throughput Panel Discussants Travis Schmitz, Northwestern
Care on Arrival
Louis Burton, Grady
Low acuity patient re-direction
Adrian Tyndall, MD, Florida
Front end operational changes
James McCarty MD, Hermann Hospital
Expedited MICU Admission
Louis Burton, Grady
Boarding---What’s that????
Jim Scheulen, Johns Hopkins
Simulation Modeling ED Operations
Ted Christopher, MD, Thomas Jefferson
Patient Satisfaction 4/9/2013 2<br>
03
Emergency Department Patient Throughput 4/9/2013 3<br>
04
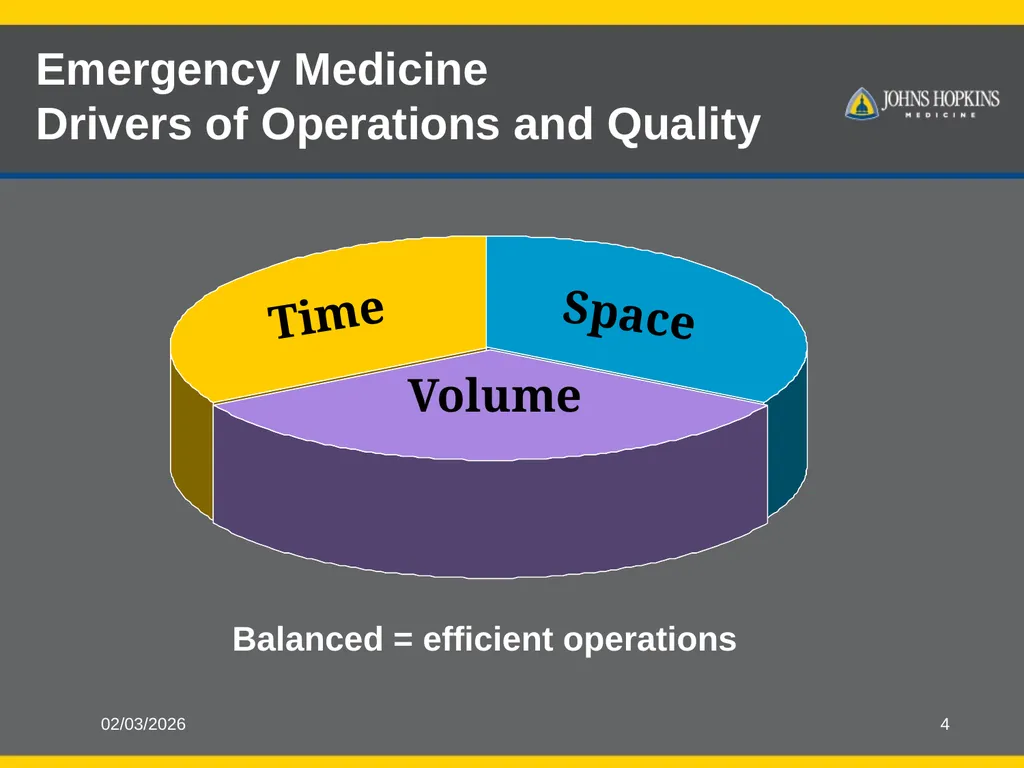
Emergency Medicine Drivers of Operations and Quality 4/9/2013 4 Balanced = efficient operations<br>
05
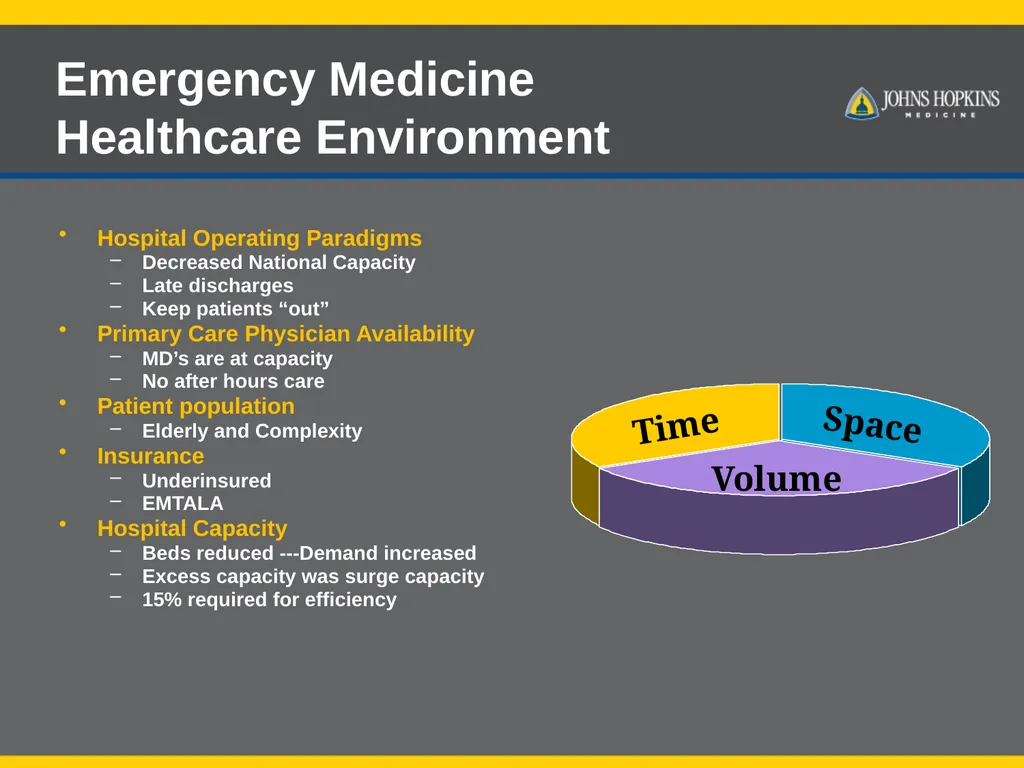
Emergency Medicine Healthcare Environment Hospital Operating Paradigms
Decreased National Capacity
Late discharges
Keep patients “out”
Primary Care Physician Availability
MD’s are at capacity
No after hours care
Patient population
Elderly and Complexity
Insurance
Underinsured
EMTALA
Hospital Capacity
Beds reduced ---Demand increased
Excess capacity was surge capacity
15% required for efficiency<br>
06
Emergency Medicine Service Expectations 24 Hour Service
Minimal Waiting Time
Demand Based Service
Different Expectations AND A Different Standard
It’s okay to wait days for my MD but not hours in ED
Convenience and Episodic Care Drive thru if possible!!!<br>
07
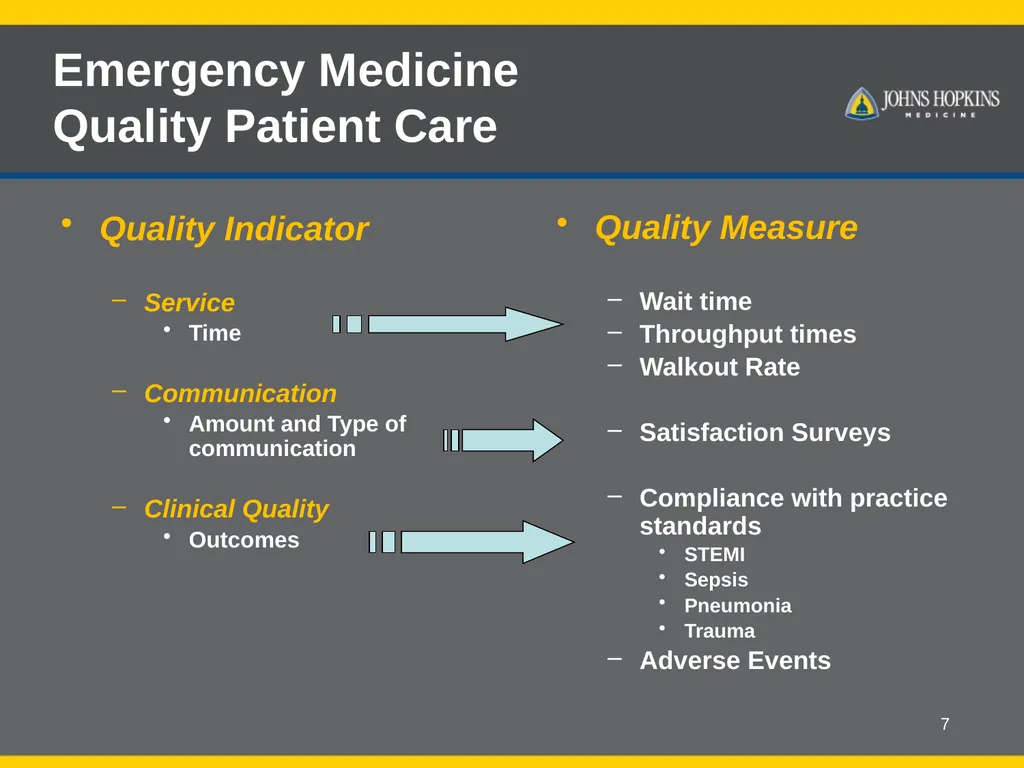
7 Emergency Medicine Quality Patient Care Quality Indicator
Service
Time
Communication
Amount and Type of communication
Clinical Quality
Outcomes Quality Measure
Wait time
Throughput times
Walkout Rate
Satisfaction Surveys
Compliance with practice standards
STEMI
Sepsis
Pneumonia
Trauma
Adverse Events<br>
08
4/9/2013 8 Time is central to
Emergency Medicine Quality = Time<br>
09
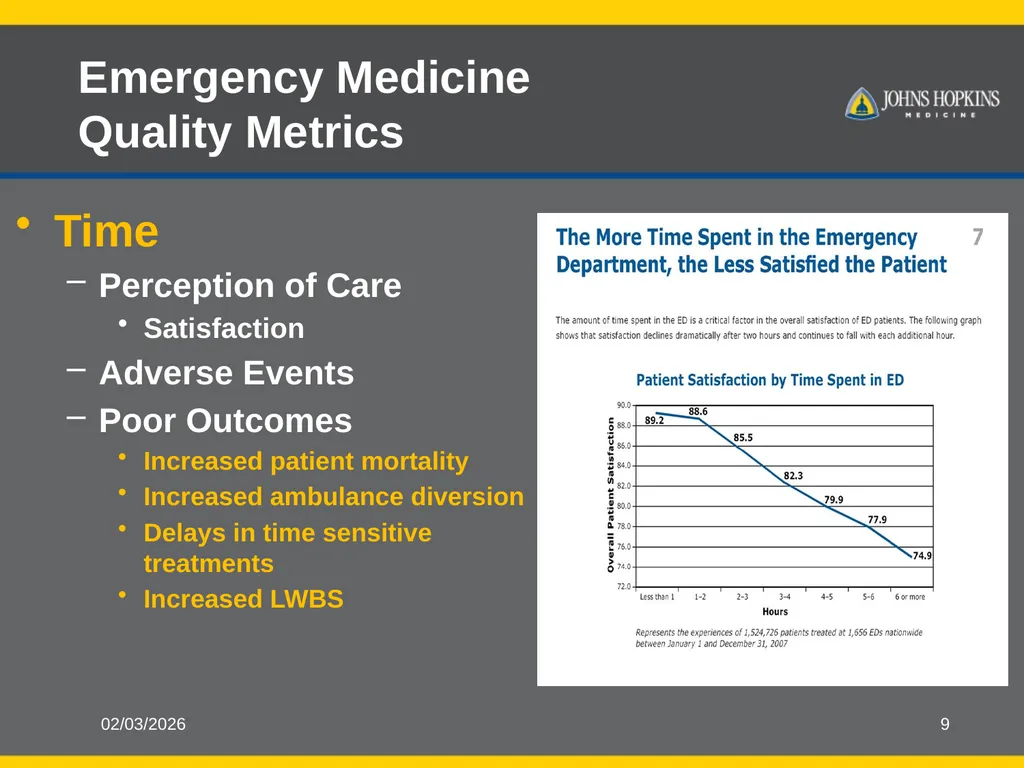
Emergency Medicine Quality Metrics Time
Perception of Care
Satisfaction
Adverse Events
Poor Outcomes
Increased patient mortality
Increased ambulance diversion
Delays in time sensitive treatments
Increased LWBS 4/9/2013 9<br>
10
Emergency Medicine All about Process Segmenting Patient Flow in the ED<br>
11
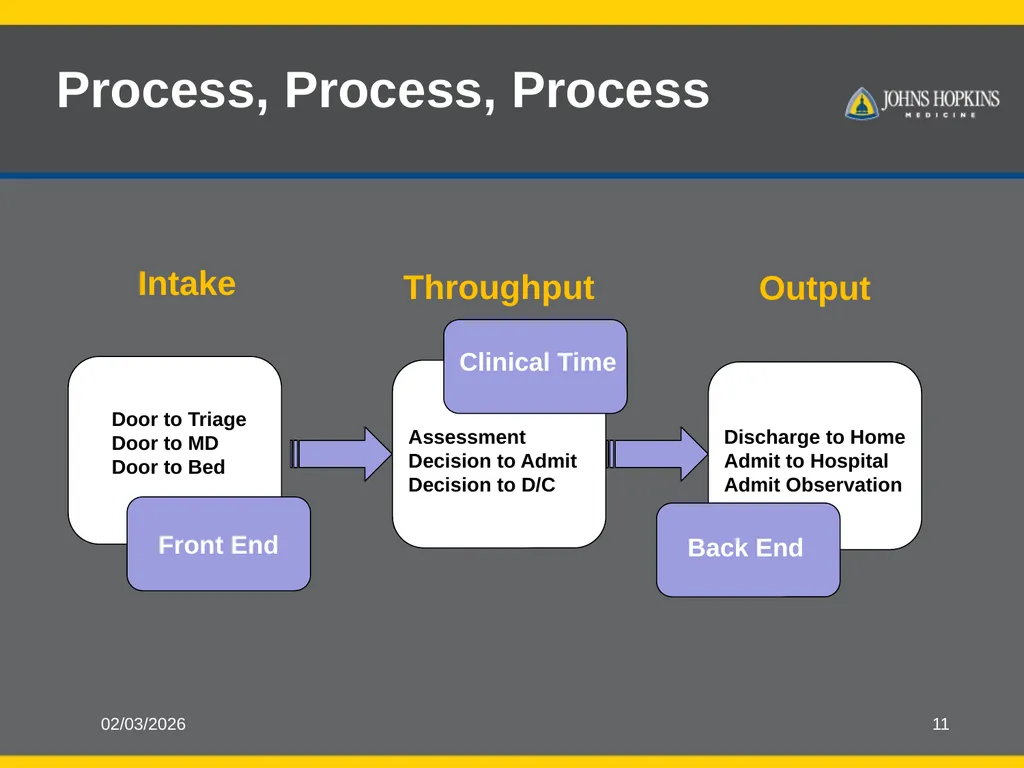
Process, Process, Process 4/9/2013 11 Intake Throughput Output<br>
12
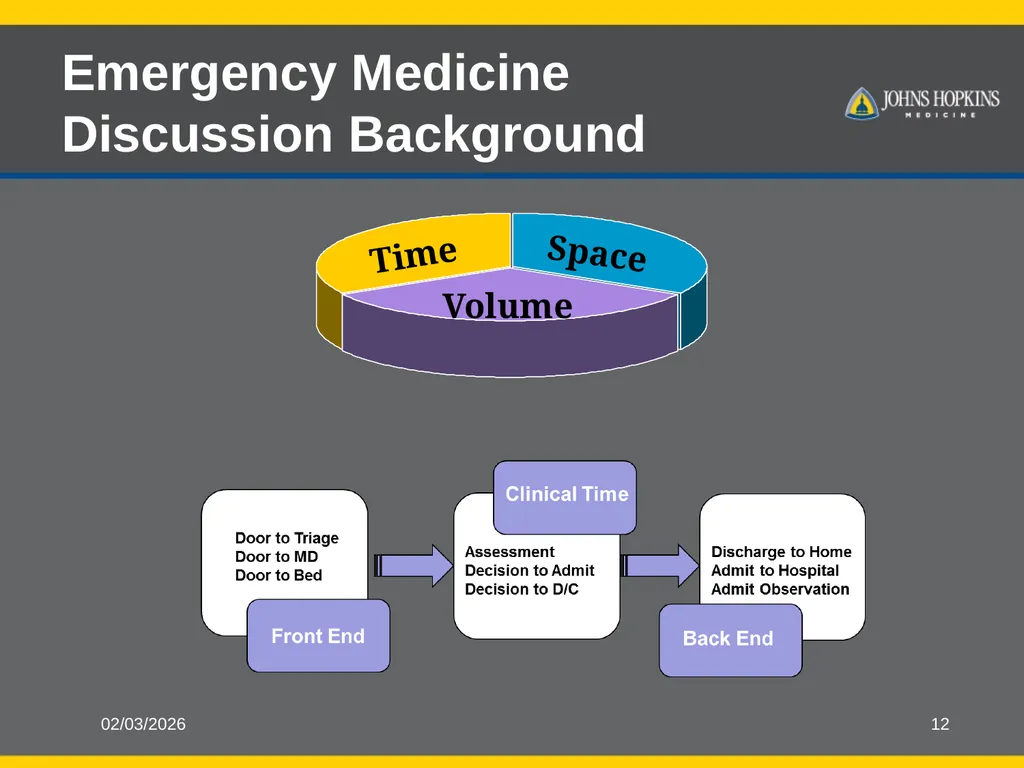
Emergency Medicine Discussion Background 4/9/2013 12<br>
13
Discussion and Questions Best Practices: Front, Middle, Back End
Related Questions:
What are the most important metrics to use in order to monitor success?
As a way of managing “excess” volume, are there hospitals who successfully redirect patients to alternate treatment sites?
Who in your system is responsible for the care of the patient who is boarding in the ED?
Has anyone identified an effective way to manage physician practice variability? 4/9/2013 13<br>
14
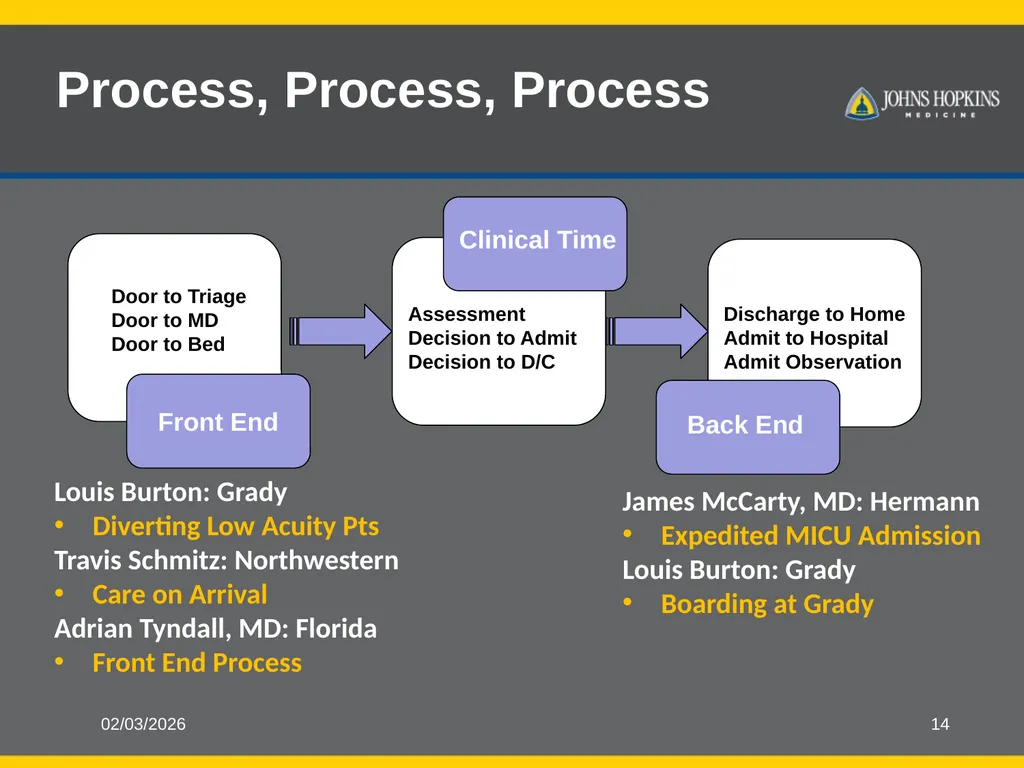
Process, Process, Process 4/9/2013 14 Louis Burton: Grady
Diverting Low Acuity Pts
Travis Schmitz: Northwestern
Care on Arrival
Adrian Tyndall, MD: Florida
Front End Process James McCarty, MD: Hermann
Expedited MICU Admission
Louis Burton: Grady
Boarding at Grady<br>