
General Infection Prevention Practices Debbie
OM
Published · 72 slides · 0 views

1 / 1





























































Description
General Infection Prevention Practices Debbie Hurst RN, BSN Program Manager, Infection Prevention Control Rogue Valley Medical Center 1 2 http:www.youtube.comwatch?vySizJnSnK8 Objectives Describe Standard Precautions practices and
Related Topics
Share
Embed code
Download this presentation From Below
"General Infection Prevention Practices Debbie" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
01
General Infection Prevention Practices Debbie Hurst RN, BSN
Program Manager, Infection Prevention & Control
Rogue Valley Medical Center 1<br>
Program Manager, Infection Prevention & Control
Rogue Valley Medical Center 1<br>
02
2 http://www.youtube.com/watch?v=ySiz_JnSnK8<br>
03
Objectives Describe Standard Precautions practices and use of appropriate personal protective equipment (PPE)
Identify proper hand hygiene practices
Identify how to manage patients with potential transmissible diseases in an ASC 3<br>
Identify proper hand hygiene practices
Identify how to manage patients with potential transmissible diseases in an ASC 3<br>
04
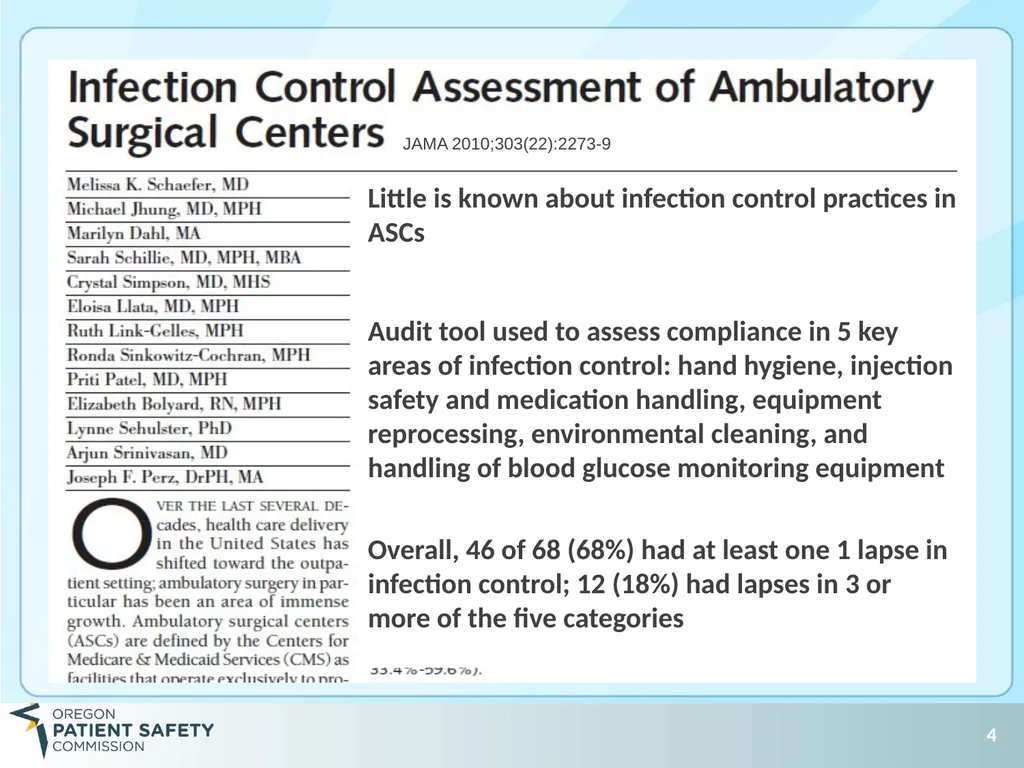
4 Little is known about infection control practices in ASCs Audit tool used to assess compliance in 5 key areas of infection control: hand hygiene, injection safety and medication handling, equipment reprocessing, environmental cleaning, and handling of blood glucose monitoring equipment Overall, 46 of 68 (68%) had at least one 1 lapse in infection control; 12 (18%) had lapses in 3 or more of the five categories JAMA 2010;303(22):2273-9<br>
05
CMS Survey CMS will observe:
Soap and water availability
Alcohol-based hand rubs available and installed appropriately
Hand hygiene performed:
After removing gloves
After direct patient contact
Before invasive procedures
After contact with blood and body fluid (BBF) or contaminated surfaces (even if gloves worn) 5<br>
Soap and water availability
Alcohol-based hand rubs available and installed appropriately
Hand hygiene performed:
After removing gloves
After direct patient contact
Before invasive procedures
After contact with blood and body fluid (BBF) or contaminated surfaces (even if gloves worn) 5<br>
06
Oregon HCRQI General Infection Prevention Program Findings Lack of a policy and system for reporting infectious diseases or outbreak management
Hand hygiene: not done between patients, after removal of gloves, and after contact with contaminated materials
Personal protective equipment (e.g., gloves) not used for contact with contaminated material
Staff drinks with lids by the handwashing station
Gloves not always worn when starting IVs
Hand sanitizers not mounted appropriately 6<br>
07
Standard Precautions Used for all patients
To prevent bloodborne pathogen transmission
To prevent transmission of other organisms
To protect both patients and staff 7<br>
To prevent bloodborne pathogen transmission
To prevent transmission of other organisms
To protect both patients and staff 7<br>
08
Standard Precautions Includes hand hygiene/hand washing
Personal protective equipment (PPE)
Sharps precautions
Equipment handling
Linen handling
Waste and lab specimen handling
Cleaning and disinfecting 8<br>
Personal protective equipment (PPE)
Sharps precautions
Equipment handling
Linen handling
Waste and lab specimen handling
Cleaning and disinfecting 8<br>
09
Helps prevent disease transmission
Handwash with soap and water
Agent, Friction, Time
Hand sanitizer needs to dry
No artificial or long nails for personnel with patient contact
Monitor adherence to CDC/WHO hand hygiene guidelines Hand Hygiene 9<br>
Handwash with soap and water
Agent, Friction, Time
Hand sanitizer needs to dry
No artificial or long nails for personnel with patient contact
Monitor adherence to CDC/WHO hand hygiene guidelines Hand Hygiene 9<br>
10
Nurse Hand
Shows bacterial growth
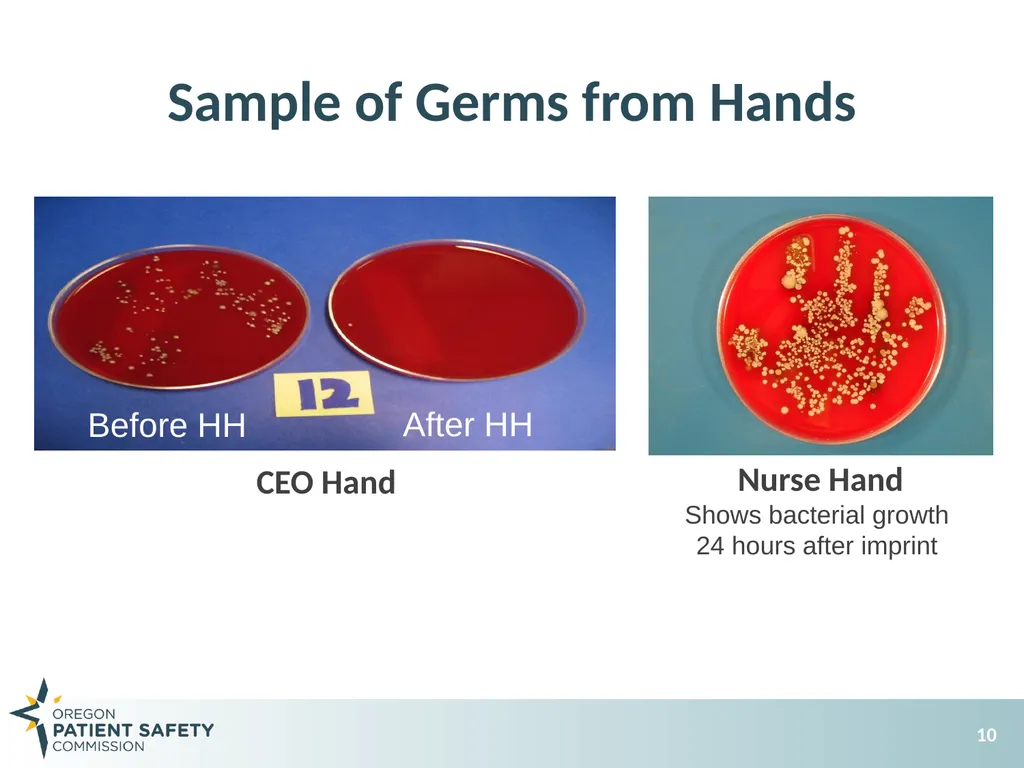
24 hours after imprint Sample of Germs from Hands 10 CEO Hand Before HH After HH<br>
Shows bacterial growth
24 hours after imprint Sample of Germs from Hands 10 CEO Hand Before HH After HH<br>
11
Reasons why healthcare workers do not wash their hands as often as they should:
Heavy workloads (too busy)
Skin irritation caused by frequent use of soap and water
Hands don’t look dirty
Sinks are poorly located
Handwashing takes too long Why is Compliance with Recommended Handwashing so Poor? 11<br>
Heavy workloads (too busy)
Skin irritation caused by frequent use of soap and water
Hands don’t look dirty
Sinks are poorly located
Handwashing takes too long Why is Compliance with Recommended Handwashing so Poor? 11<br>
12
Sinks used for handwashing are often installed in bad locations.
Workers may fail to wash their hands when indicated because it is too much trouble to get to the sinks provided.
Can you find the sink in this picture? Where’s the Sink? 12<br>
Workers may fail to wash their hands when indicated because it is too much trouble to get to the sinks provided.
Can you find the sink in this picture? Where’s the Sink? 12<br>
13
When compared to traditional soap and water handwashing, alcohol hand rubs have the following advantages:
Take less time to use
Can be made more accessible than sinks
Cause less skin irritation and dryness
Are more effective in reducing the number of germs on hands
Making alcohol-based hand rubs readily available to personnel has led to improved hand hygiene practices Advantages of Cleaning Hands with Alcohol-based Hand Rubs 13<br>
14
Wash your hands with plain soap and water or with anti-microbial soap and water if:
Your hands are visibly soiled (dirty)
Hands are visibly contaminated with blood or body fluids
Before eating
After using the restroom
Consider after providing care to a
patient with C. difficile When Should You Wash Your Hands with Soap and Water? 14<br>
Your hands are visibly soiled (dirty)
Hands are visibly contaminated with blood or body fluids
Before eating
After using the restroom
Consider after providing care to a
patient with C. difficile When Should You Wash Your Hands with Soap and Water? 14<br>
15
When Should You Use an
Alcohol-based Hand Rub? If hands are not visibly soiled or contaminated with blood or body fluids, use an alcohol-based hand rub for routinely cleaning your hands:
Before having direct contact with one patient after having direct contact with another patient’s skin
After having contact with body fluids, wounds or broken skin
After touching equipment or furniture near the patient
After removing gloves
Surveyors may ask staff to identify when they should use soap and water instead of hand sanitizers 15<br>
16
Hand Hygiene Tools The toolkit contains the following:
Hand Hygiene Policy and Procedure (2.01a)
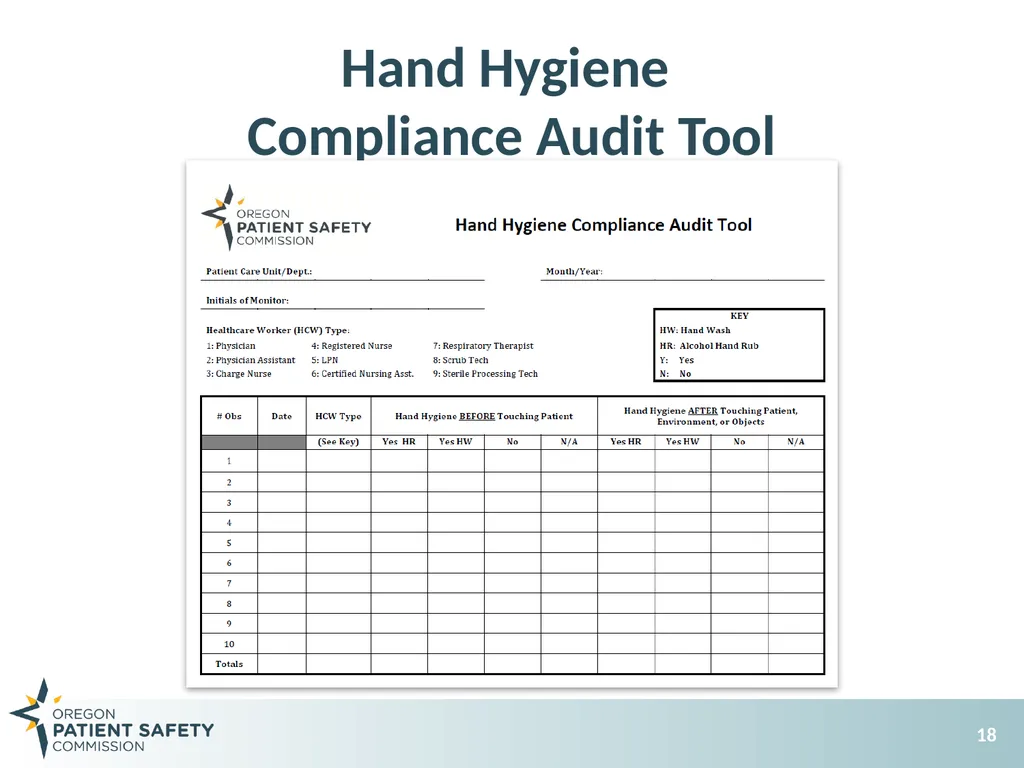
Hand Hygiene Compliance Audit Tool (2.01b)
Surgical Hand Rub or Hand Scrub Policy and Procedure (2.01c)
Web links:
CDC Guidelines for Hand Hygiene
WHO Guidelines for Hand Hygiene
CDC and other hand hygiene resource centers which include training programs and posters 16<br>
17
Why Monitor Hand Hygiene? Hand hygiene is a major platform for establishing a safe environment for our patients
Hand hygiene is a behavior; all behaviors need constant attention to be reinforced and maintained
Having a conversation focuses the attention
To be effective, the conversation should deliver feedback on performance and make recommendations based on that performance 17<br>
Hand hygiene is a behavior; all behaviors need constant attention to be reinforced and maintained
Having a conversation focuses the attention
To be effective, the conversation should deliver feedback on performance and make recommendations based on that performance 17<br>
18
Hand Hygiene
Compliance Audit Tool 18<br>
19
Hand Hygiene
Compliance Audit Tool Hand hygiene feedback needs accurate and reliable data to be meaningful
Consistent data collection is needed because it tells you where you are in achieving the desired behavior
The Hand Hygiene Compliance Audit Tool is an observational tool, but it does not need to be completed at the same time; instead, observe behavior as you round or assist with patient care, then complete the form
Collect data on a monthly basis and share results with all staff, LIPs, HCPs, volunteers, etc. 19<br>
20
When Should Hand Hygiene
Not be Performed? 20<br>
21
CMS Survey CMS will observe:
Staff wear gloves for procedures that might involve contact with blood or body fluids (e.g., starting IVs)
Wear gloves when handling potentially contaminated patient equipment
Remove gloves before moving to the next task and/or patient
Note: PPE needs to be provided by the employer but staff need to know its location 21<br>
22
Personal Protective Equipment Wear gloves if contact is anticipated with blood, blood products, body fluids, excretions, secretions, mucous membranes, non-intact skin, drainage tubes, or when performing venipuncture or invasive procedures
Wear gowns/aprons if soiling with any of the above is anticipated
Wear face/eye protection (mask and goggles or face shield) during procedures that are likely to generate droplets or splashing 22<br>
Wear gowns/aprons if soiling with any of the above is anticipated
Wear face/eye protection (mask and goggles or face shield) during procedures that are likely to generate droplets or splashing 22<br>
23
Additional Mask Requirement Wear a surgical mask when placing a catheter or injecting material into an epidural or subdural space 23<br>
24
Linen and Laundry Clean linen must be covered when in areas of public access
Minimize soiled linen handling
Handle dirty laundry with gloves at a minimum
Wear a gown with gloves if patient linens are soiled or patient has diarrhea
Do not carry dirty linen through unit; instead, place hampers close to point of use
Used linen should be placed in an impervious bag or placed in a container lined with an impervious bag 24<br>
25
Contracted Services Need documentation of your evaluation and oversight of contracted services (e.g., environmental services and linen)
Need to evaluate the safety and effectiveness of those services 25<br>
Need to evaluate the safety and effectiveness of those services 25<br>
26
Lab Specimens Place in container which prevents leakage
Transport in biohazard bag
No food or drink in vicinity of where blood or other body substances may be placed 26<br>
Transport in biohazard bag
No food or drink in vicinity of where blood or other body substances may be placed 26<br>
27
What Goes Into “Red Bag” or
Biohazardous Waste? Any blood/body substance that could be expelled when squeezed or compressed
Small amounts of tissue
Surgery drapes with pouches
Containers with blood or body fluids
Tubing with blood or body fluids
Cultures of infectious agents, culture dishes, swabs
Syringes that never had a needle attached
Waste containers or bags should be impervious 27<br>
Small amounts of tissue
Surgery drapes with pouches
Containers with blood or body fluids
Tubing with blood or body fluids
Cultures of infectious agents, culture dishes, swabs
Syringes that never had a needle attached
Waste containers or bags should be impervious 27<br>
28
What Goes into Regular Waste? Gowns, gloves, shoe covers
Paper drapes
Q-tips, swabs
Diapers, peri-pads
Toolkit contains links to Oregon Infectious Waste Disposal Pamphlet
Check your county and landfill regulations as well 28<br>
Paper drapes
Q-tips, swabs
Diapers, peri-pads
Toolkit contains links to Oregon Infectious Waste Disposal Pamphlet
Check your county and landfill regulations as well 28<br>
29
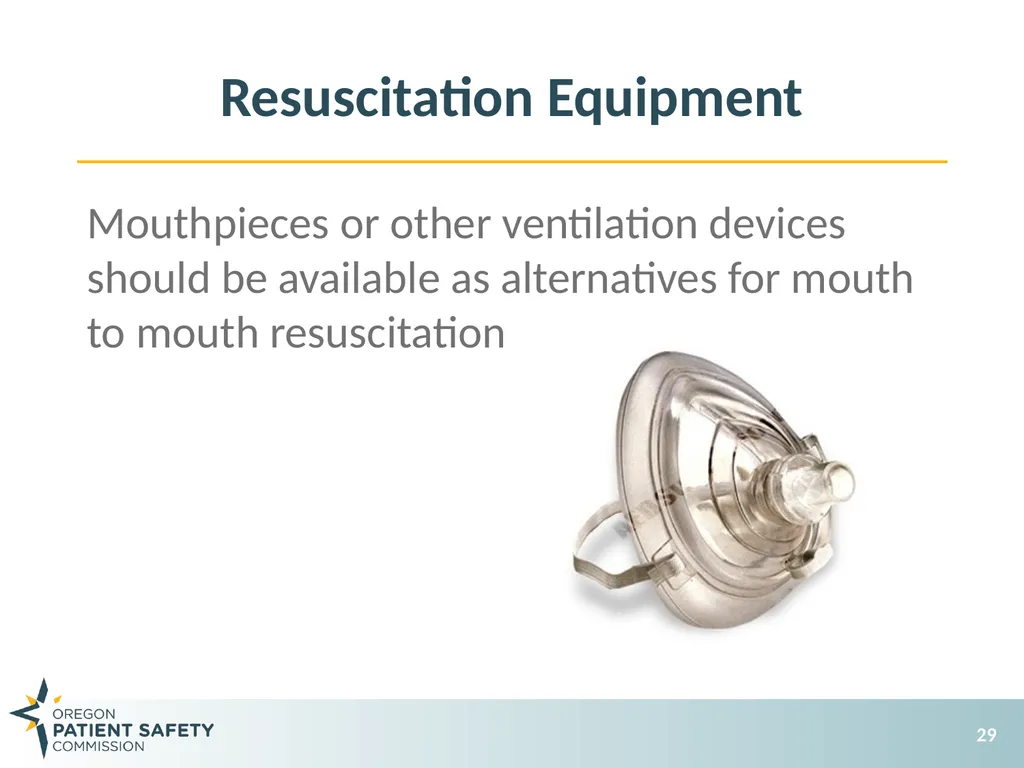
Resuscitation Equipment Mouthpieces or other ventilation devices should be available as alternatives for mouth to mouth resuscitation 29<br>
30
Cleaning Blood Spills Blood or body fluids should first be removed
The area should then be decontaminated using a hospital approved EPA disinfectant
Gloves should always be worn; based on the size of the spill, additional PPE may need to be worn
Never pick up broken glass with hands 30<br>
The area should then be decontaminated using a hospital approved EPA disinfectant
Gloves should always be worn; based on the size of the spill, additional PPE may need to be worn
Never pick up broken glass with hands 30<br>
31
Disinfect Shared Patient Equipment Patient care equipment such as: wheelchairs, gurneys, BP cuffs, stethoscopes, etc.
Include computers: keyboard, mouse, screen 31<br>
Include computers: keyboard, mouse, screen 31<br>
32
Toolkit Contents Standard Precautions Policy (2.04)
Web links to:
Oregon OSHA Bloodborne Pathogen Standards
Resources including a Federal OSHA Bloodborne Exposure Control Plan Template
Oregon’s Infectious Waste Regulations 32<br>
Web links to:
Oregon OSHA Bloodborne Pathogen Standards
Resources including a Federal OSHA Bloodborne Exposure Control Plan Template
Oregon’s Infectious Waste Regulations 32<br>
33
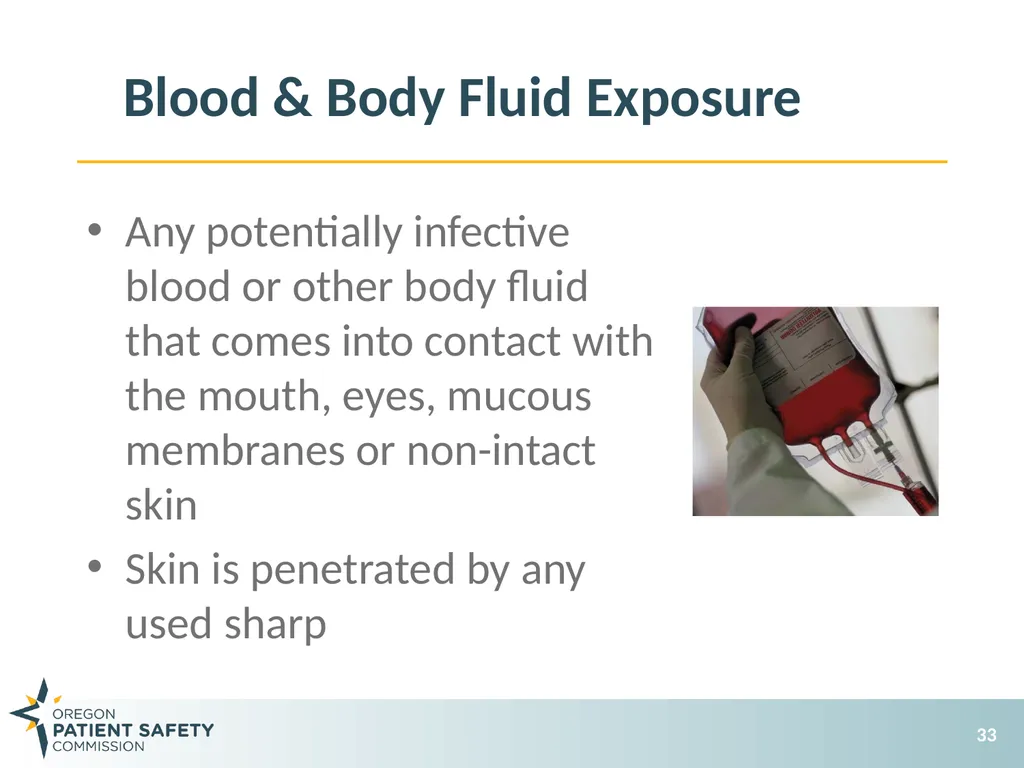
Blood & Body Fluid Exposure Any potentially infective blood or other body fluid that comes into contact with the mouth, eyes, mucous membranes or non-intact skin
Skin is penetrated by any used sharp 33<br>
Skin is penetrated by any used sharp 33<br>
34
Sharps Safety Every day, more than 1,000 healthcare workers (HCW) are injured with a needle or other sharp device.
Risk of:
Hepatitis B: 1 in 5 (if not vaccinated)
Hepatitis C: 1 in 50
HIV: 1 in 300
Source: Centers for Disease Control & Prevention. Updated U.S. Public Health Service Guidelines for the Management of Occupational Exposures to HBV, HCV, and HIV and Recommendations for Postexposure Prophylaxis. Morbidity and Mortality Weekly Report, 50(RR11), 1-42. 34<br>
35
Sharps Injuries in the OR Nationally, 30.4% of hospital sharps injuries occur in the OR (Source: Hosp. Emp. Health, 2008)
Nationally, 20% of all sharps injuries involve a suture needle (Source: Hosp. Emp. Health, 2008) 35<br>
Nationally, 20% of all sharps injuries involve a suture needle (Source: Hosp. Emp. Health, 2008) 35<br>
36
1991 OSHA Bloodborne
Pathogens (BBP) Standard Required employers to:
Develop a written exposure control plan
Implement universal (standard) precautions
Provide personal protective equipment
Use preventative engineering and work practice controls
Prohibit bending, recapping and removing contaminated sharps 36<br>
Develop a written exposure control plan
Implement universal (standard) precautions
Provide personal protective equipment
Use preventative engineering and work practice controls
Prohibit bending, recapping and removing contaminated sharps 36<br>
37
2000 Needlestick Safety & Prevention Act Required OSHA to update the BBP Standard in four areas:
Modification of definitions relating to engineering controls (sharps with injury prevention and needleless systems)
Revision and update of exposure control plans
Maintain more detailed sharps injury logs
Solicitation of health care workers input 37<br>
Modification of definitions relating to engineering controls (sharps with injury prevention and needleless systems)
Revision and update of exposure control plans
Maintain more detailed sharps injury logs
Solicitation of health care workers input 37<br>
38
“Every employer with employees that use medical sharps in direct patient care must, at least annually, identify, evaluate and select engineering and work practice controls, including safer medical devices.”
(OAR 437-002-0360)
Involve frontline employees
Additional documentation on device evaluation, selection process, implementation
Employees are informed of selection process for safer medical devices 38 Additional Oregon Rules<br>
(OAR 437-002-0360)
Involve frontline employees
Additional documentation on device evaluation, selection process, implementation
Employees are informed of selection process for safer medical devices 38 Additional Oregon Rules<br>
39
39 In the past 4 years, OSHA has increased ASC inspections, citing more ASCs and MD offices for violations
The most frequent violations were:
Outdated or nonexistent exposure control plans
Poor documentation
Failure to use safety devices
Lack of free training during working hours
Infection Control Today 11/8/2011 OSHA Most Frequently Cites ASCs for Bloodborne Pathogen Violations<br>
The most frequent violations were:
Outdated or nonexistent exposure control plans
Poor documentation
Failure to use safety devices
Lack of free training during working hours
Infection Control Today 11/8/2011 OSHA Most Frequently Cites ASCs for Bloodborne Pathogen Violations<br>
40
OSHA Violations (cont.) The violations that merited the largest fines dealt with:
Failure to immediately remove personal protective equipment (PPE) penetrated with body fluids
Failure to use safety devices
Failure to provide workers with a free Hepatitis B vaccination and follow-up 40<br>
Failure to immediately remove personal protective equipment (PPE) penetrated with body fluids
Failure to use safety devices
Failure to provide workers with a free Hepatitis B vaccination and follow-up 40<br>
41
87% of U.S. nurses say safety concerns influence the decisions made about the type of nursing they do
82% admit to putting patient care before their own personal safety at work
64% report being accidentally stuck by a needle
74% of nurses say needlestick injuries are underreported 41 2008 ANA Study of Nurses Views on Workplace Safety & Needlestick Injuries<br>
82% admit to putting patient care before their own personal safety at work
64% report being accidentally stuck by a needle
74% of nurses say needlestick injuries are underreported 41 2008 ANA Study of Nurses Views on Workplace Safety & Needlestick Injuries<br>
42
“The overall range of costs to manage reported exposure was $74 - $4838.” (CABI Abstract, 2003)
One case of serious infection by BBPs can soon add up to $1 million or more in expenditures for testing, follow-up, lost time, disability
The potential emotional impact…PRICELESS 42 Cost of Exposure<br>
One case of serious infection by BBPs can soon add up to $1 million or more in expenditures for testing, follow-up, lost time, disability
The potential emotional impact…PRICELESS 42 Cost of Exposure<br>
43
Types of Sharp Safety Devices Needle-free IV systems
Sheathed, blunting or retractable needles
Blood transfer adapters
Non-breakable plastic vacuum and capillary tubes
Sharps disposal devices
Employers are required to have frontline workers involved in selecting safety devices 43<br>
Sheathed, blunting or retractable needles
Blood transfer adapters
Non-breakable plastic vacuum and capillary tubes
Sharps disposal devices
Employers are required to have frontline workers involved in selecting safety devices 43<br>
44
Selecting Sharp Safety Devices Consider sharp safety devices with the following:
Come attached with safety features that can’t be removed
Are easy to use and have clear instructions
Do not interfere with patient care
Can be engaged with one hand
Enable hands to remain behind the exposed sharp
Are visibly different when activated 44<br>
Come attached with safety features that can’t be removed
Are easy to use and have clear instructions
Do not interfere with patient care
Can be engaged with one hand
Enable hands to remain behind the exposed sharp
Are visibly different when activated 44<br>
45
High Risk Activities Inserting or withdrawing a needle
Inserting needles into IV lines
Handling or passing sharps
Recapping a used needle
Transferring or processing specimens
Disposing of sharps into proper containers
Cleaning up after a procedure
Sharps left on floors and tables or found in linen, beds, or waste containers 45<br>
Inserting needles into IV lines
Handling or passing sharps
Recapping a used needle
Transferring or processing specimens
Disposing of sharps into proper containers
Cleaning up after a procedure
Sharps left on floors and tables or found in linen, beds, or waste containers 45<br>
46
Causes of Sharps Injuries 80% of sharps injuries are due to the use of:
Hypodermic needles/syringes
Suture needles
Winged-steel (butterfly) needles
Blood collection needles
Scalpels
IV stylets
Other items such as glass can also cause injury 46<br>
Hypodermic needles/syringes
Suture needles
Winged-steel (butterfly) needles
Blood collection needles
Scalpels
IV stylets
Other items such as glass can also cause injury 46<br>
47
Be Prepared Organize your work area with appropriate sharps disposal containers within reach
Work in well-lighted areas
Receive training on how to use sharps safety devices
Before handling sharps, assess any hazards; get help if needed 47<br>
Work in well-lighted areas
Receive training on how to use sharps safety devices
Before handling sharps, assess any hazards; get help if needed 47<br>
48
Be Aware Keep the exposed sharp in view
Be aware of people around you
Stop if you feel rushed or distracted
Focus on your task
Avoid hand-passing sharps and use verbal alerts when moving sharps
Watch for sharps in linen, beds, on the floor, or in waste containers 48<br>
Be aware of people around you
Stop if you feel rushed or distracted
Focus on your task
Avoid hand-passing sharps and use verbal alerts when moving sharps
Watch for sharps in linen, beds, on the floor, or in waste containers 48<br>
49
Dispose of Sharps with Care Be responsible for the device you use
Activate safety features after use
Dispose of devices in rigid sharps containers; do not overfill containers
Keep fingers away from the opening of sharps containers 49<br>
Activate safety features after use
Dispose of devices in rigid sharps containers; do not overfill containers
Keep fingers away from the opening of sharps containers 49<br>
50
Facilities that Value Safety have Fewer Sharps Injuries Sharps injury prevention is a prominent organizational priority
Management and staff have a shared commitment to prevent sharps injuries
Staff members are encouraged to report sharps injuries promptly
Individual safety accountability is promoted 50<br>
Management and staff have a shared commitment to prevent sharps injuries
Staff members are encouraged to report sharps injuries promptly
Individual safety accountability is promoted 50<br>
51
Toolkit Contents Section 6: Employee Health Program, has several policies, procedures and forms to address BBF exposure follow-up 51<br>
52
Management of Patients with Potentially Communicable Diseases Standard Precautions are used for all patients and all situations
Some diseases require additional precautions in conjunction with Standard Precautions, such as the use of a mask 52<br>
Some diseases require additional precautions in conjunction with Standard Precautions, such as the use of a mask 52<br>
53
Management of Patients with Transmissible Diseases CDC’s Transmission-based Precautions Policy is somewhat vague for implementation in ambulatory environment, especially for contact precautions (multi-drug resistant organisms (MDROs))
Diseases requiring isolation for airborne or droplet precautions should not be treated in ASCs; instead, procedures should be delayed until illness is resolved 53<br>
Diseases requiring isolation for airborne or droplet precautions should not be treated in ASCs; instead, procedures should be delayed until illness is resolved 53<br>
54
Patient Scheduling Screen patients for potential infections (fever, rash, new onset diarrheal illness)
Reschedule patients with acute infections
Screen patients for history of MRSA or another type of MDRO
If patient has an active infection, consult physician to determine if they wish to reschedule procedure
It is not necessary to schedule patients with MDROs as the last case of the day 54<br>
Reschedule patients with acute infections
Screen patients for history of MRSA or another type of MDRO
If patient has an active infection, consult physician to determine if they wish to reschedule procedure
It is not necessary to schedule patients with MDROs as the last case of the day 54<br>
55
Triage of Patients Reception room staff should be trained to be alert to patients presenting with symptoms of infections
Clinical staff will be notified of their observation so the patient can be placed into a designed exam room or room with a closable door until examined further 55<br>
Clinical staff will be notified of their observation so the patient can be placed into a designed exam room or room with a closable door until examined further 55<br>
56
Diseases Requiring
Airborne Isolation Masks should be given to the patient and door closed until sent home or transferred if the following diseases are suspected:
Tuberculosis (wait one hour to use room once patient has left)
Chickenpox (wait one hour to use room once patient has left)
Measles (wait two hours to use room once patient has left) 56<br>
Tuberculosis (wait one hour to use room once patient has left)
Chickenpox (wait one hour to use room once patient has left)
Measles (wait two hours to use room once patient has left) 56<br>
57
Disease Requiring Droplet Precautions If the following diseases are suspected, masks should be given to the patient and door closed until patient is sent home or transferred:
Mumps
Rubella
Bacterial Meningitis 57<br>
Mumps
Rubella
Bacterial Meningitis 57<br>
58
Communication to Receiving Facilities Be certain to communicate isolation requirements to:
Individuals transporting the patient
Receiving facilities such as hospitals, nursing homes, etc. 58<br>
Individuals transporting the patient
Receiving facilities such as hospitals, nursing homes, etc. 58<br>
59
Management of MRSA/MDRO Record MDRO on pre-surgical health history form
Communication
Identify MDRO according to your ASC policy (i.e., make notation in electronic medical record, mark MDRO on chart, mark MDRO by patient’s name on surgery whiteboard) 59<br>
Communication
Identify MDRO according to your ASC policy (i.e., make notation in electronic medical record, mark MDRO on chart, mark MDRO by patient’s name on surgery whiteboard) 59<br>
60
MRSA/MDRO Use Standard Precautions being certain to use gloves and gowns for contact with:
Uncontrolled secretions
Pressure ulcers
Draining wounds
Stool incontinence
Ostomy tubes and bags
If possible, consider private room or spatial separation of patients with potentially active MDROs 60<br>
Uncontrolled secretions
Pressure ulcers
Draining wounds
Stool incontinence
Ostomy tubes and bags
If possible, consider private room or spatial separation of patients with potentially active MDROs 60<br>
61
Disinfection for MDROs Shared patient equipment and surfaces (gurney, BP cuffs, oximeters) should be cleaned and disinfected with an approved EPA registered disinfectant agent before reuse
Note: a hypochlorite based germicidal agent should be used to disinfect items used by incontinent patients with known or suspected C. difficile infections 61<br>
Note: a hypochlorite based germicidal agent should be used to disinfect items used by incontinent patients with known or suspected C. difficile infections 61<br>
62
Monitor Lab Results Cultures should be monitored pre- and post- procedure
If MDROs are identified, notify the physician as well as the referring or receiving facilities 62<br>
If MDROs are identified, notify the physician as well as the referring or receiving facilities 62<br>
63
Patient and Family Education Patients and families should receive educational materials about their MDRO and control measures to follow when they are home 63<br>
64
Toolkit Contents Management of Patients with Transmissible Diseases (Isolation) Policy (2.06)
Web links to:
CDC isolation guidelines, including an alphabetized, disease-specific grid listing the required isolation category
Information on donning and removing PPE for isolation
Patient and family educational materials for MDROs 64<br>
Web links to:
CDC isolation guidelines, including an alphabetized, disease-specific grid listing the required isolation category
Information on donning and removing PPE for isolation
Patient and family educational materials for MDROs 64<br>
65
Respiratory Hygiene/
Cough Etiquette Policy Component of Standard Precautions
Prevents the transmission of respiratory infections such as influenza
Implement at first point of contact (i.e., waiting room)
Post visual alerts at ASC entrances and in waiting rooms 65<br>
Prevents the transmission of respiratory infections such as influenza
Implement at first point of contact (i.e., waiting room)
Post visual alerts at ASC entrances and in waiting rooms 65<br>
66
Respiratory Hygiene/
Cough Etiquette (cont.) Cover nose/mouth when coughing or sneezing
Tissues to contain secretions; dispose of tissues in receptacles
Perform hand hygiene
ASCs should provide tissue, hand sanitizer, masks, and receptacles at reception desk and in waiting area 66<br>
Tissues to contain secretions; dispose of tissues in receptacles
Perform hand hygiene
ASCs should provide tissue, hand sanitizer, masks, and receptacles at reception desk and in waiting area 66<br>
67
Enhanced Respiratory Etiquette Offer masks to those coughing during periods of increased respiratory infections in the community (e.g., flu season)
Healthcare professionals should wear a mask with eye protection for close contact if examining a patient with cough or fever 67<br>
Healthcare professionals should wear a mask with eye protection for close contact if examining a patient with cough or fever 67<br>
68
ASC Respiratory Etiquette 68<br>
69
Toolkit Contents Respiratory Hygiene/Cough Etiquette Policy (2.02)
Web links to:
Downloadable and printable Visual Alerts (i.e., posters) from the CDC to post in your ASC 69<br>
Web links to:
Downloadable and printable Visual Alerts (i.e., posters) from the CDC to post in your ASC 69<br>
70
Reporting Infections in Oregon The Oregon Health Authority requires health care facilities to report certain diseases
Reports should be made to the patient’s local health department
ASCs should keep a list of reportable diseases and documentation of cases they have reported (e.g., patient name, disease, date, name of county health department notified) 70<br>
Reports should be made to the patient’s local health department
ASCs should keep a list of reportable diseases and documentation of cases they have reported (e.g., patient name, disease, date, name of county health department notified) 70<br>
71
Toolkit Contents Reportable Infections Policy and Procedure (2.08)
Web links to:
List of diseases required to be reported in Oregon and required reporting time intervals
Contact information for all of Oregon’s County Health Departments 71<br>
Web links to:
List of diseases required to be reported in Oregon and required reporting time intervals
Contact information for all of Oregon’s County Health Departments 71<br>
72
72<br>