
Generating Non Surgical Income John R. Corsetti,


















































Description: Generating Non Surgical Income John R. Corsetti, M.D. New England Orthopedic Surgeons Springfield, MA Disclosure I have nothing to disclose Goals of Presentation Convey the importance of creating ancillary streams of revenue Outline the
Related Topics
Download Presentation
"Generating Non Surgical Income John R. Corsetti," is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Generating Non Surgical Income John R. Corsetti, M.D.
New England Orthopedic Surgeons
Springfield, MA<br>
slide2. Disclosure I have nothing to disclose<br>
slide3. Goals of Presentation Convey the importance of creating ancillary streams of revenue
Outline the most commonly used ancillary lines
Raise awareness that not all ancillaries work in all practices
Use 4 common ancillaries to demonstrate the process
Heighten awareness that private practice viability is increasingly dependent on ancillary revenue streams.
Take Home: Ancillary revenue is vital to the success of orthopedic surgery practices today, but planning and execution must be done precisely, or a potentially long term negative cash flow situation can be created.<br>
slide4. 4 Ancillaries to Discuss Physician Assistants/Extenders Personnel, group based
Ambulatory Surgery Center Hospital JV v. Group
Medical Legal Individual
Physical Therapy Service, group based<br>
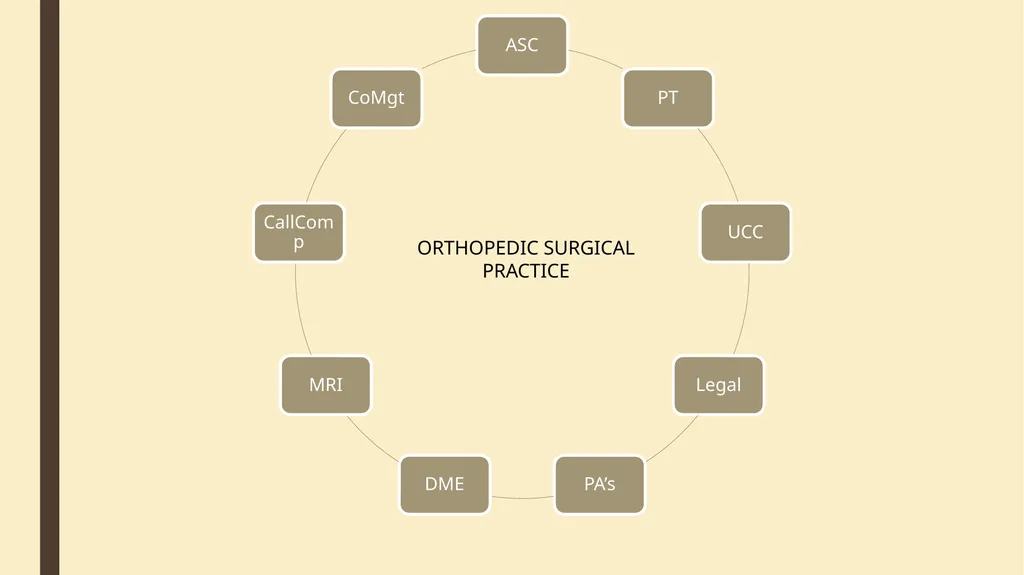
slide5. Decisions, decisions…… Physical Therapy
Surgery Center (ASC)
DME
Co-management Agreement
Urgent Care Center
On Call Compensation
Physician “Extenders”
Medical Legal
MRI/Ultrasound<br>
slide6. ORTHOPEDIC SURGICAL PRACTICE<br>
slide7. Ancillary Revenue Lines Separate businesses from orthopedic surgical practice, about which you know very little as a physician.
Ancillary must meet need for highest quality, uncompromised patient care FIRST
Theory: Physician managed patient care is, in general, better run, more efficient, more profitable, and is associated with better patient satisfaction and perhaps outcomes than large organization managed patient care.<br>
slide8. What is Ancillary Revenue Money earned by the creation of lines of business outside of the core practice of orthopedic surgery, defined as the billing for services provided by a physician for patient care provided in either the office or operating room settings.<br>
slide9. Passive v. Active Income Doctors are “piece workers”
Time is limited, and efficiencies can only be pushed so far
Active Income: revenue generated by the active participation of a physician. Is limited by hours worked and efficiencies of workplace
Passive Income: revenue that does not require the “active” involvement of the beneficiary, from activities that are outside of the “core” purpose of the beneficiary.
Independent of hours worked, patients seen, surgeries done<br>
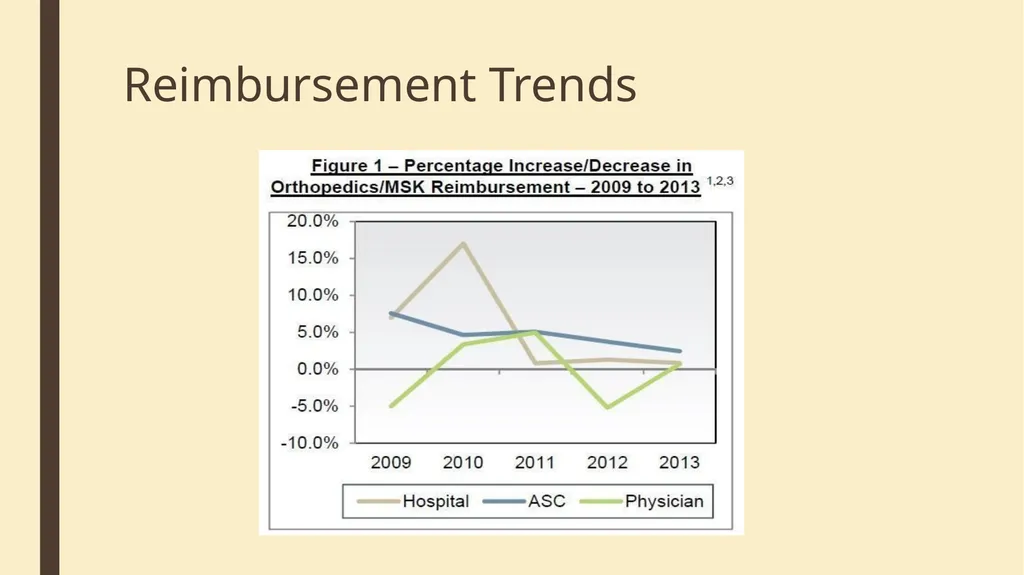
slide10. The “Death and Taxes” of Medicine Reimbursements Decrease $$
while
Overhead Increases $$<br>
slide11. Why is Ancillary Revenue Important? Form of “income diversification”
Hedge against the vagaries of reimbursement
Income is potentially scalable (“proportional growth”)
Recruitment and retention of high quality doctors
Insulation from inevitable production variability (group and individual)
Allows for physician control of patient care<br>
slide12. Ancillary Revenue Trend 1995 5% of total income
2015 40% of total income
Note: employed physician (v. private practice) model is rapidly growing.<br>
slide13. Reimbursement Trends<br>
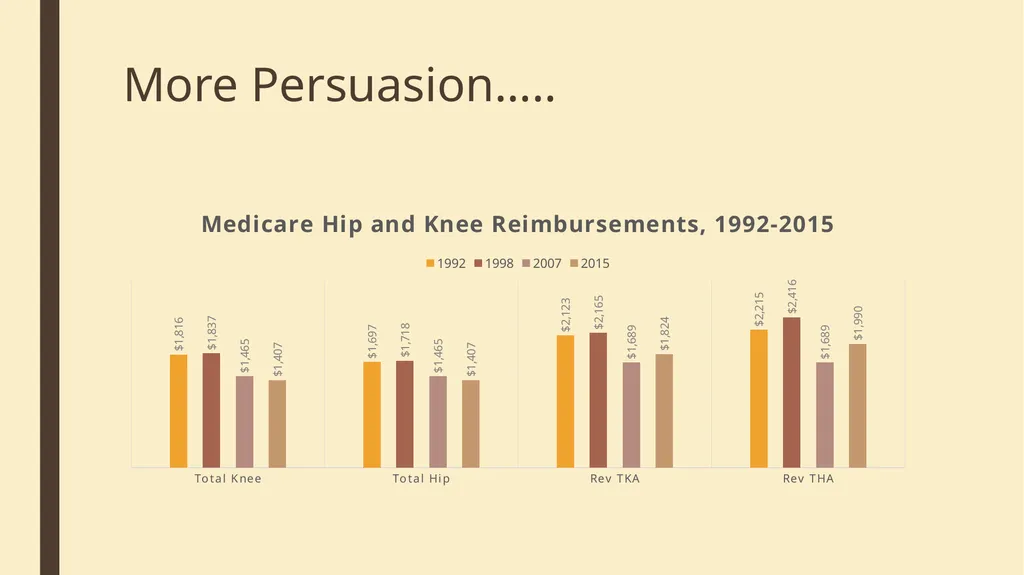
slide14. More Persuasion…..<br>
slide15. What About Inflation? Adjusted for the CPI, TKA and THA reimbursement dropped 44% from 1992-2007
From 2007 until the present, reimbursement is roughly flat, ignoring the CPI!! With the CPI that’s roughly another 20% reduction.
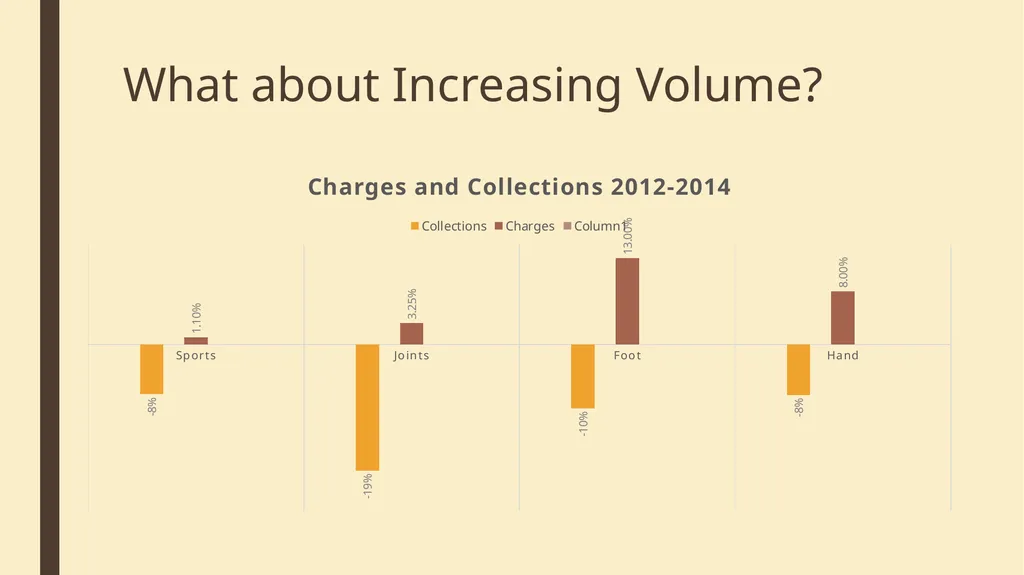
Conclusion: Efficiency and increased volume cannot maintain income against declining reimbursement and rising costs.<br>
slide16. What about Increasing Volume?<br>
slide17. Adding Ancillary Services Adding a new business line, about which you may know nothing…..
Plan carefully…..
Be humble….learn, look around, ask questions
Mistakes can be costly and irreversible
Errors can damage group culture, take years to resolve
So, how do we avoid errors…….<br>
slide18. Due Diligence “A comprehensive appraisal of a business undertaken by a prospective buyer, especially to establish its assets and liabilities and evaluate its commercial potential.”
Costs, revenue, operational, legal/regulatory<br>
slide19. Elements of Due Diligence Equipment alternatives and financing options
All start up costs
Careful volume projections…..assess upward and downward scalability
Assess reimbursement, including potential changes over time
Analyze operational issues
Detailed legal/regulatory analysis
Opportunity cost analysis (often forgotten!)
Effect on Relationships/Balance of Power<br>
slide20. The Medical Community as an Ecosystem Many entities coexist:
The Hospital
Radiologists
Physical Therapists
Brace shops
Critical to carefully analyze how your ancillary service will alter the “medical ecosystem”, and how the resultant changes in the ecosystem will effect your practice.
“Pigs get slaughtered”<br>
slide21. Stark and Anti-Kickback Laws Stark: prohibits physician referrals of designated health services for Medicare and Medicaid patients if the physician has a financial relationship with the entity. Exceptions exist, one is ASC.
Civil penalties for violation
Anti Kickback: prohibits the “knowing and willful solicitation, receipt, offer, or payment of any remuneration….to any person in return for referring or inducing to refer an individual to a person for the furnishing…of any item or service for which payment will be made…..”
ASC “safe harbor”
Can’t get paid for referrals
Criminal penalties for violation<br>
slide22. Buy In for Ancillaries Separate business line, so some “cost of entry” is appropriate.
Ballpark 1-2x yearly profit/partner is fair.
Buy in can be dollars or time.
Often limited negotiability as prior hires have set precedent
Remember that a “bad deal” can become a “good deal” for the remainder of your career!!!<br>
slide23. No Ancillary Revenue? Income entirely dependent on the vagaries of reimbursement for work units
No way to maintain income except increasing volume
Personal Opinion: I would question the long term financial viability of a private group without ancillary streams of revenue.<br>
slide24. Ancillary #1: Physician Extenders Physician assistants, nurse practitioners, non operative physicians
PA expected growth rate of 40% from 2012-2020
Ortho, family medicine and ER medicine most PA demand
Options for Structure
1 physician-1 PA
Specialty Specific
Practice Float<br>
slide25. Physician Assistants in Orthopedic Practice Primary goal: to improve practice efficiency by increasing both nonoperative and operative volume, while maintaining quality of care and patient satisfaction
Patients should perceive the PA as an integrated part of the care team, rather than independent of the treating physician.
In some demographics, PA’s can develop their own patient following, independent of a particular physician.<br>
slide26. Physician Assistants: Revenue Increase revenue by
Direct billing and collection for services (new and rechecks, globals)
Surgical bookings
Providing nonoperative orthopedic care
Increasing operating room volume/efficiency
Increase utilization of fixed overhead while surgeon operates
Are PA’s part of “Overhead”?
In an efficient model, a PA with total comp X can bring in 3-4X in collections<br>
slide27. Physician Assistants…Pitfalls and Considerations Is there a backlog of patients, or will PA cannibalize physician schedules?
Can PA’s be trained at a high enough level to allow for independent practice?
Intra-practice cultural problems from disparate compensation.
PA remuneration: “pay for volume” can lead to poor quality
Practice needs to create model for revenue distribution
Need clear guidelines for scope of practice, protocols for management, etc. Supervision and close physician relationships are key.<br>
slide28. PA Hiring…Due Diligence Example Costs of recruiting, support staff, space, CME, salary, phone, benefits, etc.
Evaluate patient demand, increased surgical volume, ?build in decrease in physician revenue, training/ramp up period
Understand your referral pattern and demographic, MAY NOT work in your area
Ancillary referral revenue (brace, PT, MRI, etc)
Evaluate specific payor mix (that applies to PA) to generate revenue model
Build worse case, best case and likely case scenarios<br>
slide29. Non Surgical Physicians Physiatrists, Non-operative Orthopedists/Podiatrists, Rheumatologist, Sports trained Internist
“Expensive” physician assistant versus practice asset
Same advantages as PA….allow surgeons to practice at “top of license”
? Better patient satisfaction than PA
Manage non operative problems to discharge
“Name recognition” of recent retirees, can be a draw
Physiatrists can fill an ASC, feed spine surgeon
Same due diligence analysis<br>
slide30. Non Surgical Physicians Generally not “partnered”, will generate lower revenue
Create reimbursement formula, generally related to production
Effective use of fixed overhead….real estate and personnel
Surgeons use office space only 50-75% of time
Only “Win-Win” business arrangements are durable<br>
slide31. Ancillary #2: Ambulatory Surgery Center Best friend or worst enemy
1/3 profitable, 1/3 not profitable, 1/3 “who cares”
Meticulous planning and execution essential
NOT a “no brainer”
Big money proposition……can take down a group if done poorly<br>
slide32. Our Story…… 10 surgeon group (2001), 6 ASC surgeons (sports, hand, foot)
High volume surgical practice with growth potential
No competitive groups in the area
Outpt ASC at main hospital, but multispecialty, +/- efficiency
No Brainer……right????<br>
slide33. Our Story….. Analysis
Payor mix….2 major insurers, one hospital owned
High proportion of govt insured in area
Excellent relationship with hospital management
Wanted and needed a scalable facility, big dollar proposition
Concerns
Pro Forma…..profitable, but not wildly so
Erode hospital relationships, create competitive environment
Split facilities….introduce inefficiencies
Concerned about reimbursement decline over time<br>
slide34. Our Story….. Approach
Cooperative discussions with hospital to pursue JV
Recruitment and retention argument
Worked to create a classic “win-win”
Outcome
Took over an underproducing hospital owned 4 room ASC
Brought it to 4000 cases/year
Built an 8 room facility, Ortho only
Negotiated management agreement<br>
slide35. The Result……<br>
slide36. Lessons learned….. Physician owned ASC is not always the best option
Specifics of your demographic, hospital relations, payor mix, regulatory environment, etc. must be carefully analyzed
Detailed, realistic 8 year pro forma must be constructed…..May need consultant to do it right!
Cooperative deal with the hospital set stage for further deals (ER coverage, Trauma Program, 2 OR rooms for Joint Program)
Had we chosen to compete with hospital……..???<br>
slide37. ASC Considerations Physician Owned v. Joint Venture
Planning: done with 3rd party consultant or hospital team.
Physician Owned Centers:
Create competitive environment with hospital
Require large capital outlay, all risk assumed by investors
Even if the expertise exists, what about the time to manage??
Can create intra-group conflict…income distribution, device use, other issues
Declining reimbursement can be a major threat in narrow margin markets
But: most control, highest potential profit<br>
slide38. ASC Joint Venture Model Enhances hospital relationship….other deals to be done
Co-management, trauma, inpt coverage
Spreads risk
Use hospital resources for management
Deep pockets…..can build a more robust, scalable center
Regulatory Environment can be overwhelming without deep pocket backing<br>
slide39. ASC—Working with the Hospital Hospitals and orthopedic groups have aligned goals:
High volume, efficient, profitable center providing high level patient care with excellent patient satisfaction
Creation of a win-win, in which both parties feel successful in the negotiation, is the goal.<br>
slide40. ASC….Summary Myriad of ownership structures available
Outside consultant advisable
Compete v. cooperate
Understand risk and manage it carefully
No such thing as a “no brainer”<br>
slide41. Ancillary #3: Medical Legal/Forensic Medicine Black Box, “underbelly of medicine”
We have no training or expertise, fish out of water
Different language, set of rules, goals
Conflict resolution not patient care
Hostile, adversarial environment filled with lawyers trying to make you look bad rather than seeking truth
So, why do it???<br>
slide42. Medical-legal practice…Why do it? Intellectually challenging
Makes you a better doctor
Develop a new skill set that can be useful
- always good to feel comfortable in a courtroom
Hedge against reimbursement declines, totally “market based”, scalable
Impossible to avoid having to render opinions to legal entities
Revenue is not W2, and can be saved in retirement vehicles pre tax (SEP-IRA, DB)<br>
slide43. Medical-legal Independent Medical Exams (IME’s)
Disability Ratings
Med Mal (defense v. plaintiff)
Personal Injury evaluations (defense v. plaintiff)
Any matter in which someone will pay you to render a forensic opinion<br>
slide44. Medical-legal AAOS Standards of Professionalism
http://www3.aaos.org/member/profcomp/ewtestimony_May_2010.pdf
Guidelines regarding
Subject matter knowledge
Qualifications
Compensation<br>
slide45. Medical Legal… Developing a Referral Base Takes 3-5 years to cultivate
Personal Injury law firms are excellent client source
IME “clearing houses”
Insurance companies
Courses exist to train in both being an expert witness and developing a business
Word-of-mouth is the best advertisement<br>
slide46. What Do I Charge? Annual practice income/2000 hours = hourly rate (starting point)
Analyze the market:
What are other doctors charging?
Experience counts
True “Market”: supply/demand, quality costs more (foreign concepts to doctors!)
Group needs to decide how this revenue is treated, can be tricky<br>
slide47. How do I learn? Quality should be paramount….do this like everything else, with the utmost rigor and attention to detail.
Academy or privately run courses exist and are recommended
American Board of Independent Medical Examiners
Certified Independent Medical Examiner (fairly uncommon)<br>
slide48. Medical-legal Individual v. Practice based
Nights/weekends/off hours v. work day
Paid by 1099, not W2
Allows you to set up a separate retirement account pre tax
Can be a game changer<br>
slide49. Analysis Costs
Opportunity cost (time, life)
Time away from patient care, transcription costs
Revenue
Hours per week x hourly rate
Operational
Staff to organize/schedule, billing
Regulatory
Academy guidelines, words are forever!<br>
slide50. Ancillary #4: Physical Therapy Practice associated physical therapy improves quality of care
Major patient and physician satisfier
“One stop shop”, coordination of care<br>
slide51. Physical Therapy, Due Diligence Costs:
Space, therapists, support staff, equipment, build out, finance how
Opportunity cost of space
Revenue
How many patients will be seen, payment per visit expected
Ramp up period to cash flow positive
Do all payors allow patients to use your PT?
Effect of declining reimbursements, high deductible plans Operational/Regulatory
Legal opinion on Stark
Effect on hospital relationship
Effect on referral sources
Legislative issues
Other
How to divide profit<br>
slide52. Physical Therapy Lots to consider for this “relatively simple” ancillary
Like anything, it can be done poorly or well
Generally one of the most profitable, and best physician and patient satisfiers
Profitable doesn’t mean optimized<br>
slide53. Ancillary Revenue in Orthopedic Surgical Practices Necessary and growing revenue stream for private practices
Essential for recruitment and retention
Separate business lines that need rigorous due diligence and execution to succeed
Opportunity for cooperative engagement with the hospital
Profitable does not always equate to optimized
Humility is key! Don’t be afraid of consultants.<br>
slide54. Thank You!<br>
New England Orthopedic Surgeons
Springfield, MA<br>
slide2. Disclosure I have nothing to disclose<br>
slide3. Goals of Presentation Convey the importance of creating ancillary streams of revenue
Outline the most commonly used ancillary lines
Raise awareness that not all ancillaries work in all practices
Use 4 common ancillaries to demonstrate the process
Heighten awareness that private practice viability is increasingly dependent on ancillary revenue streams.
Take Home: Ancillary revenue is vital to the success of orthopedic surgery practices today, but planning and execution must be done precisely, or a potentially long term negative cash flow situation can be created.<br>
slide4. 4 Ancillaries to Discuss Physician Assistants/Extenders Personnel, group based
Ambulatory Surgery Center Hospital JV v. Group
Medical Legal Individual
Physical Therapy Service, group based<br>
slide5. Decisions, decisions…… Physical Therapy
Surgery Center (ASC)
DME
Co-management Agreement
Urgent Care Center
On Call Compensation
Physician “Extenders”
Medical Legal
MRI/Ultrasound<br>
slide6. ORTHOPEDIC SURGICAL PRACTICE<br>
slide7. Ancillary Revenue Lines Separate businesses from orthopedic surgical practice, about which you know very little as a physician.
Ancillary must meet need for highest quality, uncompromised patient care FIRST
Theory: Physician managed patient care is, in general, better run, more efficient, more profitable, and is associated with better patient satisfaction and perhaps outcomes than large organization managed patient care.<br>
slide8. What is Ancillary Revenue Money earned by the creation of lines of business outside of the core practice of orthopedic surgery, defined as the billing for services provided by a physician for patient care provided in either the office or operating room settings.<br>
slide9. Passive v. Active Income Doctors are “piece workers”
Time is limited, and efficiencies can only be pushed so far
Active Income: revenue generated by the active participation of a physician. Is limited by hours worked and efficiencies of workplace
Passive Income: revenue that does not require the “active” involvement of the beneficiary, from activities that are outside of the “core” purpose of the beneficiary.
Independent of hours worked, patients seen, surgeries done<br>
slide10. The “Death and Taxes” of Medicine Reimbursements Decrease $$
while
Overhead Increases $$<br>
slide11. Why is Ancillary Revenue Important? Form of “income diversification”
Hedge against the vagaries of reimbursement
Income is potentially scalable (“proportional growth”)
Recruitment and retention of high quality doctors
Insulation from inevitable production variability (group and individual)
Allows for physician control of patient care<br>
slide12. Ancillary Revenue Trend 1995 5% of total income
2015 40% of total income
Note: employed physician (v. private practice) model is rapidly growing.<br>
slide13. Reimbursement Trends<br>
slide14. More Persuasion…..<br>
slide15. What About Inflation? Adjusted for the CPI, TKA and THA reimbursement dropped 44% from 1992-2007
From 2007 until the present, reimbursement is roughly flat, ignoring the CPI!! With the CPI that’s roughly another 20% reduction.
Conclusion: Efficiency and increased volume cannot maintain income against declining reimbursement and rising costs.<br>
slide16. What about Increasing Volume?<br>
slide17. Adding Ancillary Services Adding a new business line, about which you may know nothing…..
Plan carefully…..
Be humble….learn, look around, ask questions
Mistakes can be costly and irreversible
Errors can damage group culture, take years to resolve
So, how do we avoid errors…….<br>
slide18. Due Diligence “A comprehensive appraisal of a business undertaken by a prospective buyer, especially to establish its assets and liabilities and evaluate its commercial potential.”
Costs, revenue, operational, legal/regulatory<br>
slide19. Elements of Due Diligence Equipment alternatives and financing options
All start up costs
Careful volume projections…..assess upward and downward scalability
Assess reimbursement, including potential changes over time
Analyze operational issues
Detailed legal/regulatory analysis
Opportunity cost analysis (often forgotten!)
Effect on Relationships/Balance of Power<br>
slide20. The Medical Community as an Ecosystem Many entities coexist:
The Hospital
Radiologists
Physical Therapists
Brace shops
Critical to carefully analyze how your ancillary service will alter the “medical ecosystem”, and how the resultant changes in the ecosystem will effect your practice.
“Pigs get slaughtered”<br>
slide21. Stark and Anti-Kickback Laws Stark: prohibits physician referrals of designated health services for Medicare and Medicaid patients if the physician has a financial relationship with the entity. Exceptions exist, one is ASC.
Civil penalties for violation
Anti Kickback: prohibits the “knowing and willful solicitation, receipt, offer, or payment of any remuneration….to any person in return for referring or inducing to refer an individual to a person for the furnishing…of any item or service for which payment will be made…..”
ASC “safe harbor”
Can’t get paid for referrals
Criminal penalties for violation<br>
slide22. Buy In for Ancillaries Separate business line, so some “cost of entry” is appropriate.
Ballpark 1-2x yearly profit/partner is fair.
Buy in can be dollars or time.
Often limited negotiability as prior hires have set precedent
Remember that a “bad deal” can become a “good deal” for the remainder of your career!!!<br>
slide23. No Ancillary Revenue? Income entirely dependent on the vagaries of reimbursement for work units
No way to maintain income except increasing volume
Personal Opinion: I would question the long term financial viability of a private group without ancillary streams of revenue.<br>
slide24. Ancillary #1: Physician Extenders Physician assistants, nurse practitioners, non operative physicians
PA expected growth rate of 40% from 2012-2020
Ortho, family medicine and ER medicine most PA demand
Options for Structure
1 physician-1 PA
Specialty Specific
Practice Float<br>
slide25. Physician Assistants in Orthopedic Practice Primary goal: to improve practice efficiency by increasing both nonoperative and operative volume, while maintaining quality of care and patient satisfaction
Patients should perceive the PA as an integrated part of the care team, rather than independent of the treating physician.
In some demographics, PA’s can develop their own patient following, independent of a particular physician.<br>
slide26. Physician Assistants: Revenue Increase revenue by
Direct billing and collection for services (new and rechecks, globals)
Surgical bookings
Providing nonoperative orthopedic care
Increasing operating room volume/efficiency
Increase utilization of fixed overhead while surgeon operates
Are PA’s part of “Overhead”?
In an efficient model, a PA with total comp X can bring in 3-4X in collections<br>
slide27. Physician Assistants…Pitfalls and Considerations Is there a backlog of patients, or will PA cannibalize physician schedules?
Can PA’s be trained at a high enough level to allow for independent practice?
Intra-practice cultural problems from disparate compensation.
PA remuneration: “pay for volume” can lead to poor quality
Practice needs to create model for revenue distribution
Need clear guidelines for scope of practice, protocols for management, etc. Supervision and close physician relationships are key.<br>
slide28. PA Hiring…Due Diligence Example Costs of recruiting, support staff, space, CME, salary, phone, benefits, etc.
Evaluate patient demand, increased surgical volume, ?build in decrease in physician revenue, training/ramp up period
Understand your referral pattern and demographic, MAY NOT work in your area
Ancillary referral revenue (brace, PT, MRI, etc)
Evaluate specific payor mix (that applies to PA) to generate revenue model
Build worse case, best case and likely case scenarios<br>
slide29. Non Surgical Physicians Physiatrists, Non-operative Orthopedists/Podiatrists, Rheumatologist, Sports trained Internist
“Expensive” physician assistant versus practice asset
Same advantages as PA….allow surgeons to practice at “top of license”
? Better patient satisfaction than PA
Manage non operative problems to discharge
“Name recognition” of recent retirees, can be a draw
Physiatrists can fill an ASC, feed spine surgeon
Same due diligence analysis<br>
slide30. Non Surgical Physicians Generally not “partnered”, will generate lower revenue
Create reimbursement formula, generally related to production
Effective use of fixed overhead….real estate and personnel
Surgeons use office space only 50-75% of time
Only “Win-Win” business arrangements are durable<br>
slide31. Ancillary #2: Ambulatory Surgery Center Best friend or worst enemy
1/3 profitable, 1/3 not profitable, 1/3 “who cares”
Meticulous planning and execution essential
NOT a “no brainer”
Big money proposition……can take down a group if done poorly<br>
slide32. Our Story…… 10 surgeon group (2001), 6 ASC surgeons (sports, hand, foot)
High volume surgical practice with growth potential
No competitive groups in the area
Outpt ASC at main hospital, but multispecialty, +/- efficiency
No Brainer……right????<br>
slide33. Our Story….. Analysis
Payor mix….2 major insurers, one hospital owned
High proportion of govt insured in area
Excellent relationship with hospital management
Wanted and needed a scalable facility, big dollar proposition
Concerns
Pro Forma…..profitable, but not wildly so
Erode hospital relationships, create competitive environment
Split facilities….introduce inefficiencies
Concerned about reimbursement decline over time<br>
slide34. Our Story….. Approach
Cooperative discussions with hospital to pursue JV
Recruitment and retention argument
Worked to create a classic “win-win”
Outcome
Took over an underproducing hospital owned 4 room ASC
Brought it to 4000 cases/year
Built an 8 room facility, Ortho only
Negotiated management agreement<br>
slide35. The Result……<br>
slide36. Lessons learned….. Physician owned ASC is not always the best option
Specifics of your demographic, hospital relations, payor mix, regulatory environment, etc. must be carefully analyzed
Detailed, realistic 8 year pro forma must be constructed…..May need consultant to do it right!
Cooperative deal with the hospital set stage for further deals (ER coverage, Trauma Program, 2 OR rooms for Joint Program)
Had we chosen to compete with hospital……..???<br>
slide37. ASC Considerations Physician Owned v. Joint Venture
Planning: done with 3rd party consultant or hospital team.
Physician Owned Centers:
Create competitive environment with hospital
Require large capital outlay, all risk assumed by investors
Even if the expertise exists, what about the time to manage??
Can create intra-group conflict…income distribution, device use, other issues
Declining reimbursement can be a major threat in narrow margin markets
But: most control, highest potential profit<br>
slide38. ASC Joint Venture Model Enhances hospital relationship….other deals to be done
Co-management, trauma, inpt coverage
Spreads risk
Use hospital resources for management
Deep pockets…..can build a more robust, scalable center
Regulatory Environment can be overwhelming without deep pocket backing<br>
slide39. ASC—Working with the Hospital Hospitals and orthopedic groups have aligned goals:
High volume, efficient, profitable center providing high level patient care with excellent patient satisfaction
Creation of a win-win, in which both parties feel successful in the negotiation, is the goal.<br>
slide40. ASC….Summary Myriad of ownership structures available
Outside consultant advisable
Compete v. cooperate
Understand risk and manage it carefully
No such thing as a “no brainer”<br>
slide41. Ancillary #3: Medical Legal/Forensic Medicine Black Box, “underbelly of medicine”
We have no training or expertise, fish out of water
Different language, set of rules, goals
Conflict resolution not patient care
Hostile, adversarial environment filled with lawyers trying to make you look bad rather than seeking truth
So, why do it???<br>
slide42. Medical-legal practice…Why do it? Intellectually challenging
Makes you a better doctor
Develop a new skill set that can be useful
- always good to feel comfortable in a courtroom
Hedge against reimbursement declines, totally “market based”, scalable
Impossible to avoid having to render opinions to legal entities
Revenue is not W2, and can be saved in retirement vehicles pre tax (SEP-IRA, DB)<br>
slide43. Medical-legal Independent Medical Exams (IME’s)
Disability Ratings
Med Mal (defense v. plaintiff)
Personal Injury evaluations (defense v. plaintiff)
Any matter in which someone will pay you to render a forensic opinion<br>
slide44. Medical-legal AAOS Standards of Professionalism
http://www3.aaos.org/member/profcomp/ewtestimony_May_2010.pdf
Guidelines regarding
Subject matter knowledge
Qualifications
Compensation<br>
slide45. Medical Legal… Developing a Referral Base Takes 3-5 years to cultivate
Personal Injury law firms are excellent client source
IME “clearing houses”
Insurance companies
Courses exist to train in both being an expert witness and developing a business
Word-of-mouth is the best advertisement<br>
slide46. What Do I Charge? Annual practice income/2000 hours = hourly rate (starting point)
Analyze the market:
What are other doctors charging?
Experience counts
True “Market”: supply/demand, quality costs more (foreign concepts to doctors!)
Group needs to decide how this revenue is treated, can be tricky<br>
slide47. How do I learn? Quality should be paramount….do this like everything else, with the utmost rigor and attention to detail.
Academy or privately run courses exist and are recommended
American Board of Independent Medical Examiners
Certified Independent Medical Examiner (fairly uncommon)<br>
slide48. Medical-legal Individual v. Practice based
Nights/weekends/off hours v. work day
Paid by 1099, not W2
Allows you to set up a separate retirement account pre tax
Can be a game changer<br>
slide49. Analysis Costs
Opportunity cost (time, life)
Time away from patient care, transcription costs
Revenue
Hours per week x hourly rate
Operational
Staff to organize/schedule, billing
Regulatory
Academy guidelines, words are forever!<br>
slide50. Ancillary #4: Physical Therapy Practice associated physical therapy improves quality of care
Major patient and physician satisfier
“One stop shop”, coordination of care<br>
slide51. Physical Therapy, Due Diligence Costs:
Space, therapists, support staff, equipment, build out, finance how
Opportunity cost of space
Revenue
How many patients will be seen, payment per visit expected
Ramp up period to cash flow positive
Do all payors allow patients to use your PT?
Effect of declining reimbursements, high deductible plans Operational/Regulatory
Legal opinion on Stark
Effect on hospital relationship
Effect on referral sources
Legislative issues
Other
How to divide profit<br>
slide52. Physical Therapy Lots to consider for this “relatively simple” ancillary
Like anything, it can be done poorly or well
Generally one of the most profitable, and best physician and patient satisfiers
Profitable doesn’t mean optimized<br>
slide53. Ancillary Revenue in Orthopedic Surgical Practices Necessary and growing revenue stream for private practices
Essential for recruitment and retention
Separate business lines that need rigorous due diligence and execution to succeed
Opportunity for cooperative engagement with the hospital
Profitable does not always equate to optimized
Humility is key! Don’t be afraid of consultants.<br>
slide54. Thank You!<br>