
OVERDOSE AND POISONING Karishma Domah Simon Brooks
















Description: OVERDOSE AND POISONING Karishma Domah Simon Brooks Rahul Lakman INTRODUCTION Poisoning and overdose is relatively common in our socioeconomic setting. Poison refers to a substance that is capable of causing harm or death when introduced or
Related Topics
Download Presentation
"OVERDOSE AND POISONING Karishma Domah Simon Brooks" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. OVERDOSE
AND
POISONING Karishma Domah
Simon Brooks
Rahul Lakman<br>
slide2. INTRODUCTION Poisoning and overdose is relatively common in our socioeconomic setting.
Poison refers to a substance that is capable of causing harm or death when introduced or absorbed by the body.
Overdose refers to the consumption or administration of a quantity of drug, in excess of the prescribed or usual dose.
Both of which can be deliberate or accidental.
Poisoning and overdose are grouped into Toxidromes.
These are defined by the mental state, vital sign trends as well as other physical signs.<br>
slide3. Contents General approach to overdose and poisoning
When to suspect poisoning
Toxidromes
Paracetamol
INH Poisoning
Warfarin poisoning
Snake bites Cholinergics
Anticholinergics
Serotonin syndrome
Opioids
Sympathomimetics
Sedatives
Hallucinogens
Salicylates
Ethanol<br>
slide4. GENERAL APPROACH TO OVERDOSE AND POISONING (RRSI DEAD) RESUSCITATION
Airway
Breathing
Circuation
Hypertension
Hypotension
Arrhythmias
Disability
Seizures
Hypoglycaemia
Exposure
Hyperthermia RISK ASSESSMENT
Patient factors e.g. Comorbidities, weight
Current clinical status ( vitals, GCS)
Agent, dose, time of ingestion (history and examination) Daly, S., Little, M., & Murray, L. (2006). A risk assessment based approach to the management of acute poisoning. TOXICOLOGY: AN AUSTRALIAN PERSPECTIVE , 396-399.<br>
slide5. SUPPORTIVE CARE
Feeding/fluids
Analgesia
Sedation
Thromboprophylaxis
Head up position
Ulcer prophylaxis
Glycemic control
Spontaneous breathing trial
Bowel care
Indwelling catheter removal
Deescalation of antibiotics INVESTIGATIONS
ECG
Paracetamol levels<br>
slide6. DECONTAMINATION
Aims to reduce the absorption of ingested agent
Ingestion
Caustic vs Toxic: Duration since exposure, vomiting – activated charcoal, gastric lavage.
Dry powders
Brush off.
Liquids
Irrigation
Gasses
Ventilation ENHANCED ELIMINATION
Interventions aimed to enhance the elimination of an agent
Examples: Urine alkalinisation
Haemodialysis<br>
slide7. ANTIDOTES
Correct the effects of the poison
Side effects DISPOSITION
Initial risk assessment allows for appropriate planning of disposition<br>
slide8. When to suspect poisoning or overdose T - Temperature
O- Odour
X- Extrapyramidal signs
I- Ileus
D- Dry mouth/ excessive salivation/Delirium
R- Rashes
O- Overdose (polypharmacy)
M- muscle tone abnormalities
E- Eyes/ ECG
S-Seizures<br>
slide9. TOXIDROMES Group of abnormal vital signs and features found on examination associated with a specific group of toxin or drug.
Common types of toxidromes
Cholinergics
Anticholinergics
Serotonin syndrome
Opioids
Sympathomimetics
Sedatives
Hallucinogens
Salicylates
Ethanol<br>
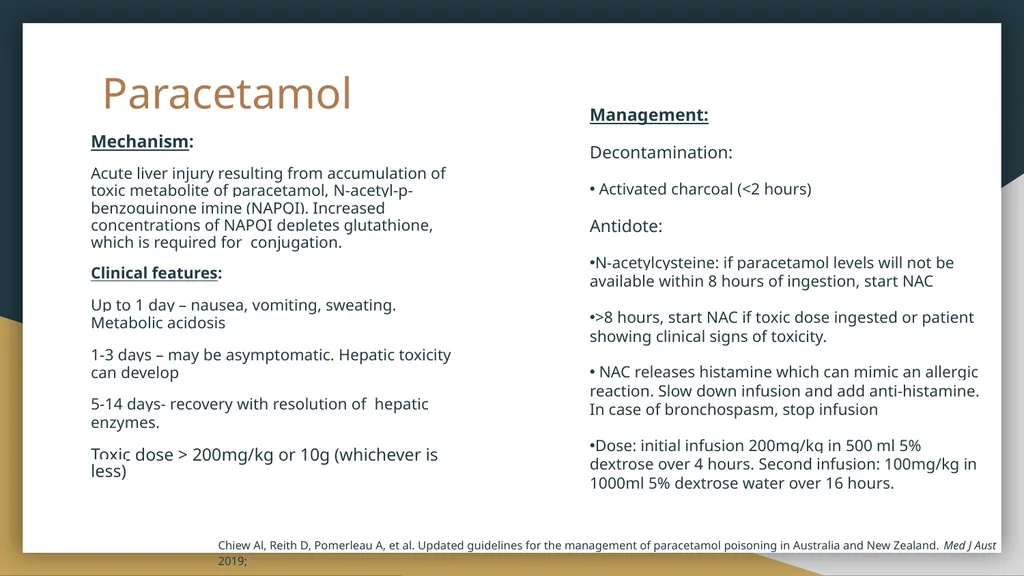
slide10. Paracetamol Mechanism:
Acute liver injury resulting from accumulation of toxic metabolite of paracetamol, N-acetyl-p-benzoquinone imine (NAPQI). Increased concentrations of NAPQI depletes glutathione, which is required for conjugation.
Clinical features:
Up to 1 day – nausea, vomiting, sweating. Metabolic acidosis
1-3 days – may be asymptomatic. Hepatic toxicity can develop
5-14 days- recovery with resolution of hepatic enzymes.
Toxic dose > 200mg/kg or 10g (whichever is less) Management:
Decontamination:
Activated charcoal (<2 hours)
Antidote:
N-acetylcysteine: if paracetamol levels will not be available within 8 hours of ingestion, start NAC
>8 hours, start NAC if toxic dose ingested or patient showing clinical signs of toxicity.
NAC releases histamine which can mimic an allergic reaction. Slow down infusion and add anti-histamine. In case of bronchospasm, stop infusion
Dose: initial infusion 200mg/kg in 500 ml 5% dextrose over 4 hours. Second infusion: 100mg/kg in 1000ml 5% dextrose water over 16 hours. Chiew Al, Reith D, Pomerleau A, et al. Updated guidelines for the management of paracetamol poisoning in Australia and New Zealand. Med J Aust 2019;<br>
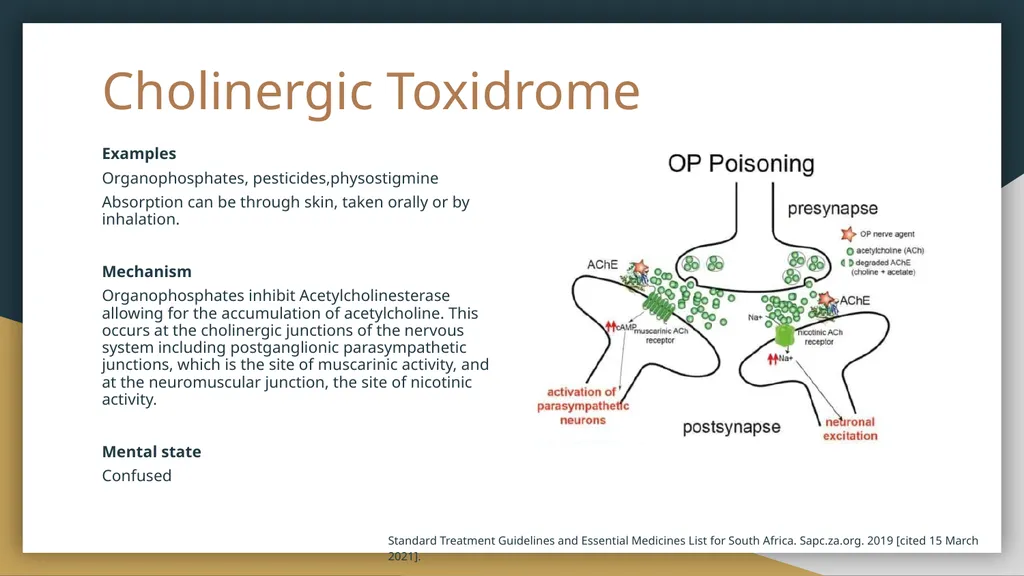
slide11. Cholinergic Toxidrome Examples
Organophosphates, pesticides,physostigmine
Absorption can be through skin, taken orally or by inhalation.
Mechanism
Organophosphates inhibit Acetylcholinesterase allowing for the accumulation of acetylcholine. This occurs at the cholinergic junctions of the nervous system including postganglionic parasympathetic junctions, which is the site of muscarinic activity, and at the neuromuscular junction, the site of nicotinic activity.
Mental state
Confused Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
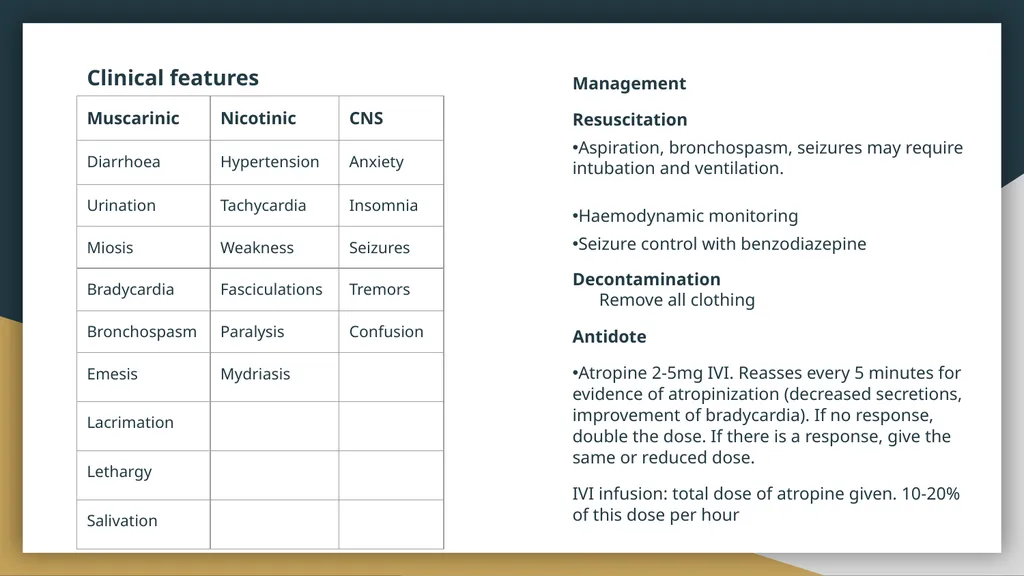
slide12. Clinical features Management
Resuscitation
Aspiration, bronchospasm, seizures may require intubation and ventilation.
Haemodynamic monitoring
Seizure control with benzodiazepine
Decontamination Remove all clothing
Antidote
Atropine 2-5mg IVI. Reasses every 5 minutes for evidence of atropinization (decreased secretions, improvement of bradycardia). If no response, double the dose. If there is a response, give the same or reduced dose.
IVI infusion: total dose of atropine given. 10-20% of this dose per hour<br>
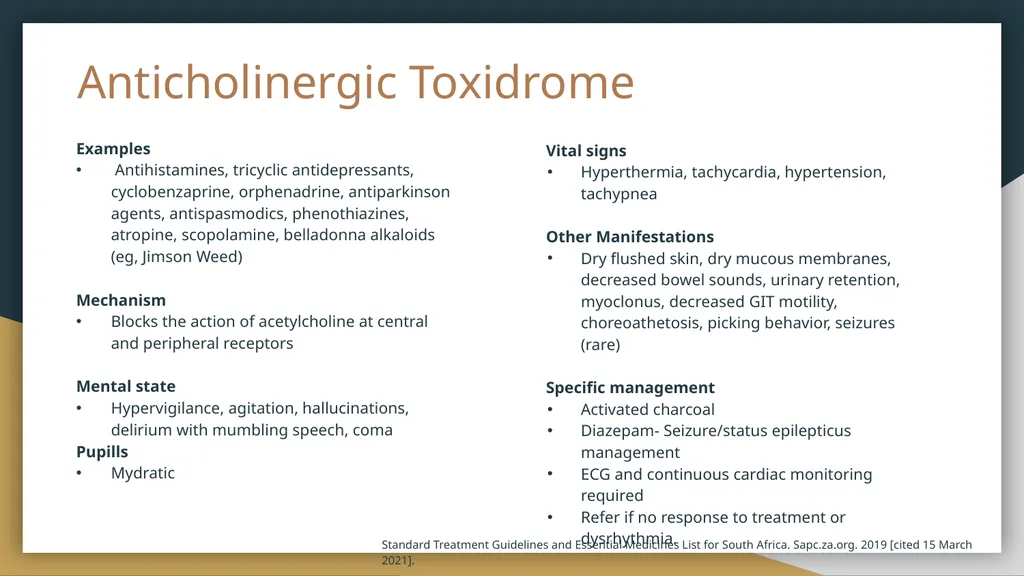
slide13. Anticholinergic Toxidrome Examples
Antihistamines, tricyclic antidepressants, cyclobenzaprine, orphenadrine, antiparkinson agents, antispasmodics, phenothiazines, atropine, scopolamine, belladonna alkaloids (eg, Jimson Weed)
Mechanism
Blocks the action of acetylcholine at central and peripheral receptors
Mental state
Hypervigilance, agitation, hallucinations, delirium with mumbling speech, coma
Pupills
Mydratic Vital signs
Hyperthermia, tachycardia, hypertension, tachypnea
Other Manifestations
Dry flushed skin, dry mucous membranes, decreased bowel sounds, urinary retention, myoclonus, decreased GIT motility, choreoathetosis, picking behavior, seizures (rare)
Specific management
Activated charcoal
Diazepam- Seizure/status epilepticus management
ECG and continuous cardiac monitoring required
Refer if no response to treatment or dysrhythmia. Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide14. Serotonin syndrome Examples:
MAOIs alone or with: SSRIs, meperidine, dextromethorphan, TCAs, L-tryptophan
Mechanism:
Activation of serotonergic receptors by either inhibition of serotonin uptake, decrease metabolism or increased synthesis of serotonin
Mental state
Confusion, agitation, coma
Pupils
Mydriasis
Vital signs
Hyperthermia, tachycardia, hypertension, tachypnea Other Manifestations
Tremor, myoclonus, hyperreflexia, clonus, diaphoresis, flushing, trismus, rigidity, diarrhea
Specific management
Supportive
Fits monitoring
Benzodiazepines as required for muscular rigidity and seizures
ECG Leikin, J., & Paloucek, F. (2008). Poisoning and Toxicology Handbook. New York: Informa Healthcare.<br>
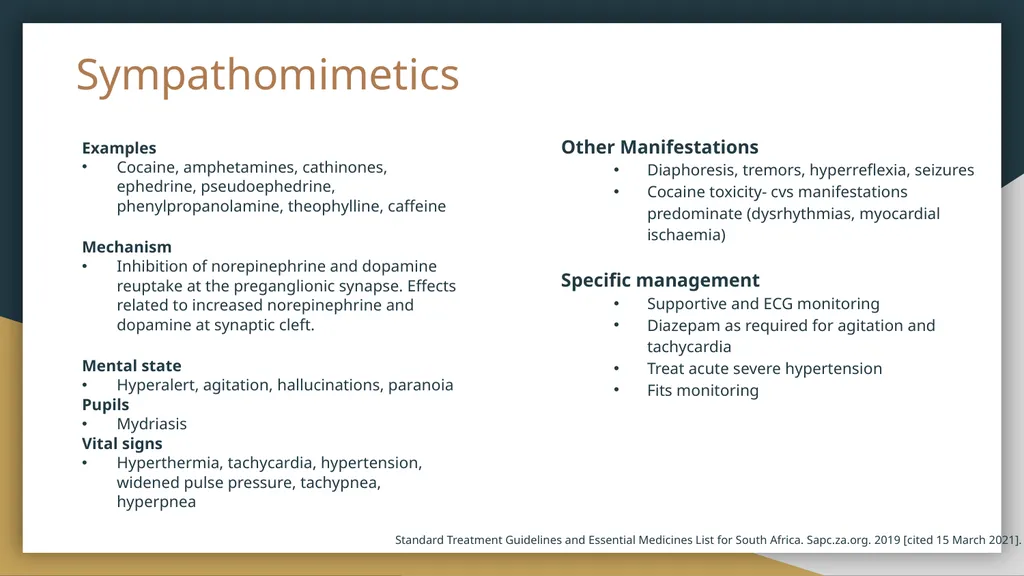
slide15. Sympathomimetics Examples
Cocaine, amphetamines, cathinones, ephedrine, pseudoephedrine, phenylpropanolamine, theophylline, caffeine
Mechanism
Inhibition of norepinephrine and dopamine reuptake at the preganglionic synapse. Effects related to increased norepinephrine and dopamine at synaptic cleft.
Mental state
Hyperalert, agitation, hallucinations, paranoia
Pupils
Mydriasis
Vital signs
Hyperthermia, tachycardia, hypertension, widened pulse pressure, tachypnea, hyperpnea Other Manifestations
Diaphoresis, tremors, hyperreflexia, seizures
Cocaine toxicity- cvs manifestations predominate (dysrhythmias, myocardial ischaemia)
Specific management
Supportive and ECG monitoring
Diazepam as required for agitation and tachycardia
Treat acute severe hypertension
Fits monitoring Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
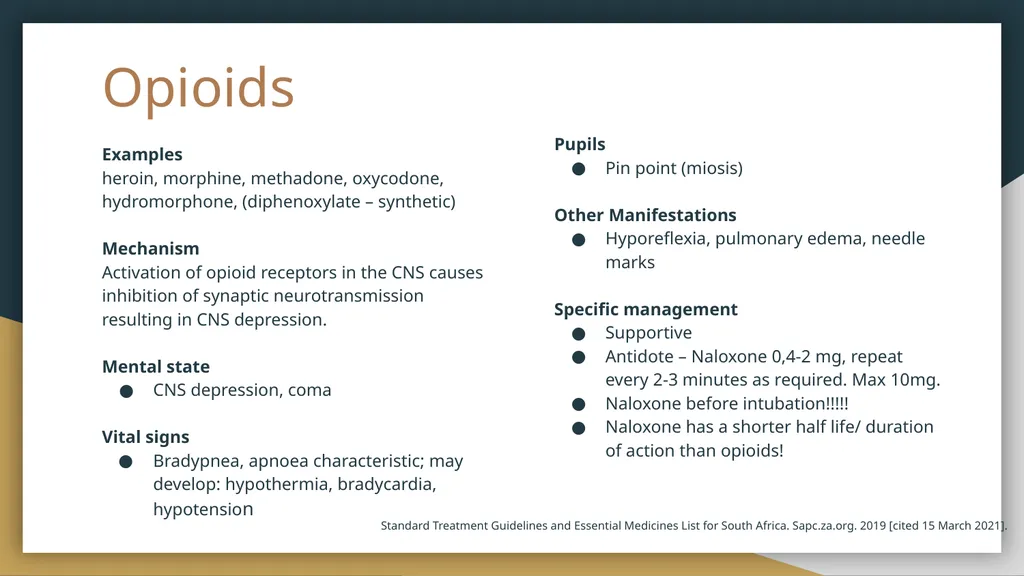
slide16. Opioids Examples
heroin, morphine, methadone, oxycodone, hydromorphone, (diphenoxylate – synthetic)
Mechanism
Activation of opioid receptors in the CNS causes inhibition of synaptic neurotransmission resulting in CNS depression.
Mental state
CNS depression, coma
Vital signs
Bradypnea, apnoea characteristic; may develop: hypothermia, bradycardia, hypotension Pupils
Pin point (miosis)
Other Manifestations
Hyporeflexia, pulmonary edema, needle marks
Specific management
Supportive
Antidote – Naloxone 0,4-2 mg, repeat every 2-3 minutes as required. Max 10mg.
Naloxone before intubation!!!!!
Naloxone has a shorter half life/ duration of action than opioids! Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
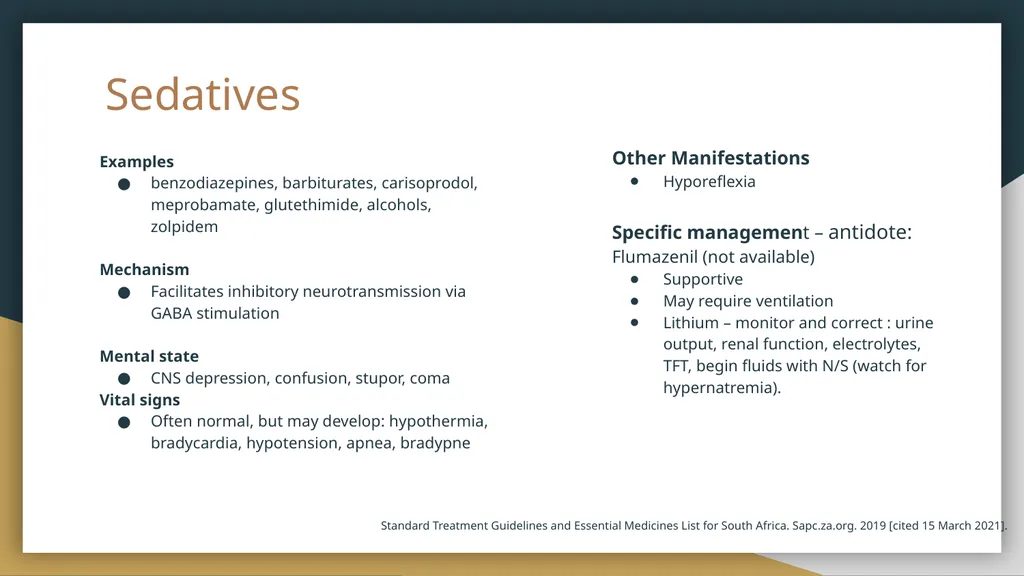
slide17. Sedatives Examples
benzodiazepines, barbiturates, carisoprodol, meprobamate, glutethimide, alcohols, zolpidem
Mechanism
Facilitates inhibitory neurotransmission via GABA stimulation
Mental state
CNS depression, confusion, stupor, coma
Vital signs
Often normal, but may develop: hypothermia, bradycardia, hypotension, apnea, bradypne Other Manifestations
Hyporeflexia
Specific management – antidote: Flumazenil (not available)
Supportive
May require ventilation
Lithium – monitor and correct : urine output, renal function, electrolytes, TFT, begin fluids with N/S (watch for hypernatremia). Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
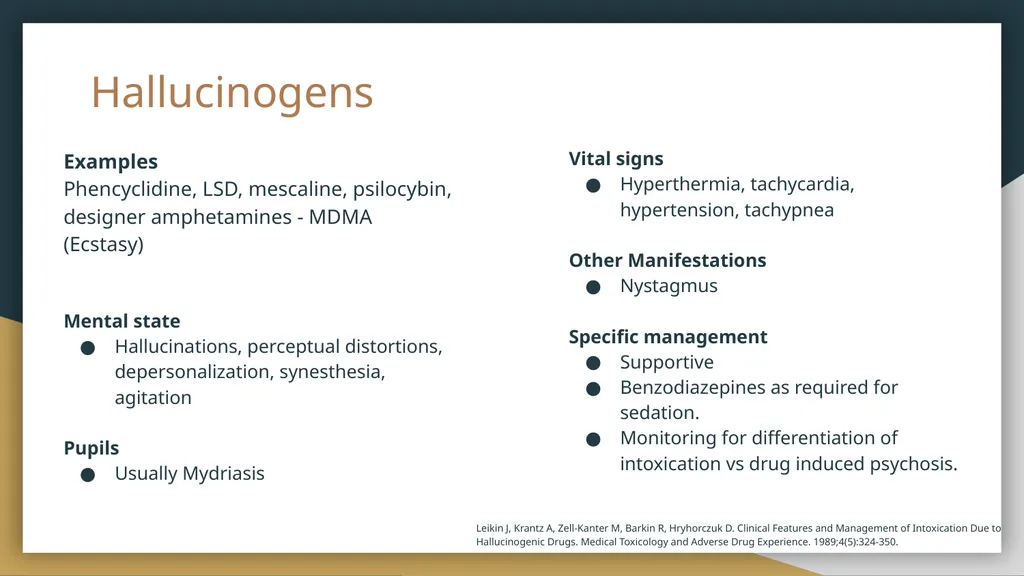
slide18. Hallucinogens Examples
Phencyclidine, LSD, mescaline, psilocybin, designer amphetamines - MDMA (Ecstasy)
Mental state
Hallucinations, perceptual distortions, depersonalization, synesthesia, agitation
Pupils
Usually Mydriasis Vital signs
Hyperthermia, tachycardia, hypertension, tachypnea
Other Manifestations
Nystagmus
Specific management
Supportive
Benzodiazepines as required for sedation.
Monitoring for differentiation of intoxication vs drug induced psychosis. Leikin J, Krantz A, Zell-Kanter M, Barkin R, Hryhorczuk D. Clinical Features and Management of Intoxication Due to Hallucinogenic Drugs. Medical Toxicology and Adverse Drug Experience. 1989;4(5):324-350.<br>
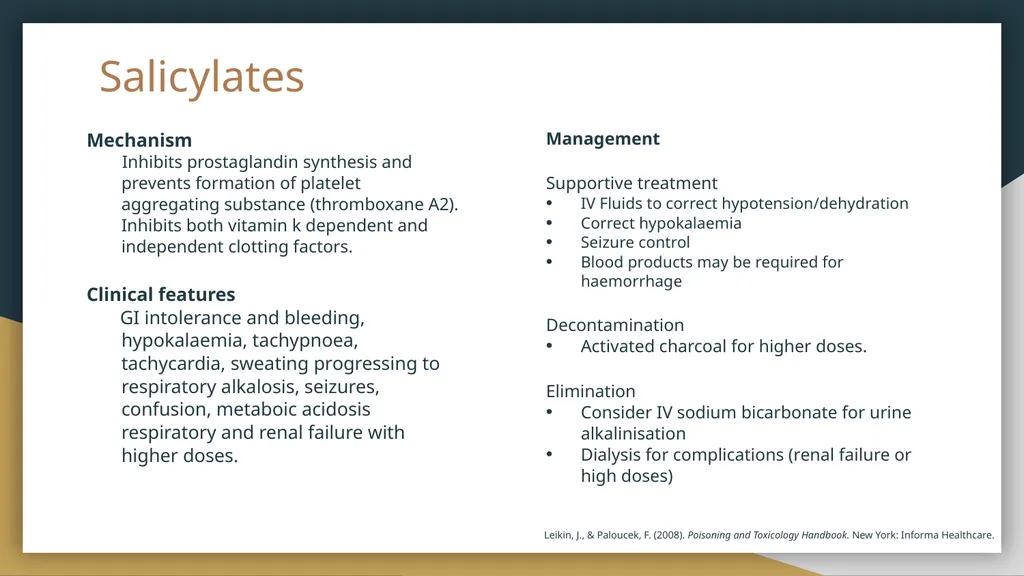
slide19. Salicylates Mechanism
Inhibits prostaglandin synthesis and prevents formation of platelet aggregating substance (thromboxane A2). Inhibits both vitamin k dependent and independent clotting factors.
Clinical features
GI intolerance and bleeding, hypokalaemia, tachypnoea, tachycardia, sweating progressing to respiratory alkalosis, seizures, confusion, metaboic acidosis respiratory and renal failure with higher doses. Management
Supportive treatment
IV Fluids to correct hypotension/dehydration
Correct hypokalaemia
Seizure control
Blood products may be required for haemorrhage
Decontamination
Activated charcoal for higher doses.
Elimination
Consider IV sodium bicarbonate for urine alkalinisation
Dialysis for complications (renal failure or high doses) Leikin, J., & Paloucek, F. (2008). Poisoning and Toxicology Handbook. New York: Informa Healthcare.<br>
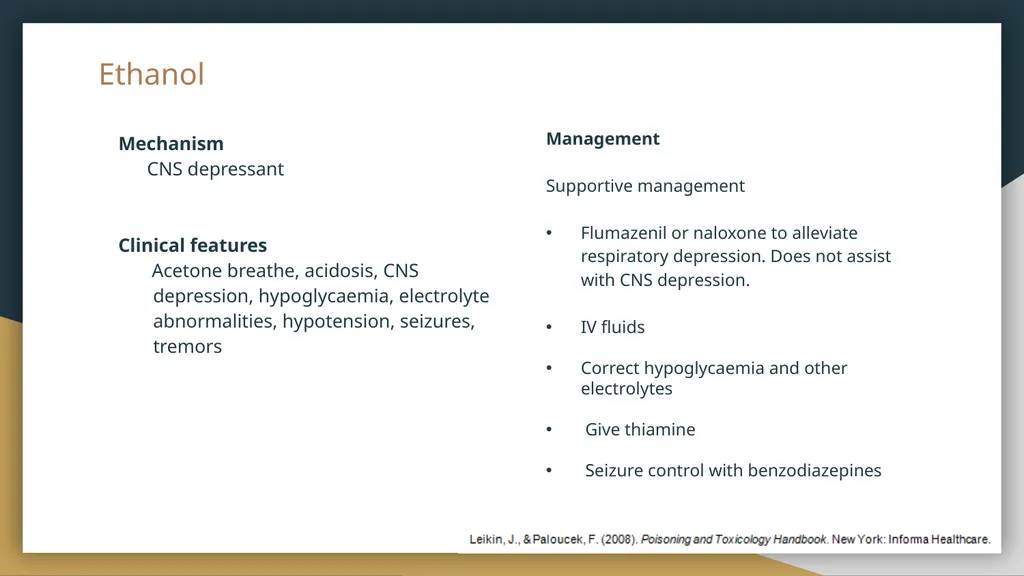
slide20. Ethanol Mechanism
CNS depressant
Clinical features
Acetone breathe, acidosis, CNS depression, hypoglycaemia, electrolyte abnormalities, hypotension, seizures, tremors Management
Supportive management
Flumazenil or naloxone to alleviate respiratory depression. Does not assist with CNS depression.
IV fluids
Correct hypoglycaemia and other electrolytes
Give thiamine
Seizure control with benzodiazepines<br>
slide21. Isoniazid poisoning Mechanism
Metabolism of INH produces reactive metabolites that bind and damage cellular macromolecules in liver
Clinical features
Triad of seizures, metabolic acidosis and coma Management
Antidote:
Pyridoxine 1g for every gram of isoniazid ingested( max 5g)
If unknown amount - 5g
Supportive care
Benzodiazepines for seizure control Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide22. Anticoagulant poisoning Examples
Warfarin
Rat poisons (superwarfarin- more potent and longer duration of effect)
Mechanism
Vitamin K antagonist
Clinical features
Bleeding is the main clinical presentation Management
Resuscitation- may require FFP is significant bleeding
Stop warfarin
Evaluate bleeding risk
*High risk ( stroke, anemia, bleeding) Give Vitamin K 1-2.5mg and monitor INR
*Low risk: Monitor INR
Superwafarin- may require months of vitamin K therapy<br>
slide23. Snake Bites For the majority of cases of snake bites, the snake is not identified.
Three types of venom: cytotoxic, Neurotoxic and haemotoxic
Cytotoxic features (e.g. puff adder):
Pain, swelling, blisters, necrosis, hypotension, compartment syndrome
Neurotoxic features (e.g black/green mamba:
Paraesthesia, visual disturbance, ptosis, drowsiness, weakness, respiratory paralysis
Haemotoxic features (e.g. boomslang)
Spontaneous bleeding, headache, dizziness Management
Supportive and symptomatic management
Mechanical ventilation may be required with neurotoxic venom
Blood products for haemotoxic venom
Clean wound and antibiotics for secondary infection
Anti-venom Muller, G. J. (2012). Snake bite in southern africa: diagnosis and management. Continuing Medical Education , Vol 30.<br>
slide24. Conclusion A structured approach is needed to adequately manage the patient
Stabilise the intoxicated patient
Remember family and friends for collateral history
Physical examination to help identify toxidromes
Quick referral
Treat the patient, not the toxidrome
Poison information centre
Tygerberg Poison Information Centre
Red Cross War Memorial Children’s Hospital Poisons Information Centre<br>
slide25. REFERENCES Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021]. Available from: https://www.sapc.za.org/Media/Default/Documents/STG%20hospital%20level%20adult%202019_v2.0.pdf
Daly, S., Little, M., & Murray, L. (2006). A risk assessment based approach to the management of acute poisoning. TOXICOLOGY: AN AUSTRALIAN PERSPECTIVE , 396-399.
Chiew Al, Reith D, Pomerleau A, et al. Updated guidelines for the management of paracetamol poisoning in Australia and New Zealand. Med J Aust 2019;
Leikin, J., & Paloucek, F. (2008). Poisoning and Toxicology Handbook. New York: Informa Healthcare.
Leikin J, Krantz A, Zell-Kanter M, Barkin R, Hryhorczuk D. Clinical Features and Management of Intoxication Due to Hallucinogenic Drugs. Medical Toxicology and Adverse Drug Experience. 1989;4(5):324-350.
Muller, G. J. (2012). Snake bite in southern africa: diagnosis and management. Continuing Medical Education , Vol 30.
WHO. WHO | Poisoning [Internet]. Who.int. 2021 [cited 25 March 2021]. Available from: https://www.who.int/environmental_health_emergencies/poisoning/en/<br>
Simon Brooks
Rahul Lakman<br>
slide2. INTRODUCTION Poisoning and overdose is relatively common in our socioeconomic setting.
Poison refers to a substance that is capable of causing harm or death when introduced or absorbed by the body.
Overdose refers to the consumption or administration of a quantity of drug, in excess of the prescribed or usual dose.
Both of which can be deliberate or accidental.
Poisoning and overdose are grouped into Toxidromes.
These are defined by the mental state, vital sign trends as well as other physical signs.<br>
slide3. Contents General approach to overdose and poisoning
When to suspect poisoning
Toxidromes
Paracetamol
INH Poisoning
Warfarin poisoning
Snake bites Cholinergics
Anticholinergics
Serotonin syndrome
Opioids
Sympathomimetics
Sedatives
Hallucinogens
Salicylates
Ethanol<br>
slide4. GENERAL APPROACH TO OVERDOSE AND POISONING (RRSI DEAD) RESUSCITATION
Airway
Breathing
Circuation
Hypertension
Hypotension
Arrhythmias
Disability
Seizures
Hypoglycaemia
Exposure
Hyperthermia RISK ASSESSMENT
Patient factors e.g. Comorbidities, weight
Current clinical status ( vitals, GCS)
Agent, dose, time of ingestion (history and examination) Daly, S., Little, M., & Murray, L. (2006). A risk assessment based approach to the management of acute poisoning. TOXICOLOGY: AN AUSTRALIAN PERSPECTIVE , 396-399.<br>
slide5. SUPPORTIVE CARE
Feeding/fluids
Analgesia
Sedation
Thromboprophylaxis
Head up position
Ulcer prophylaxis
Glycemic control
Spontaneous breathing trial
Bowel care
Indwelling catheter removal
Deescalation of antibiotics INVESTIGATIONS
ECG
Paracetamol levels<br>
slide6. DECONTAMINATION
Aims to reduce the absorption of ingested agent
Ingestion
Caustic vs Toxic: Duration since exposure, vomiting – activated charcoal, gastric lavage.
Dry powders
Brush off.
Liquids
Irrigation
Gasses
Ventilation ENHANCED ELIMINATION
Interventions aimed to enhance the elimination of an agent
Examples: Urine alkalinisation
Haemodialysis<br>
slide7. ANTIDOTES
Correct the effects of the poison
Side effects DISPOSITION
Initial risk assessment allows for appropriate planning of disposition<br>
slide8. When to suspect poisoning or overdose T - Temperature
O- Odour
X- Extrapyramidal signs
I- Ileus
D- Dry mouth/ excessive salivation/Delirium
R- Rashes
O- Overdose (polypharmacy)
M- muscle tone abnormalities
E- Eyes/ ECG
S-Seizures<br>
slide9. TOXIDROMES Group of abnormal vital signs and features found on examination associated with a specific group of toxin or drug.
Common types of toxidromes
Cholinergics
Anticholinergics
Serotonin syndrome
Opioids
Sympathomimetics
Sedatives
Hallucinogens
Salicylates
Ethanol<br>
slide10. Paracetamol Mechanism:
Acute liver injury resulting from accumulation of toxic metabolite of paracetamol, N-acetyl-p-benzoquinone imine (NAPQI). Increased concentrations of NAPQI depletes glutathione, which is required for conjugation.
Clinical features:
Up to 1 day – nausea, vomiting, sweating. Metabolic acidosis
1-3 days – may be asymptomatic. Hepatic toxicity can develop
5-14 days- recovery with resolution of hepatic enzymes.
Toxic dose > 200mg/kg or 10g (whichever is less) Management:
Decontamination:
Activated charcoal (<2 hours)
Antidote:
N-acetylcysteine: if paracetamol levels will not be available within 8 hours of ingestion, start NAC
>8 hours, start NAC if toxic dose ingested or patient showing clinical signs of toxicity.
NAC releases histamine which can mimic an allergic reaction. Slow down infusion and add anti-histamine. In case of bronchospasm, stop infusion
Dose: initial infusion 200mg/kg in 500 ml 5% dextrose over 4 hours. Second infusion: 100mg/kg in 1000ml 5% dextrose water over 16 hours. Chiew Al, Reith D, Pomerleau A, et al. Updated guidelines for the management of paracetamol poisoning in Australia and New Zealand. Med J Aust 2019;<br>
slide11. Cholinergic Toxidrome Examples
Organophosphates, pesticides,physostigmine
Absorption can be through skin, taken orally or by inhalation.
Mechanism
Organophosphates inhibit Acetylcholinesterase allowing for the accumulation of acetylcholine. This occurs at the cholinergic junctions of the nervous system including postganglionic parasympathetic junctions, which is the site of muscarinic activity, and at the neuromuscular junction, the site of nicotinic activity.
Mental state
Confused Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide12. Clinical features Management
Resuscitation
Aspiration, bronchospasm, seizures may require intubation and ventilation.
Haemodynamic monitoring
Seizure control with benzodiazepine
Decontamination Remove all clothing
Antidote
Atropine 2-5mg IVI. Reasses every 5 minutes for evidence of atropinization (decreased secretions, improvement of bradycardia). If no response, double the dose. If there is a response, give the same or reduced dose.
IVI infusion: total dose of atropine given. 10-20% of this dose per hour<br>
slide13. Anticholinergic Toxidrome Examples
Antihistamines, tricyclic antidepressants, cyclobenzaprine, orphenadrine, antiparkinson agents, antispasmodics, phenothiazines, atropine, scopolamine, belladonna alkaloids (eg, Jimson Weed)
Mechanism
Blocks the action of acetylcholine at central and peripheral receptors
Mental state
Hypervigilance, agitation, hallucinations, delirium with mumbling speech, coma
Pupills
Mydratic Vital signs
Hyperthermia, tachycardia, hypertension, tachypnea
Other Manifestations
Dry flushed skin, dry mucous membranes, decreased bowel sounds, urinary retention, myoclonus, decreased GIT motility, choreoathetosis, picking behavior, seizures (rare)
Specific management
Activated charcoal
Diazepam- Seizure/status epilepticus management
ECG and continuous cardiac monitoring required
Refer if no response to treatment or dysrhythmia. Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide14. Serotonin syndrome Examples:
MAOIs alone or with: SSRIs, meperidine, dextromethorphan, TCAs, L-tryptophan
Mechanism:
Activation of serotonergic receptors by either inhibition of serotonin uptake, decrease metabolism or increased synthesis of serotonin
Mental state
Confusion, agitation, coma
Pupils
Mydriasis
Vital signs
Hyperthermia, tachycardia, hypertension, tachypnea Other Manifestations
Tremor, myoclonus, hyperreflexia, clonus, diaphoresis, flushing, trismus, rigidity, diarrhea
Specific management
Supportive
Fits monitoring
Benzodiazepines as required for muscular rigidity and seizures
ECG Leikin, J., & Paloucek, F. (2008). Poisoning and Toxicology Handbook. New York: Informa Healthcare.<br>
slide15. Sympathomimetics Examples
Cocaine, amphetamines, cathinones, ephedrine, pseudoephedrine, phenylpropanolamine, theophylline, caffeine
Mechanism
Inhibition of norepinephrine and dopamine reuptake at the preganglionic synapse. Effects related to increased norepinephrine and dopamine at synaptic cleft.
Mental state
Hyperalert, agitation, hallucinations, paranoia
Pupils
Mydriasis
Vital signs
Hyperthermia, tachycardia, hypertension, widened pulse pressure, tachypnea, hyperpnea Other Manifestations
Diaphoresis, tremors, hyperreflexia, seizures
Cocaine toxicity- cvs manifestations predominate (dysrhythmias, myocardial ischaemia)
Specific management
Supportive and ECG monitoring
Diazepam as required for agitation and tachycardia
Treat acute severe hypertension
Fits monitoring Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide16. Opioids Examples
heroin, morphine, methadone, oxycodone, hydromorphone, (diphenoxylate – synthetic)
Mechanism
Activation of opioid receptors in the CNS causes inhibition of synaptic neurotransmission resulting in CNS depression.
Mental state
CNS depression, coma
Vital signs
Bradypnea, apnoea characteristic; may develop: hypothermia, bradycardia, hypotension Pupils
Pin point (miosis)
Other Manifestations
Hyporeflexia, pulmonary edema, needle marks
Specific management
Supportive
Antidote – Naloxone 0,4-2 mg, repeat every 2-3 minutes as required. Max 10mg.
Naloxone before intubation!!!!!
Naloxone has a shorter half life/ duration of action than opioids! Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide17. Sedatives Examples
benzodiazepines, barbiturates, carisoprodol, meprobamate, glutethimide, alcohols, zolpidem
Mechanism
Facilitates inhibitory neurotransmission via GABA stimulation
Mental state
CNS depression, confusion, stupor, coma
Vital signs
Often normal, but may develop: hypothermia, bradycardia, hypotension, apnea, bradypne Other Manifestations
Hyporeflexia
Specific management – antidote: Flumazenil (not available)
Supportive
May require ventilation
Lithium – monitor and correct : urine output, renal function, electrolytes, TFT, begin fluids with N/S (watch for hypernatremia). Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide18. Hallucinogens Examples
Phencyclidine, LSD, mescaline, psilocybin, designer amphetamines - MDMA (Ecstasy)
Mental state
Hallucinations, perceptual distortions, depersonalization, synesthesia, agitation
Pupils
Usually Mydriasis Vital signs
Hyperthermia, tachycardia, hypertension, tachypnea
Other Manifestations
Nystagmus
Specific management
Supportive
Benzodiazepines as required for sedation.
Monitoring for differentiation of intoxication vs drug induced psychosis. Leikin J, Krantz A, Zell-Kanter M, Barkin R, Hryhorczuk D. Clinical Features and Management of Intoxication Due to Hallucinogenic Drugs. Medical Toxicology and Adverse Drug Experience. 1989;4(5):324-350.<br>
slide19. Salicylates Mechanism
Inhibits prostaglandin synthesis and prevents formation of platelet aggregating substance (thromboxane A2). Inhibits both vitamin k dependent and independent clotting factors.
Clinical features
GI intolerance and bleeding, hypokalaemia, tachypnoea, tachycardia, sweating progressing to respiratory alkalosis, seizures, confusion, metaboic acidosis respiratory and renal failure with higher doses. Management
Supportive treatment
IV Fluids to correct hypotension/dehydration
Correct hypokalaemia
Seizure control
Blood products may be required for haemorrhage
Decontamination
Activated charcoal for higher doses.
Elimination
Consider IV sodium bicarbonate for urine alkalinisation
Dialysis for complications (renal failure or high doses) Leikin, J., & Paloucek, F. (2008). Poisoning and Toxicology Handbook. New York: Informa Healthcare.<br>
slide20. Ethanol Mechanism
CNS depressant
Clinical features
Acetone breathe, acidosis, CNS depression, hypoglycaemia, electrolyte abnormalities, hypotension, seizures, tremors Management
Supportive management
Flumazenil or naloxone to alleviate respiratory depression. Does not assist with CNS depression.
IV fluids
Correct hypoglycaemia and other electrolytes
Give thiamine
Seizure control with benzodiazepines<br>
slide21. Isoniazid poisoning Mechanism
Metabolism of INH produces reactive metabolites that bind and damage cellular macromolecules in liver
Clinical features
Triad of seizures, metabolic acidosis and coma Management
Antidote:
Pyridoxine 1g for every gram of isoniazid ingested( max 5g)
If unknown amount - 5g
Supportive care
Benzodiazepines for seizure control Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021].<br>
slide22. Anticoagulant poisoning Examples
Warfarin
Rat poisons (superwarfarin- more potent and longer duration of effect)
Mechanism
Vitamin K antagonist
Clinical features
Bleeding is the main clinical presentation Management
Resuscitation- may require FFP is significant bleeding
Stop warfarin
Evaluate bleeding risk
*High risk ( stroke, anemia, bleeding) Give Vitamin K 1-2.5mg and monitor INR
*Low risk: Monitor INR
Superwafarin- may require months of vitamin K therapy<br>
slide23. Snake Bites For the majority of cases of snake bites, the snake is not identified.
Three types of venom: cytotoxic, Neurotoxic and haemotoxic
Cytotoxic features (e.g. puff adder):
Pain, swelling, blisters, necrosis, hypotension, compartment syndrome
Neurotoxic features (e.g black/green mamba:
Paraesthesia, visual disturbance, ptosis, drowsiness, weakness, respiratory paralysis
Haemotoxic features (e.g. boomslang)
Spontaneous bleeding, headache, dizziness Management
Supportive and symptomatic management
Mechanical ventilation may be required with neurotoxic venom
Blood products for haemotoxic venom
Clean wound and antibiotics for secondary infection
Anti-venom Muller, G. J. (2012). Snake bite in southern africa: diagnosis and management. Continuing Medical Education , Vol 30.<br>
slide24. Conclusion A structured approach is needed to adequately manage the patient
Stabilise the intoxicated patient
Remember family and friends for collateral history
Physical examination to help identify toxidromes
Quick referral
Treat the patient, not the toxidrome
Poison information centre
Tygerberg Poison Information Centre
Red Cross War Memorial Children’s Hospital Poisons Information Centre<br>
slide25. REFERENCES Standard Treatment Guidelines and Essential Medicines List for South Africa. Sapc.za.org. 2019 [cited 15 March 2021]. Available from: https://www.sapc.za.org/Media/Default/Documents/STG%20hospital%20level%20adult%202019_v2.0.pdf
Daly, S., Little, M., & Murray, L. (2006). A risk assessment based approach to the management of acute poisoning. TOXICOLOGY: AN AUSTRALIAN PERSPECTIVE , 396-399.
Chiew Al, Reith D, Pomerleau A, et al. Updated guidelines for the management of paracetamol poisoning in Australia and New Zealand. Med J Aust 2019;
Leikin, J., & Paloucek, F. (2008). Poisoning and Toxicology Handbook. New York: Informa Healthcare.
Leikin J, Krantz A, Zell-Kanter M, Barkin R, Hryhorczuk D. Clinical Features and Management of Intoxication Due to Hallucinogenic Drugs. Medical Toxicology and Adverse Drug Experience. 1989;4(5):324-350.
Muller, G. J. (2012). Snake bite in southern africa: diagnosis and management. Continuing Medical Education , Vol 30.
WHO. WHO | Poisoning [Internet]. Who.int. 2021 [cited 25 March 2021]. Available from: https://www.who.int/environmental_health_emergencies/poisoning/en/<br>