
Professional Performance Evaluation FPPE & OPPE
DJ
Published · 53 slides · 0 views

1 / 1









































Description
Professional Performance Evaluation FPPE OPPE Presented by John Pastrano, BBA, CPMSM, CPCS Washington Association of Medical Staff Services April 24, 2019 Privileging Historically Verification of training Residency Fellowship CME
Related Topics
Share
Embed code
Download this presentation From Below
"Professional Performance Evaluation FPPE & OPPE" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
01
Professional Performance Evaluation
FPPE & OPPE Presented by John Pastrano, BBA, CPMSM, CPCS
Washington Association of Medical Staff Services
April 24, 2019<br>
Washington Association of Medical Staff Services
April 24, 2019<br>
02
Privileging Historically… Verification of training
Residency / Fellowship
CME
Credentialing Standards
Numbers criteria
Previous Chair/Faculty/Peer confirmation<br>
Residency / Fellowship
CME
Credentialing Standards
Numbers criteria
Previous Chair/Faculty/Peer confirmation<br>
03
Joint Commission 2007 Professional
Practice
Evaluation OPPE FPPE<br>
Practice
Evaluation OPPE FPPE<br>
04
JC Medical Staff Standards MS.08.01.01 Focused Professional Practice Evaluation
The organized medical staff defines the circumstances requiring monitoring and evaluation of a practitioner’s professional performance.<br>
The organized medical staff defines the circumstances requiring monitoring and evaluation of a practitioner’s professional performance.<br>
05
…and JC Medical Staff Standards MS.08.01.03 Ongoing Professional Practice Evaluation
Ongoing professional practice evaluation information is factored into the decision to maintain existing privilege(s), to revise existing privilege(s), or to revoke an existing privilege prior to or at the time of renewal.<br>
Ongoing professional practice evaluation information is factored into the decision to maintain existing privilege(s), to revise existing privilege(s), or to revoke an existing privilege prior to or at the time of renewal.<br>
06
Joint Commission 2007 Professional
Practice
Evaluation OPPE FPPE<br>
Practice
Evaluation OPPE FPPE<br>
07
What is FPPE? Process whereby the organization evaluates the privilege-specific competence of the practitioner who does not have documented evidence of competently performing the requested privilege at the organization<br>
08
Concept
External performance data cannot be used for own privileging purposes
Concept - CMS does not allow privileging by proxy
Sharing Compromises Peer Protection<br>
External performance data cannot be used for own privileging purposes
Concept - CMS does not allow privileging by proxy
Sharing Compromises Peer Protection<br>
09
What is OPPE? Routine monitoring of current competency for current Medical Staff members<br>
10
Isn’t this the same as Peer Review? The process by which a practitioner, or committee of practitioners, examines the work of a peer and determines whether the practitioner under review has met accepted standards of care in rendering medical services.<br>
11
Components of Peer Review Focused Professional Practice Evaluation
Ongoing Professional Practice Evaluation
Individual Case Review
Proctor / Consult<br>
Ongoing Professional Practice Evaluation
Individual Case Review
Proctor / Consult<br>
12
Individual Case Review The process outlined for peer review of a particular case identified with a potential quality of care issue.<br>
13
Peer Review Peer - Any practitioner who possesses the same or similar knowledge and training in a medical specialty as the practitioner whose care is the subject of review.<br>
14
Peer Review Examples of Peers:
Emergency Medicine / Internal Med / Family Med
Pediatrics / Family Practice
General Surgery / Gynecology / Urology
Orthopedics / Neurosurgery
Pathology
Radiology<br>
Emergency Medicine / Internal Med / Family Med
Pediatrics / Family Practice
General Surgery / Gynecology / Urology
Orthopedics / Neurosurgery
Pathology
Radiology<br>
15
Peer Review More Examples of Peers:
Anesthesiology
Dentist / Oral Surgeon
Cardiology / Internal Medicine
Interventional Cardiology
Nurse Practitioner / PA – same or physician
CRNA – same or physician<br>
Anesthesiology
Dentist / Oral Surgeon
Cardiology / Internal Medicine
Interventional Cardiology
Nurse Practitioner / PA – same or physician
CRNA – same or physician<br>
16
Scope of FPPE & OPPE Applies to all credentialed / privileged members of the Medical Staff and Allied Health Practitioners.<br>
17
Scope of FPPE & OPPE Exception:
No-volume providers with medical staff membership and without clinical privileges per Joint Commission clarification are exempt from the Ongoing Professional Performance Evaluation and Focused Professional Practice Evaluation requirements contained within this document.<br>
No-volume providers with medical staff membership and without clinical privileges per Joint Commission clarification are exempt from the Ongoing Professional Performance Evaluation and Focused Professional Practice Evaluation requirements contained within this document.<br>
18
Purpose of FPPE & OPPE To assure that the hospital, through the activities of its medical staff, assess the ongoing professional practice and competence of its medical staff, conducts professional practice evaluations, and uses the results of such assessments and evaluations to improve professional competence, practice, and the quality of patient care.<br>
19
Purpose of FPPE & OPPE To define those circumstances in which an external review or focused review may be necessary.
To address identified issues in an effective and consistent manner.<br>
To address identified issues in an effective and consistent manner.<br>
20
Purpose of FPPE & OPPE “Professional Practice Evaluation” is considered an element of the peer review process and the records and proceedings relating to this policy are confidential and privileged to the fullest extent permitted by applicable law.<br>
21
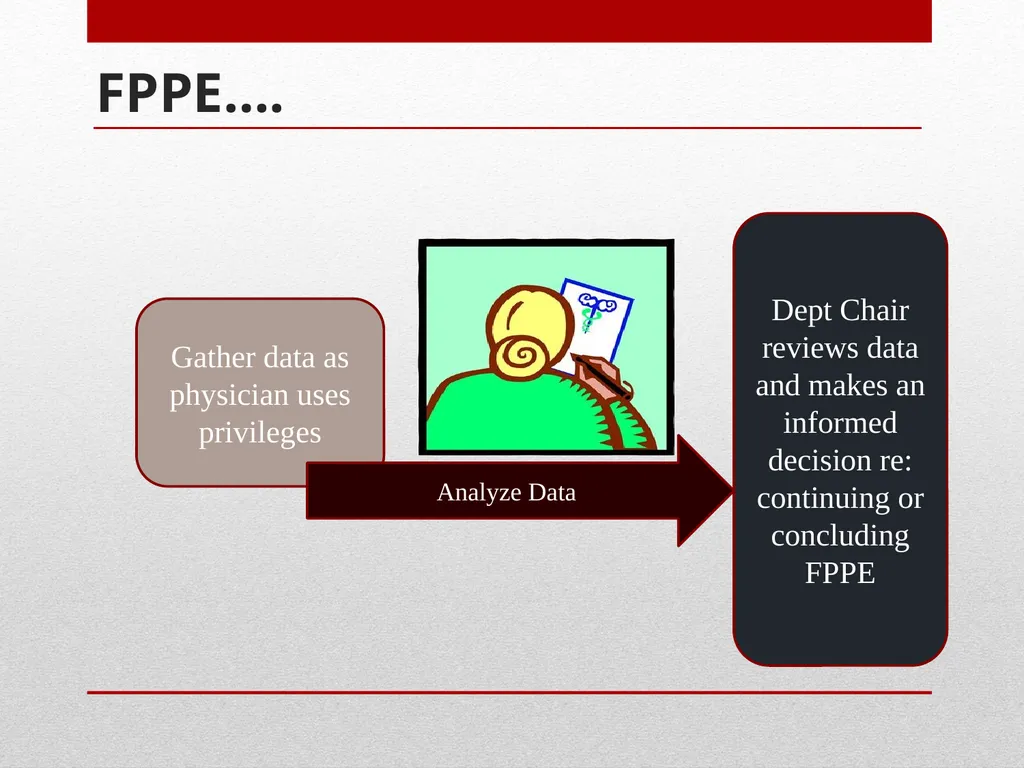
FPPE…. Gather data as physician uses privileges Analyze Data Dept Chair reviews data and makes an informed decision re: continuing or concluding FPPE<br>
22
Initiation of FPPE Upon initial appointment
When a new privilege is requested by an existing practitioner
When a question arises through the OPPE process, individual case review, or other peer review process regarding a currently privileged practitioner’s ability to provide safe, high-quality patient care<br>
When a new privilege is requested by an existing practitioner
When a question arises through the OPPE process, individual case review, or other peer review process regarding a currently privileged practitioner’s ability to provide safe, high-quality patient care<br>
23
Initiation of FPPE Example:
When a trigger is exceeded and preliminary review indicates a need for further evaluation.<br>
When a trigger is exceeded and preliminary review indicates a need for further evaluation.<br>
24
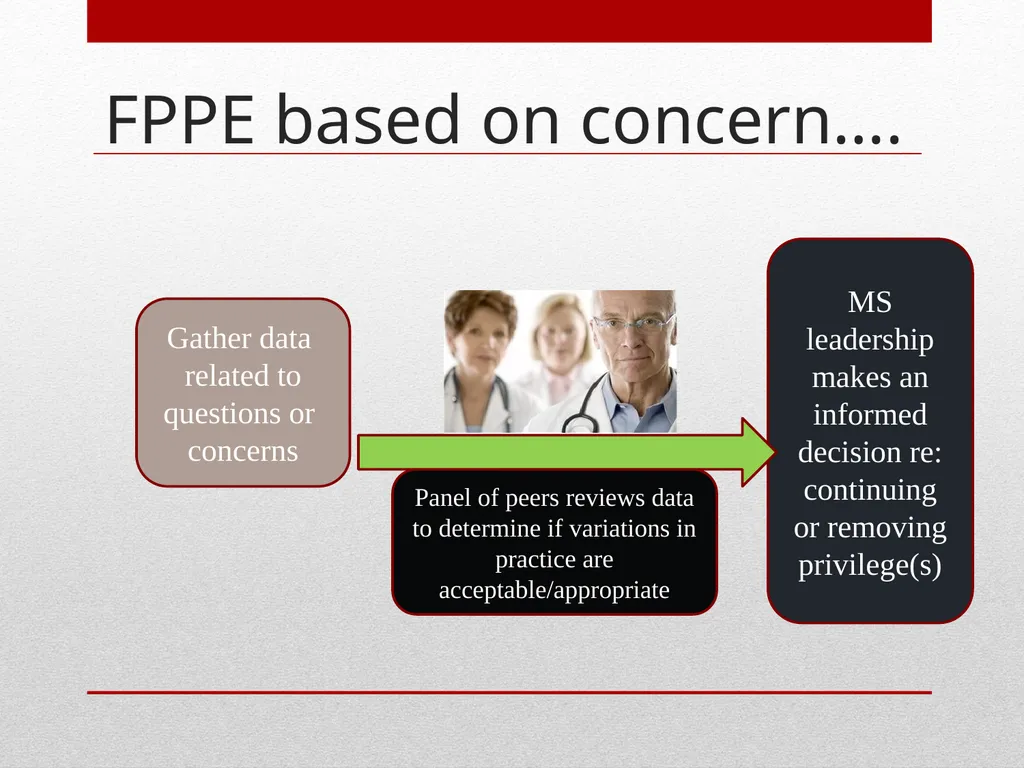
FPPE based on concern…. Gather data related to questions or concerns MS leadership makes an informed decision re: continuing or removing privilege(s) Panel of peers reviews data to determine if variations in practice are acceptable/appropriate<br>
25
What is Initiated? FPPE is not considered an investigation as defined in the Medical Staff Bylaws and is not subject to the bylaws provisions related to investigations.
If FPPE results in an action plan to perform an investigation, the process identified in the Medical Staff Bylaws would be followed.<br>
If FPPE results in an action plan to perform an investigation, the process identified in the Medical Staff Bylaws would be followed.<br>
26
Timeframe for Collection & Reporting Must be time-limited, defined by:
A specific period of time, and/or
A specific volume
(number of procedures/admissions)<br>
A specific period of time, and/or
A specific volume
(number of procedures/admissions)<br>
27
Other FPPE considerations May take into account previous experience in determining the approach, extent, and time frame:
Recent graduate from training program affiliated with the facility (data available)
Recent graduate from a training program at another facility (data not available)<br>
Recent graduate from training program affiliated with the facility (data available)
Recent graduate from a training program at another facility (data not available)<br>
28
Other FPPE considerations May take into account previous experience in determining the approach, extent, and time frame:
Practitioner with regular experience exercising the requested privilege of fewer than two years on another medical staff
Regular experience exercising the requested privilege of more than five years at another medical staff<br>
Practitioner with regular experience exercising the requested privilege of fewer than two years on another medical staff
Regular experience exercising the requested privilege of more than five years at another medical staff<br>
29
Other FPPE considerations Should begin with the first admission / procedure
Should (optimally) be completed with 3 months, or a suitable period based upon volume
Period may be extended as necessary but may not extend beyond the first biennial reappointment<br>
Should (optimally) be completed with 3 months, or a suitable period based upon volume
Period may be extended as necessary but may not extend beyond the first biennial reappointment<br>
30
FPPE Methods Chart review - concurrent and/or retrospective
Simulation
Discussion with the practitioner and/or other individuals involved in care
Dependent AHPs – review or proctoring by the sponsoring physician
Internal or external peer review<br>
Simulation
Discussion with the practitioner and/or other individuals involved in care
Dependent AHPs – review or proctoring by the sponsoring physician
Internal or external peer review<br>
31
FPPE Methods Communicate with the Practitioner
Cause for the focused monitoring
Anticipated duration
Specific mechanism by which monitoring will occur (i.e. chart review, proctoring, etc.)<br>
Cause for the focused monitoring
Anticipated duration
Specific mechanism by which monitoring will occur (i.e. chart review, proctoring, etc.)<br>
32
Performance Monitoring Criteria & Triggers
Develop monitoring criteria
Include specific performance elements
Include thresholds or triggers
Approved by the medical staff department/committee, MEC<br>
Develop monitoring criteria
Include specific performance elements
Include thresholds or triggers
Approved by the medical staff department/committee, MEC<br>
33
Triggers Single egregious case
Evidence of a practice trend
Exceeding a threshold established for OPPE
Patient / staff complaints
Non-compliance with Bylaws, R&R
Elevated infection, mortality
Elevated complication rates
Failure to follow approved clinical practice guidelines
Unprofessional behavior or disruptive conduct<br>
Evidence of a practice trend
Exceeding a threshold established for OPPE
Patient / staff complaints
Non-compliance with Bylaws, R&R
Elevated infection, mortality
Elevated complication rates
Failure to follow approved clinical practice guidelines
Unprofessional behavior or disruptive conduct<br>
34
Conclusion of FPPE Findings reviewed by MEC or Department/Chair
Decision and recommendation
Move forward with OPPE
Extend period and/or scope of FPPE
Develop performance improvement plan
Limit or suspend privilege(s)<br>
Decision and recommendation
Move forward with OPPE
Extend period and/or scope of FPPE
Develop performance improvement plan
Limit or suspend privilege(s)<br>
35
Conclusion of FPPE Practitioner should be notified of performance outcome in writing
Findings & outcome of FPPE
Specific actions that need to be taken by Practitioner to address any quality concerns, including follow-up
If FPPE is complete or will continue (w/period)
If complete – move to OPPE<br>
Findings & outcome of FPPE
Specific actions that need to be taken by Practitioner to address any quality concerns, including follow-up
If FPPE is complete or will continue (w/period)
If complete – move to OPPE<br>
36
Conclusion of FPPE Activity/volume insufficient to meet FPPE, Practitioner may:
Voluntarily resign privilege(s)
Submit request for extending FPPE period
Submit evidence of sufficient volume from another local facility w/ external peer reference
Chair/Department/Committee may discretionarily extend FPPE
NOTE: Practitioner is not entitled to a hearing/procedural rights for voluntary relinquishment<br>
37
Performance Improvement Plan Plan drafted by Department/Chair/Committee
Presented to MEC for approval
Practitioner offered opportunity to address Committee and respond to findings
Methods to resolve issues clearly defined
Education / CME
Proctoring and/or mentoring
Counseling
Practitioner assistance program
Suspension or revocation of privilege(s)<br>
Presented to MEC for approval
Practitioner offered opportunity to address Committee and respond to findings
Methods to resolve issues clearly defined
Education / CME
Proctoring and/or mentoring
Counseling
Practitioner assistance program
Suspension or revocation of privilege(s)<br>
38
Performance Improvement Plan MEC approved PI Plan
Dept Chair and/or COS meet w/ Practitioner
Agree – sign written document
Does not agree – forward to MEC for resolution<br>
Dept Chair and/or COS meet w/ Practitioner
Agree – sign written document
Does not agree – forward to MEC for resolution<br>
39
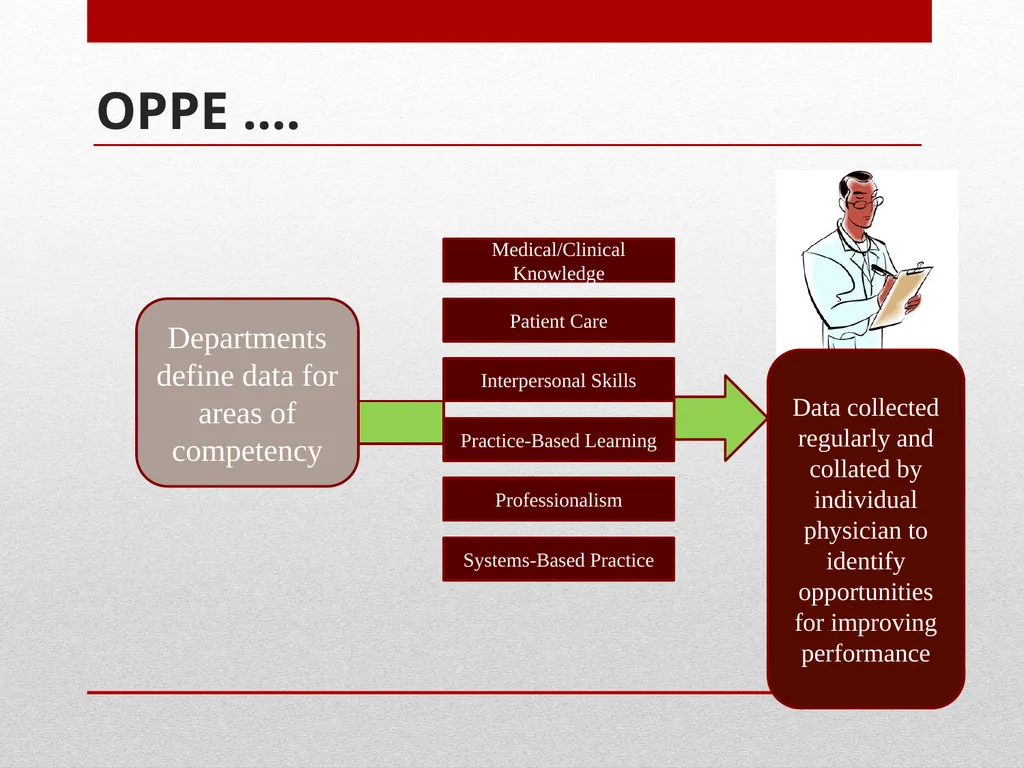
OPPE …. Departments define data for areas of competency Medical/Clinical Knowledge Patient Care Interpersonal Skills Practice-Based Learning Professionalism Systems-Based Practice Data collected regularly and collated by individual physician to identify opportunities for improving performance<br>
40
OPPE Timeline for collection and reporting
All practitioners with clinical privileges
Every 3 to 6 months (discretion)
No less than every 9 months<br>
All practitioners with clinical privileges
Every 3 to 6 months (discretion)
No less than every 9 months<br>
41
OPPE Indicators for Review Type of data to be collected and related thresholds or triggers is determined by medical staff committees/departments & approved by MEC
Indicators may changes as appropriate
Reviewed annually
Do not limit data collection to negative/outlier trending data – consider good performance data<br>
Indicators may changes as appropriate
Reviewed annually
Do not limit data collection to negative/outlier trending data – consider good performance data<br>
42
OPPE Indicators for Review Department selects 3 to 5 specialty-specific indicators
MEC selects general indicators applicable to all practitioners
Consider using ACGME “General Competencies”
Patient care
Medical/clinical knowledge
Practice-based learning and improvement
Interpersonal and communication skills
Professionalism
Systems-based practice<br>
MEC selects general indicators applicable to all practitioners
Consider using ACGME “General Competencies”
Patient care
Medical/clinical knowledge
Practice-based learning and improvement
Interpersonal and communication skills
Professionalism
Systems-based practice<br>
43
OPPE Indicators for Review Threshold/triggers for performance must be defined for select indicators
Triggers define unacceptable levels of performance
– may trigger FPPE<br>
Triggers define unacceptable levels of performance
– may trigger FPPE<br>
44
OPPE Indicators for Review Triggers to consider
Defined number of events occurring
Defined number of adverse outcomes
Elevated infection, mortality, complication rates
Sentinel events
Low admissions/procedures over extended time
Increased LOS compared to peers
Increased returns to surgery
Frequent unanticipated readmits for same issue
Patterns of unnecessary diagnostic testing
Failure to follow approved practice guidelines
“Examples of Performance Measures & Triggers”<br>
45
OPPE Results & Reporting Data Data are analyzed and reported to determine whether to continue, limit, or revoke any privilege(s)
Outcome of evaluation must be documented and maintained in the Practitioners quality file
At Completion of review period, OPPE results (practitioner profile report) is communicated to Practitioner & filed in quality file<br>
Outcome of evaluation must be documented and maintained in the Practitioners quality file
At Completion of review period, OPPE results (practitioner profile report) is communicated to Practitioner & filed in quality file<br>
46
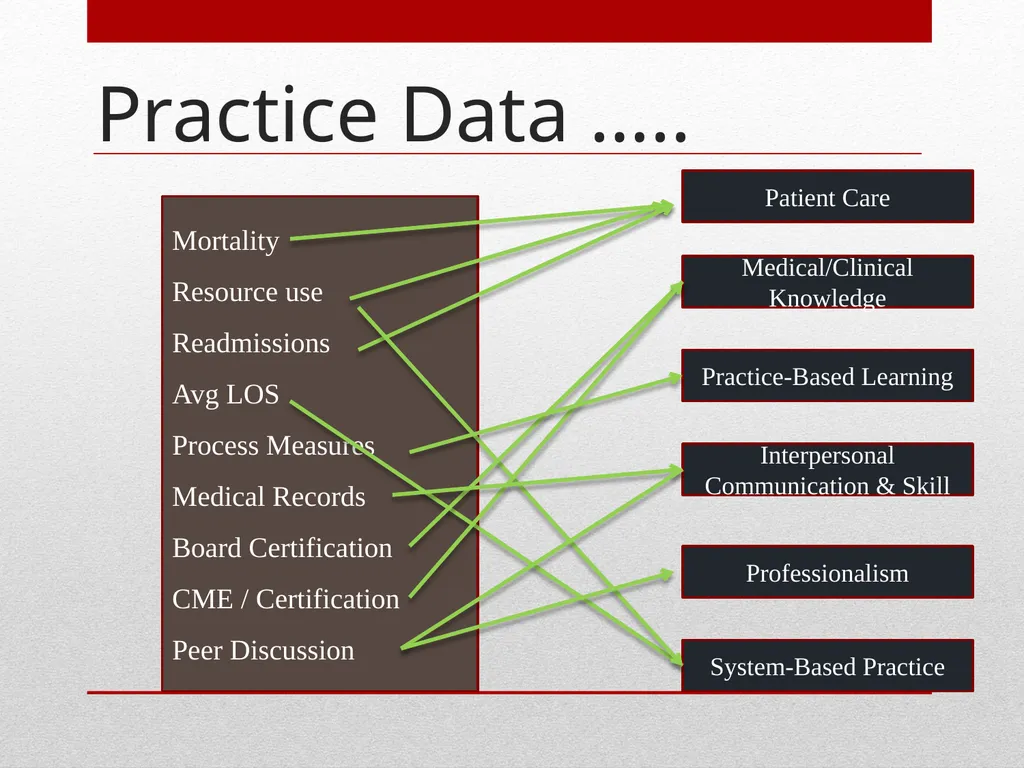
Practice Data ….. Patient Care Medical/Clinical Knowledge Practice-Based Learning Interpersonal Communication & Skill Professionalism System-Based Practice Mortality
Resource use
Readmissions
Avg LOS
Process Measures
Medical Records
Board Certification
CME / Certification
Peer Discussion<br>
Resource use
Readmissions
Avg LOS
Process Measures
Medical Records
Board Certification
CME / Certification
Peer Discussion<br>
47
Challenges to Implementation Identifying meaningful FPPE / OPPE
Education & compliance of Medical Staff
Most data collection is manual (FTE)
Software / IT support
Restructure & training of support staff
Urgency of implementation<br>
Education & compliance of Medical Staff
Most data collection is manual (FTE)
Software / IT support
Restructure & training of support staff
Urgency of implementation<br>
48
Steps toward change and conformance… Dept Chairs define FPPE / OPPE indicators
Obtain MEC & Board approval
Identify data collection methodology
Create data inventory / statistical analysis / reporting tool
Establish reporting chain of command
Write practice evaluation policy / plans<br>
Obtain MEC & Board approval
Identify data collection methodology
Create data inventory / statistical analysis / reporting tool
Establish reporting chain of command
Write practice evaluation policy / plans<br>
49
External Review MEC/COS/Dept Chair/Board may request external peer review
External Reviewer – Board Certified same specialty
Circumstances
Eligible reviewers unable to serve
No qualified Practitioner on Staff to review
Litigation risk
NOTE: Practitioner may not require Hospital to obtain external review<br>
External Reviewer – Board Certified same specialty
Circumstances
Eligible reviewers unable to serve
No qualified Practitioner on Staff to review
Litigation risk
NOTE: Practitioner may not require Hospital to obtain external review<br>
50
Review Form Type of data to be collected and related thresholds or triggers is determined by medical staff committees/departments & approved by MEC
Indicators may changes as appropriate
Reviewed annually
Do not limit data collection to negative/outlier trending data – consider good performance data<br>
Indicators may changes as appropriate
Reviewed annually
Do not limit data collection to negative/outlier trending data – consider good performance data<br>
51
What about temporary privileges? Temporary – Applicant
Application must be complete
May grant temporary privileges up to 120 days
FPPE applicable
Temporary – Non-applicant / Locums
Fits under urgent patient care needs
Verification of license, competence, NPDB, insurance
Temporary privileges to care for patient (non-applicant) or up to 15 days (Locums)<br>
52
Professional Performance Evaluation FPPE and OPPE<br>
53
THANK YOU! Contact Information:
John Pastrano, BBA, CPMSM, CPCS
Southern Belles and Beau Speaker Bureau
Email: John.Pastrano@tenethealth.com<br>
John Pastrano, BBA, CPMSM, CPCS
Southern Belles and Beau Speaker Bureau
Email: John.Pastrano@tenethealth.com<br>