04
Tracheostomy is indicated for a patient who requires emergent or elective airway management for:
prolonged ventilator dependence
acute upper airway obstruction
chronic upper airway obstruction<br>
05
Pathology for Tracheotomy or Tracheostomy Vocal cord paralysis
Neck surgery
Trauma
Prolonged intubation
Secretion management
Cannot intubate
Stridor due to tracheal blockage
Sleep apnea<br>
06
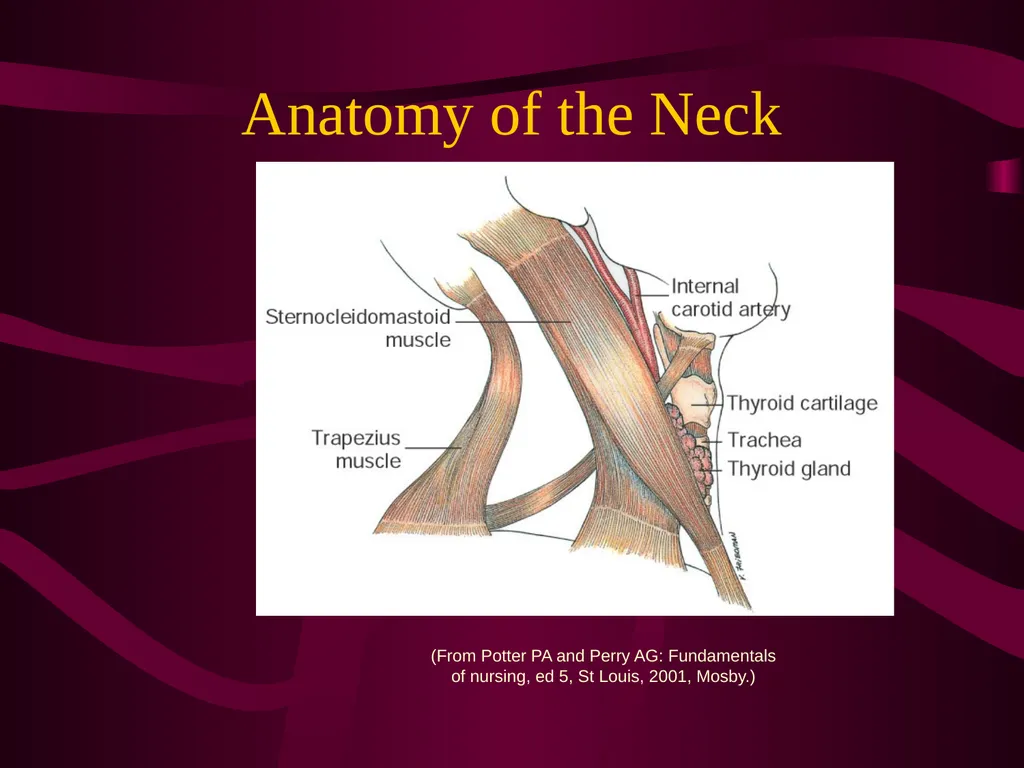
Anatomy of the Neck (From Potter PA and Perry AG: Fundamentals of nursing, ed 5, St Louis, 2001, Mosby.)<br>
07
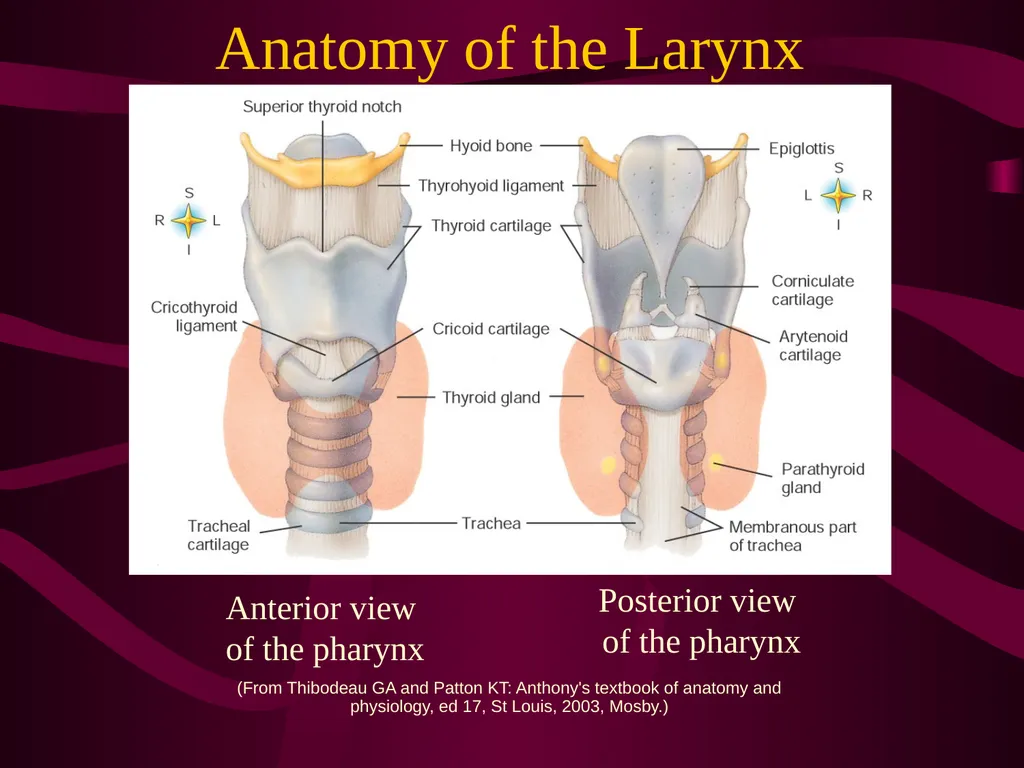
Anatomy of the Larynx Anterior view �of the pharynx Posterior view �of the pharynx (From Thibodeau GA and Patton KT: Anthony's textbook of anatomy and physiology, ed 17, St Louis, 2003, Mosby.)<br>
08
Anesthesia General
Local<br>
09
Medications Local anesthetic: Lidocaine or bupivicaine with or without epinephrine
Antibiotic irrigation<br>
10
Positioning Supine
Shoulder roll
Donut headrest
Pillow under knees
Safety strap<br>
11
Prep End of chin to midchest and bedsheet to bedsheet
Prep of choice: Duraprep, betadine scrub and/or paint<br>
12
Draping Towels
Small fenestrated sheet (Pediatric lap sheet)<br>
13
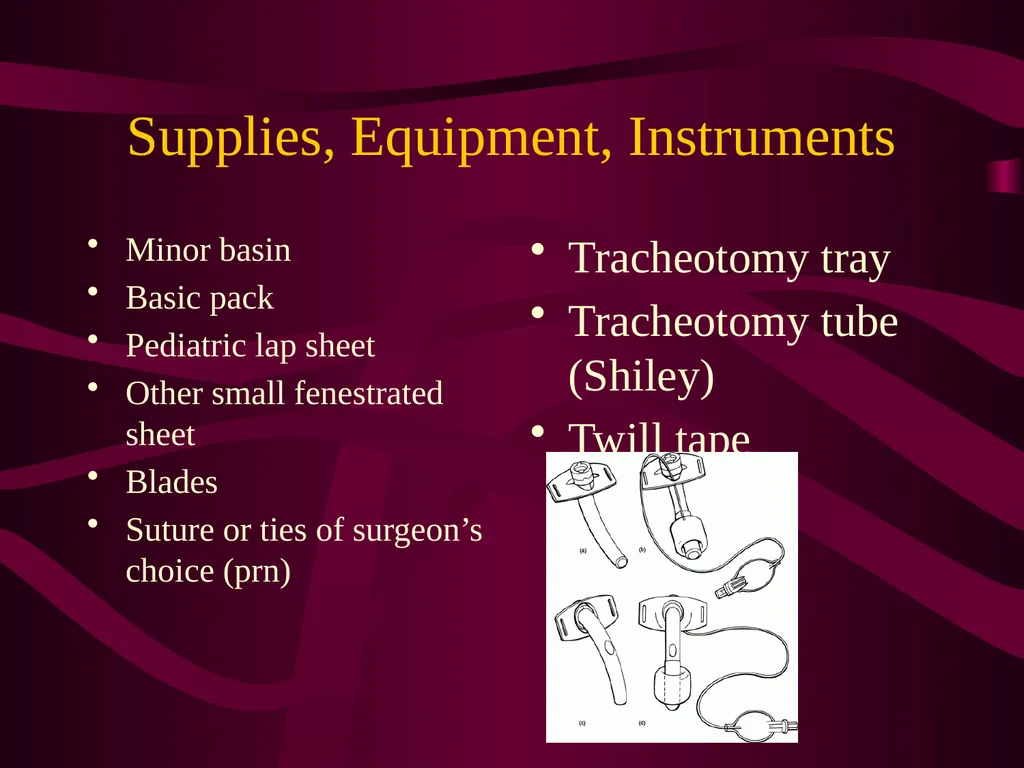
Supplies, Equipment, Instruments Minor basin
Basic pack
Pediatric lap sheet
Other small fenestrated sheet
Blades
Suture or ties of surgeon’s choice (prn) Tracheotomy tray
Tracheotomy tube (Shiley)
Twill tape<br>
14
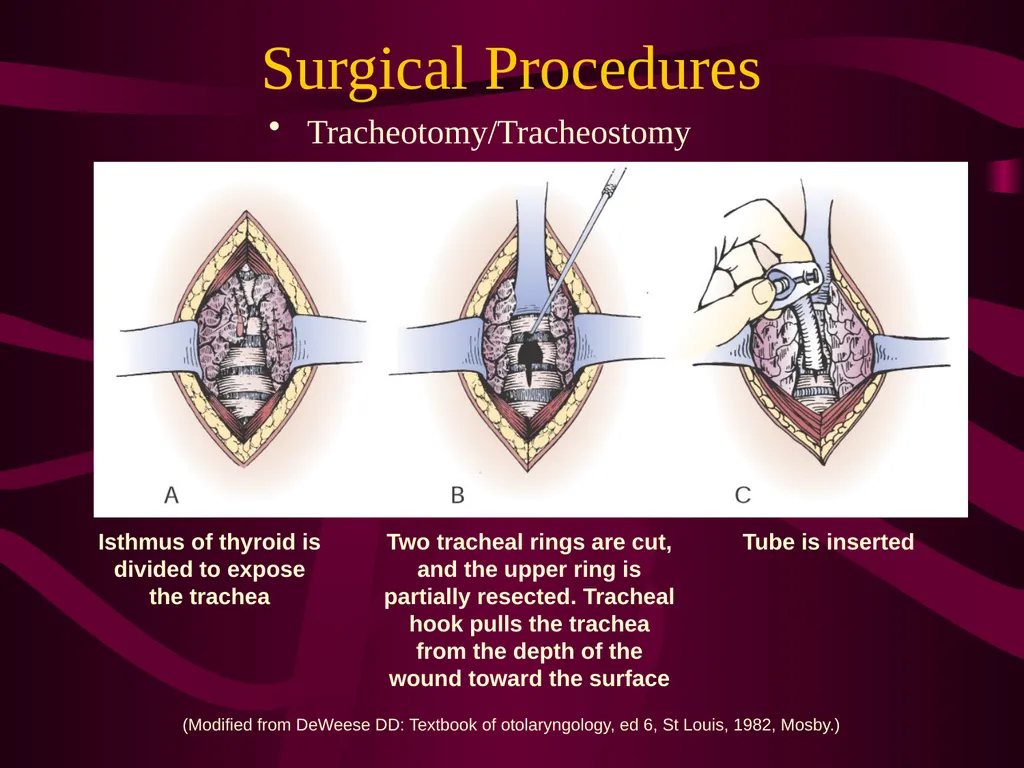
Surgical Procedures Tracheotomy/Tracheostomy Isthmus of thyroid is divided to expose�the trachea Tube is inserted Two tracheal rings are cut, and the upper ring is partially resected. Tracheal hook pulls the trachea from the depth of the wound toward the surface (Modified from DeWeese DD: Textbook of otolaryngology, ed 6, St Louis, 1982, Mosby.)<br>
15
Operative Sequence Discussion
http://video.google.com/videoplay?docid=261546049131841443&q=tracheostomy&total=37&start=0&num=10&so=0&type=search&plindex=0<br>
16
Considerations Will make sure obturator goes with patient to PACU or ICU
Complications: hemorrhage, infection, damage to other structures<br>
17
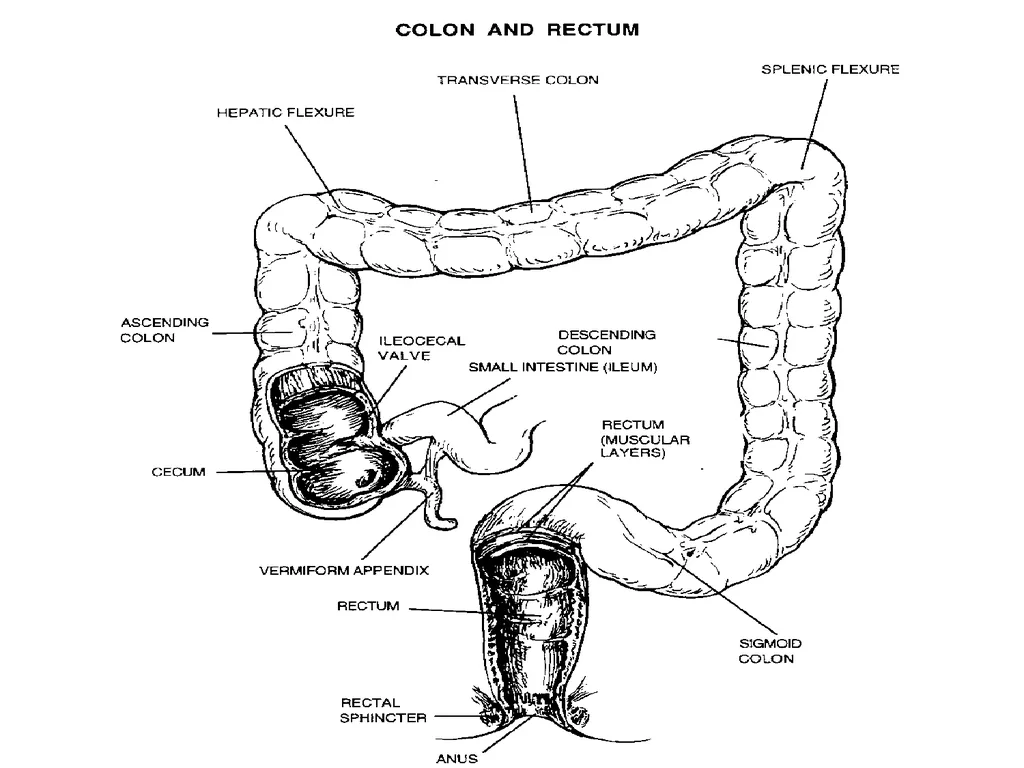
Large Intestine (Colon) Anatomy Look to page 395-404 in ST<br>
18
Appendectomy
Removal of the appendix
Appendicitis
Inflammation/infection of the appendix
Acute condition
Urgent procedure
Becomes emergent procedure if ruptures
Rupture leads to peritonitis which untreated leads to death
Sometimes Removed as Prophylactic Procedure (Incidental Appendectomy) in addition to other lower abdominal surgical procedures<br>
19
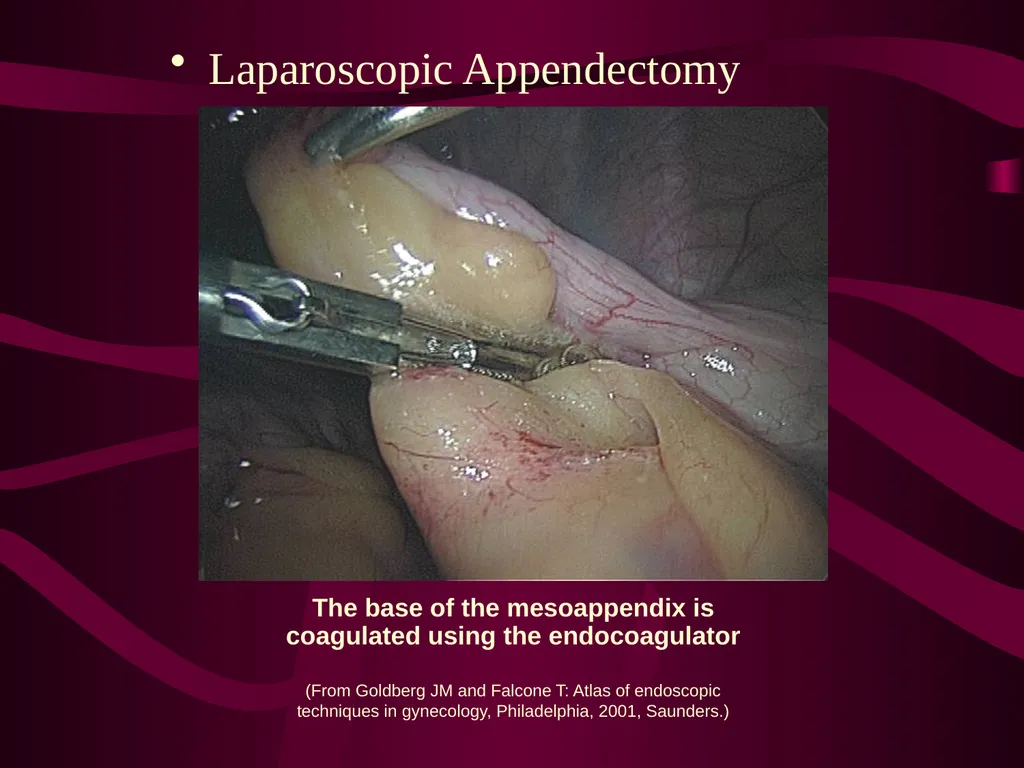
Laparoscopic Appendectomy The base of the mesoappendix is coagulated using the endocoagulator (From Goldberg JM and Falcone T: Atlas of endoscopic techniques in gynecology, Philadelphia, 2001, Saunders.)<br>
20
The appendix is attached to the mesoappendix, which is divided with scissors or ESU and ligated with vessel clips or surgical stapler<br>
21
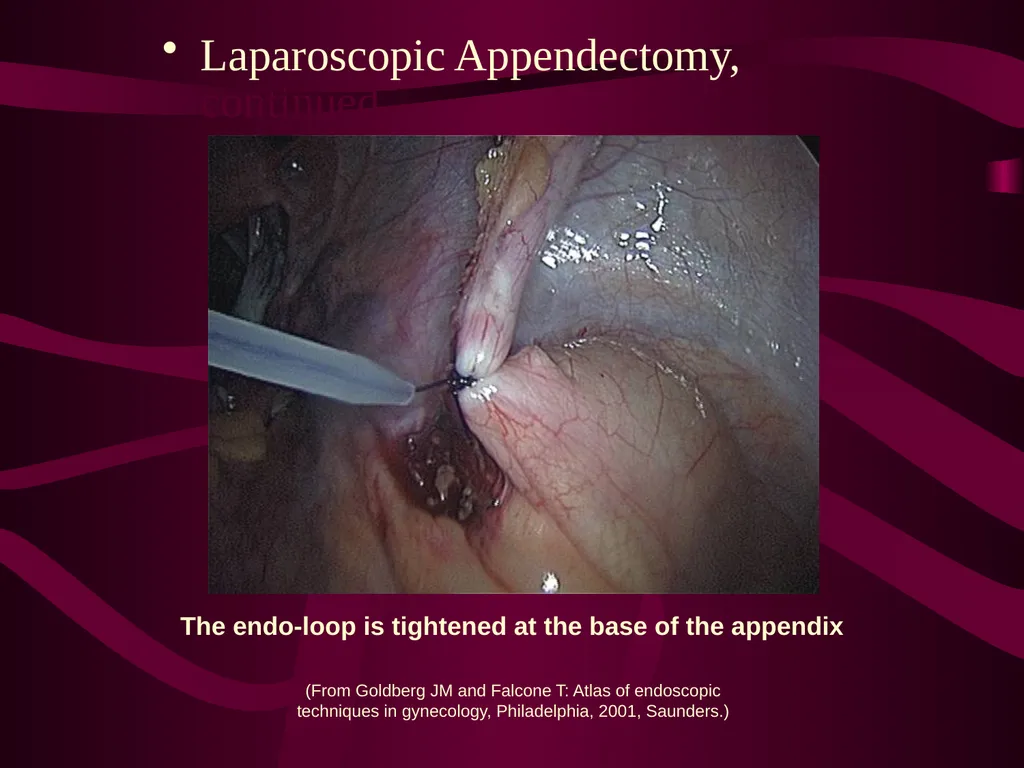
Laparoscopic Appendectomy, continued (From Goldberg JM and Falcone T: Atlas of endoscopic techniques in gynecology, Philadelphia, 2001, Saunders.) The endo-loop is tightened at the base of the appendix<br>
22
Once the appendix is mobilized, it can be amputated from the cecum
Two ties must be placed around the appendix between the lines of amputation<br>
23
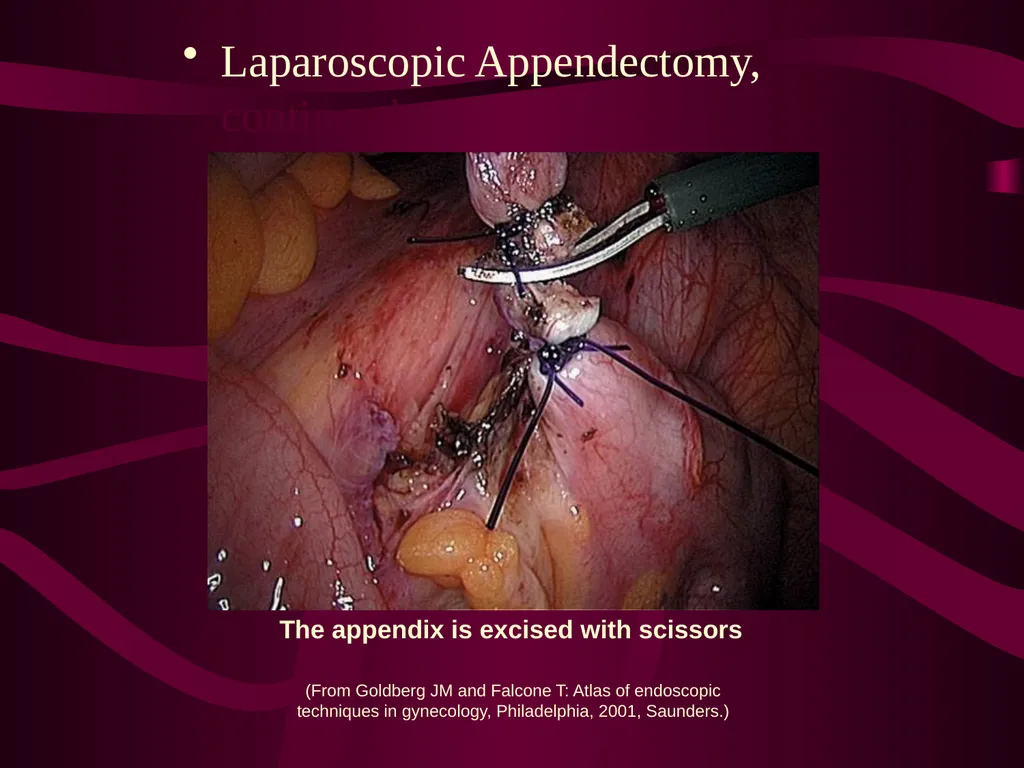
Laparoscopic Appendectomy, continued (From Goldberg JM and Falcone T: Atlas of endoscopic techniques in gynecology, Philadelphia, 2001, Saunders.) The appendix is excised with scissors<br>
24
The appendix is then transected with the ESU, scissors, or surgical stapler
The stapler provides additional security against leakage
The specimen is brought out of the abdomen with a specimen retrieval bag<br>
25
Loop technique: http://www.dailymotion.com/video/x403wh_lap-appendectomy_tech
Stapler technique: http://www.dailymotion.com/video/x4046e_lap-appendectomy-with-stapler_tech<br>