
Training package on active tuberculosis drug












Description: Training package on active tuberculosis drug safety monitoring and management (aDSM) 2023 3.2. Causality assessment: scales and methods Describe the main principles of causality assessment Identify the different levels of certainty when
Related Topics
Download Presentation
"Training package on active tuberculosis drug" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Training package on active tuberculosis drug safety monitoring and management (aDSM)
2023<br>
slide2. 3.2. Causality assessment:
scales and methods<br>
slide3. Describe the main principles of causality assessment
Identify the different levels of certainty when attributing an event to a suspected exposure Learning objectives By the end of this presentation, the participant is expected to be able to:<br>
slide4. Causality assessment (1) An integral part of clinical management
Evaluating the likelihood that a TB medicine was the causative agent of an observed adverse reaction forms part of clinical evaluation.
While the details of the systematic method of conducting causality assessment may not be familiar to the practitioner, the overall approach is not too different from the clinical practice followed when evaluating any patient on treatment.<br>
slide5. Causality assessment (2) The attribution (relationship or causality or drug related assessment) must be made
A physician or any other health care professional who has the right expertise describes the relationship between the adverse event and an exposure
This determination must be recorded both in the medical record as well as in the case report form
For aDSM, causality assessment should be made primarily at the country level and by consulting the relevant data sources close to where the event occurred<br>
slide6. Causality assessment (3) Is there a convincing relationship between the medicine and the event ?
Did the medicine actually cause the event ?
OR
Other TB medicines ?
Medicines for other diseases ?
Effect of the TB disease itself or co-morbidities?<br>
slide7. Causality assessment (4)
reaction versus event Adverse drug reactions (ADR): a response to a medicine which is noxious and unintended, and which occurs at doses normally used in humans
Adverse events (AE): Any untoward medical occurrence that may present during treatment with a pharmaceutical product, but which does not necessarily have a causal relationship with this treatment<br>
slide8. Is the time to onset of the event compatible with the suspected cause (plausible time-frame) ?
Did the event occur after the start of some other medicine or new illness?
Is the event plausible given what is known about the drug?
Is there any other possible cause for the event?
What is the response to withdrawal of the medicine
(dechallenge)?
What is the response to rechallenge, if applicable? Causality assessment (5) main things to look out for<br>
slide9. Medical history (incl. concomitant disease)
Other risk factors (social factors, alcohol use, substance abuse, etc.)
Details of drugs taken : names, doses, routes
Start and stop dates and indications for use
Description of adverse event, including clinical description, laboratory results, and date of onset / end
Evolution of event, severity, seriousness, outcome Key data elements for causality assessment<br>
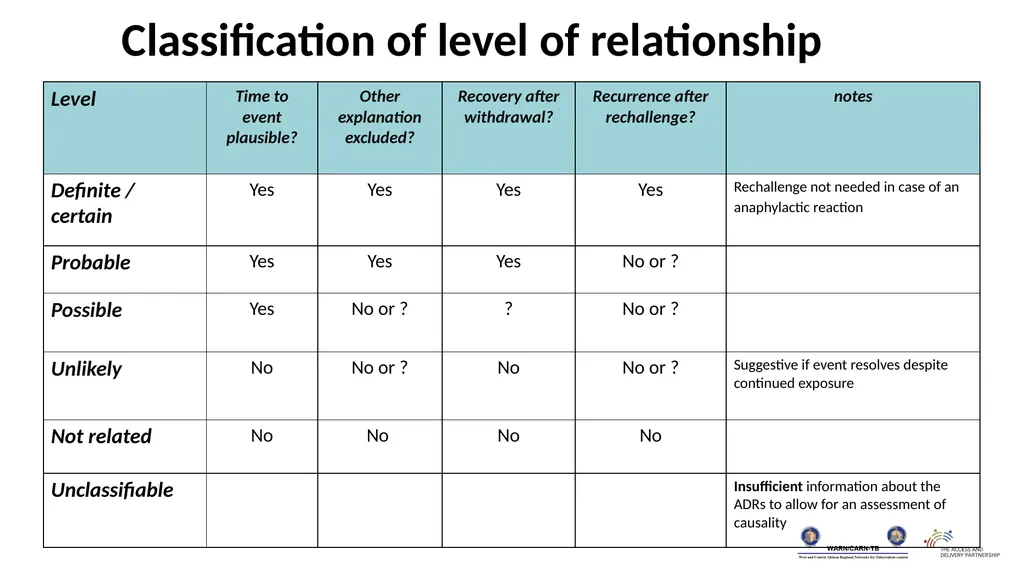
slide10. Classification of level of relationship<br>
slide11. Inference on the grade of the relationship<br>
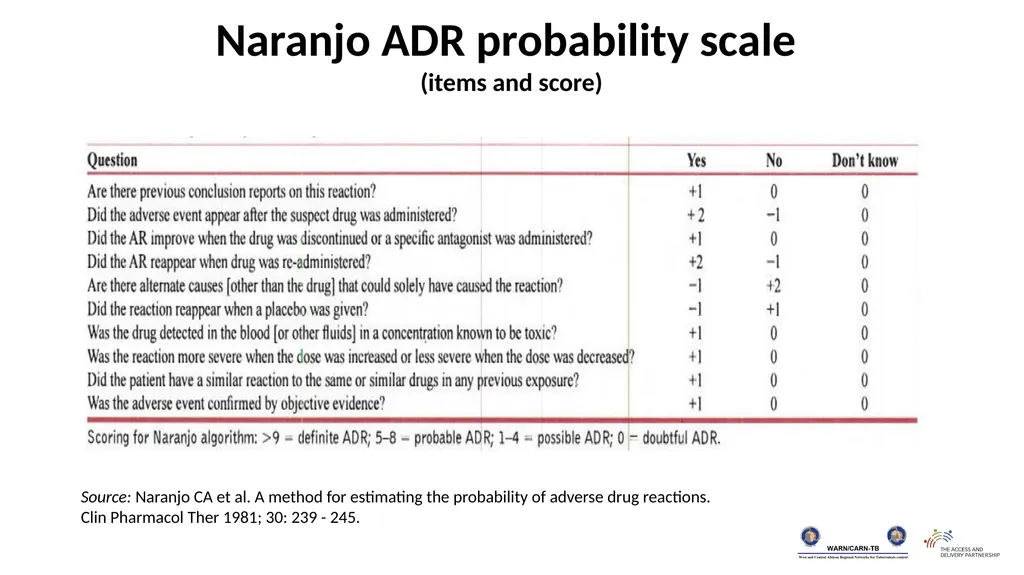
slide12. Naranjo ADR probability scale
(items and score) Source: Naranjo CA et al. A method for estimating the probability of adverse drug reactions. Clin Pharmacol Ther 1981; 30: 239 - 245.<br>
slide13. WHO-UMC system Practical tool for the assessment of case reports
Combined assessment taking into account
clinical-pharmacological aspects of the case history
the quality of the documentation
Other criteria such as previous knowledge and statistical chance play a less prominent role as to facilitate detection of unknown and unexpected adverse drug reactions
Source: http://who-umc.org/Graphics/24734.pdf<br>
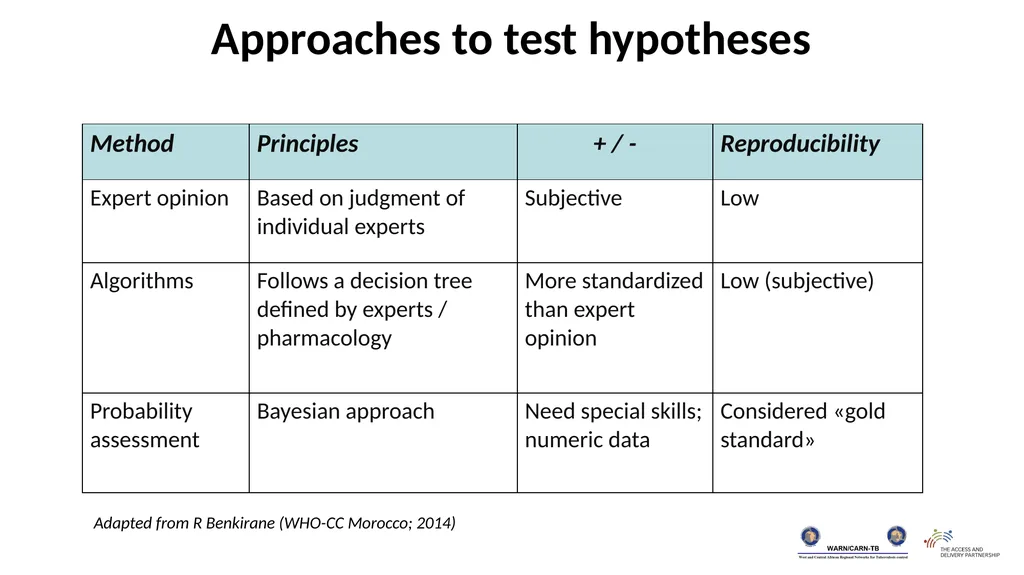
slide14. Approaches to test hypotheses Adapted from R Benkirane (WHO-CC Morocco; 2014)<br>
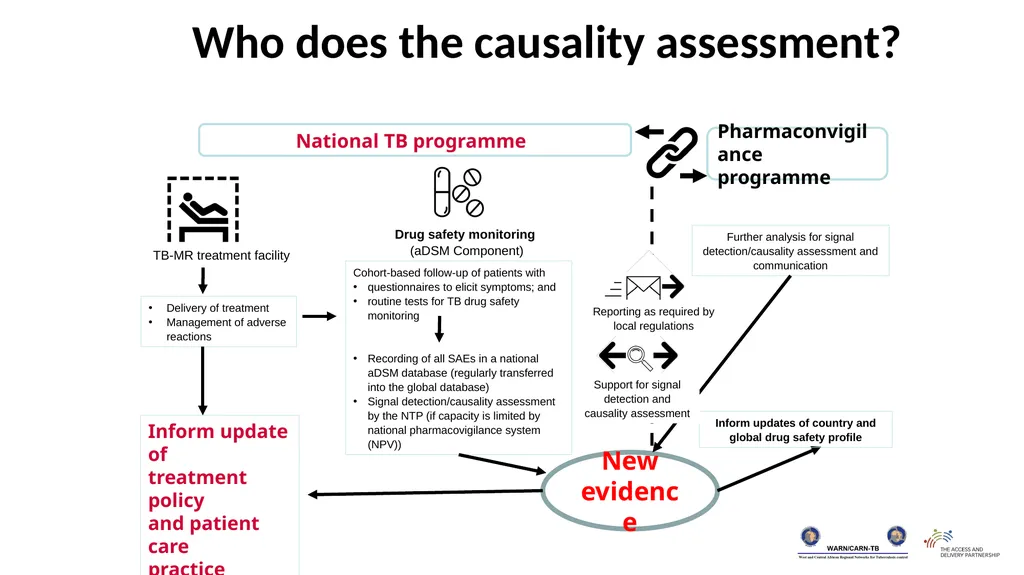
slide15. National TB programme TB-MR treatment facility Delivery of treatment
Management of adverse reactions Inform update of
treatment policy
and patient care
practice
(as per PMDT guidance) Drug safety monitoring
(aDSM Component) Cohort-based follow-up of patients with
questionnaires to elicit symptoms; and
routine tests for TB drug safety monitoring
Recording of all SAEs in a national aDSM database (regularly transferred into the global database)
Signal detection/causality assessment by the NTP (if capacity is limited by national pharmacovigilance system (NPV)) Pharmaconvigilance
programme Further analysis for signal detection/causality assessment and communication New
evidence Reporting as required by local regulations Inform updates of country and global drug safety profile Support for signal detection and causality assessment Who does the causality assessment?<br>
slide16. Conclusions An attempt to attribute an event to a cause is a basic principle of monitoring and clinical management in aDSM
Attributing a relationship requires a systematic process and is one of the main reasons why data are collected in aDSM. The exercise is done by experts who are competent in therapeutics and toxicity
The causality assessment once done attributes a level of certainty between the event and the exposure, ranging from ‘certain’ to ‘unclassifiable’<br>
slide17. Acknowledgements
The development of the aDSM training material was funded by TDR as part of the Access and Delivery Partnership (ADP) with funding from the Government of Japan.
These training materials were put together in 2016 the WHO Task Force on aDSM with technical partners KNCV Tuberculosis Foundation, Management Sciences for Health (SIAPS), MSF, WHO GTB, and TDR.
The materials were updated in 2022-23 by Mahamadou Bassirou Souleymane (TDR consultant) with Marie-Eve Raguenaud (TDR), Branwen J Hennig (TDR), and Corinne Merle (TDR), and reviewed by Linh Nhat Nguyen (WHO/GTB), Medea Gegia (WHO/GTB), and Fuad Mirzayev (WHO/GTB).
We thank all members of the WARN/CARN-TB working group on aDSM who contributed to the development of the aDSM generic guidelines as well as the secretariat, particularly Dr Christ Houessinon: Disadidi Ambrioso, Esse Marius, Adomou Jamal Rouamba Ruffine, Haro Sougrimani, Koumbem Boureima, Nsanzerugeze Josélyne, Tollo Tollo Daniel Alphonse Désiré, Mpaba Minkat Théophile Mistral, Julie Abessolo, Ursule IDOKO, Tijan Baldeh , Wandifa Samateh, Tida S Kinteh, Alieu Wurie, Mardemn Yeasuen, Benjamin K. Quenneh, Cheick Oumar Bah, Kane El Hadj Malick, Aw Idriss, Mamoudou Hama Rachida, Gagara I. M. Assiatou, Katambé Balkissa, Seiyabatou Elh Saidou, Liombo Anastasie, Lunganyu Junior, Kitambala Sentime, Lula Yves , Habimana-Mucyo Yves, Migambi Patrick, dos Santos Brigite, Castro Vânia, Wadson Cruz, Gueye Aminata, Mukeh Fahnbulleh, Bailor Samuel, Manjo Lamin, Saleh Mahareb Abdoulaye, Haroun Saleh Naima, Mouhoudine Yerima, Kpelafia Silifa<br>
2023<br>
slide2. 3.2. Causality assessment:
scales and methods<br>
slide3. Describe the main principles of causality assessment
Identify the different levels of certainty when attributing an event to a suspected exposure Learning objectives By the end of this presentation, the participant is expected to be able to:<br>
slide4. Causality assessment (1) An integral part of clinical management
Evaluating the likelihood that a TB medicine was the causative agent of an observed adverse reaction forms part of clinical evaluation.
While the details of the systematic method of conducting causality assessment may not be familiar to the practitioner, the overall approach is not too different from the clinical practice followed when evaluating any patient on treatment.<br>
slide5. Causality assessment (2) The attribution (relationship or causality or drug related assessment) must be made
A physician or any other health care professional who has the right expertise describes the relationship between the adverse event and an exposure
This determination must be recorded both in the medical record as well as in the case report form
For aDSM, causality assessment should be made primarily at the country level and by consulting the relevant data sources close to where the event occurred<br>
slide6. Causality assessment (3) Is there a convincing relationship between the medicine and the event ?
Did the medicine actually cause the event ?
OR
Other TB medicines ?
Medicines for other diseases ?
Effect of the TB disease itself or co-morbidities?<br>
slide7. Causality assessment (4)
reaction versus event Adverse drug reactions (ADR): a response to a medicine which is noxious and unintended, and which occurs at doses normally used in humans
Adverse events (AE): Any untoward medical occurrence that may present during treatment with a pharmaceutical product, but which does not necessarily have a causal relationship with this treatment<br>
slide8. Is the time to onset of the event compatible with the suspected cause (plausible time-frame) ?
Did the event occur after the start of some other medicine or new illness?
Is the event plausible given what is known about the drug?
Is there any other possible cause for the event?
What is the response to withdrawal of the medicine
(dechallenge)?
What is the response to rechallenge, if applicable? Causality assessment (5) main things to look out for<br>
slide9. Medical history (incl. concomitant disease)
Other risk factors (social factors, alcohol use, substance abuse, etc.)
Details of drugs taken : names, doses, routes
Start and stop dates and indications for use
Description of adverse event, including clinical description, laboratory results, and date of onset / end
Evolution of event, severity, seriousness, outcome Key data elements for causality assessment<br>
slide10. Classification of level of relationship<br>
slide11. Inference on the grade of the relationship<br>
slide12. Naranjo ADR probability scale
(items and score) Source: Naranjo CA et al. A method for estimating the probability of adverse drug reactions. Clin Pharmacol Ther 1981; 30: 239 - 245.<br>
slide13. WHO-UMC system Practical tool for the assessment of case reports
Combined assessment taking into account
clinical-pharmacological aspects of the case history
the quality of the documentation
Other criteria such as previous knowledge and statistical chance play a less prominent role as to facilitate detection of unknown and unexpected adverse drug reactions
Source: http://who-umc.org/Graphics/24734.pdf<br>
slide14. Approaches to test hypotheses Adapted from R Benkirane (WHO-CC Morocco; 2014)<br>
slide15. National TB programme TB-MR treatment facility Delivery of treatment
Management of adverse reactions Inform update of
treatment policy
and patient care
practice
(as per PMDT guidance) Drug safety monitoring
(aDSM Component) Cohort-based follow-up of patients with
questionnaires to elicit symptoms; and
routine tests for TB drug safety monitoring
Recording of all SAEs in a national aDSM database (regularly transferred into the global database)
Signal detection/causality assessment by the NTP (if capacity is limited by national pharmacovigilance system (NPV)) Pharmaconvigilance
programme Further analysis for signal detection/causality assessment and communication New
evidence Reporting as required by local regulations Inform updates of country and global drug safety profile Support for signal detection and causality assessment Who does the causality assessment?<br>
slide16. Conclusions An attempt to attribute an event to a cause is a basic principle of monitoring and clinical management in aDSM
Attributing a relationship requires a systematic process and is one of the main reasons why data are collected in aDSM. The exercise is done by experts who are competent in therapeutics and toxicity
The causality assessment once done attributes a level of certainty between the event and the exposure, ranging from ‘certain’ to ‘unclassifiable’<br>
slide17. Acknowledgements
The development of the aDSM training material was funded by TDR as part of the Access and Delivery Partnership (ADP) with funding from the Government of Japan.
These training materials were put together in 2016 the WHO Task Force on aDSM with technical partners KNCV Tuberculosis Foundation, Management Sciences for Health (SIAPS), MSF, WHO GTB, and TDR.
The materials were updated in 2022-23 by Mahamadou Bassirou Souleymane (TDR consultant) with Marie-Eve Raguenaud (TDR), Branwen J Hennig (TDR), and Corinne Merle (TDR), and reviewed by Linh Nhat Nguyen (WHO/GTB), Medea Gegia (WHO/GTB), and Fuad Mirzayev (WHO/GTB).
We thank all members of the WARN/CARN-TB working group on aDSM who contributed to the development of the aDSM generic guidelines as well as the secretariat, particularly Dr Christ Houessinon: Disadidi Ambrioso, Esse Marius, Adomou Jamal Rouamba Ruffine, Haro Sougrimani, Koumbem Boureima, Nsanzerugeze Josélyne, Tollo Tollo Daniel Alphonse Désiré, Mpaba Minkat Théophile Mistral, Julie Abessolo, Ursule IDOKO, Tijan Baldeh , Wandifa Samateh, Tida S Kinteh, Alieu Wurie, Mardemn Yeasuen, Benjamin K. Quenneh, Cheick Oumar Bah, Kane El Hadj Malick, Aw Idriss, Mamoudou Hama Rachida, Gagara I. M. Assiatou, Katambé Balkissa, Seiyabatou Elh Saidou, Liombo Anastasie, Lunganyu Junior, Kitambala Sentime, Lula Yves , Habimana-Mucyo Yves, Migambi Patrick, dos Santos Brigite, Castro Vânia, Wadson Cruz, Gueye Aminata, Mukeh Fahnbulleh, Bailor Samuel, Manjo Lamin, Saleh Mahareb Abdoulaye, Haroun Saleh Naima, Mouhoudine Yerima, Kpelafia Silifa<br>