
Entamoeba histolytica MIC 25 Amebae are primitive











Description: Entamoeba histolytica MIC 25 Amebae are primitive unicellular microorganisms. Their life cycle is relatively simple and divided into two stages: the actively motile feeding stage (trophozoite) and the quiescent, resistant, infective stage
Related Topics
Download Presentation
"Entamoeba histolytica MIC 25 Amebae are primitive" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Entamoeba histolytica MIC 25<br>
slide2. Amebae are primitive unicellular microorganisms.
Their life cycle is relatively simple and divided into two stages: the actively motile feeding stage (trophozoite) and the quiescent, resistant, infective stage (cyst).
Replication is accomplished by binary fission (splitting the trophozoite) or by the development of numerous trophozoites within the mature multi- nucleated cyst.
Motility is accomplished by extension of a pseudopod (“false foot”), with extrusion of the cellular ectoplasm and then drawing up of the rest of the cell in a snail- like movement to meet this pseudopod.
The amebic trophozoites remain actively motile as long as the environment is favorable. The cyst form develops when the environmental temperature or moisture level drops.<br>
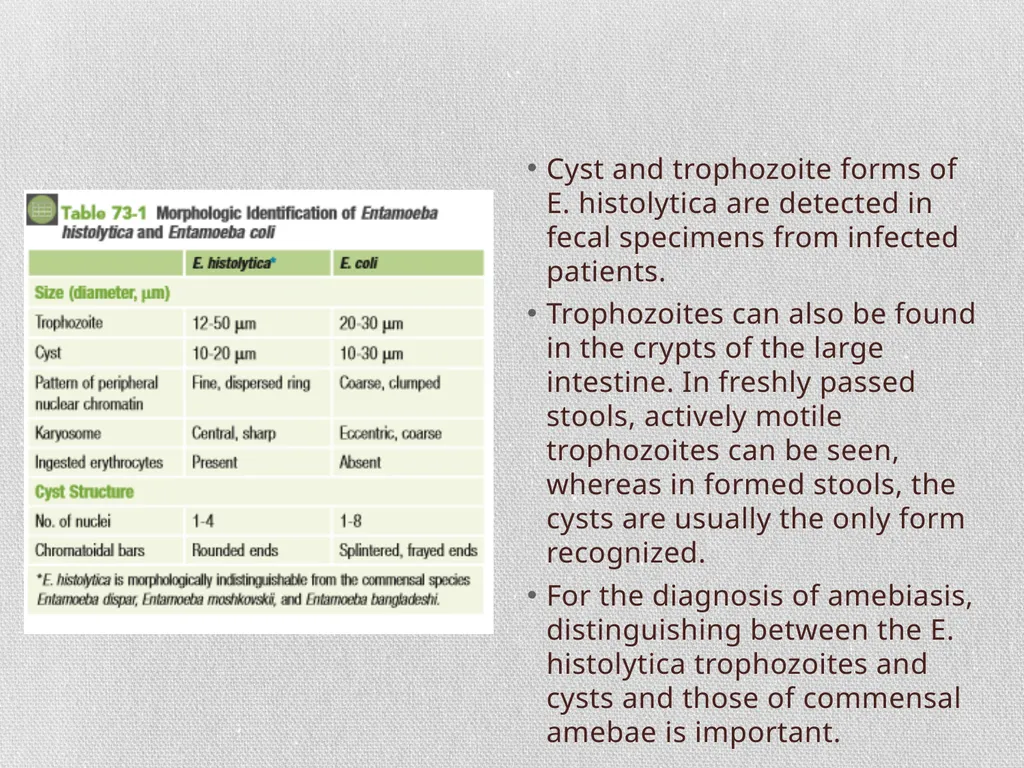
slide3. Cyst and trophozoite forms of E. histolytica are detected in fecal specimens from infected patients.
Trophozoites can also be found in the crypts of the large intestine. In freshly passed stools, actively motile trophozoites can be seen, whereas in formed stools, the cysts are usually the only form recognized.
For the diagnosis of amebiasis, distinguishing between the E. histolytica trophozoites and cysts and those of commensal amebae is important.<br>
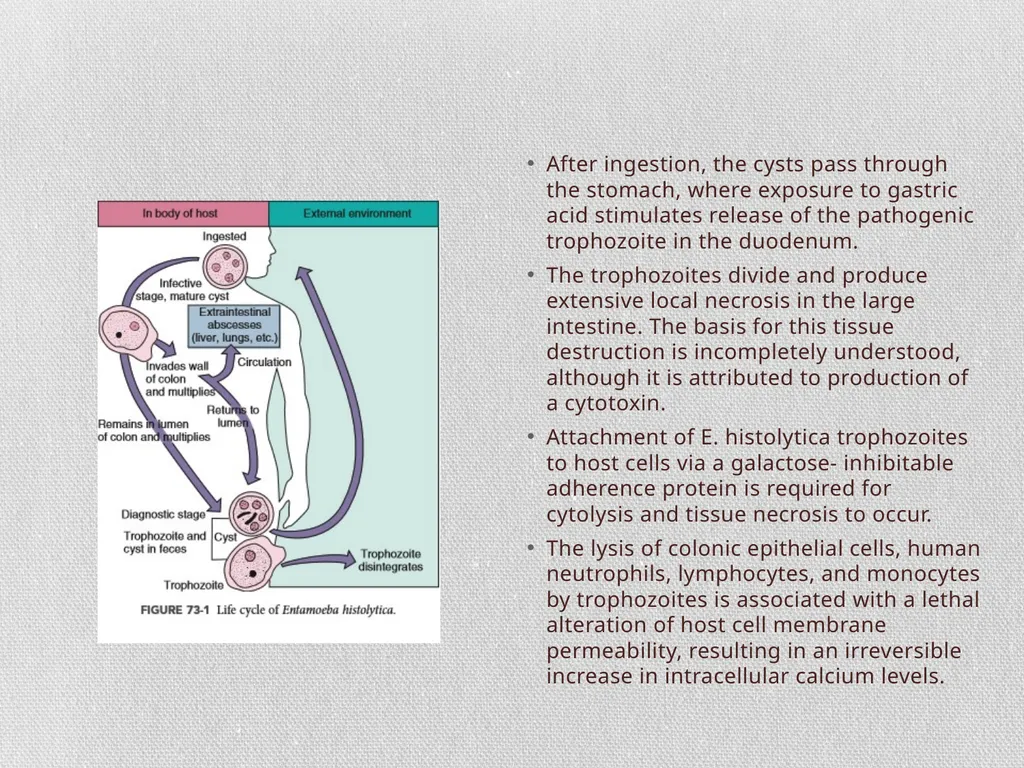
slide4. After ingestion, the cysts pass through the stomach, where exposure to gastric acid stimulates release of the pathogenic trophozoite in the duodenum.
The trophozoites divide and produce extensive local necrosis in the large intestine. The basis for this tissue destruction is incompletely understood, although it is attributed to production of a cytotoxin.
Attachment of E. histolytica trophozoites to host cells via a galactose- inhibitable adherence protein is required for cytolysis and tissue necrosis to occur.
The lysis of colonic epithelial cells, human neutrophils, lymphocytes, and monocytes by trophozoites is associated with a lethal alteration of host cell membrane permeability, resulting in an irreversible increase in intracellular calcium levels.<br>
slide5. The release of toxic neutrophil constituents after the lysis of neutrophils may contribute to tissue destruction.
Flask-shaped ulcerations of the intestinal mucosa are present with inflammation, hemorrhage, and secondary bacterial infection.
Invasion into the deeper mucosa with extension into the peritoneal cavity may occur. This can lead to secondary involvement of organs, primarily the liver but also the lungs, brain, and heart.
Extraintestinal amebiasis is associated with trophozoites. Amebae are found only in environments that have a low oxygen pressure, because the protozoa are killed by ambient oxygen concentrations Lectin binding, zymodeme analysis, genome deoxyribonucleic acid (DNA) analysis, and staining with specific monoclonal antibodies have been used as markers to identify invasive strains of E. histolytica. It is now recognized that the ameba morphologically identified as E. histolytica is actually four distinct species. The pathogenic species is E. histolytica, and the nonpathogenic species are E. dispar, E. moshkovskii, and E. bangladeshi.
The zymodeme profiles and biochemical, molecular, and immunologic differences are stable and support the existence of four species. Of note, these four species are morphologically indistinguishable from one another<br>
slide6. Epidemiology E. histolytica has a worldwide distribution.
Although it is found in cold areas such as Alaska, Canada, and Eastern Europe, its incidence is highest in tropical and subtropical regions that have poor sanitation and contaminated water. (The average prevalence- 10% to 15%, with as many as 50% of the population infected in some areas)
Many of the infected individuals are asymptomatic carriers who represent a reservoir for the spread of E. histolytica to others. The prevalence of infection in the United States is 1% to 2%.
Patients infected with E. histolytica pass noninfectious trophozoites and the infectious cysts in their stools.
The trophozoites cannot survive in the external environment or in transport through the stomach if ingested. Therefore the main source of water and food contamination is the asymptomatic carrier who passes cysts.
This is a particular problem in hospitals for the mentally ill, military and refugee camps, prisons, and crowded day-care centers. Flies and cockroaches can serve as mechanical vectors for the transmission of E. histolytica cysts.
Sewage containing cysts can contaminate water systems, wells, springs, and agricultural areas where human waste is used as fertilizer.
cysts can be transmitted by oral-anal sexual practices, with amebiasis prevalent in homosexual populations.
Direct trophozoite transmission in sexual encounters can produce cutaneous amebiasis.<br>
slide7. Clinical Syndromes The outcome of infection- carrier state, intestinal amebiasis, or extraintestinal amebiasis.
E. histolytica has a low virulence, the inoculum is low, or the patient’s immune system is intact, the organisms may reproduce, and cysts may be passed in stool specimens, with no clinical symptoms.
Detection of carriers of E. histolytica in areas with low endemicity is important for epidemiologic purposes Intestinal amebiasis: develop clinical symptoms related to localized tissue destruction in the large intestine (abdominal pain, cramping, and colitis with diarrhea)
More severe disease is characterized by numerous bloody stools per day
Systemic signs of infection (fever, leukocytosis, rigors (a sudden feeling of cold with shivering accompanied by a rise in temperature, often with copious sweating, especially at the onset or height of a fever) are present in patients with extraintestinal amebiasis
The liver is primarily involved because trophozoites in the blood are removed as they pass through this organ.
Abscess (tender, soft, swelling filled with pus, often surrounded by an area of skin coloured from pink to deep red) formation is common. The right lobe is most commonly involved. Pain over the liver, with hepatomegaly and elevation of the diaphragm, is observed.<br>
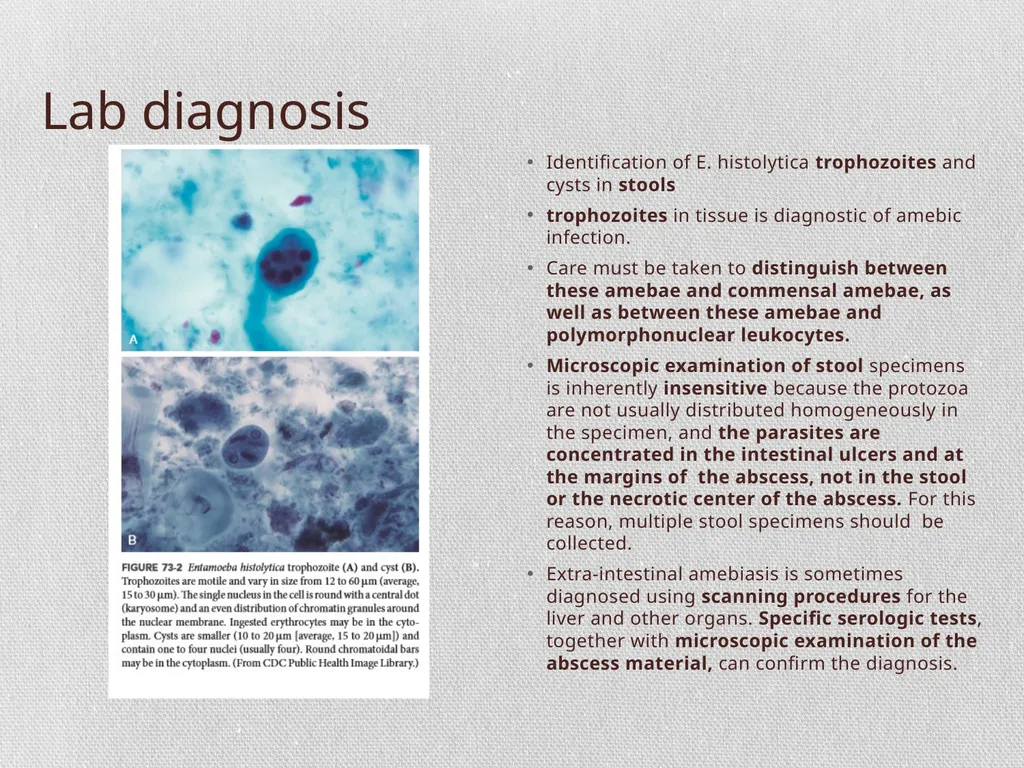
slide8. Lab diagnosis Identification of E. histolytica trophozoites and cysts in stools
trophozoites in tissue is diagnostic of amebic infection.
Care must be taken to distinguish between these amebae and commensal amebae, as well as between these amebae and polymorphonuclear leukocytes.
Microscopic examination of stool specimens is inherently insensitive because the protozoa are not usually distributed homogeneously in the specimen, and the parasites are concentrated in the intestinal ulcers and at the margins of the abscess, not in the stool or the necrotic center of the abscess. For this reason, multiple stool specimens should be collected.
Extra-intestinal amebiasis is sometimes diagnosed using scanning procedures for the liver and other organs. Specific serologic tests, together with microscopic examination of the abscess material, can confirm the diagnosis.<br>
slide9. Lab diagnosis Virtually all patients with hepatic amebiasis and most patients (>80%) with intestinal disease have positive serologic findings at the time of clinical presentation. This may be less useful in endemic areas where the prevalence of positive serologic results is higher.
Examinations of stool specimens are frequently negative in extraintestinal disease.
In addition to conventional microscopic and serologic tests, researchers have developed several immunologic tests for the detection of fecal antigen, as well as polymerase chain reaction (PCR) and DNA-probe assays for the detection of pathogenic strains of E. histolytica (versus nonpathogenic E. dispar and E. moshkovskii).
These newer diagnostic approaches are promising and are now commercially available.<br>
slide10. Treatment, Prevention, and Control Acute fulminating (coming on suddenly with great severity) amebiasis is treated with metronidazole, followed by iodoquinol, diloxanide furoate, or paromomycin.
Asymptomatic carriage can be eradicated with iodoquinol, diloxanide furoate, or paromomycin.
Because human infection results from ingestion of food or water contaminated with human feces or as a result of specific sexual practices, eliminating the cycle of infection requires introduction of adequate sanitation measures and education about the routes of transmission. Chlorination and filtration of water supplies may limit the spread of these and other enteric protozoal infections but are not possible in many developing countries.
Physicians should alert travellers to developing countries of the risks associated with consumption of water (including ice cubes), unpeeled fruits, and raw vegetables.
Water should be boiled and fruits and vegetables thoroughly cleaned before consumption.<br>
slide11. Trichomonas vaginalis Physiology and Structure
T. vaginalis- not an intestinal protozoan but rather the cause of urogenital infections.
The flagellate’s four flagella and short, undulating membrane- responsible for motility.
T. vaginalis
-exists only as a trophozoite
-found in the urethras and vaginas of women and the urethras and prostate glands of men.
Epidemiology
worldwide distribution
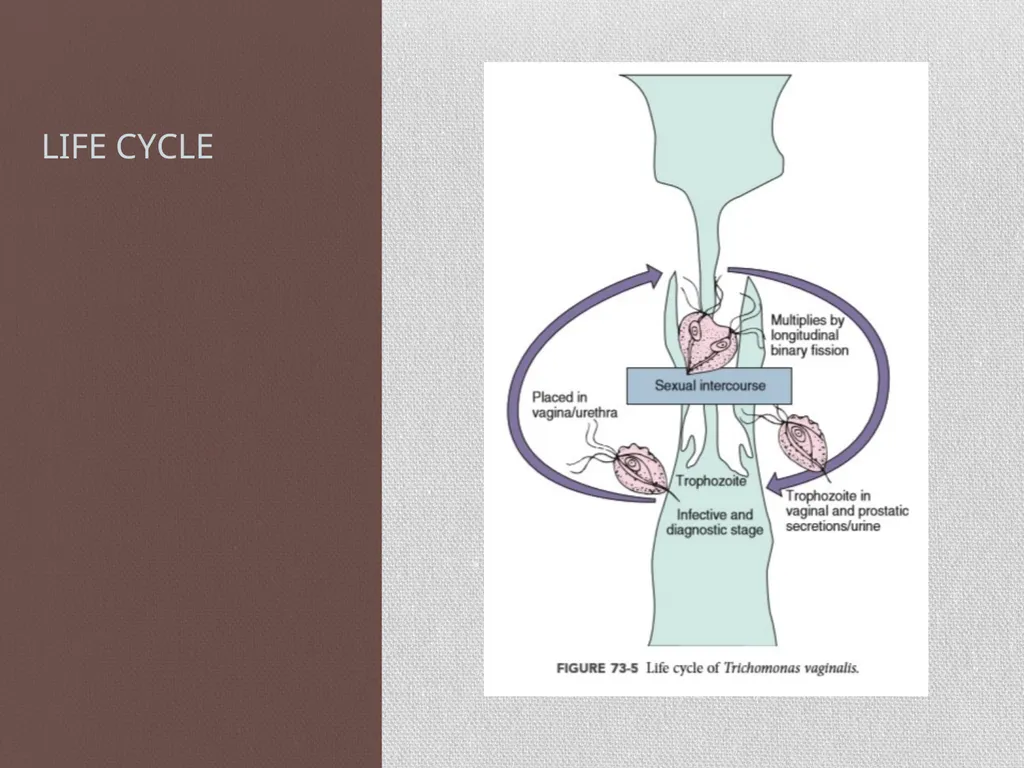
sexual intercourse -the primary mode of transmission
Occasionally, infections have been transmitted by fomites (toilet articles, clothing), although this transmission is limited by the lability of the trophozoite form.
Infants may be infected by passage through the mother’s infected birth canal.
The prevalence of this flagellate in developed countries is reported to be 5% to 20% in women and 2% to 10% in men.
Clinical Syndromes
Most infected women are asymptomatic or have a scant, watery vaginal discharge.
Vaginitis may occur, with more extensive inflammation and erosion of the epithelial lining that is associated with itching, burning, and painful urination.
Men are primarily asymptomatic carriers who serve as a reservoir for infections in women. However, men occasionally experience urethritis, prostatitis, and other urinary tract problems.<br>
slide12. LIFE CYCLE<br>
slide13. Laboratory Diagnosis
Diagnostic method of choice - Microscopic examination of vaginal or urethral discharge for characteristic trophozoites (Giemsa, Papanicolaou) or unstained smears can be examined.
The diagnostic yield may be improved by culturing the organism (93% sensitivity) or using monoclonal fluorescent antibody staining (86% sensitivity).
A nucleic acid probe assay is also available commercially.
Serologic tests may be useful in epidemiologic surveillance.<br>
slide14. Treatment, Prevention, and Control The drug of choice is metronidazole.
Both male and female sex partners must be treated to avoid reinfection.
Resistance to metronidazole has been reported and may require re-treatment with higher doses.
More recently, tinidazole has received FDA approval for treatment of trichomoniasis in adults and may be used as a first-line agent or for cases refractory to metronidazole.
Personal hygiene, avoidance of shared toilet articles and clothing, and safe sexual practices are important preventive actions.
Elimination of carriage in men is critical for eradication of disease.<br>
slide2. Amebae are primitive unicellular microorganisms.
Their life cycle is relatively simple and divided into two stages: the actively motile feeding stage (trophozoite) and the quiescent, resistant, infective stage (cyst).
Replication is accomplished by binary fission (splitting the trophozoite) or by the development of numerous trophozoites within the mature multi- nucleated cyst.
Motility is accomplished by extension of a pseudopod (“false foot”), with extrusion of the cellular ectoplasm and then drawing up of the rest of the cell in a snail- like movement to meet this pseudopod.
The amebic trophozoites remain actively motile as long as the environment is favorable. The cyst form develops when the environmental temperature or moisture level drops.<br>
slide3. Cyst and trophozoite forms of E. histolytica are detected in fecal specimens from infected patients.
Trophozoites can also be found in the crypts of the large intestine. In freshly passed stools, actively motile trophozoites can be seen, whereas in formed stools, the cysts are usually the only form recognized.
For the diagnosis of amebiasis, distinguishing between the E. histolytica trophozoites and cysts and those of commensal amebae is important.<br>
slide4. After ingestion, the cysts pass through the stomach, where exposure to gastric acid stimulates release of the pathogenic trophozoite in the duodenum.
The trophozoites divide and produce extensive local necrosis in the large intestine. The basis for this tissue destruction is incompletely understood, although it is attributed to production of a cytotoxin.
Attachment of E. histolytica trophozoites to host cells via a galactose- inhibitable adherence protein is required for cytolysis and tissue necrosis to occur.
The lysis of colonic epithelial cells, human neutrophils, lymphocytes, and monocytes by trophozoites is associated with a lethal alteration of host cell membrane permeability, resulting in an irreversible increase in intracellular calcium levels.<br>
slide5. The release of toxic neutrophil constituents after the lysis of neutrophils may contribute to tissue destruction.
Flask-shaped ulcerations of the intestinal mucosa are present with inflammation, hemorrhage, and secondary bacterial infection.
Invasion into the deeper mucosa with extension into the peritoneal cavity may occur. This can lead to secondary involvement of organs, primarily the liver but also the lungs, brain, and heart.
Extraintestinal amebiasis is associated with trophozoites. Amebae are found only in environments that have a low oxygen pressure, because the protozoa are killed by ambient oxygen concentrations Lectin binding, zymodeme analysis, genome deoxyribonucleic acid (DNA) analysis, and staining with specific monoclonal antibodies have been used as markers to identify invasive strains of E. histolytica. It is now recognized that the ameba morphologically identified as E. histolytica is actually four distinct species. The pathogenic species is E. histolytica, and the nonpathogenic species are E. dispar, E. moshkovskii, and E. bangladeshi.
The zymodeme profiles and biochemical, molecular, and immunologic differences are stable and support the existence of four species. Of note, these four species are morphologically indistinguishable from one another<br>
slide6. Epidemiology E. histolytica has a worldwide distribution.
Although it is found in cold areas such as Alaska, Canada, and Eastern Europe, its incidence is highest in tropical and subtropical regions that have poor sanitation and contaminated water. (The average prevalence- 10% to 15%, with as many as 50% of the population infected in some areas)
Many of the infected individuals are asymptomatic carriers who represent a reservoir for the spread of E. histolytica to others. The prevalence of infection in the United States is 1% to 2%.
Patients infected with E. histolytica pass noninfectious trophozoites and the infectious cysts in their stools.
The trophozoites cannot survive in the external environment or in transport through the stomach if ingested. Therefore the main source of water and food contamination is the asymptomatic carrier who passes cysts.
This is a particular problem in hospitals for the mentally ill, military and refugee camps, prisons, and crowded day-care centers. Flies and cockroaches can serve as mechanical vectors for the transmission of E. histolytica cysts.
Sewage containing cysts can contaminate water systems, wells, springs, and agricultural areas where human waste is used as fertilizer.
cysts can be transmitted by oral-anal sexual practices, with amebiasis prevalent in homosexual populations.
Direct trophozoite transmission in sexual encounters can produce cutaneous amebiasis.<br>
slide7. Clinical Syndromes The outcome of infection- carrier state, intestinal amebiasis, or extraintestinal amebiasis.
E. histolytica has a low virulence, the inoculum is low, or the patient’s immune system is intact, the organisms may reproduce, and cysts may be passed in stool specimens, with no clinical symptoms.
Detection of carriers of E. histolytica in areas with low endemicity is important for epidemiologic purposes Intestinal amebiasis: develop clinical symptoms related to localized tissue destruction in the large intestine (abdominal pain, cramping, and colitis with diarrhea)
More severe disease is characterized by numerous bloody stools per day
Systemic signs of infection (fever, leukocytosis, rigors (a sudden feeling of cold with shivering accompanied by a rise in temperature, often with copious sweating, especially at the onset or height of a fever) are present in patients with extraintestinal amebiasis
The liver is primarily involved because trophozoites in the blood are removed as they pass through this organ.
Abscess (tender, soft, swelling filled with pus, often surrounded by an area of skin coloured from pink to deep red) formation is common. The right lobe is most commonly involved. Pain over the liver, with hepatomegaly and elevation of the diaphragm, is observed.<br>
slide8. Lab diagnosis Identification of E. histolytica trophozoites and cysts in stools
trophozoites in tissue is diagnostic of amebic infection.
Care must be taken to distinguish between these amebae and commensal amebae, as well as between these amebae and polymorphonuclear leukocytes.
Microscopic examination of stool specimens is inherently insensitive because the protozoa are not usually distributed homogeneously in the specimen, and the parasites are concentrated in the intestinal ulcers and at the margins of the abscess, not in the stool or the necrotic center of the abscess. For this reason, multiple stool specimens should be collected.
Extra-intestinal amebiasis is sometimes diagnosed using scanning procedures for the liver and other organs. Specific serologic tests, together with microscopic examination of the abscess material, can confirm the diagnosis.<br>
slide9. Lab diagnosis Virtually all patients with hepatic amebiasis and most patients (>80%) with intestinal disease have positive serologic findings at the time of clinical presentation. This may be less useful in endemic areas where the prevalence of positive serologic results is higher.
Examinations of stool specimens are frequently negative in extraintestinal disease.
In addition to conventional microscopic and serologic tests, researchers have developed several immunologic tests for the detection of fecal antigen, as well as polymerase chain reaction (PCR) and DNA-probe assays for the detection of pathogenic strains of E. histolytica (versus nonpathogenic E. dispar and E. moshkovskii).
These newer diagnostic approaches are promising and are now commercially available.<br>
slide10. Treatment, Prevention, and Control Acute fulminating (coming on suddenly with great severity) amebiasis is treated with metronidazole, followed by iodoquinol, diloxanide furoate, or paromomycin.
Asymptomatic carriage can be eradicated with iodoquinol, diloxanide furoate, or paromomycin.
Because human infection results from ingestion of food or water contaminated with human feces or as a result of specific sexual practices, eliminating the cycle of infection requires introduction of adequate sanitation measures and education about the routes of transmission. Chlorination and filtration of water supplies may limit the spread of these and other enteric protozoal infections but are not possible in many developing countries.
Physicians should alert travellers to developing countries of the risks associated with consumption of water (including ice cubes), unpeeled fruits, and raw vegetables.
Water should be boiled and fruits and vegetables thoroughly cleaned before consumption.<br>
slide11. Trichomonas vaginalis Physiology and Structure
T. vaginalis- not an intestinal protozoan but rather the cause of urogenital infections.
The flagellate’s four flagella and short, undulating membrane- responsible for motility.
T. vaginalis
-exists only as a trophozoite
-found in the urethras and vaginas of women and the urethras and prostate glands of men.
Epidemiology
worldwide distribution
sexual intercourse -the primary mode of transmission
Occasionally, infections have been transmitted by fomites (toilet articles, clothing), although this transmission is limited by the lability of the trophozoite form.
Infants may be infected by passage through the mother’s infected birth canal.
The prevalence of this flagellate in developed countries is reported to be 5% to 20% in women and 2% to 10% in men.
Clinical Syndromes
Most infected women are asymptomatic or have a scant, watery vaginal discharge.
Vaginitis may occur, with more extensive inflammation and erosion of the epithelial lining that is associated with itching, burning, and painful urination.
Men are primarily asymptomatic carriers who serve as a reservoir for infections in women. However, men occasionally experience urethritis, prostatitis, and other urinary tract problems.<br>
slide12. LIFE CYCLE<br>
slide13. Laboratory Diagnosis
Diagnostic method of choice - Microscopic examination of vaginal or urethral discharge for characteristic trophozoites (Giemsa, Papanicolaou) or unstained smears can be examined.
The diagnostic yield may be improved by culturing the organism (93% sensitivity) or using monoclonal fluorescent antibody staining (86% sensitivity).
A nucleic acid probe assay is also available commercially.
Serologic tests may be useful in epidemiologic surveillance.<br>
slide14. Treatment, Prevention, and Control The drug of choice is metronidazole.
Both male and female sex partners must be treated to avoid reinfection.
Resistance to metronidazole has been reported and may require re-treatment with higher doses.
More recently, tinidazole has received FDA approval for treatment of trichomoniasis in adults and may be used as a first-line agent or for cases refractory to metronidazole.
Personal hygiene, avoidance of shared toilet articles and clothing, and safe sexual practices are important preventive actions.
Elimination of carriage in men is critical for eradication of disease.<br>