
Obstructive and restrictive Lung Disease Jed
























Description: Obstructive and restrictive Lung Disease Jed Wolpaw MD, M.Ed Outline Obstructive disease Upper airway Extrathoracic INtrathoracic Lower airwayParenchymal Restrictive disease Neurologic Muskuloskeletal Parenchymal Pleural and mediastinal
Related Topics
Download Presentation
"Obstructive and restrictive Lung Disease Jed" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. Obstructive and restrictive Lung Disease Jed Wolpaw MD, M.Ed<br>
slide2. Outline Obstructive disease
Upper airway
Extrathoracic
INtrathoracic
Lower airway/Parenchymal
Restrictive disease
Neurologic
Muskuloskeletal
Parenchymal
Pleural and mediastinal
other<br>
slide3. Obstructive disease: Upper airway<br>
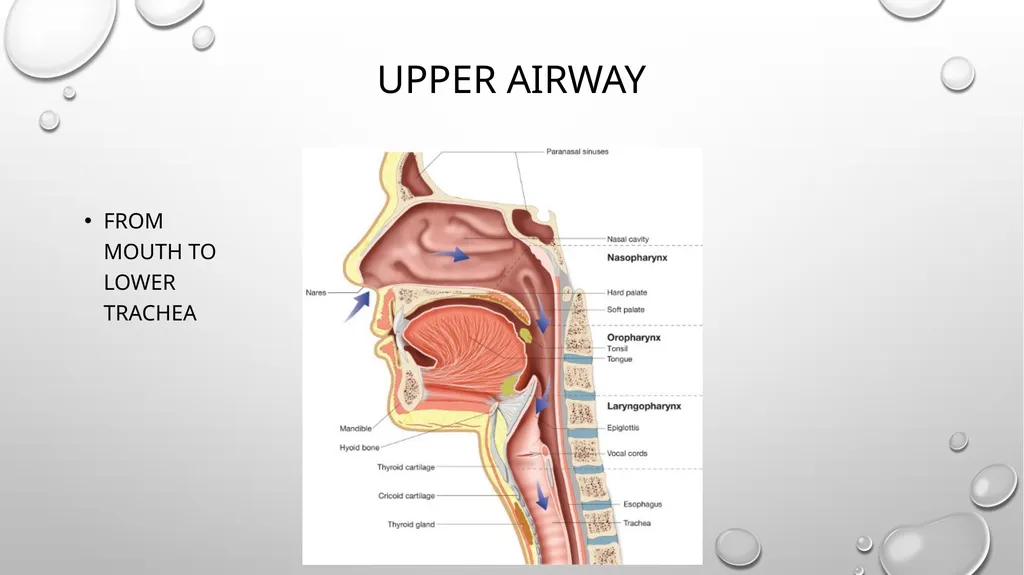
slide4. Upper airway From mouth to lower trachea<br>
slide5. Intra vs Extrathoracic Which lesion limits inspiratory flow the most?
A: Variable upper airway extrathoracic obstruction
B: Variable upper airway intrathoracic obstruction
C: COPD
D: Asthma<br>
slide6. Intra vs Extrathoracic Which lesion limits inspiratory flow the most?
A: Variable upper airway extrathoracic obstruction
B: Variable upper airway intrathoracic obstruction
C: COPD
D: Asthma<br>
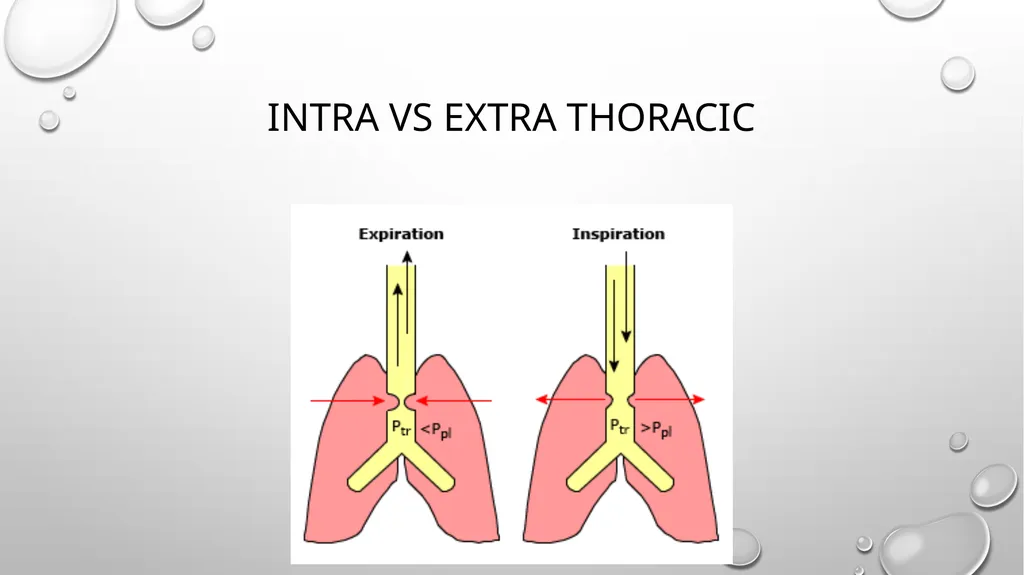
slide7. Intra vs extra thoracic<br>
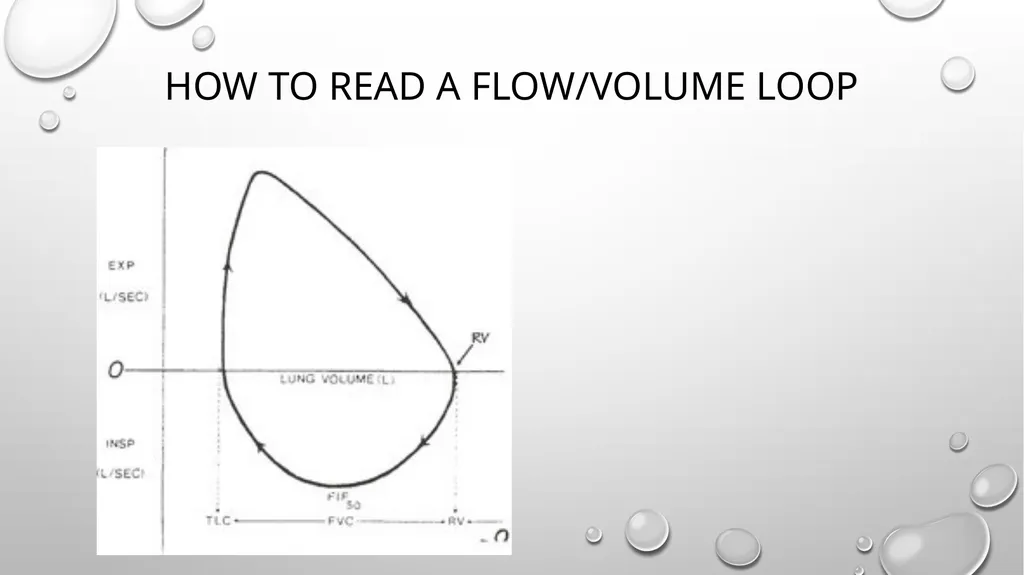
slide8. How to read a flow volume loop Where is:
-Flow?
-Volume?
-Inspiration?
-Expiration?
Where is:
-Total Lung Capacity?
-End Exhilation (residual volume)?<br>
slide9. How to read a flow/volume loop<br>
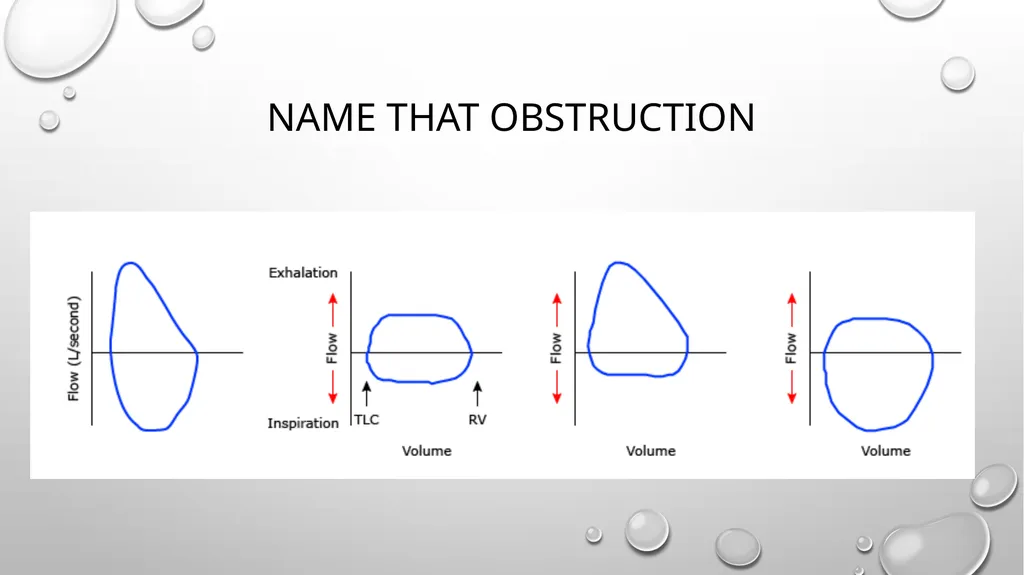
slide10. Name that obstruction<br>
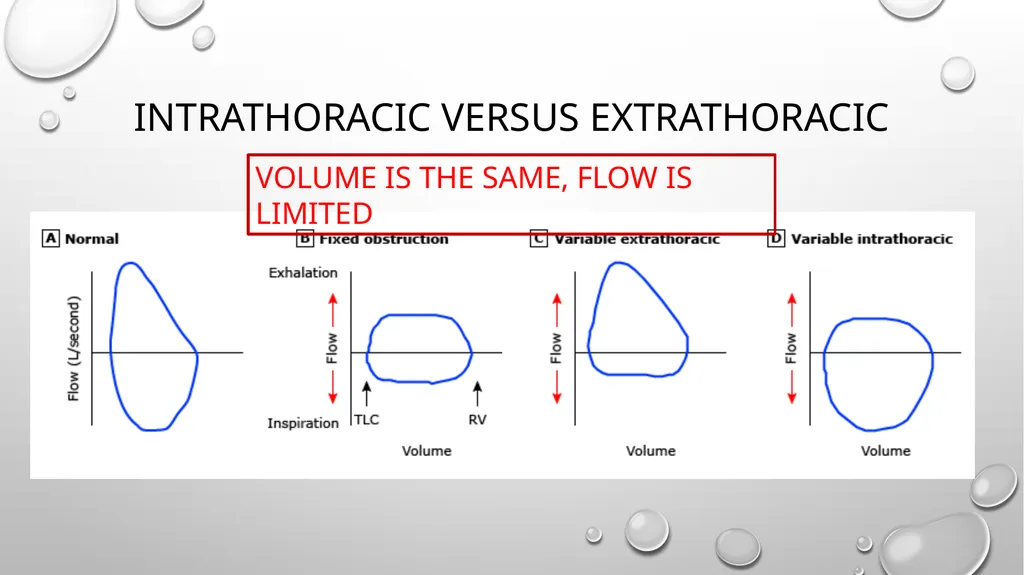
slide11. Intrathoracic versus extrathoracic VOLUME IS THE SAME, FLOW IS LIMITED<br>
slide12. Lesions at the thoracic inlet Starts intrathoracic Shifts to extrathoracic<br>
slide13. FEF50%/FIF50% Forced expiratory flow at 50% vital capacity/forced inspiratory flow at 50% VC
Extrathoracic: Increased to average 2.2 from normal 1
Intrathoracic: Decreased to average 0.32 from normal 1
Fixed obstruction: around 1<br>
slide14. Causes of upper airway obstruction: Intra or extrathoracic depending on location Congenital: tracheomalacia (upper), laryngomalacia, vocal cord abnormalities, vascular rings, laryngeal webs, scoliosis (can compress trachea)
Infectious: epiglottitis, peritonsillar abscess, Retropharyngeal abscess, Ludwig’s angina, Diptheria, Croup
Tumors
Trauma: Neck hematoma, fracture, Burns
Foreign body
Soft tissue: osa, nerve palsies<br>
slide15. Obstructive disease: lower airway/parenchymal<br>
slide16. Lower airway/Parenchymal obstructive diseases Asthma
Emphysema
Bronchitis
CF: bronchiectasis
Mediastinal masses<br>
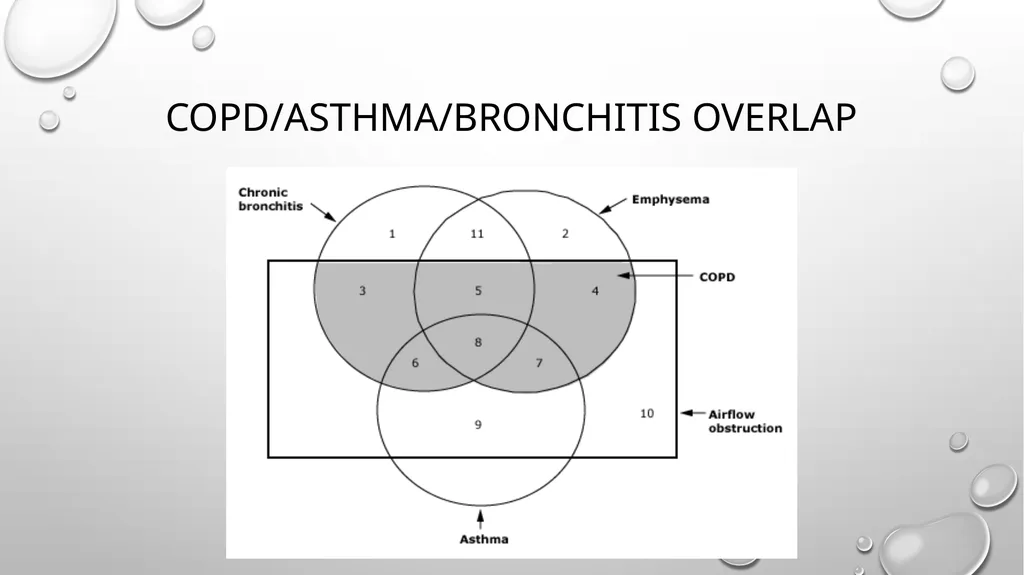
slide17. Mechanisms Officially these are no longer separated and are all copd (if asthma isn’t completely reversible
Asthma: thickened/tightened airway smooth muscle and excess mucous
CD4+ cells, T lymphocytes, eosinophils, IL-4 and IL-5
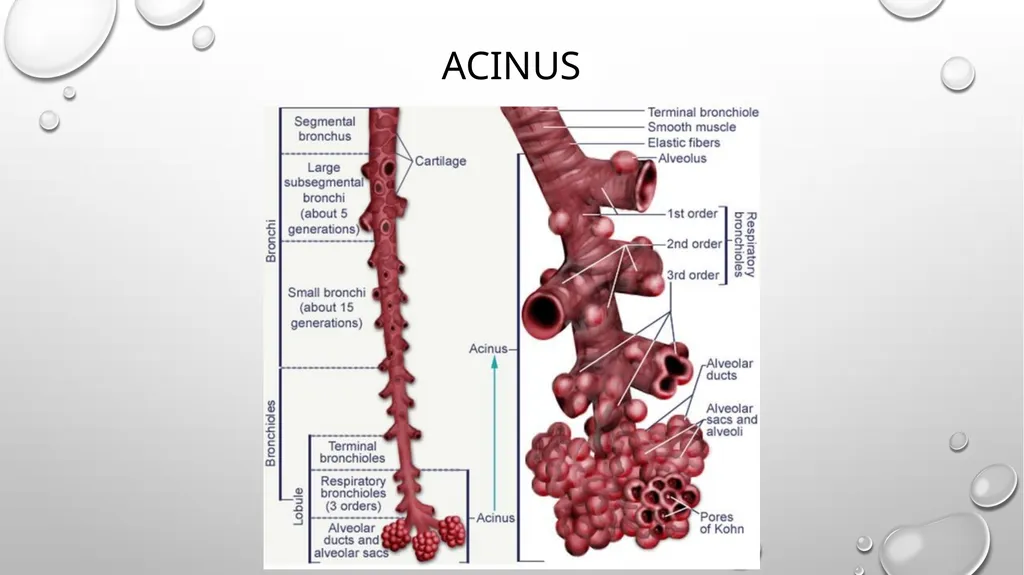
Emphysema: dilation/destruction of airway distal to terminal bronchiole (acinus)
CD8+ T-lymphocytes, neutrophils, and CD68+ monocytes/macrophages
Chronic bronchitis: Excess mucous, airway thickening
CD8+ T-lymphocytes, neutrophils, and CD68+ monocytes/macrophages<br>
slide18. COPD/Asthma/Bronchitis overlap<br>
slide19. acinus<br>
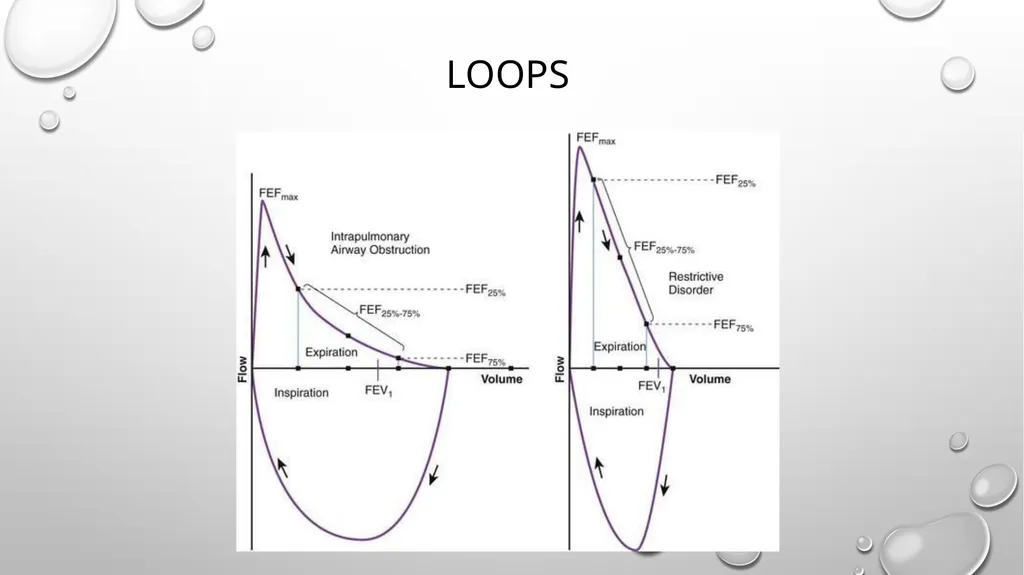
slide20. Loops<br>
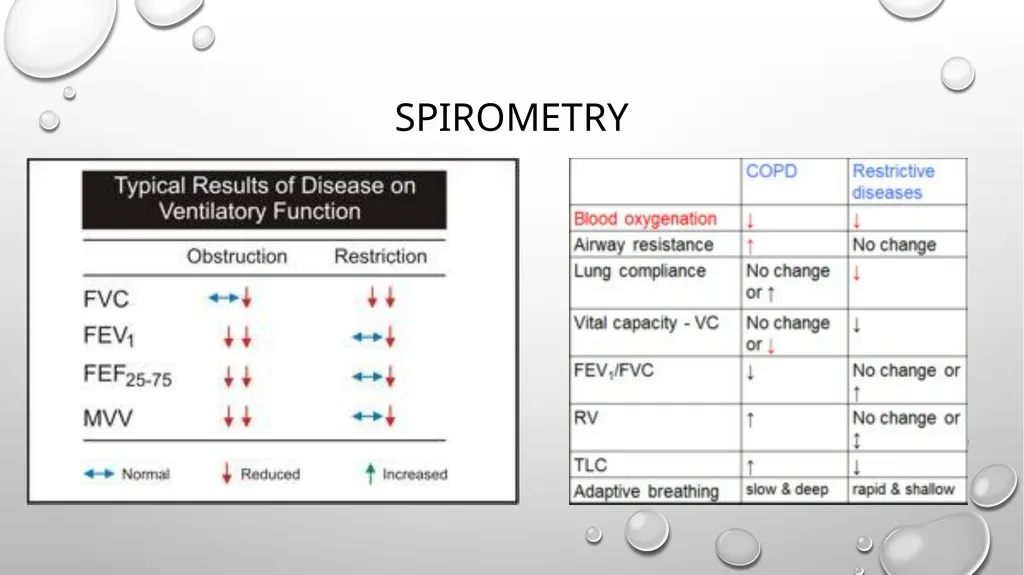
slide21. Spirometry FVC: Forced vital capacity
FEV1: Forced expiratory volume
FEV1/FVC: Ratio of these two
FEF 25-75%: Forced expiratory flow from 25-75% of vital capacity
Thought to be effort independent
Mvv: Maximum voluntary expiration (how much can one inhale and exhale in 1 minute)<br>
slide22. Spirometry<br>
slide23. DLCO (Diffusion capacity for carbon monoxide) Measures the ability of the lungs to transfer o2 to the blood
Obstructive disease
Correlates with degree of emphysema
Smokers with airway obstruction but normal dlco have bronchitis but not emphysema
Asthmatics have normal or high dlco
Cystic fibrosis: normal until very late in disease<br>
slide24. Cystic Fibrosis Mutation in CFTR leading to inability to transport chloride and sodium
Autosomal recessive
Multiple organ systems effected, we will focus on respiratory
Life expectancy average 39 years<br>
slide25. What is bronchiectasis A: Chronic airway infection
B: Recurrent pneumonia in cystic fibrosis
C: Dilation of airways due to wall destruction
D: being the subject of excess bronchoscopies<br>
slide26. What is bronchiectasis A: Chronic airway infection
B: Recurrent pneumonia in cystic fibrosis
C: Dilation of airways due to wall destruction
D: being the subject of excess bronchoscopies<br>
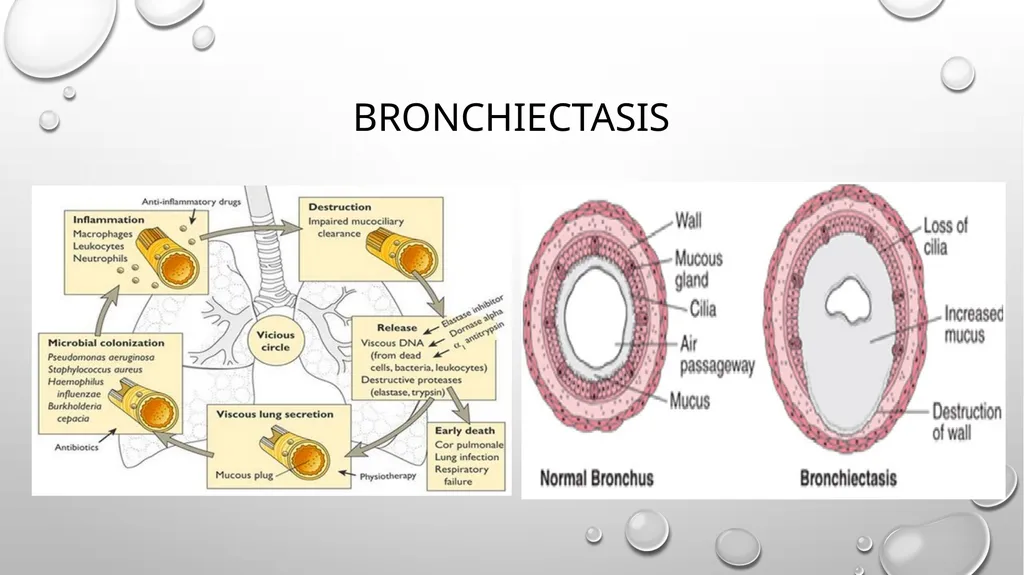
slide27. CF: Bronchiectasis Inability to transport Cl- and Na+ effectively leads to thickened secretions
Leads to colonization w organisms
Leads to massive inflammation from neutrophil degranulation
Leads to destruction of bronchus walldilation of airways
Leads to more mucous
Leads to more infection<br>
slide28. Bronchiectasis<br>
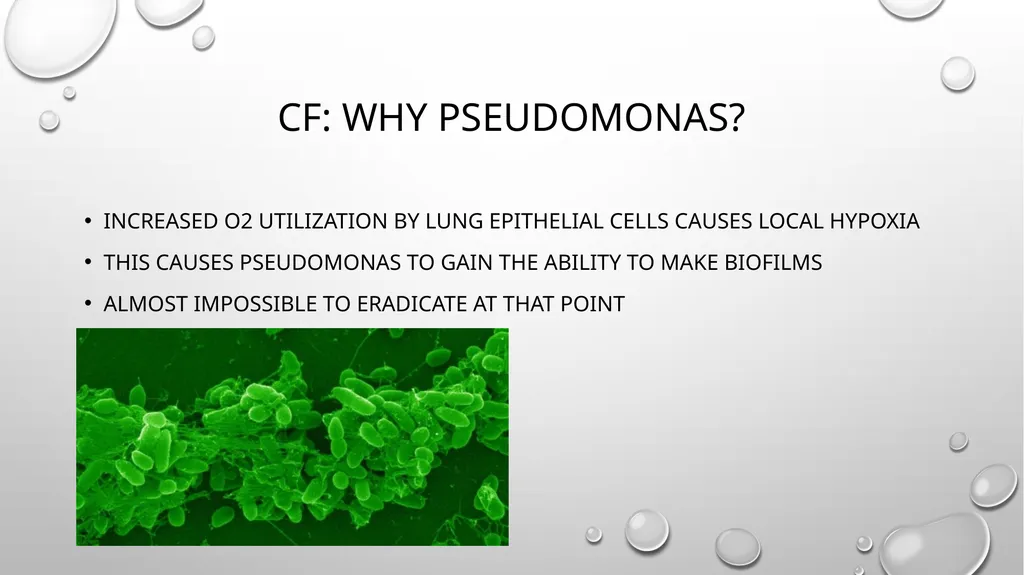
slide29. CF: Why pseudomonas? Increased o2 utilization by lung epithelial cells causes local hypoxia
This causes pseudomonas to gain the ability to make biofilms
Almost impossible to eradicate at that point<br>
slide30. Mediastinal masses Anterior, middle and posterior mediastinum
For airway compromise most significant is anterior
Most common: terrible t’s
Teratoma
Thymoma
Thyroid tissue
“terrible lymphoma”<br>
slide31. What is the safest way to induce a patient with an anterior mediastinal mass compressing the airway? A: RSI with Sux and etomidate
B: Asleep fiber
C: Awake fiber with surgeon standing by ready to perform tracheostomy
D: Awake fiber after cannulating groin vessels for ecmo<br>
slide32. What is the safest way to induce a patient with an anterior mediastinal mass compressing the airway? A: RSI with Sux and etomidate
B: Asleep fiber
C: Awake fiber with surgeon standing by ready to perform tracheostomy
D: Awake fiber after cannulating groin vessels for ecmo<br>
slide33. Mediastinal mass CXR<br>
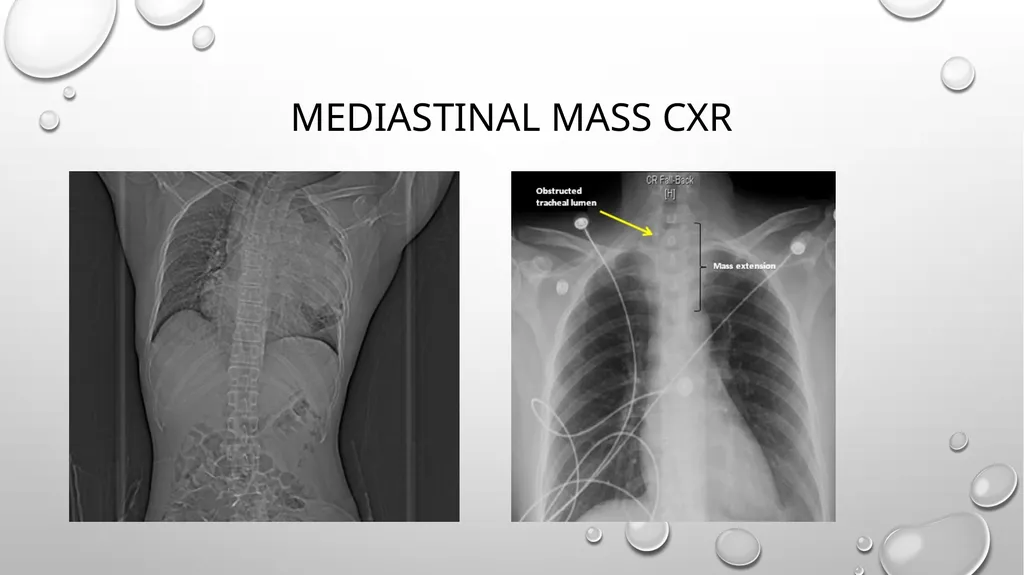
slide34. Mediastinal mass can cause both obstructive (compressing trachea) or restrictive (reducing compliance of lungs) pathology
Can compress:
Airways
Vessels (SVC)
Heart<br>
slide35. Mediastinal mass Preparation
Groin line in case of svc obstruction
Awake intubation with spontaneous ventilation in case of airway obstruction
Avoid neuromuscular blockade if possible
If imaging/symptoms very concerning cannulate for ecmo/bypass first
Crichothyrotomy will not help here<br>
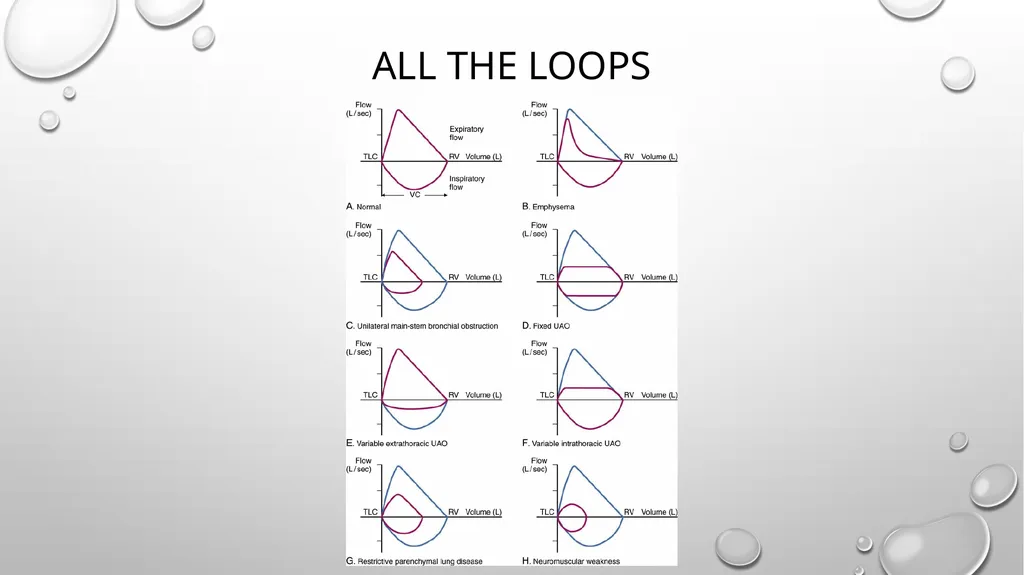
slide36. All the loops<br>
slide2. Outline Obstructive disease
Upper airway
Extrathoracic
INtrathoracic
Lower airway/Parenchymal
Restrictive disease
Neurologic
Muskuloskeletal
Parenchymal
Pleural and mediastinal
other<br>
slide3. Obstructive disease: Upper airway<br>
slide4. Upper airway From mouth to lower trachea<br>
slide5. Intra vs Extrathoracic Which lesion limits inspiratory flow the most?
A: Variable upper airway extrathoracic obstruction
B: Variable upper airway intrathoracic obstruction
C: COPD
D: Asthma<br>
slide6. Intra vs Extrathoracic Which lesion limits inspiratory flow the most?
A: Variable upper airway extrathoracic obstruction
B: Variable upper airway intrathoracic obstruction
C: COPD
D: Asthma<br>
slide7. Intra vs extra thoracic<br>
slide8. How to read a flow volume loop Where is:
-Flow?
-Volume?
-Inspiration?
-Expiration?
Where is:
-Total Lung Capacity?
-End Exhilation (residual volume)?<br>
slide9. How to read a flow/volume loop<br>
slide10. Name that obstruction<br>
slide11. Intrathoracic versus extrathoracic VOLUME IS THE SAME, FLOW IS LIMITED<br>
slide12. Lesions at the thoracic inlet Starts intrathoracic Shifts to extrathoracic<br>
slide13. FEF50%/FIF50% Forced expiratory flow at 50% vital capacity/forced inspiratory flow at 50% VC
Extrathoracic: Increased to average 2.2 from normal 1
Intrathoracic: Decreased to average 0.32 from normal 1
Fixed obstruction: around 1<br>
slide14. Causes of upper airway obstruction: Intra or extrathoracic depending on location Congenital: tracheomalacia (upper), laryngomalacia, vocal cord abnormalities, vascular rings, laryngeal webs, scoliosis (can compress trachea)
Infectious: epiglottitis, peritonsillar abscess, Retropharyngeal abscess, Ludwig’s angina, Diptheria, Croup
Tumors
Trauma: Neck hematoma, fracture, Burns
Foreign body
Soft tissue: osa, nerve palsies<br>
slide15. Obstructive disease: lower airway/parenchymal<br>
slide16. Lower airway/Parenchymal obstructive diseases Asthma
Emphysema
Bronchitis
CF: bronchiectasis
Mediastinal masses<br>
slide17. Mechanisms Officially these are no longer separated and are all copd (if asthma isn’t completely reversible
Asthma: thickened/tightened airway smooth muscle and excess mucous
CD4+ cells, T lymphocytes, eosinophils, IL-4 and IL-5
Emphysema: dilation/destruction of airway distal to terminal bronchiole (acinus)
CD8+ T-lymphocytes, neutrophils, and CD68+ monocytes/macrophages
Chronic bronchitis: Excess mucous, airway thickening
CD8+ T-lymphocytes, neutrophils, and CD68+ monocytes/macrophages<br>
slide18. COPD/Asthma/Bronchitis overlap<br>
slide19. acinus<br>
slide20. Loops<br>
slide21. Spirometry FVC: Forced vital capacity
FEV1: Forced expiratory volume
FEV1/FVC: Ratio of these two
FEF 25-75%: Forced expiratory flow from 25-75% of vital capacity
Thought to be effort independent
Mvv: Maximum voluntary expiration (how much can one inhale and exhale in 1 minute)<br>
slide22. Spirometry<br>
slide23. DLCO (Diffusion capacity for carbon monoxide) Measures the ability of the lungs to transfer o2 to the blood
Obstructive disease
Correlates with degree of emphysema
Smokers with airway obstruction but normal dlco have bronchitis but not emphysema
Asthmatics have normal or high dlco
Cystic fibrosis: normal until very late in disease<br>
slide24. Cystic Fibrosis Mutation in CFTR leading to inability to transport chloride and sodium
Autosomal recessive
Multiple organ systems effected, we will focus on respiratory
Life expectancy average 39 years<br>
slide25. What is bronchiectasis A: Chronic airway infection
B: Recurrent pneumonia in cystic fibrosis
C: Dilation of airways due to wall destruction
D: being the subject of excess bronchoscopies<br>
slide26. What is bronchiectasis A: Chronic airway infection
B: Recurrent pneumonia in cystic fibrosis
C: Dilation of airways due to wall destruction
D: being the subject of excess bronchoscopies<br>
slide27. CF: Bronchiectasis Inability to transport Cl- and Na+ effectively leads to thickened secretions
Leads to colonization w organisms
Leads to massive inflammation from neutrophil degranulation
Leads to destruction of bronchus walldilation of airways
Leads to more mucous
Leads to more infection<br>
slide28. Bronchiectasis<br>
slide29. CF: Why pseudomonas? Increased o2 utilization by lung epithelial cells causes local hypoxia
This causes pseudomonas to gain the ability to make biofilms
Almost impossible to eradicate at that point<br>
slide30. Mediastinal masses Anterior, middle and posterior mediastinum
For airway compromise most significant is anterior
Most common: terrible t’s
Teratoma
Thymoma
Thyroid tissue
“terrible lymphoma”<br>
slide31. What is the safest way to induce a patient with an anterior mediastinal mass compressing the airway? A: RSI with Sux and etomidate
B: Asleep fiber
C: Awake fiber with surgeon standing by ready to perform tracheostomy
D: Awake fiber after cannulating groin vessels for ecmo<br>
slide32. What is the safest way to induce a patient with an anterior mediastinal mass compressing the airway? A: RSI with Sux and etomidate
B: Asleep fiber
C: Awake fiber with surgeon standing by ready to perform tracheostomy
D: Awake fiber after cannulating groin vessels for ecmo<br>
slide33. Mediastinal mass CXR<br>
slide34. Mediastinal mass can cause both obstructive (compressing trachea) or restrictive (reducing compliance of lungs) pathology
Can compress:
Airways
Vessels (SVC)
Heart<br>
slide35. Mediastinal mass Preparation
Groin line in case of svc obstruction
Awake intubation with spontaneous ventilation in case of airway obstruction
Avoid neuromuscular blockade if possible
If imaging/symptoms very concerning cannulate for ecmo/bypass first
Crichothyrotomy will not help here<br>
slide36. All the loops<br>