
PRESENTATION TO PORTFOLIO COMMITTEE ON HEALTH








































Description: PRESENTATION TO PORTFOLIO COMMITTEE ON HEALTH 201718 ANNUAL REPORT 1 17 OCTOBER 2018 MS PM MATSOSO DIRECTOR-GENERAL:HEALTH To reflect on achievements and highlights for the FY201718, as outlined in the Annual Report of the National
Related Topics
Download Presentation
"PRESENTATION TO PORTFOLIO COMMITTEE ON HEALTH" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. PRESENTATION TO PORTFOLIO COMMITTEE ON HEALTH 2017/18 ANNUAL REPORT 1 17 OCTOBER 2018 MS PM MATSOSO
DIRECTOR-GENERAL:HEALTH<br>
slide2. To reflect on achievements and highlights for the FY2017/18, as outlined in the Annual Report of the National Department of Health (NDoH) 2 Purpose of the Presentation<br>
slide3. 3 Vision
A long and healthy life for all South Africans.
Mission
To improve the health status through the prevention of illnesses and the promotion of healthy lifestyles and consistently to improve the health care delivery system by focusing on access, equity, efficiency, quality and sustainability. Vision and Mission<br>
slide4. 4 The Health Sector derives its vision and mandate from NDP 2030. By 2030, South Africa should have:
Raised the life expectancy of South Africans to at least 70 years.
Progressively improved TB prevention and cure.
Reduced maternal, infant and child mortality.
Significantly reduced prevalence of non-communicable diseases.
Reduced injury, accidents and violence by 50 percent from 2010 levels.
Completed health system reforms.
Established primary healthcare teams to provide care to families and communities.
Implemented universal health coverage.
Filled posts with skilled, committed and competent individuals National Development Plan Vision 2030<br>
slide5. 5 The Annual Performance Plan 2017/18 was also designed to deliver on the MTSF commitments, namely:
Sub-outcome 1: Universal Health coverage progressively achieved through implementation of National Health Insurance
Sub-outcome 2: Improved quality of health care
Sub-outcome 3. Implement the re-engineering of Primary Health Care
Sub-outcome 4: Reduced health care costs
Sub-outcome 5: Improved human resources for health
Sub-outcome 6: Improved health management and leadership
Sub-outcome 7: Improved health facility planning and infrastructure delivery
Sub-outcome 8: HIV & AIDS and Tuberculosis prevented and successfully managed
Sub-outcome 9: Maternal, infant and child mortality reduced
Sub-outcome 10: Efficient Health Management Information System developed and implemented for improved decision making Medium Term Strategic Framework
(MTSF) 2014-2019<br>
slide6. 6 Progress Report PROGRAMME 1 : ADMINISTRATION<br>
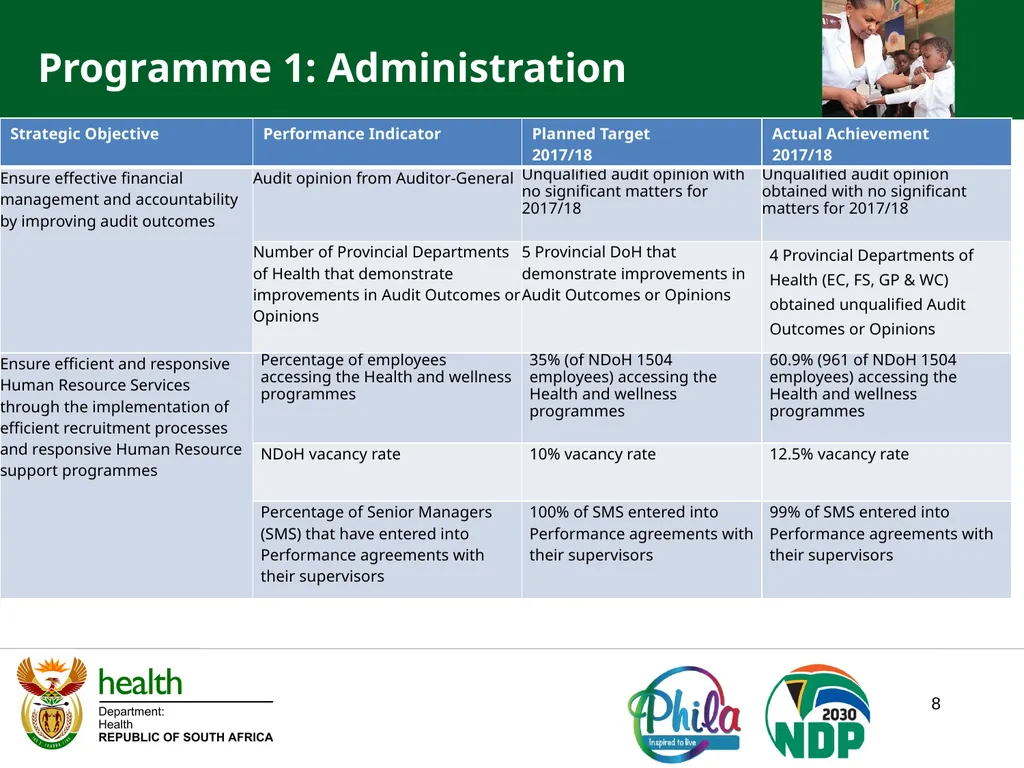
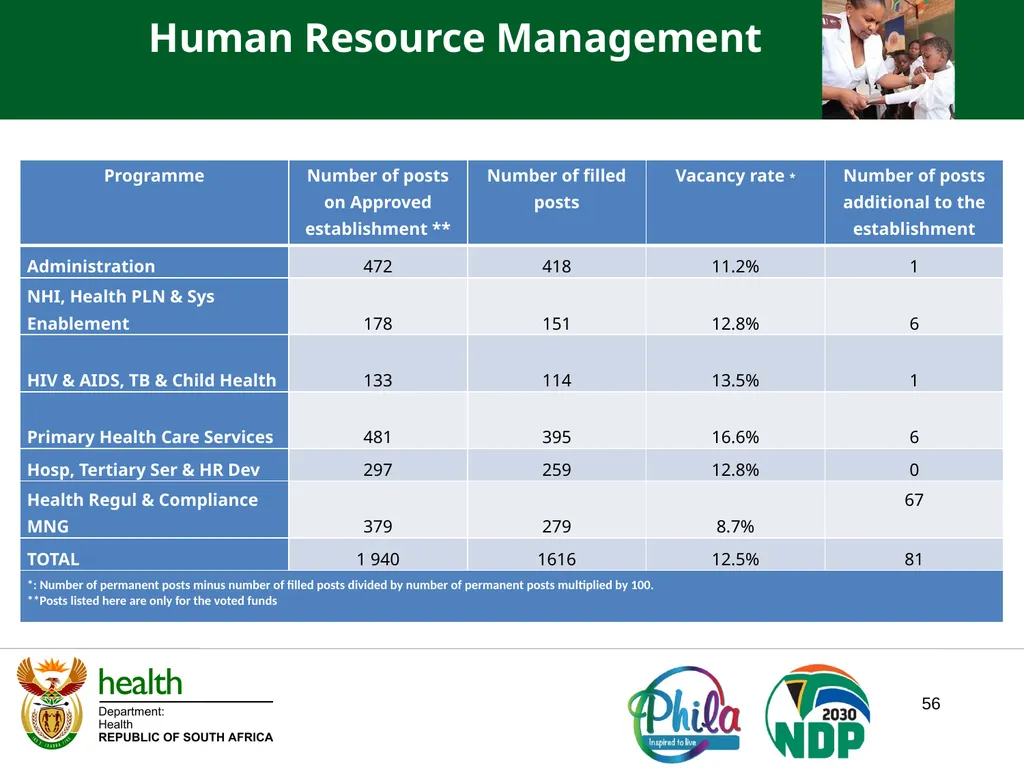
slide7. The vacancy rate was 12.5% which exceeded DPSA’s target of 10% due to budget cuts on the CoE by Treasury.
The National Department of Health (NDoH) has embarked on a robust
reprioritisation process to ensure that critical posts are filled
Turn-around Time for recruitment process was within 4 months, which exceeded the DPSA benchmark of 6 months .
NDoH has obtained an “unqualified audit opinion” from the Auditor-General for consecutive years since 2011/12, including FY2017/18 (-the period under review). Programme 1 7<br>
slide8. Programme 1: Administration 8<br>
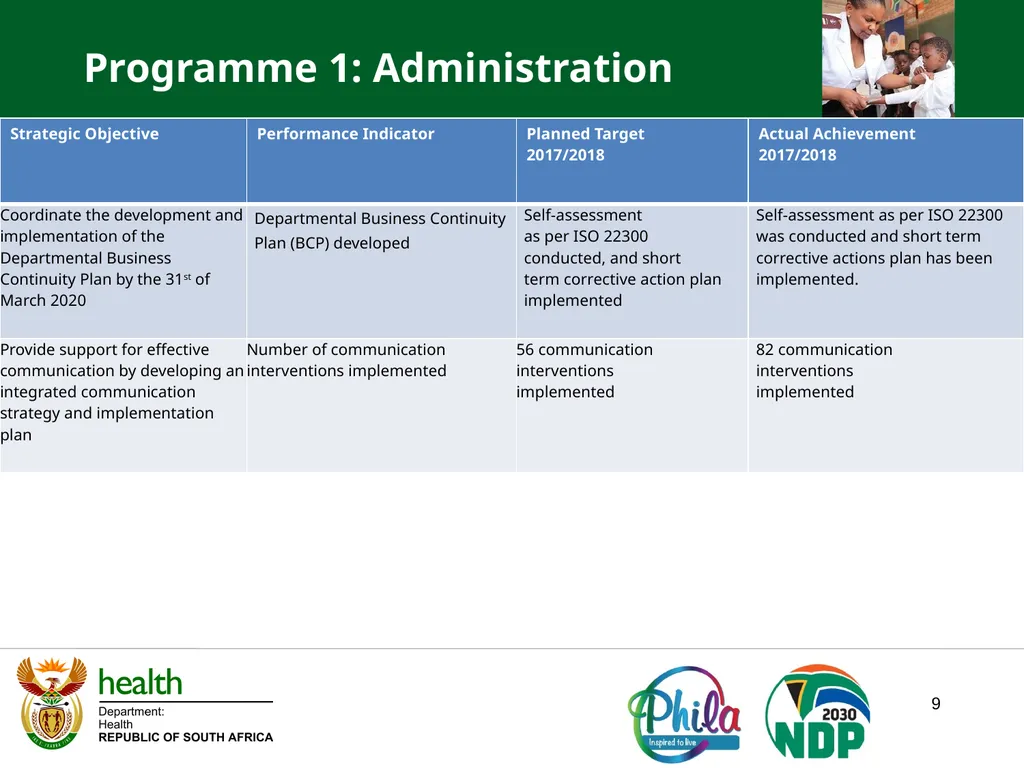
slide9. Programme 1: Administration 9<br>
slide10. Programme 1
Performance Improvement Strategies The one outstanding Performance Agreement was signed and filed with the DPSA after the stipulated deadline in 2017/18.
The reprioritisation process for critical vacant posts has been accomplished within the existing budgetary constraints. 10<br>
slide11. Progress Report PROGRAMME 2 : HEALTH PLANNING AND SYSTEMS ENABLEMENT 11<br>
slide12. Programme 2 National Health Insurance (NHI)
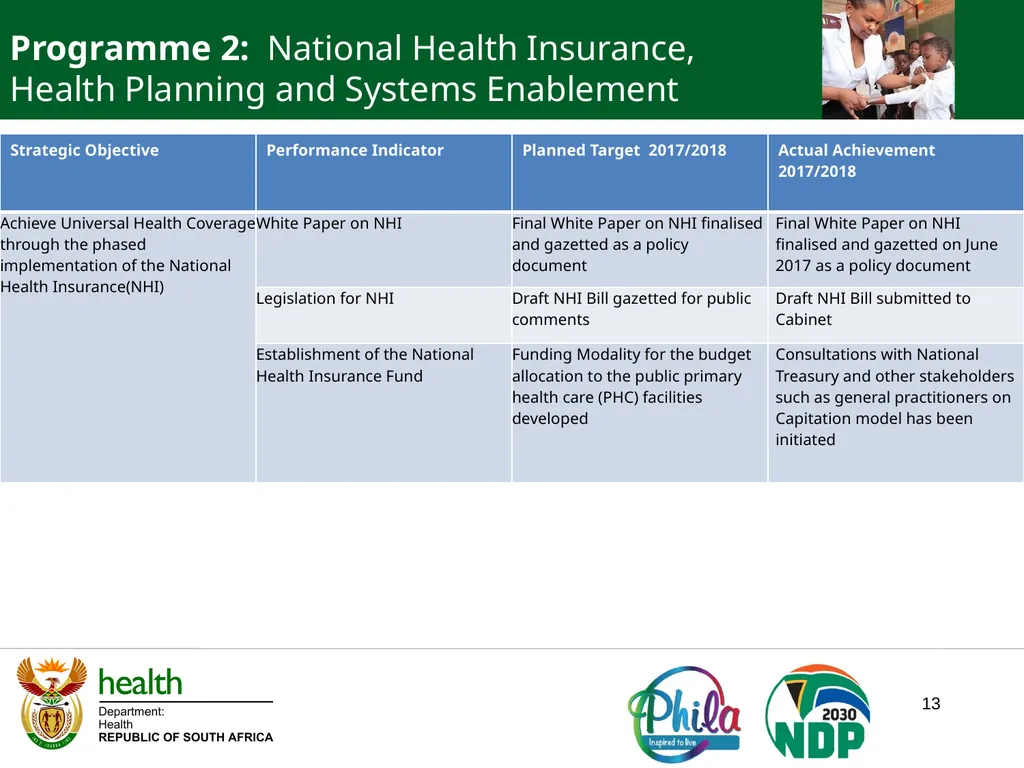
Final White Paper Policy was submitted for Cabinet consideration before end of March 2017 and published on Government Gazette on 30 June 2017
At the same time, the Minister announced the establishment of 7 NHI Implementation Structures which were published in a Government Gazette Notice on 7 July 2017. The NHI Implementation Structures are:
The Committee on Tertiary Services
The Committee on Human Resources for Health
The Committee on Health Care Benefits for National Health Insurance
National Health Pricing Advisory Committee
Committee on Consolidation of Financing Arrangements
The Committee on Health Technology Assessment for National Health Insurance
The National Health Commission
The NHI Bill & Medical Schemes Amendment Bill were submitted and approved by Cabinet. 12<br>
slide13. Programme 2: National Health Insurance, Health Planning and Systems Enablement 13<br>
slide14. Programme 2 Medicine Availability
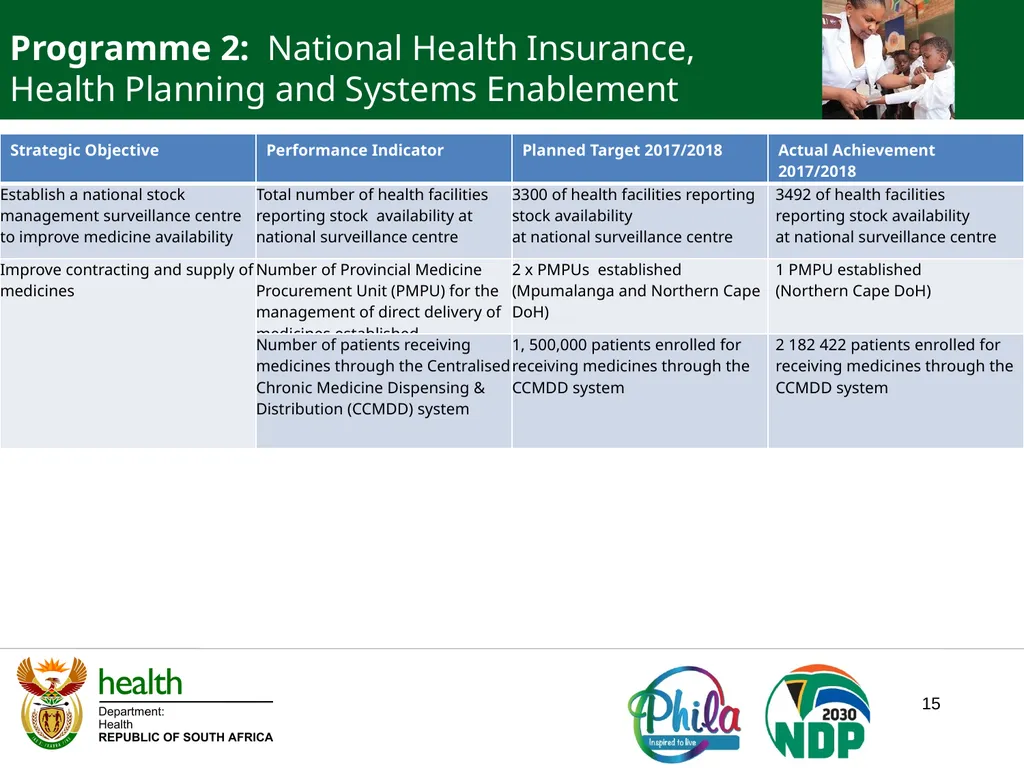
The Centralised Chronic Medicines Dispensing and Distribution (CCMDD) programme continued to enrol new patients. Patients enrolled to receive their prescribed medicines through CCMD increased from 1 252 000 in 2015/16 to 2 166 973 in 2017/18
Patients received their prescribed medicines from over 855 pick-up points including occupational health sites, GPs and private pharmacies
Use of the stock visibility system (SVS) increased to 3 168 PHC facilities The SVS allows the back code on the package or bottle to be scanned using a specially supplied cellphone and application. When a nurse scans at a clinic the stock level is reported automatically and in real time to an electronic map of all clinics at the central tower in Pretoria.
Hospitals using the electronic stock management systems in order to strengthen demand-planning and governance increased from 228 hospitals in 2016/17 to 324 hospitals in 2017/18. 14<br>
slide15. Programme 2: National Health Insurance, Health Planning and Systems Enablement 15<br>
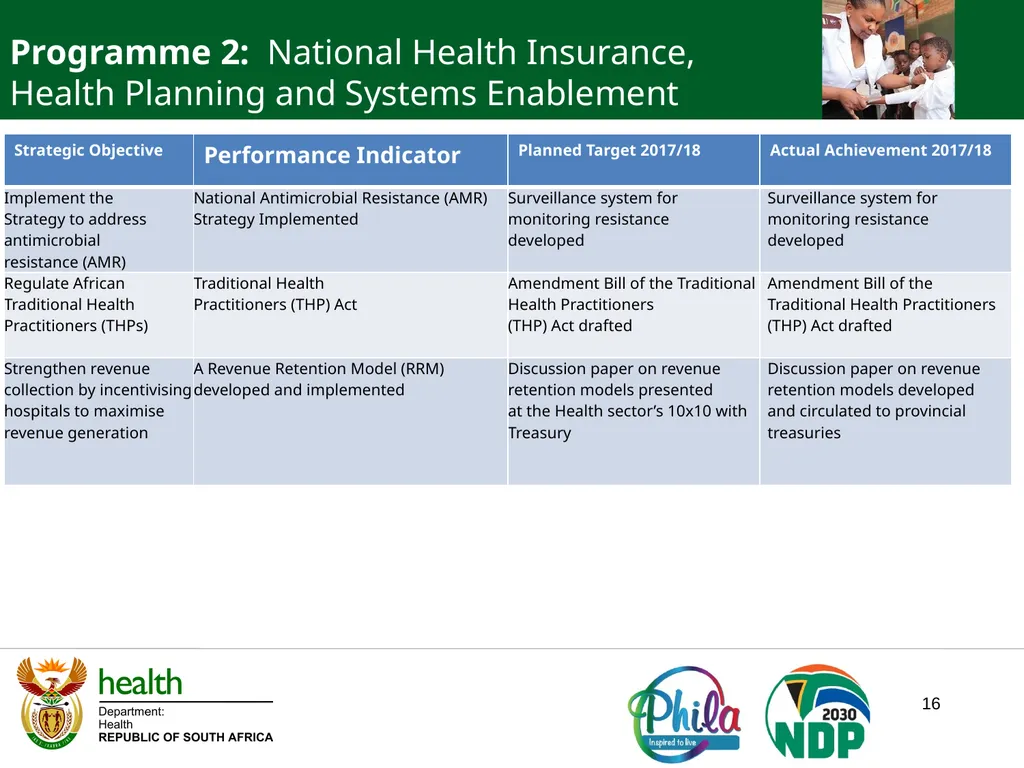
slide16. Programme 2: National Health Insurance, Health Planning and Systems Enablement 16<br>
slide17. Programme 2 eHealth and Information System
The Ministerial Advisory Committee on eHealth was appointed by the Minister of Health on 25 April 2017. The Committee completed a rapid review of the implementation of eHealth Strategy 2012-2016, and produced a report with recommendations in November 2017
The Department migrated routine data from stand-alone DHIS (District Health Information System) 1.4 to Web-DHIS. As at 31 March 2018, 1 759 of 3 955 facilities were able to capture data at facility level, whilst the remainder of the facilities are capturing data at sub-district or district levels because they do not have internet connectivity at facilities
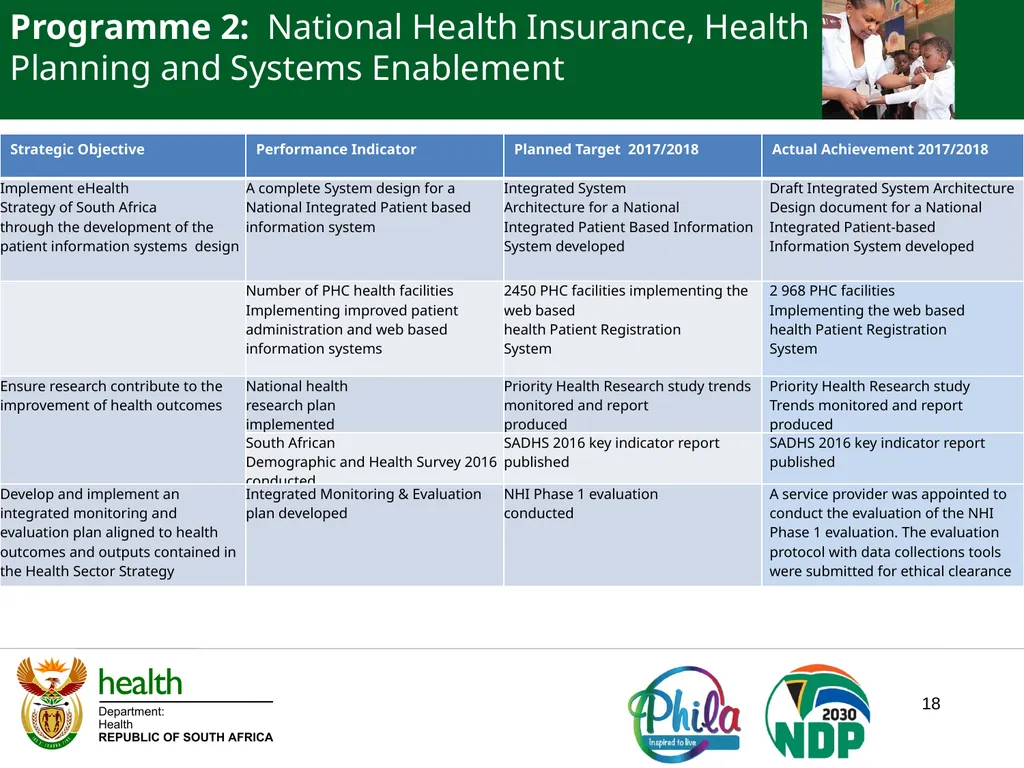
. The implementation of the HPRS was expanded from 1 854 PHC facilities in 2016/17 to 2 968 PHC facilities in 2017/18. As at 31 March 2018, 20 700 149 people were registered on the HPRS linked to a Master Patient Index. 17<br>
slide18. Programme 2: National Health Insurance, Health Planning and Systems Enablement 18<br>
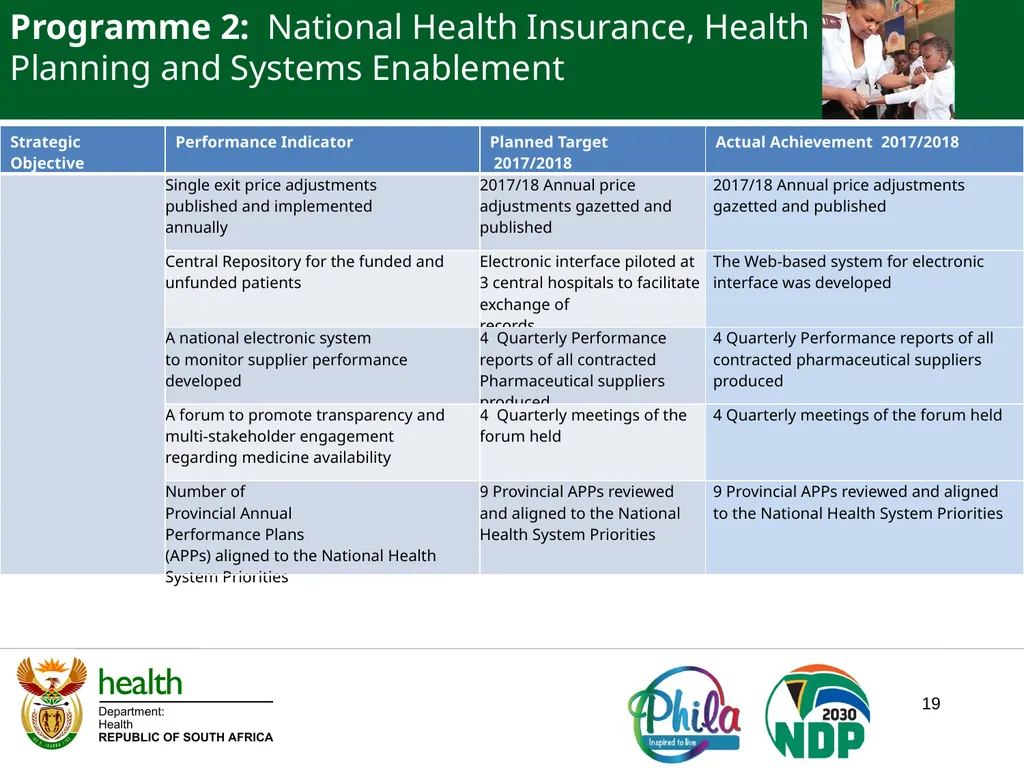
slide19. Programme 2: National Health Insurance, Health Planning and Systems Enablement 19<br>
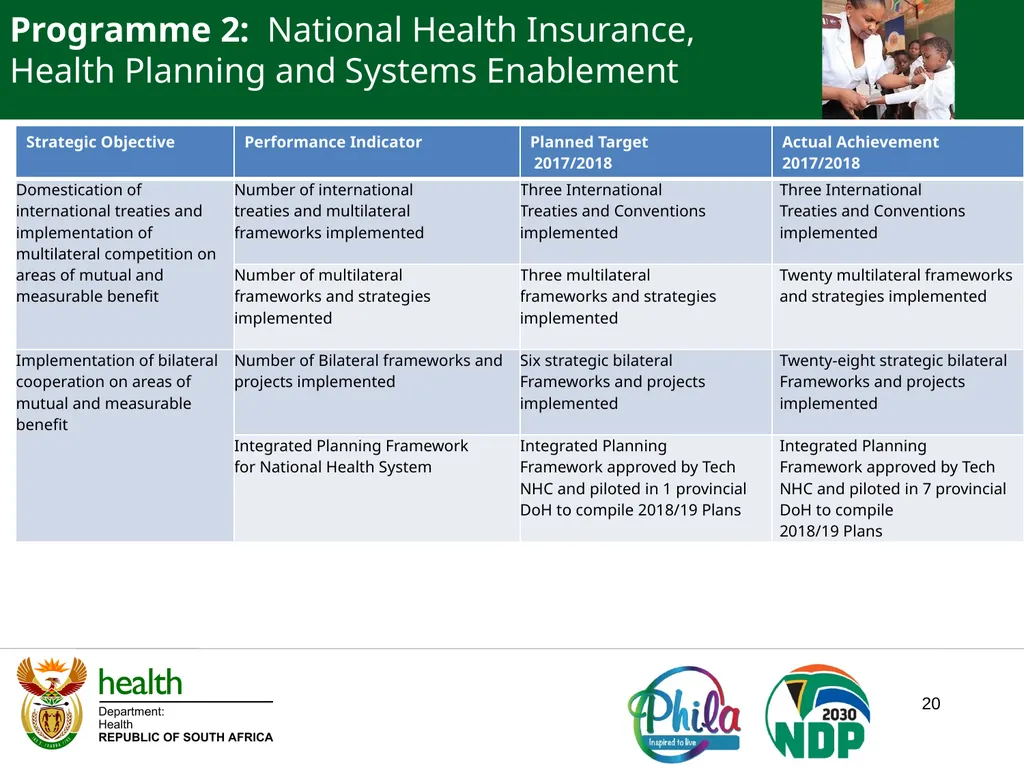
slide20. Programme 2: National Health Insurance, Health Planning and Systems Enablement 20<br>
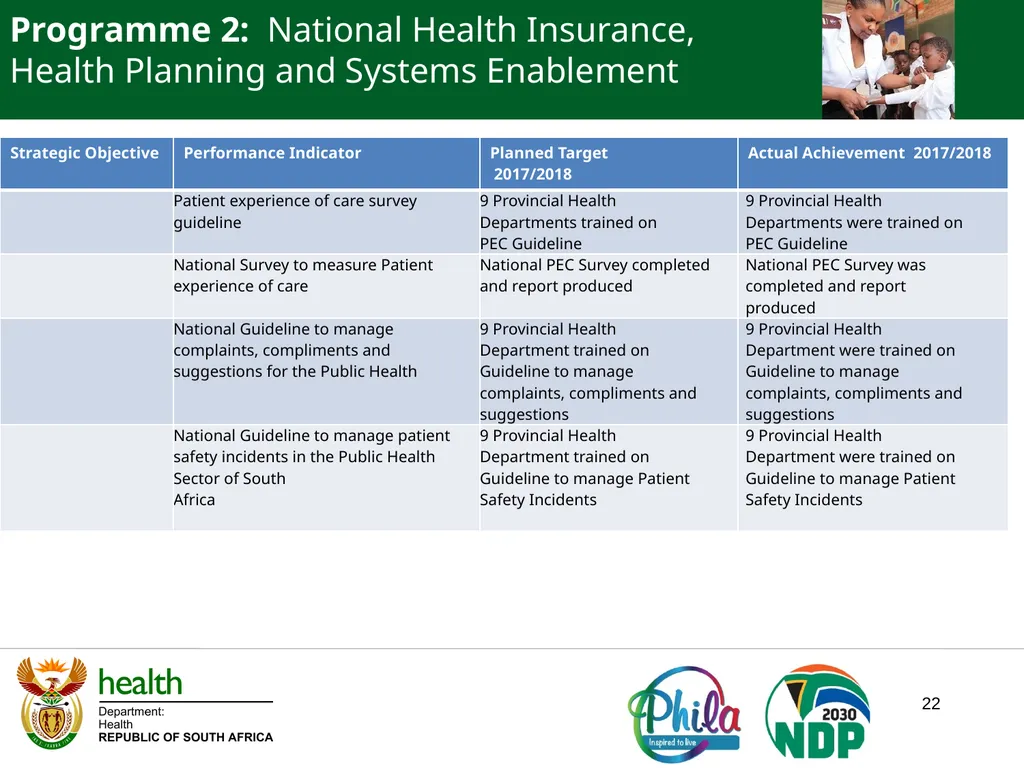
slide21. Programme 2 Quality of Care
National Survey to measure Patient Experience of Care in selected PHC facilities and hospitals.
Three Guidelines were finalised: i) Patient Experience of care survey Guideline ii) National Guideline to manage Complaints, Compliments and Suggestions for the Public Health Sector of South Africa and iii) National Guideline to manage Patient Safety Incident Reporting and Learning in the Public Health Sector of South Africa.
Norms and Standards Regulations applicable to different categories of health establishments were finalised and gazetted in February 2018, and implementation by all health establishments will be expected from 1 March 2019.
South Africa is participating in the Global Lancet Commission and has also established the Lancet National Commission consisting 15 members from public sector, Universities, private sector, Non-Governmental and Quality Institutions. The Lancet National Commission was launched in May 2017.
The Lancet National Commission and the Lancet Global Commission hosted the Global Lancet Commission meeting from 11 -13 December 2017, attended by the Chairperson of the Lancet Global Commission and National Commissioners from South Africa, Mexico, Ethiopia, Senegal, Philippines, Argentina, Nepal and Tanzania. 21<br>
slide22. Programme 2: National Health Insurance, Health Planning and Systems Enablement 22<br>
slide23. Programme 2
Performance Improvement Strategies A depot manager has been recently appointed and a revised project plan has been developed to support Provincial Medicine Procurement Unit (PMPU) functionality in the Mpumalanga Department of Health
NHI Phase 1 evaluation is currently underway. 23<br>
slide24. Progress Report PROGRAMME 3 : HIV AND AIDS, TUBERCULOSIS , MATERNAL, CHILD AND WOMEN’S HEALTH 24<br>
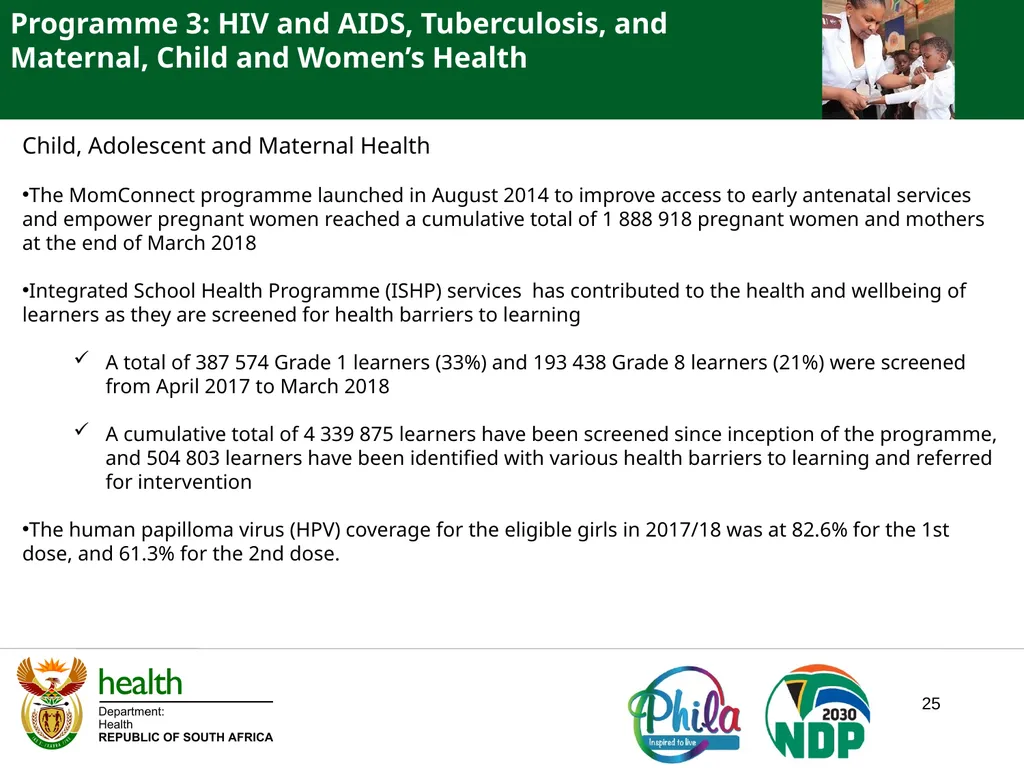
slide25. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health Child, Adolescent and Maternal Health
The MomConnect programme launched in August 2014 to improve access to early antenatal services and empower pregnant women reached a cumulative total of 1 888 918 pregnant women and mothers at the end of March 2018
Integrated School Health Programme (ISHP) services has contributed to the health and wellbeing of learners as they are screened for health barriers to learning
A total of 387 574 Grade 1 learners (33%) and 193 438 Grade 8 learners (21%) were screened from April 2017 to March 2018
A cumulative total of 4 339 875 learners have been screened since inception of the programme, and 504 803 learners have been identified with various health barriers to learning and referred for intervention
The human papilloma virus (HPV) coverage for the eligible girls in 2017/18 was at 82.6% for the 1st dose, and 61.3% for the 2nd dose. 25<br>
slide26. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health HIV and TB
Since the HIV Counselling and Testing (HCT) campaign was introduced in 2010, over 44 million people have been tested. A total of 13 872 315 people were tested for HIV, exceeding the annual target of 10 million for the 2017/18 financial year
At the end of March 2018, the total number of clients remaining on ART therapy (TROA) reached 4 189 070
Fewer infants are being infected with HIV. In 2017/18, a polymerase chain reaction (PCR) test done at around 10 weeks showed a 0.95% positivity rate for all babies born to HIV-positive women
New TB client treatment success rate reached 84.4%, while the TB client death rate was at 3.9% in 2017/18, the same as the rate in the previous financial year 26<br>
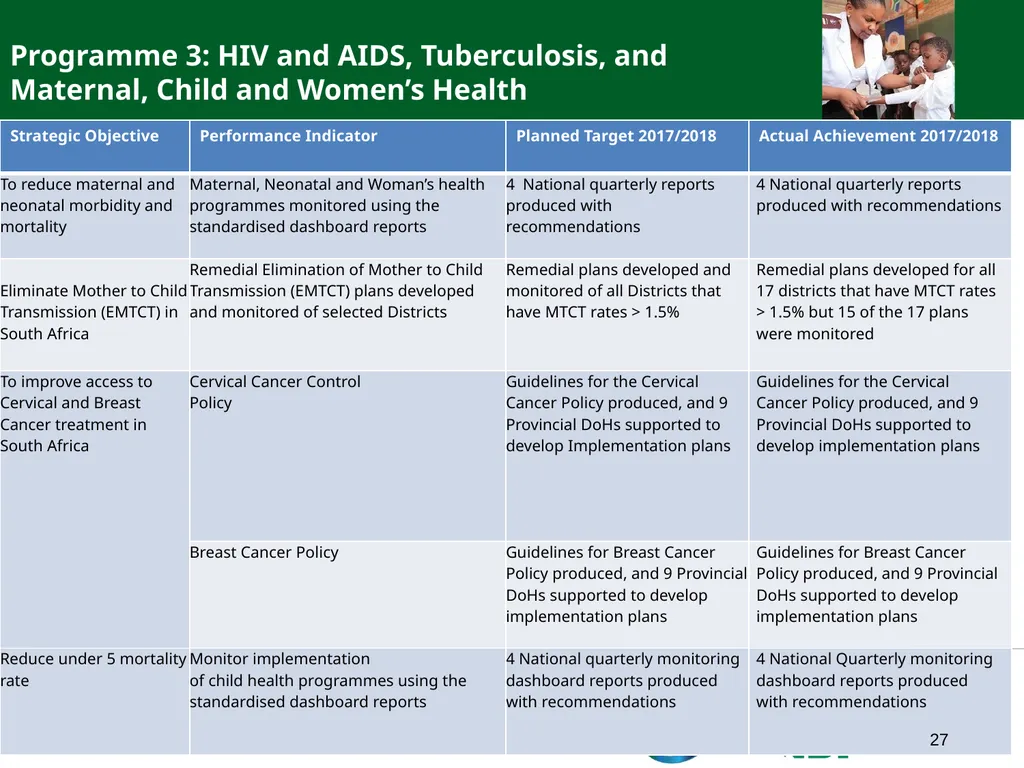
slide27. Programme 3: HIV and AIDS, Tuberculosis, and Maternal, Child and Women’s Health 27<br>
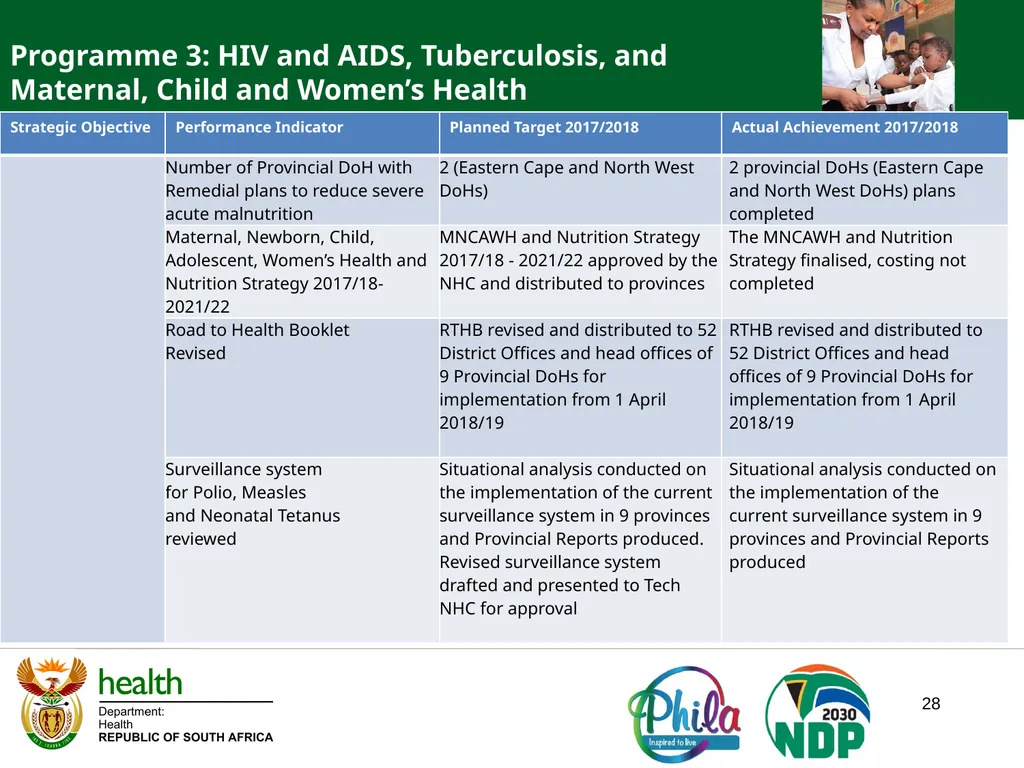
slide28. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health 28<br>
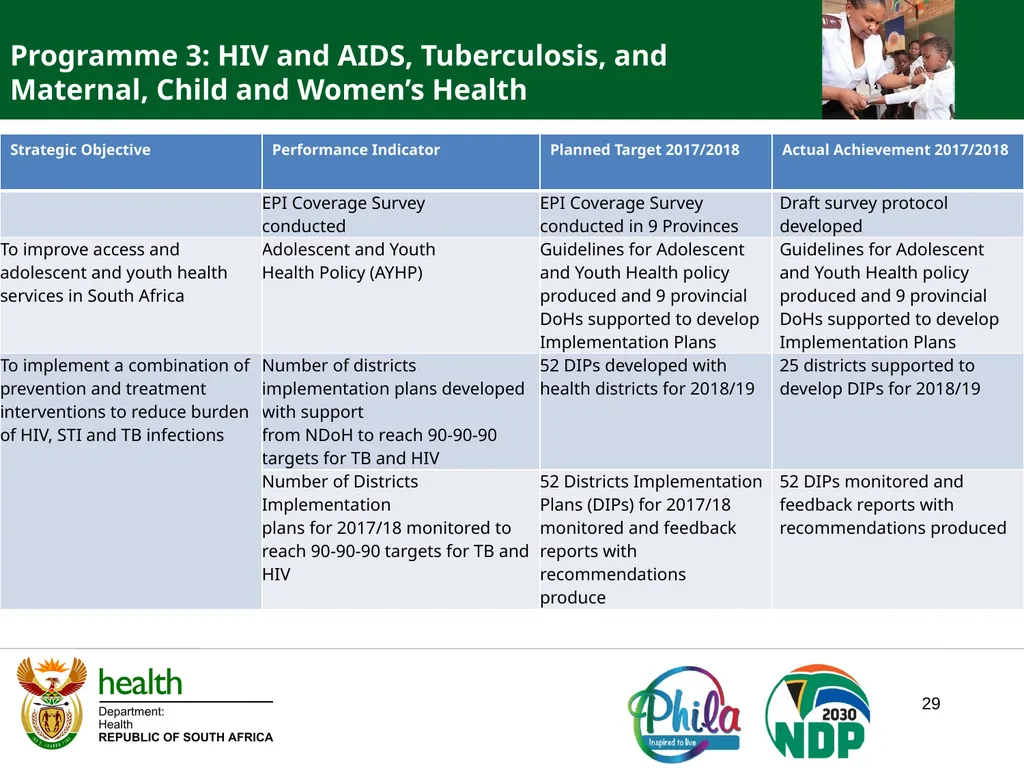
slide29. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health 29<br>
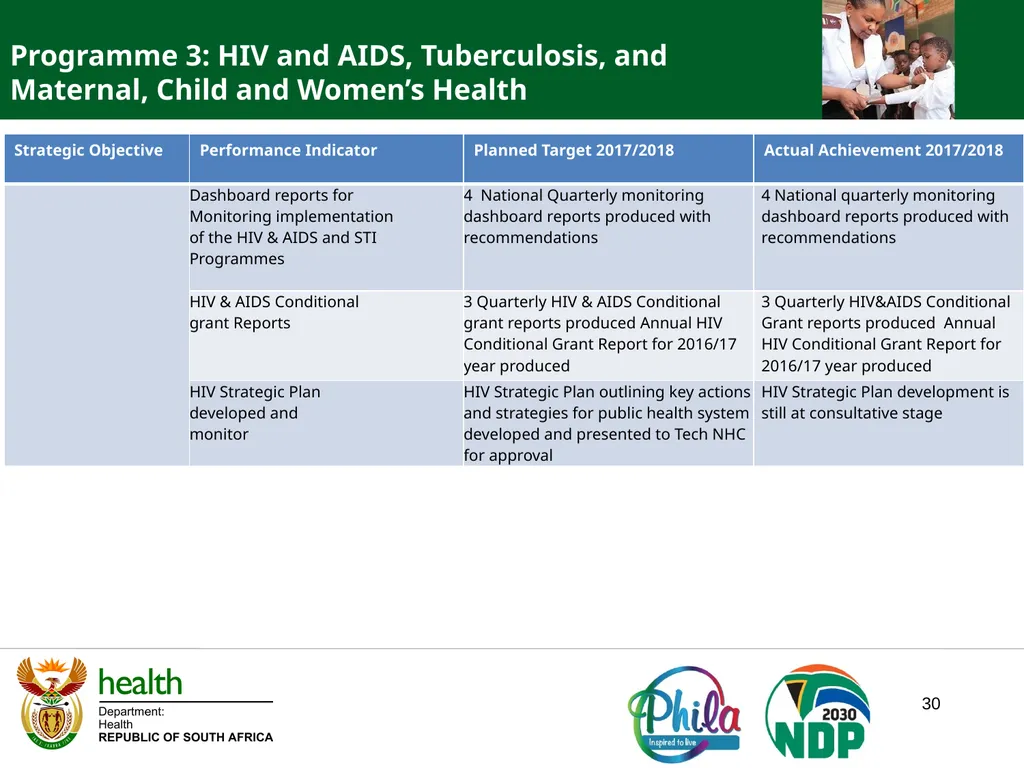
slide30. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health 30<br>
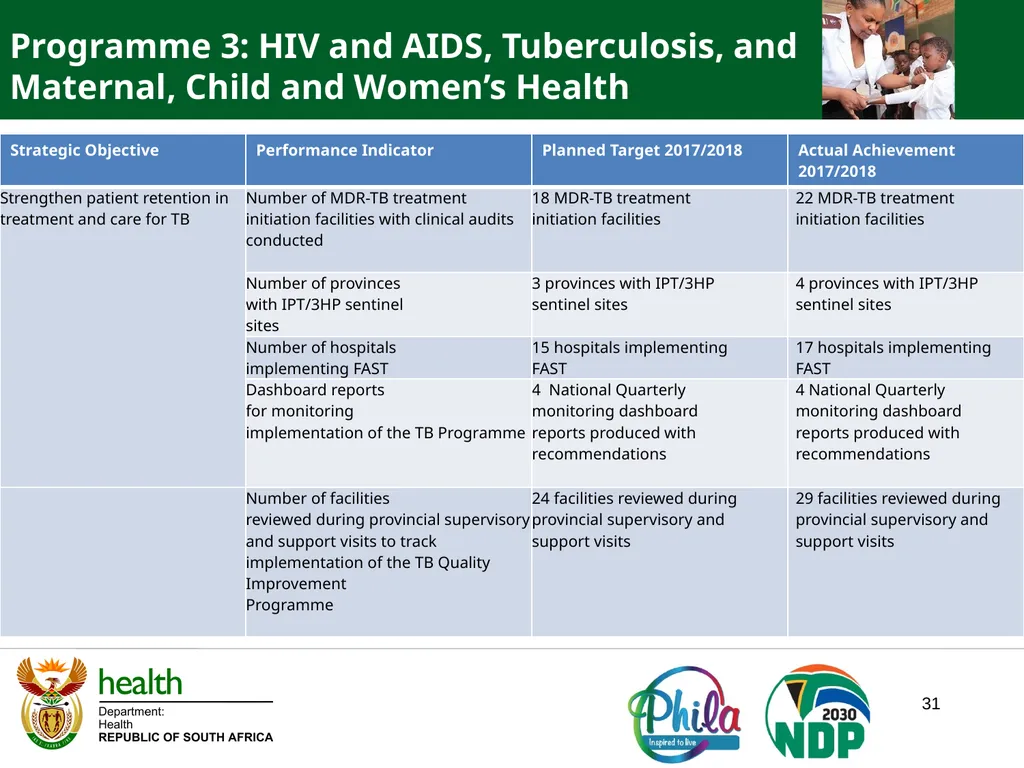
slide31. Programme 3: HIV and AIDS, Tuberculosis, and Maternal, Child and Women’s Health 31<br>
slide32. Programme 3
Performance Improvement Strategies Development of the HIV Strategic Plan outlining key actions and strategies for the public health system will be done during the 2018/19 financial year.
The District Implementation Plans to reach 90-90-90 targets for HIV and TB will be developed as part of the District Health Plans. 32<br>
slide33. Progress Report PROGRAMME 4 : PRIMARY HEALTH CARE (PHC) SERVICES 33<br>
slide34. Programme 4
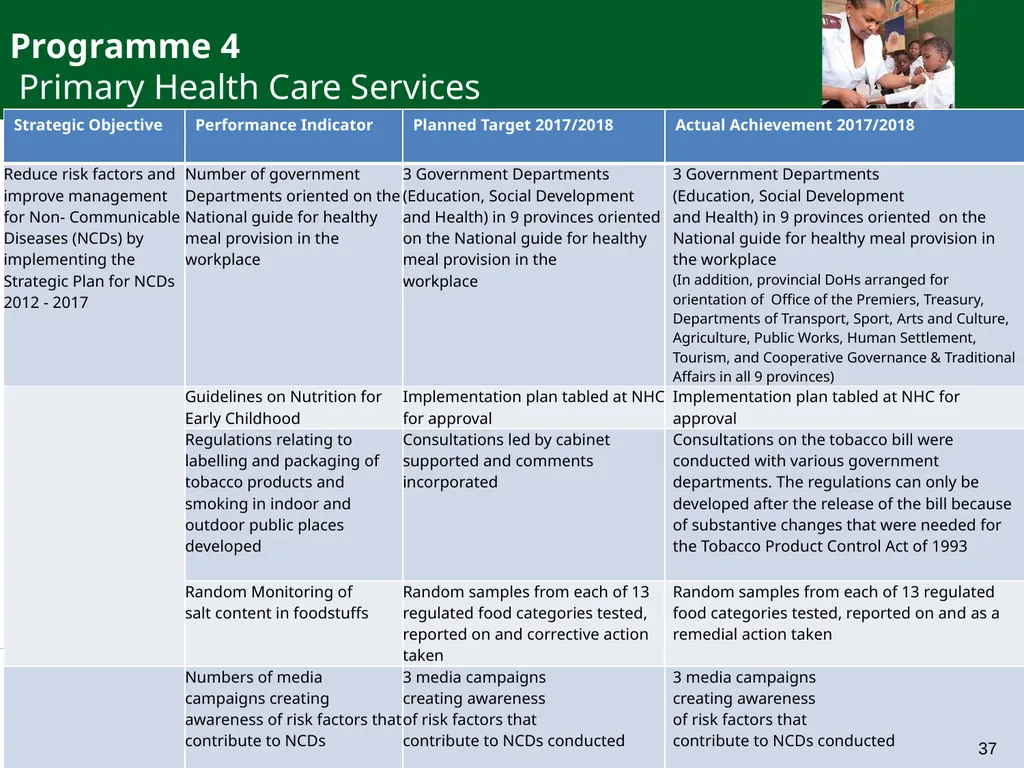
Primary Health Care Services As at the end of March 2018, a cumulative total of 1 507 facilities qualified as Ideal Clinics. This achievement has been enabled by collaboration between the NDoH and National Treasury in resolving supply chain management challenges faced by clinics, especially with regard to equipment, essential supplies and infrastructure.
Environmental and port health services: A total of 20 district and metropolitan municipalities rendering municipal health services were audited, and 13 of the 20 reached 51% and above.
10 Ports of Entry (PoEs) were assessed and found to be compliant with the International Health Regulations, 2005.
Orientation workshops to Government Departments on the national guide for healthy meal provision in the workplace were conducted in all nine provinces to assist employees adopt healthy eating habits. 34<br>
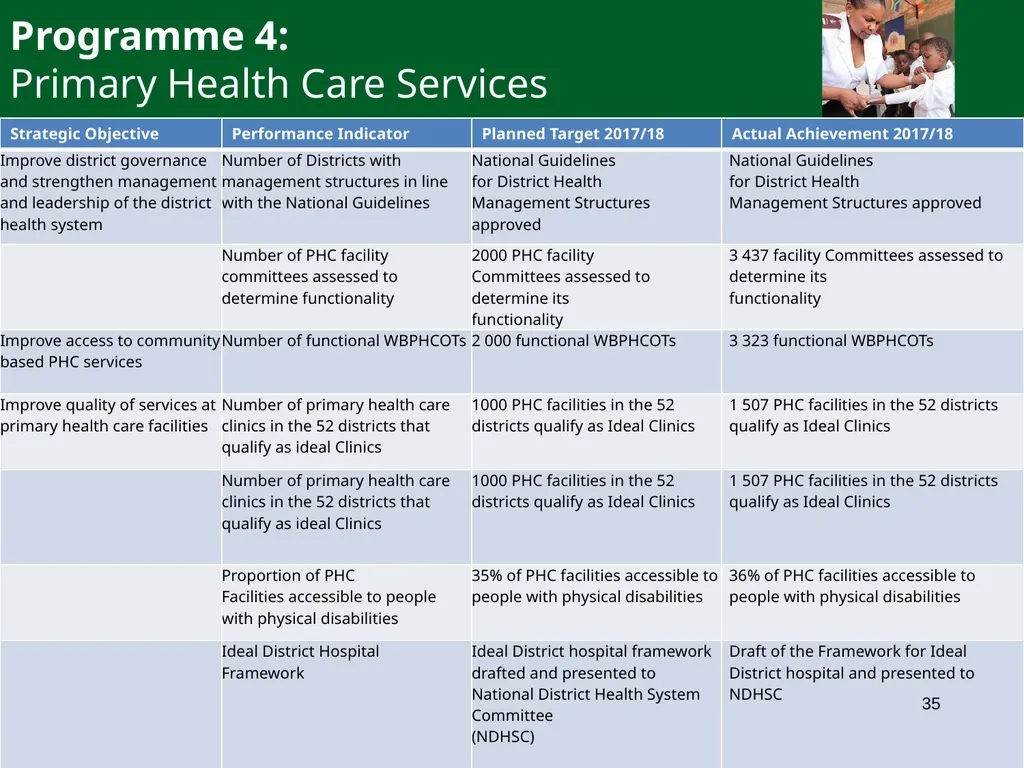
slide35. Programme 4:
Primary Health Care Services 35<br>
slide36. Programme 4
Primary Health Care Services 36<br>
slide37. Programme 4
Primary Health Care Services 37<br>
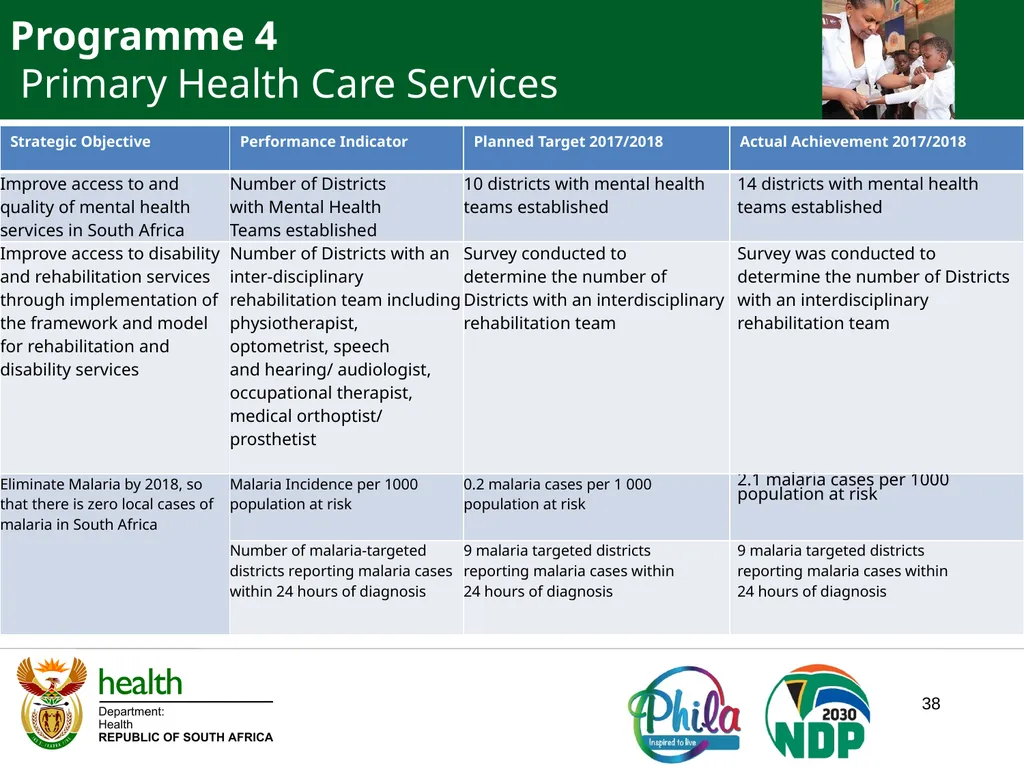
slide38. Programme 4
Primary Health Care Services 38<br>
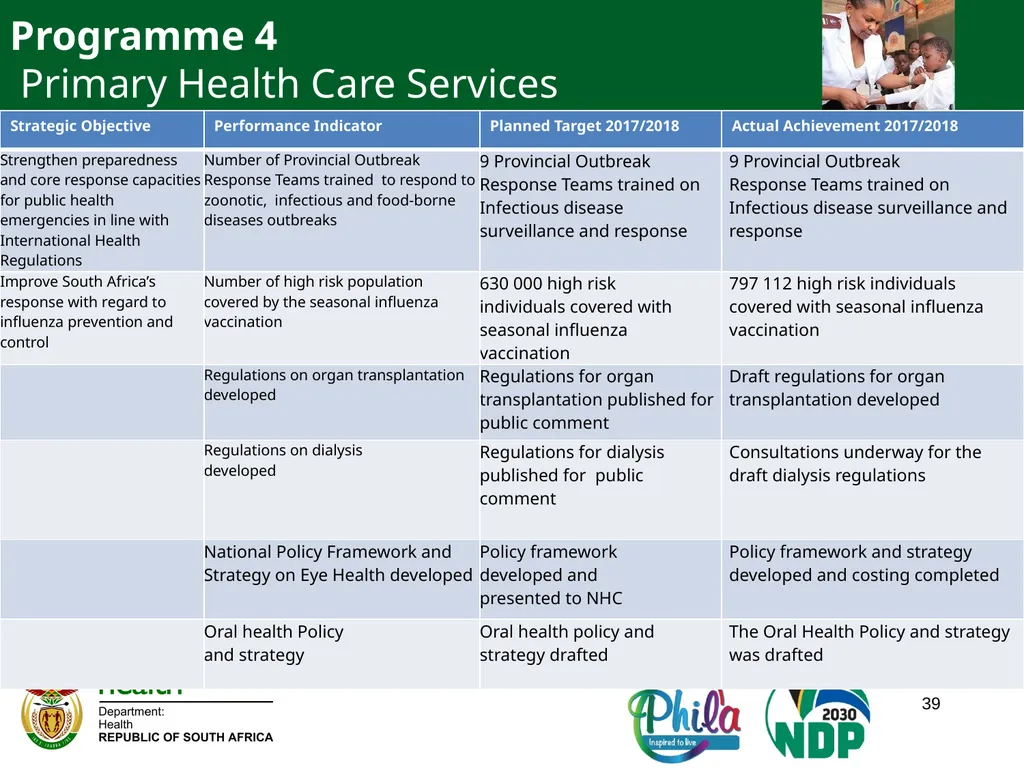
slide39. Programme 4
Primary Health Care Services 39<br>
slide40. Programme 4
Performance Improvement Strategies Malaria indoor residual spraying (IRS) will be increased, and will commence earlier than usual in the endemic provinces. Killing of larva (where appropriate) will be strengthened and rolled out in the winter. Collaboration with neighbouring countries affected by malaria will also be strengthened and scaled up 40<br>
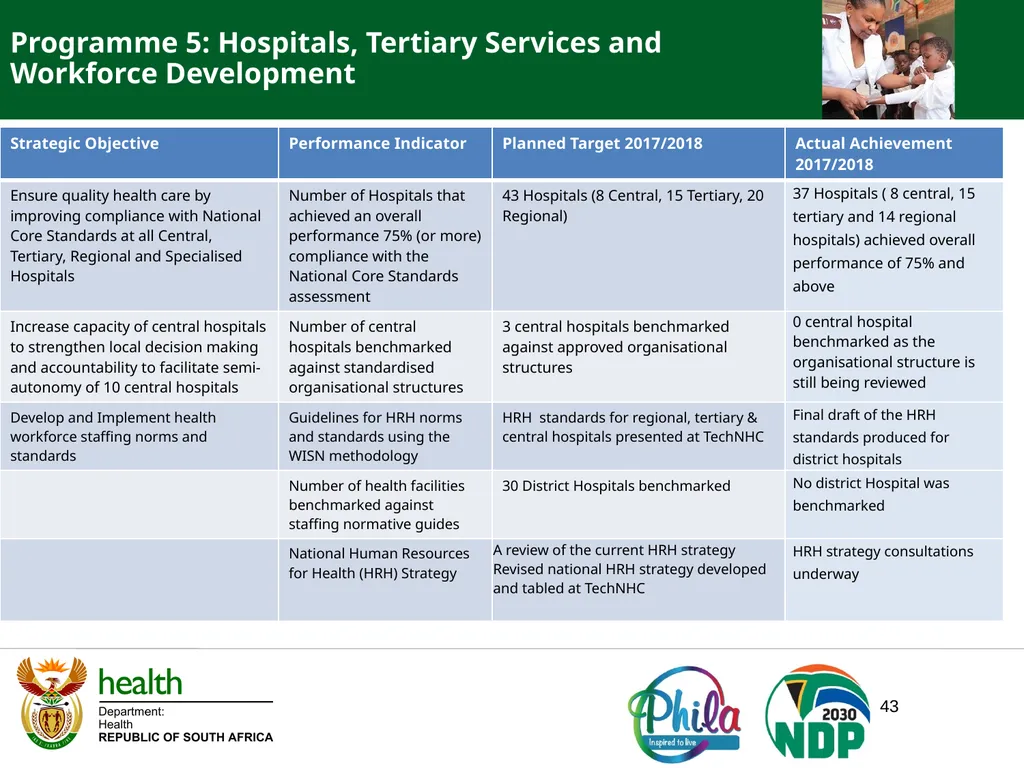
slide41. 41 Progress Report PROGRAMME 5 : Hospitals, Tertiary Services and Workforce Development<br>
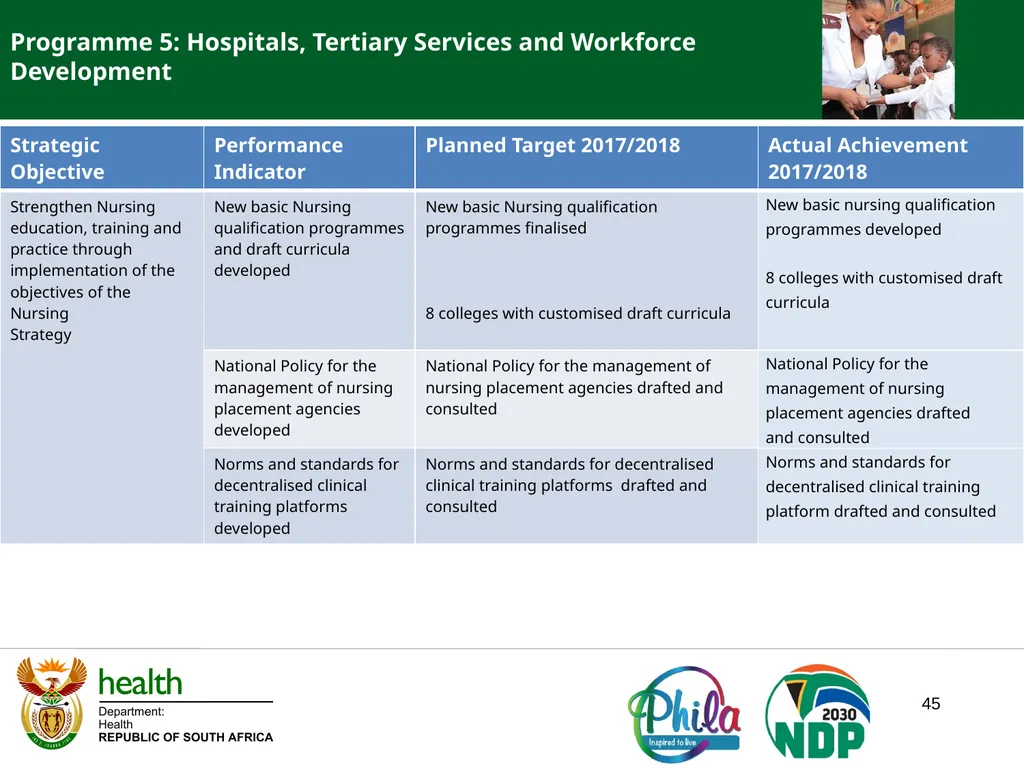
slide42. Programme 5 A national core curriculum was finalised for the new three-year diploma in general nursing and a one-year diploma in midwifery. The three-year diploma programme aims to enable graduates to function as clinically focused, service-oriented, general nurses, able to manage low-risk health problems along the continuum of care.
Eight of the 17 public nursing colleges were supported to develop customised curricula in preparation for programme accreditation
In the 2017/18 financial year, staffing norms were implemented for the PHC levels. More than 2 000 PHC facility managers in seven provinces were trained on the concept and methodology for determining staffing needs based on workload. 42<br>
slide43. Programme 5: Hospitals, Tertiary Services and Workforce Development 43<br>
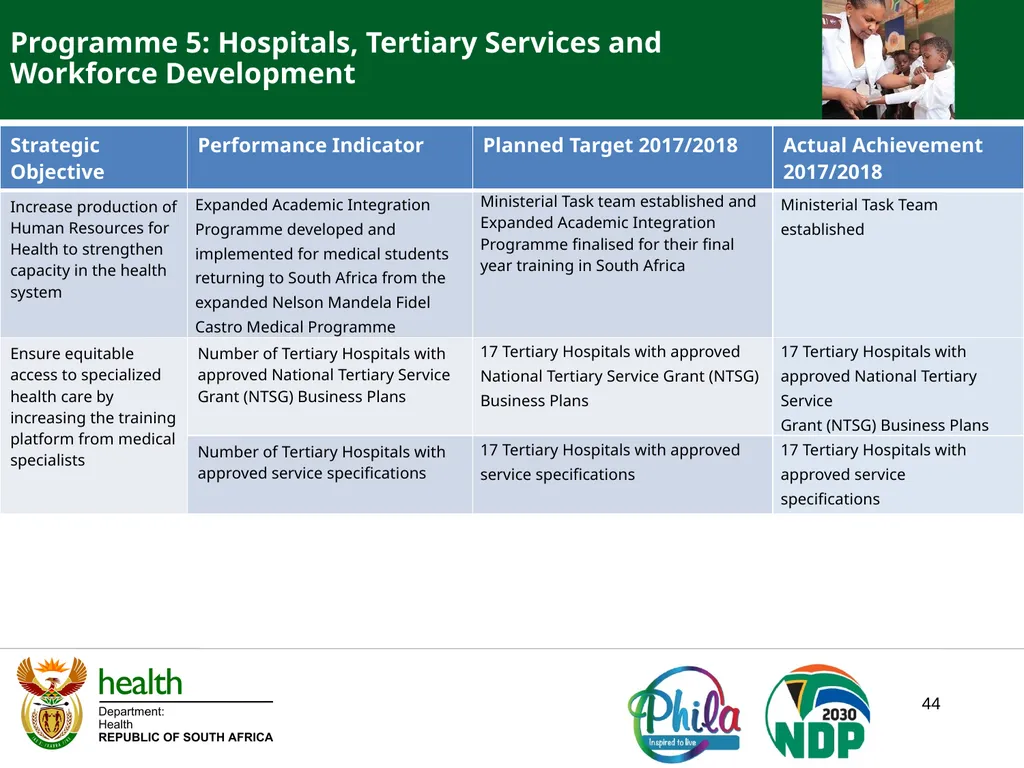
slide44. 44 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide45. 45 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
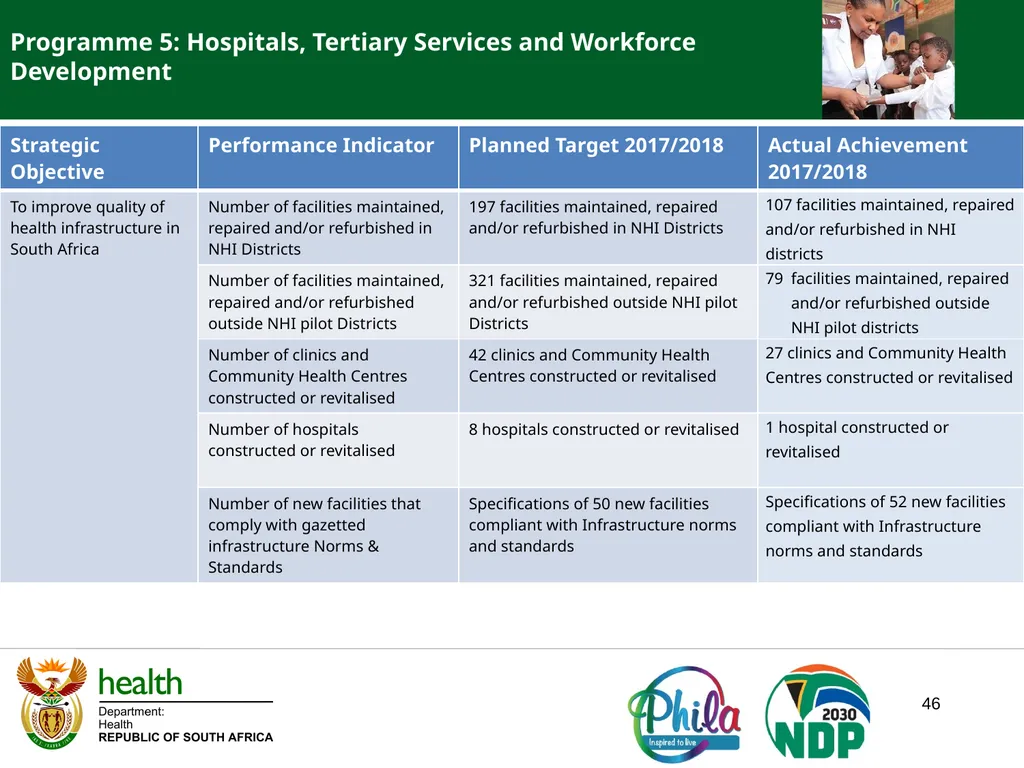
slide46. 46 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
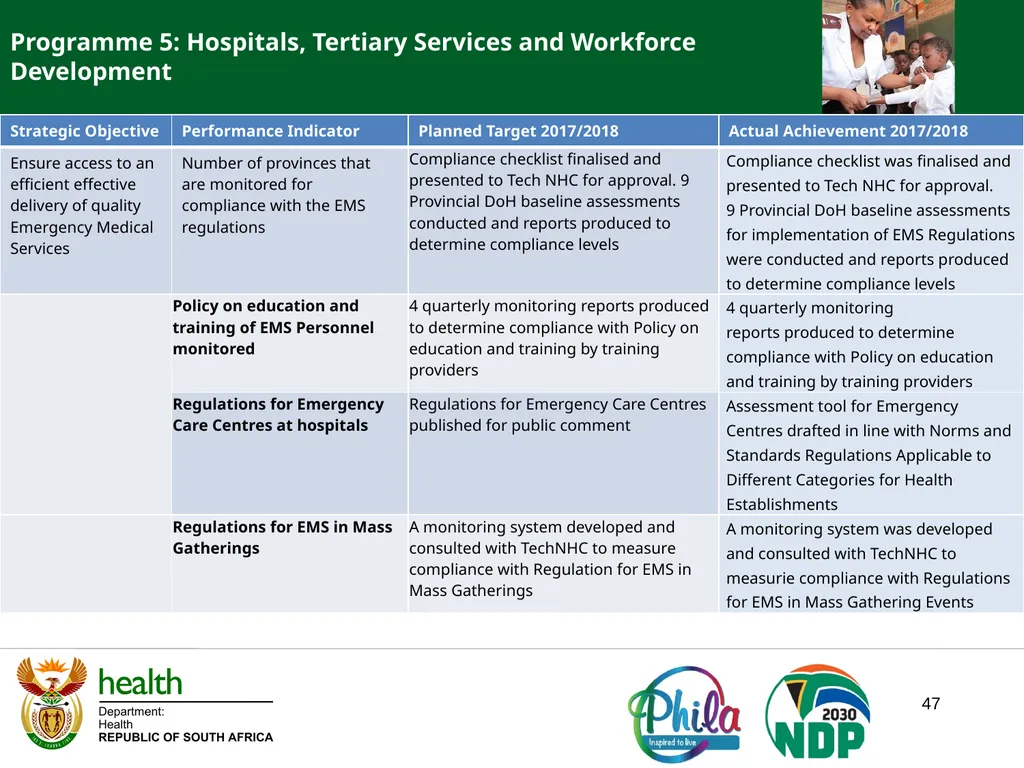
slide47. 47 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
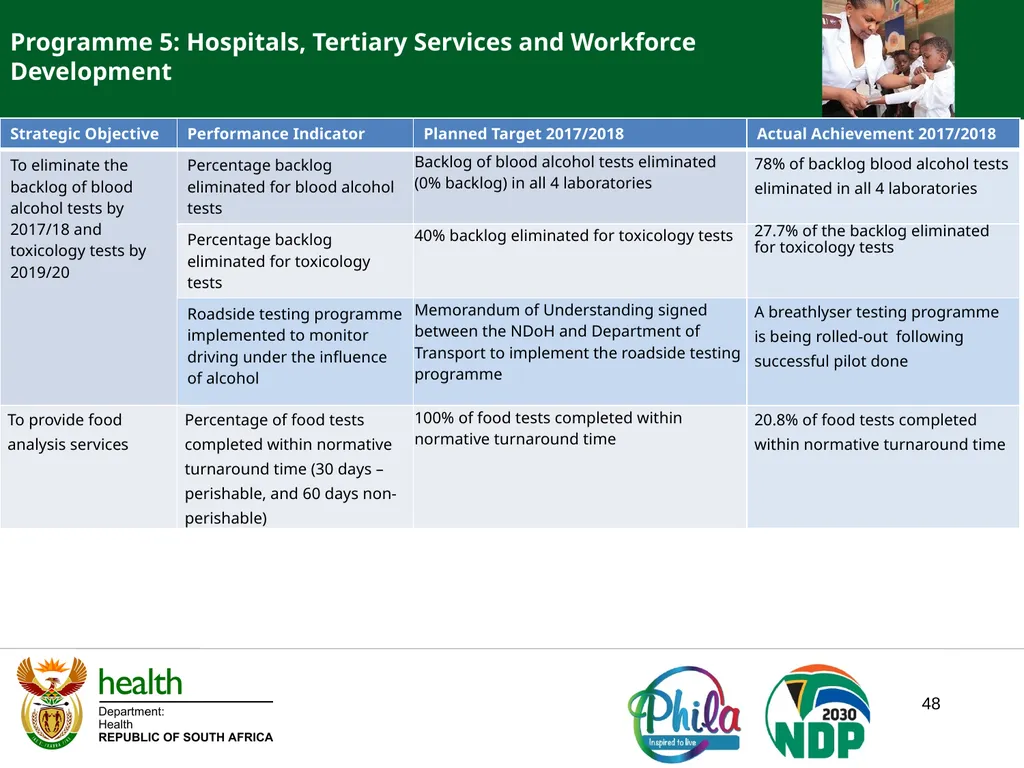
slide48. 48 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
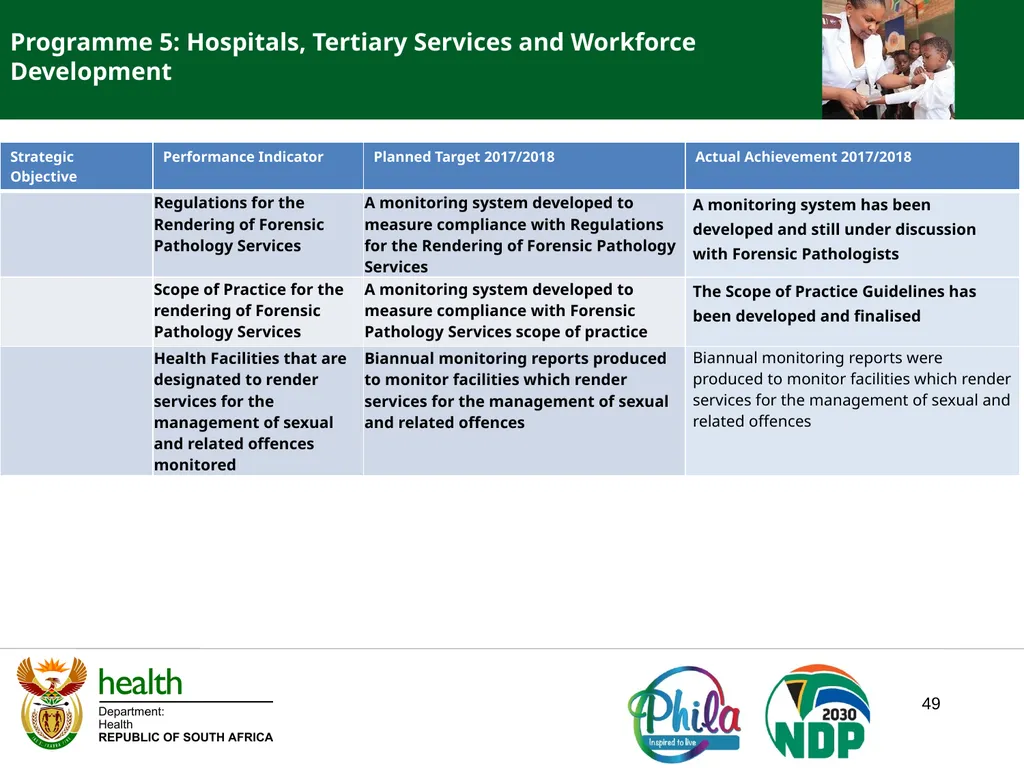
slide49. 49 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide50. 50 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide51. Programme 5
Performance Improvement Strategies Staffing norms at the higher levels of care (regional, tertiary and central hospitals) will be developed following completion of the process at district hospital level.
Forensic Chemistry Laboratories will implement a targeted approach to analysis, in particular toxicology analysis, which will significantly reduce the toxicology backlog.
Blood alcohol and food analysis turnaround time, and the repair and maintenance of equipment, will be enhanced to improve output.
All outstanding activities in the area of forensic pathology mortuaries will be facilitated through quarterly engagements with forensic pathology managers in all provinces.
The 793 infrastructure projects that failed to reach practical completion by end of March 2018 will form part of planned projects in the 2018/19 financial year
Provincial workshops are scheduled for 2018/19 to ensure that all managers access the already established knowledge hub, coaching and mentoring programme 51<br>
slide52. 52 Progress Report PROGRAMME 6 : Health Regulation and Compliance Management<br>
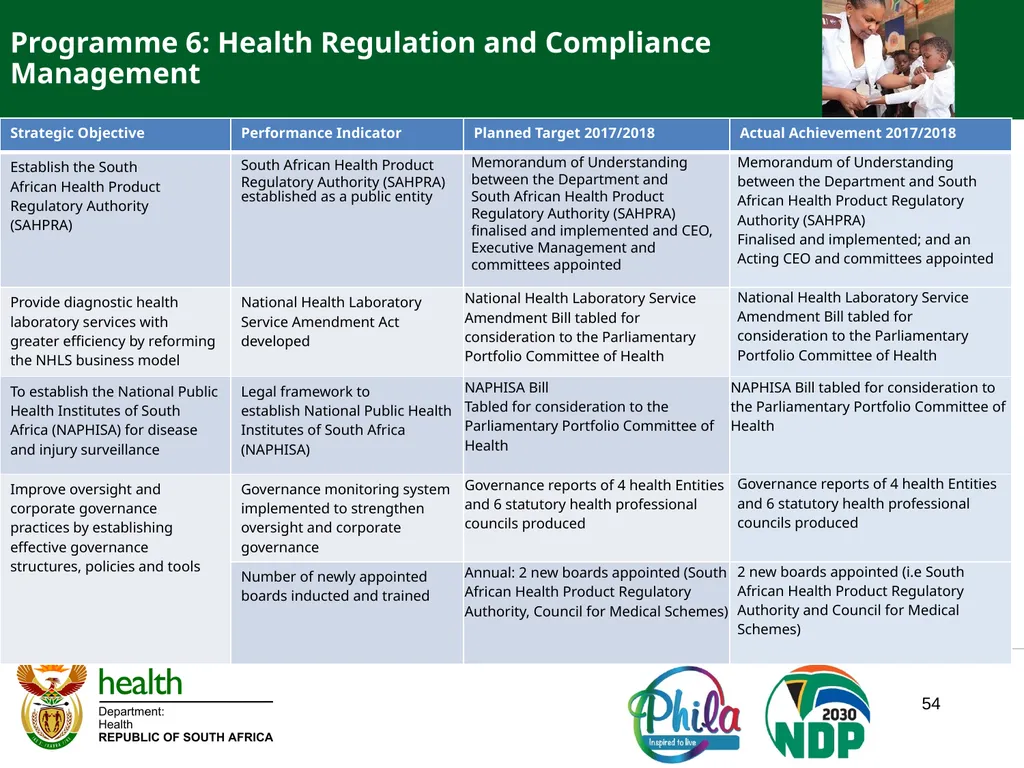
slide53. Programme 6: Health Regulation and Compliance Management The first Board of SAHPRA was appointed by the Minister for a three-year term of office. The Acting Chief Executive Officer of the Authority was appointed following the first meeting of the Board
The National Public Health Institute of South Africa (NAPHISA) Bill was also tabled for consideration at the Parliamentary Portfolio Committee of Health
The Compensation Commissioner for Occupational Diseases and Occupational Health paid about R254 million to 10 409 claimants, of which R110 million went to neighbouring countries. One Stop Service Centres were opened in Burgersfort and Kuruman, one in Botswana, two in Lesotho, two in Mozambique and two in Swaziland to give ex-mineworkers increased access to decentralised services. 53<br>
slide54. 54 Programme 6: Health Regulation and Compliance Management<br>
slide55. Human Resource Management 55<br>
slide56. Human Resource Management 56<br>
slide57. Financial Management 57<br>
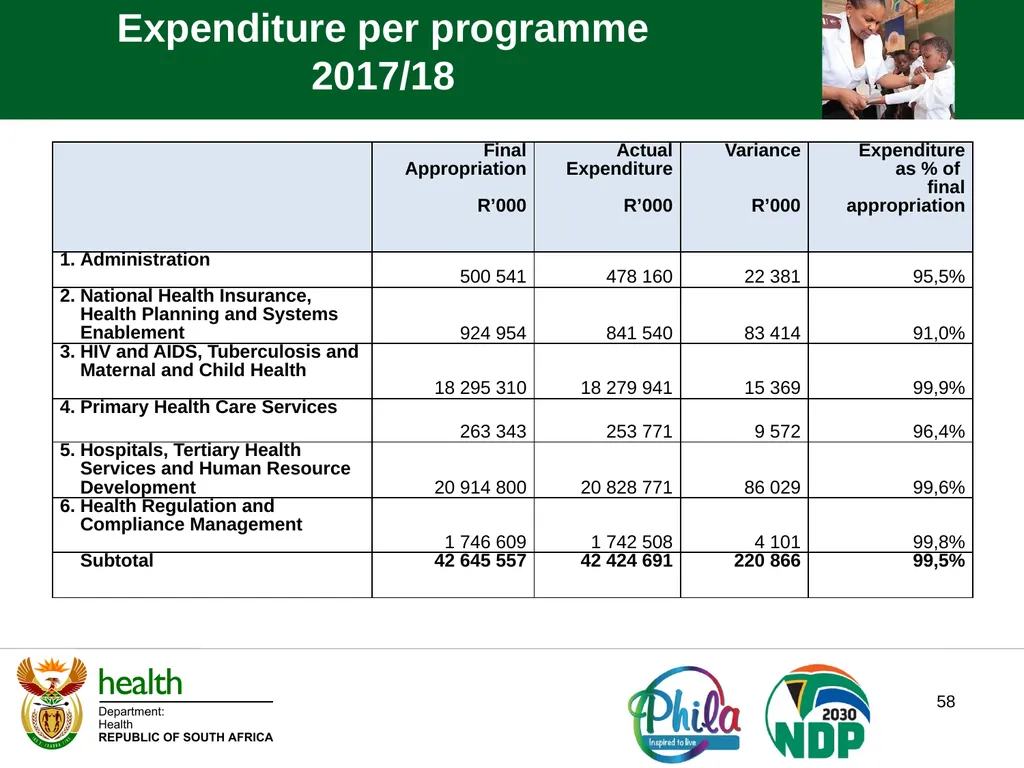
slide58. 58 Expenditure per programme
2017/18<br>
slide59. 59 Programme 1: Administration
Delays in receiving the invoice for the renewal of the software license from the supplier has resulted in non-payment and the lease contract for the Forensic Chemistry Laboratory was not signed.
Programme 2: National Health Insurance, Health Planning and System Enablement
There was no expenditure for the Drug Related Group project during 201718 year.
New in-kind grant for Medicine Stock System was experiencing initial difficulties to spend funds.
Programme 4: Primary Health Care Services
Invoices were delayed for Ideal Clinic Realisation and Maintenance (ICRM) feedback and planning meetings that were conducted in provinces. Explanations of material variances
Per Programme<br>
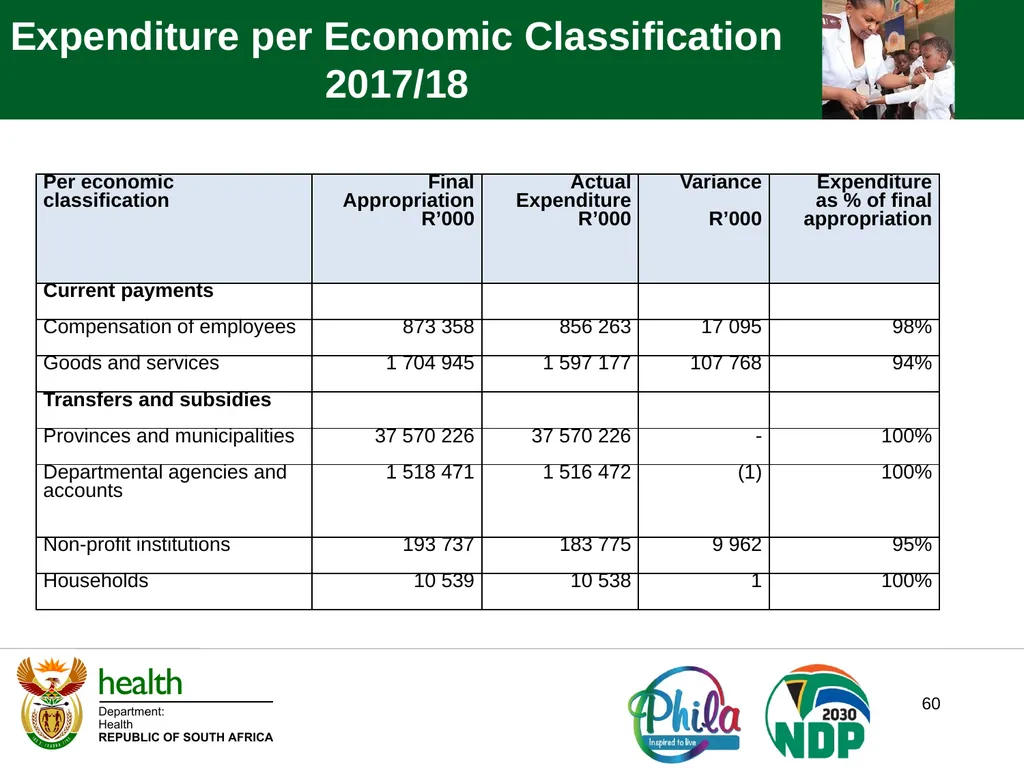
slide60. 60 Expenditure per Economic Classification
2017/18<br>
slide61. 61 Goods and Services:
Delays in receiving the invoice for the renewal of the software license from the supplier has resulted in non-payment
Invoices were delayed for Ideal Clinic Realisation and Maintenance (CRM); feedback and planning meetings were conducted in provinces
Transfer and Subsidies:
Not all Non-Profit Institutions applied for funding
Payment for capital assets:
There was no expenditure for the Drug Related Group project during 2017/18 financial year Explanations of material variances
Per Economic Classification<br>
slide62. Conditional Grants Expenditure 2017/18 62<br>
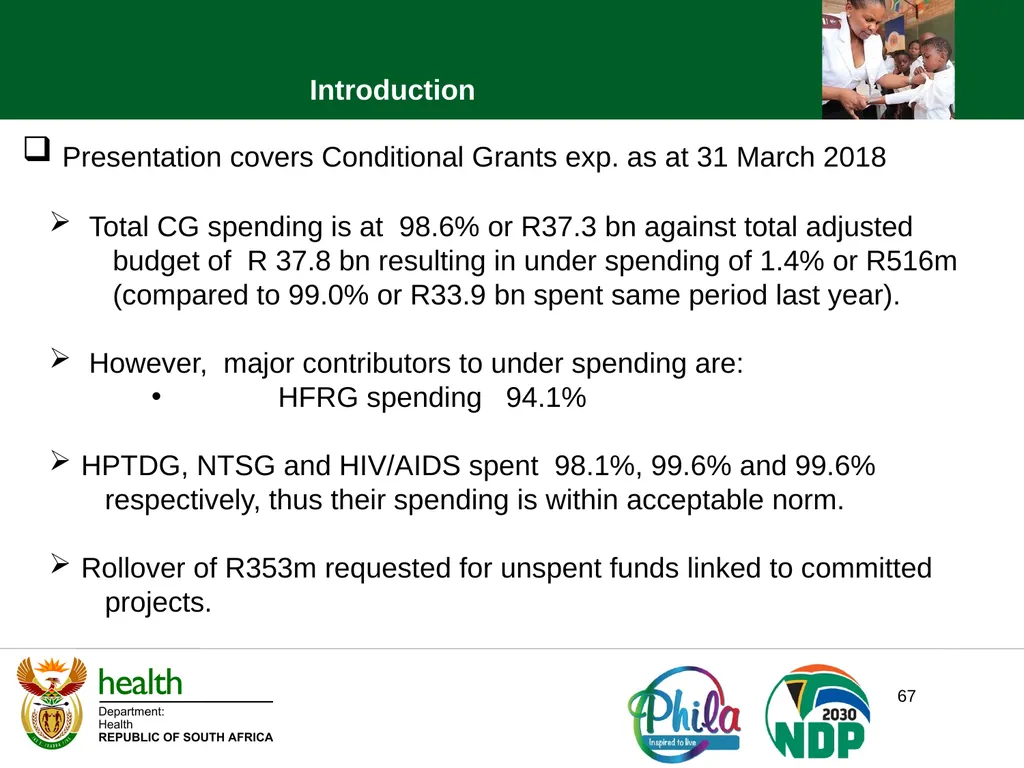
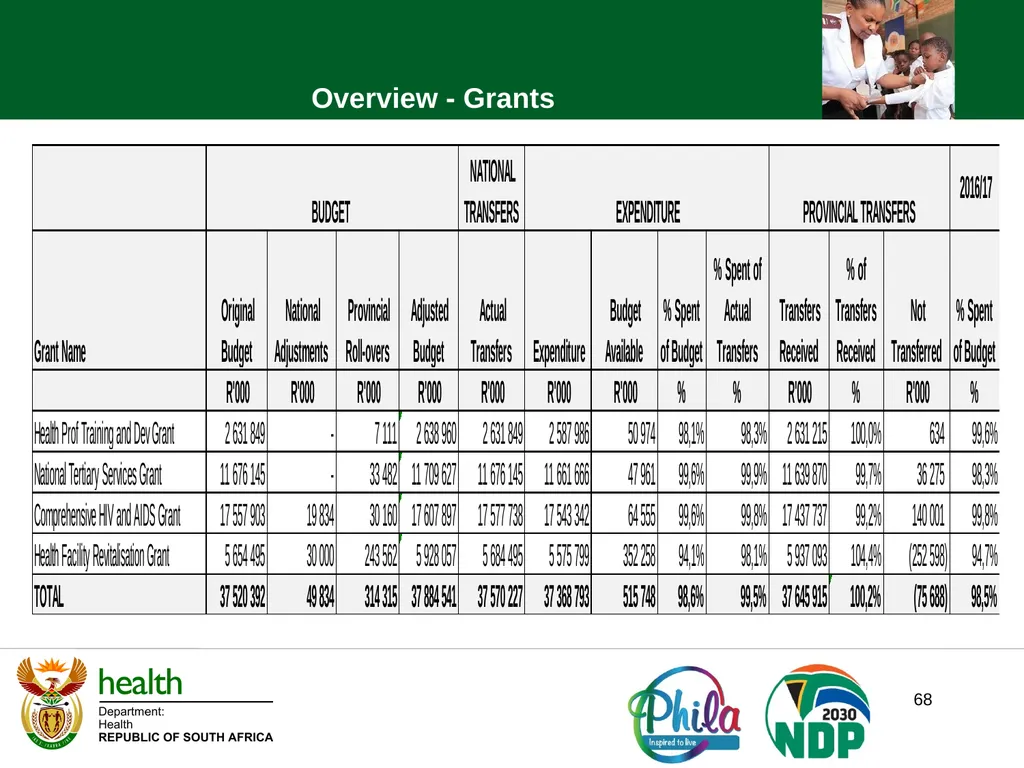
slide63. Presentation covers Conditional Grants exp. as at 31 March 2018
Total CG spending is at 98.6% or R37.3 bn against total adjusted
budget of R 37.8 bn resulting in under spending of 1.4% or R516m
(compared to 99.0% or R33.9 bn spent same period last year).
However, major contributors to under spending are:
HFRG spending 94.1%
HPTDG, NTSG and HIV/AIDS spent 98.1%, 99.6% and 99.6%
respectively, thus their spending is within acceptable norm.
Rollover of R353m requested for unspent funds linked to committed
projects. Introduction 67<br>
slide64. Overview - Grants 68<br>
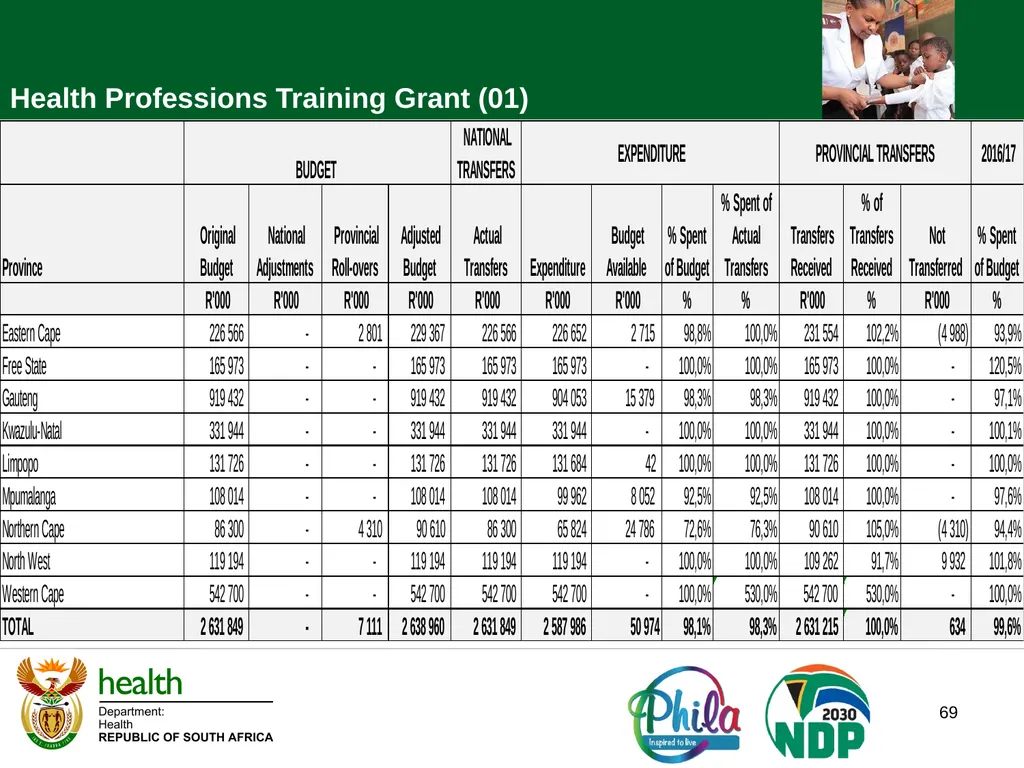
slide65. Health Professions Training Grant (01) 69<br>
slide66. Health Professions Training Grant (02) Overall spending is 98.1% in this financial year which is a decline from
prior year spending of 99.6%.
All provinces spent within the acceptable norm with the exception of MP and NC. The underspending is attributed to delays in delivery of equipment.
Rollovers have been requested and approved. 70<br>
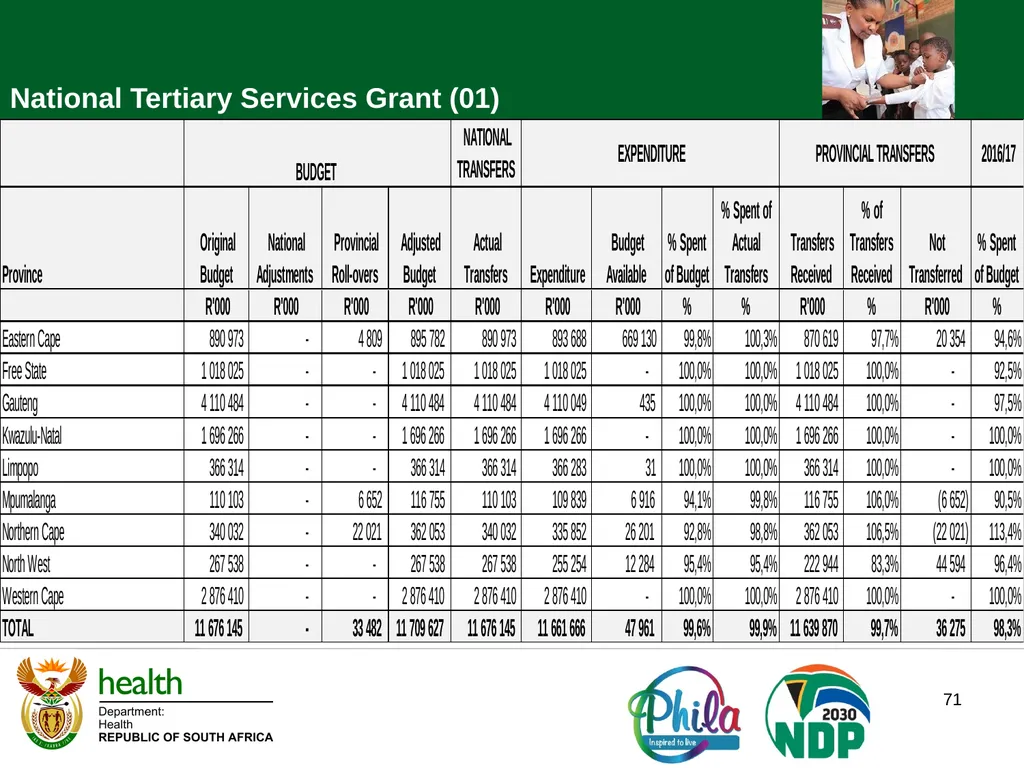
slide67. National Tertiary Services Grant (01) 71<br>
slide68. National Tertiary Services Grant (02) Overall spending is 99.6% and shows an increase compared to last
financial year where the spending was at 98.3% and is within the
acceptable norm.
All provinces spent within the acceptable norm with the exception of MP,
NC & NW that spent below the acceptable norm due to:
delays in procurement of equipment.
delays in appointment of specialists and challenges in attracting
certain category of specialists.
Rollovers have been requested and approved. 72<br>
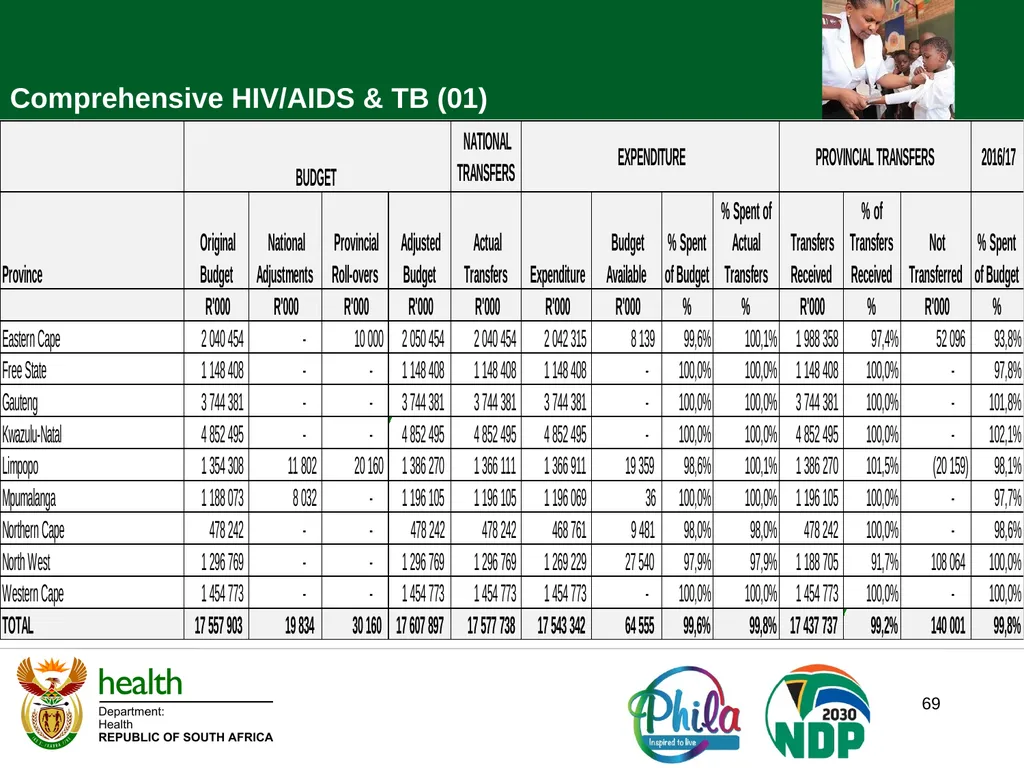
slide69. Comprehensive HIV/AIDS & TB (01) 69<br>
slide70. Comprehensive HIV/AIDS & TB (02) Overall spending is 99.6% and shows a slight decline from the previous
year spending of 99.8%.
All provinces spent within the acceptable norm
On unspent funds, rollovers were requested and approved. 70<br>
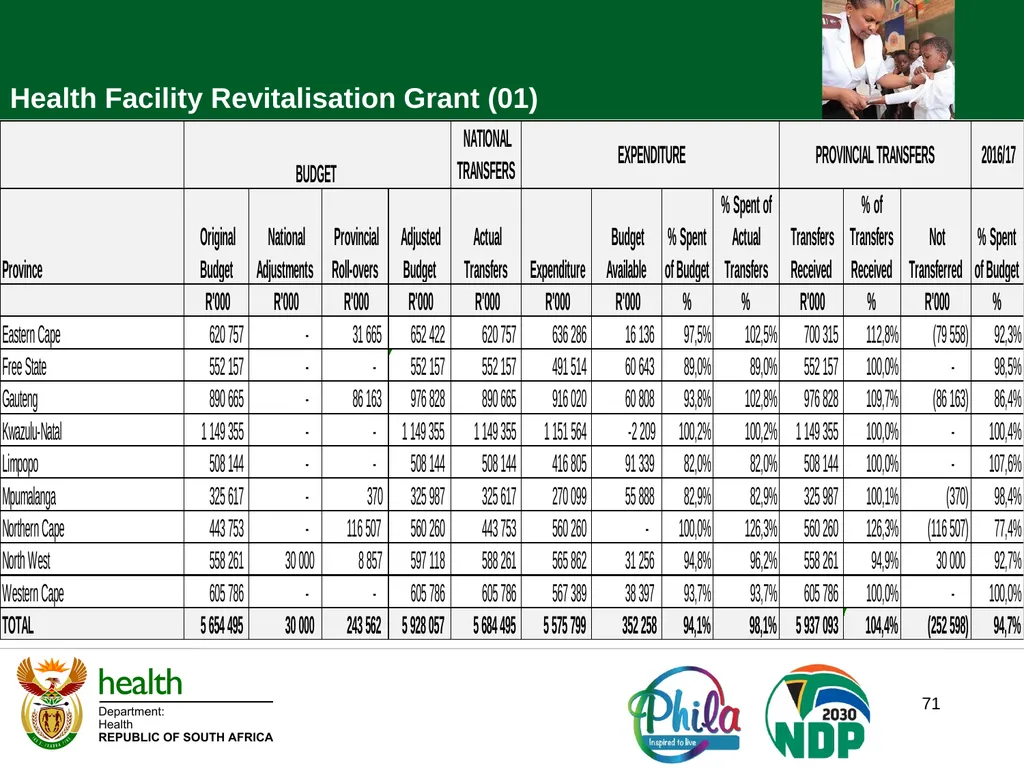
slide71. Health Facility Revitalisation Grant (01) 71<br>
slide72. Health Facility Revitalisation Grant (02) Overall spending is 94.1% and has decline from the previous year
spending of 94.7%.
Only three provinces EC, KZN & NC) spent within the acceptable norm; all other province underspent and their underspending is attributed to:
difficulty in attracting infrastructure technical skills (posts
advertised however applicants did not qualify),
Slow progress by contractors also caused by delays in Eskom connection
delays in conclusion of final accounts
late revision of the business plan – submitted during last quarter
delays in awarding of tenders by IA and implementation
However the rollovers have been requested and approved. 72<br>
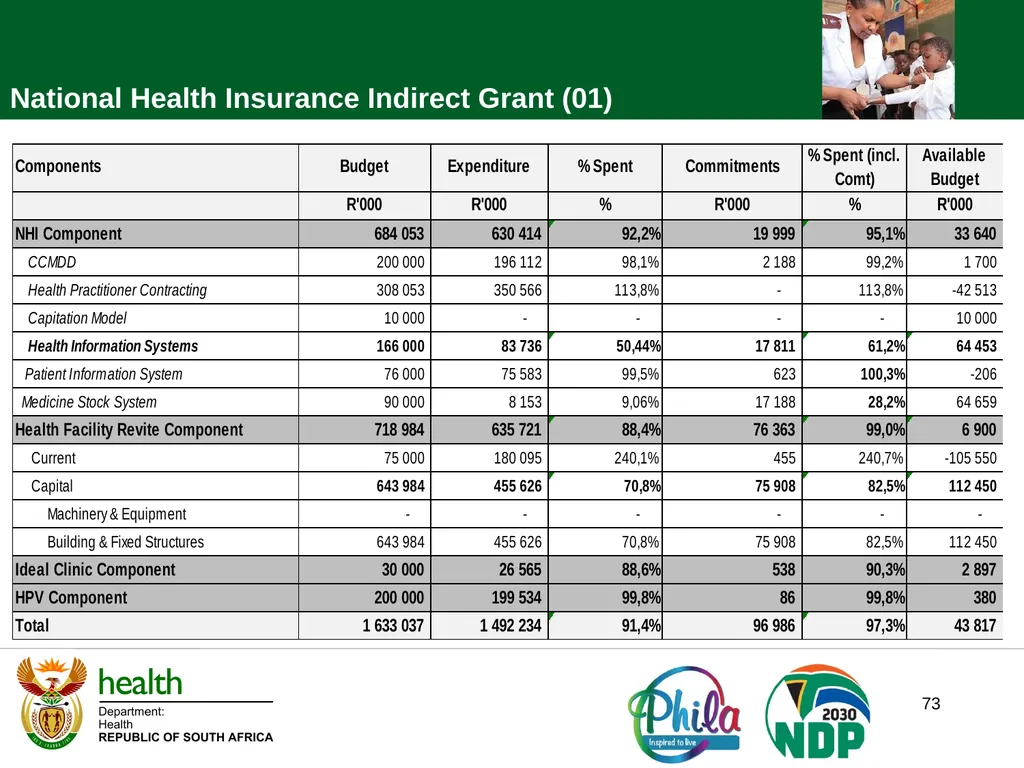
slide73. National Health Insurance Indirect Grant (01) 73<br>
slide74. National Health Insurance Indirect Grant (02) NHI component – spending is within the acceptable norm and the under
spending is attributable to CCMDD commitments at year end however
payment has already been made in this financial year.
HFR Component - component underspent and this is attributed to invoice
that could not be processed at year end as they were received very late
for processing.
Ideal Clinic component – under spending due to delays in delivery of
equipment.
HPV component – the component spent 100% and grant has been
converted to direct grant as from 2018/19 financial year 74<br>
slide75. National Health Insurance Indirect Grant (03) Capitation funding was shifted to HP Contracting due to budgetary
pressures within the component.
HP Contracting overspent due to budgetary pressures. Department has scaled down on the numbers of HPs and the contracting process has been decentralized to provinces. There is no projected overspending in future and all accruals were settled.
Health Information Systems component
Health Patient Registrations System spent full budget.
Medicine Stock Survellence system underspent due to supply chain management challenges (migration from LOGIS to G-commerce for procurement of computer equipment). 75<br>
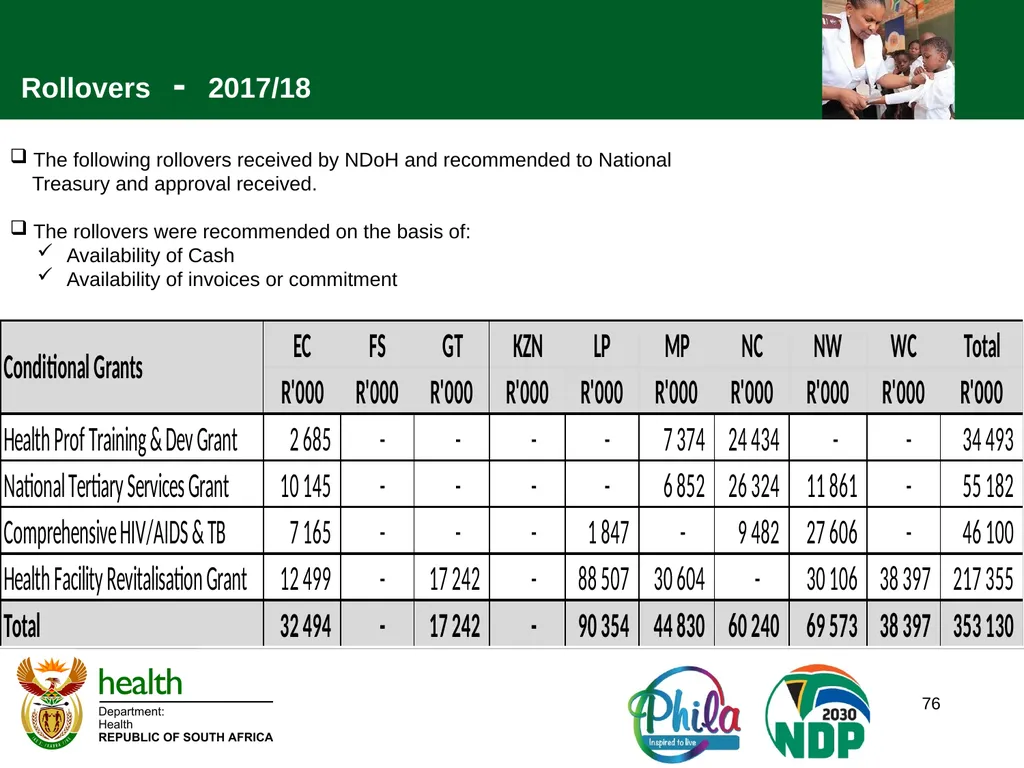
slide76. Rollovers - 2017/18 The following rollovers received by NDoH and recommended to National
Treasury and approval received.
The rollovers were recommended on the basis of:
Availability of Cash
Availability of invoices or commitment 76<br>
slide77. The End 77<br>
DIRECTOR-GENERAL:HEALTH<br>
slide2. To reflect on achievements and highlights for the FY2017/18, as outlined in the Annual Report of the National Department of Health (NDoH) 2 Purpose of the Presentation<br>
slide3. 3 Vision
A long and healthy life for all South Africans.
Mission
To improve the health status through the prevention of illnesses and the promotion of healthy lifestyles and consistently to improve the health care delivery system by focusing on access, equity, efficiency, quality and sustainability. Vision and Mission<br>
slide4. 4 The Health Sector derives its vision and mandate from NDP 2030. By 2030, South Africa should have:
Raised the life expectancy of South Africans to at least 70 years.
Progressively improved TB prevention and cure.
Reduced maternal, infant and child mortality.
Significantly reduced prevalence of non-communicable diseases.
Reduced injury, accidents and violence by 50 percent from 2010 levels.
Completed health system reforms.
Established primary healthcare teams to provide care to families and communities.
Implemented universal health coverage.
Filled posts with skilled, committed and competent individuals National Development Plan Vision 2030<br>
slide5. 5 The Annual Performance Plan 2017/18 was also designed to deliver on the MTSF commitments, namely:
Sub-outcome 1: Universal Health coverage progressively achieved through implementation of National Health Insurance
Sub-outcome 2: Improved quality of health care
Sub-outcome 3. Implement the re-engineering of Primary Health Care
Sub-outcome 4: Reduced health care costs
Sub-outcome 5: Improved human resources for health
Sub-outcome 6: Improved health management and leadership
Sub-outcome 7: Improved health facility planning and infrastructure delivery
Sub-outcome 8: HIV & AIDS and Tuberculosis prevented and successfully managed
Sub-outcome 9: Maternal, infant and child mortality reduced
Sub-outcome 10: Efficient Health Management Information System developed and implemented for improved decision making Medium Term Strategic Framework
(MTSF) 2014-2019<br>
slide6. 6 Progress Report PROGRAMME 1 : ADMINISTRATION<br>
slide7. The vacancy rate was 12.5% which exceeded DPSA’s target of 10% due to budget cuts on the CoE by Treasury.
The National Department of Health (NDoH) has embarked on a robust
reprioritisation process to ensure that critical posts are filled
Turn-around Time for recruitment process was within 4 months, which exceeded the DPSA benchmark of 6 months .
NDoH has obtained an “unqualified audit opinion” from the Auditor-General for consecutive years since 2011/12, including FY2017/18 (-the period under review). Programme 1 7<br>
slide8. Programme 1: Administration 8<br>
slide9. Programme 1: Administration 9<br>
slide10. Programme 1
Performance Improvement Strategies The one outstanding Performance Agreement was signed and filed with the DPSA after the stipulated deadline in 2017/18.
The reprioritisation process for critical vacant posts has been accomplished within the existing budgetary constraints. 10<br>
slide11. Progress Report PROGRAMME 2 : HEALTH PLANNING AND SYSTEMS ENABLEMENT 11<br>
slide12. Programme 2 National Health Insurance (NHI)
Final White Paper Policy was submitted for Cabinet consideration before end of March 2017 and published on Government Gazette on 30 June 2017
At the same time, the Minister announced the establishment of 7 NHI Implementation Structures which were published in a Government Gazette Notice on 7 July 2017. The NHI Implementation Structures are:
The Committee on Tertiary Services
The Committee on Human Resources for Health
The Committee on Health Care Benefits for National Health Insurance
National Health Pricing Advisory Committee
Committee on Consolidation of Financing Arrangements
The Committee on Health Technology Assessment for National Health Insurance
The National Health Commission
The NHI Bill & Medical Schemes Amendment Bill were submitted and approved by Cabinet. 12<br>
slide13. Programme 2: National Health Insurance, Health Planning and Systems Enablement 13<br>
slide14. Programme 2 Medicine Availability
The Centralised Chronic Medicines Dispensing and Distribution (CCMDD) programme continued to enrol new patients. Patients enrolled to receive their prescribed medicines through CCMD increased from 1 252 000 in 2015/16 to 2 166 973 in 2017/18
Patients received their prescribed medicines from over 855 pick-up points including occupational health sites, GPs and private pharmacies
Use of the stock visibility system (SVS) increased to 3 168 PHC facilities The SVS allows the back code on the package or bottle to be scanned using a specially supplied cellphone and application. When a nurse scans at a clinic the stock level is reported automatically and in real time to an electronic map of all clinics at the central tower in Pretoria.
Hospitals using the electronic stock management systems in order to strengthen demand-planning and governance increased from 228 hospitals in 2016/17 to 324 hospitals in 2017/18. 14<br>
slide15. Programme 2: National Health Insurance, Health Planning and Systems Enablement 15<br>
slide16. Programme 2: National Health Insurance, Health Planning and Systems Enablement 16<br>
slide17. Programme 2 eHealth and Information System
The Ministerial Advisory Committee on eHealth was appointed by the Minister of Health on 25 April 2017. The Committee completed a rapid review of the implementation of eHealth Strategy 2012-2016, and produced a report with recommendations in November 2017
The Department migrated routine data from stand-alone DHIS (District Health Information System) 1.4 to Web-DHIS. As at 31 March 2018, 1 759 of 3 955 facilities were able to capture data at facility level, whilst the remainder of the facilities are capturing data at sub-district or district levels because they do not have internet connectivity at facilities
. The implementation of the HPRS was expanded from 1 854 PHC facilities in 2016/17 to 2 968 PHC facilities in 2017/18. As at 31 March 2018, 20 700 149 people were registered on the HPRS linked to a Master Patient Index. 17<br>
slide18. Programme 2: National Health Insurance, Health Planning and Systems Enablement 18<br>
slide19. Programme 2: National Health Insurance, Health Planning and Systems Enablement 19<br>
slide20. Programme 2: National Health Insurance, Health Planning and Systems Enablement 20<br>
slide21. Programme 2 Quality of Care
National Survey to measure Patient Experience of Care in selected PHC facilities and hospitals.
Three Guidelines were finalised: i) Patient Experience of care survey Guideline ii) National Guideline to manage Complaints, Compliments and Suggestions for the Public Health Sector of South Africa and iii) National Guideline to manage Patient Safety Incident Reporting and Learning in the Public Health Sector of South Africa.
Norms and Standards Regulations applicable to different categories of health establishments were finalised and gazetted in February 2018, and implementation by all health establishments will be expected from 1 March 2019.
South Africa is participating in the Global Lancet Commission and has also established the Lancet National Commission consisting 15 members from public sector, Universities, private sector, Non-Governmental and Quality Institutions. The Lancet National Commission was launched in May 2017.
The Lancet National Commission and the Lancet Global Commission hosted the Global Lancet Commission meeting from 11 -13 December 2017, attended by the Chairperson of the Lancet Global Commission and National Commissioners from South Africa, Mexico, Ethiopia, Senegal, Philippines, Argentina, Nepal and Tanzania. 21<br>
slide22. Programme 2: National Health Insurance, Health Planning and Systems Enablement 22<br>
slide23. Programme 2
Performance Improvement Strategies A depot manager has been recently appointed and a revised project plan has been developed to support Provincial Medicine Procurement Unit (PMPU) functionality in the Mpumalanga Department of Health
NHI Phase 1 evaluation is currently underway. 23<br>
slide24. Progress Report PROGRAMME 3 : HIV AND AIDS, TUBERCULOSIS , MATERNAL, CHILD AND WOMEN’S HEALTH 24<br>
slide25. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health Child, Adolescent and Maternal Health
The MomConnect programme launched in August 2014 to improve access to early antenatal services and empower pregnant women reached a cumulative total of 1 888 918 pregnant women and mothers at the end of March 2018
Integrated School Health Programme (ISHP) services has contributed to the health and wellbeing of learners as they are screened for health barriers to learning
A total of 387 574 Grade 1 learners (33%) and 193 438 Grade 8 learners (21%) were screened from April 2017 to March 2018
A cumulative total of 4 339 875 learners have been screened since inception of the programme, and 504 803 learners have been identified with various health barriers to learning and referred for intervention
The human papilloma virus (HPV) coverage for the eligible girls in 2017/18 was at 82.6% for the 1st dose, and 61.3% for the 2nd dose. 25<br>
slide26. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health HIV and TB
Since the HIV Counselling and Testing (HCT) campaign was introduced in 2010, over 44 million people have been tested. A total of 13 872 315 people were tested for HIV, exceeding the annual target of 10 million for the 2017/18 financial year
At the end of March 2018, the total number of clients remaining on ART therapy (TROA) reached 4 189 070
Fewer infants are being infected with HIV. In 2017/18, a polymerase chain reaction (PCR) test done at around 10 weeks showed a 0.95% positivity rate for all babies born to HIV-positive women
New TB client treatment success rate reached 84.4%, while the TB client death rate was at 3.9% in 2017/18, the same as the rate in the previous financial year 26<br>
slide27. Programme 3: HIV and AIDS, Tuberculosis, and Maternal, Child and Women’s Health 27<br>
slide28. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health 28<br>
slide29. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health 29<br>
slide30. Programme 3: HIV and AIDS, Tuberculosis, and
Maternal, Child and Women’s Health 30<br>
slide31. Programme 3: HIV and AIDS, Tuberculosis, and Maternal, Child and Women’s Health 31<br>
slide32. Programme 3
Performance Improvement Strategies Development of the HIV Strategic Plan outlining key actions and strategies for the public health system will be done during the 2018/19 financial year.
The District Implementation Plans to reach 90-90-90 targets for HIV and TB will be developed as part of the District Health Plans. 32<br>
slide33. Progress Report PROGRAMME 4 : PRIMARY HEALTH CARE (PHC) SERVICES 33<br>
slide34. Programme 4
Primary Health Care Services As at the end of March 2018, a cumulative total of 1 507 facilities qualified as Ideal Clinics. This achievement has been enabled by collaboration between the NDoH and National Treasury in resolving supply chain management challenges faced by clinics, especially with regard to equipment, essential supplies and infrastructure.
Environmental and port health services: A total of 20 district and metropolitan municipalities rendering municipal health services were audited, and 13 of the 20 reached 51% and above.
10 Ports of Entry (PoEs) were assessed and found to be compliant with the International Health Regulations, 2005.
Orientation workshops to Government Departments on the national guide for healthy meal provision in the workplace were conducted in all nine provinces to assist employees adopt healthy eating habits. 34<br>
slide35. Programme 4:
Primary Health Care Services 35<br>
slide36. Programme 4
Primary Health Care Services 36<br>
slide37. Programme 4
Primary Health Care Services 37<br>
slide38. Programme 4
Primary Health Care Services 38<br>
slide39. Programme 4
Primary Health Care Services 39<br>
slide40. Programme 4
Performance Improvement Strategies Malaria indoor residual spraying (IRS) will be increased, and will commence earlier than usual in the endemic provinces. Killing of larva (where appropriate) will be strengthened and rolled out in the winter. Collaboration with neighbouring countries affected by malaria will also be strengthened and scaled up 40<br>
slide41. 41 Progress Report PROGRAMME 5 : Hospitals, Tertiary Services and Workforce Development<br>
slide42. Programme 5 A national core curriculum was finalised for the new three-year diploma in general nursing and a one-year diploma in midwifery. The three-year diploma programme aims to enable graduates to function as clinically focused, service-oriented, general nurses, able to manage low-risk health problems along the continuum of care.
Eight of the 17 public nursing colleges were supported to develop customised curricula in preparation for programme accreditation
In the 2017/18 financial year, staffing norms were implemented for the PHC levels. More than 2 000 PHC facility managers in seven provinces were trained on the concept and methodology for determining staffing needs based on workload. 42<br>
slide43. Programme 5: Hospitals, Tertiary Services and Workforce Development 43<br>
slide44. 44 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide45. 45 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide46. 46 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide47. 47 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide48. 48 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide49. 49 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide50. 50 Programme 5: Hospitals, Tertiary Services and Workforce Development<br>
slide51. Programme 5
Performance Improvement Strategies Staffing norms at the higher levels of care (regional, tertiary and central hospitals) will be developed following completion of the process at district hospital level.
Forensic Chemistry Laboratories will implement a targeted approach to analysis, in particular toxicology analysis, which will significantly reduce the toxicology backlog.
Blood alcohol and food analysis turnaround time, and the repair and maintenance of equipment, will be enhanced to improve output.
All outstanding activities in the area of forensic pathology mortuaries will be facilitated through quarterly engagements with forensic pathology managers in all provinces.
The 793 infrastructure projects that failed to reach practical completion by end of March 2018 will form part of planned projects in the 2018/19 financial year
Provincial workshops are scheduled for 2018/19 to ensure that all managers access the already established knowledge hub, coaching and mentoring programme 51<br>
slide52. 52 Progress Report PROGRAMME 6 : Health Regulation and Compliance Management<br>
slide53. Programme 6: Health Regulation and Compliance Management The first Board of SAHPRA was appointed by the Minister for a three-year term of office. The Acting Chief Executive Officer of the Authority was appointed following the first meeting of the Board
The National Public Health Institute of South Africa (NAPHISA) Bill was also tabled for consideration at the Parliamentary Portfolio Committee of Health
The Compensation Commissioner for Occupational Diseases and Occupational Health paid about R254 million to 10 409 claimants, of which R110 million went to neighbouring countries. One Stop Service Centres were opened in Burgersfort and Kuruman, one in Botswana, two in Lesotho, two in Mozambique and two in Swaziland to give ex-mineworkers increased access to decentralised services. 53<br>
slide54. 54 Programme 6: Health Regulation and Compliance Management<br>
slide55. Human Resource Management 55<br>
slide56. Human Resource Management 56<br>
slide57. Financial Management 57<br>
slide58. 58 Expenditure per programme
2017/18<br>
slide59. 59 Programme 1: Administration
Delays in receiving the invoice for the renewal of the software license from the supplier has resulted in non-payment and the lease contract for the Forensic Chemistry Laboratory was not signed.
Programme 2: National Health Insurance, Health Planning and System Enablement
There was no expenditure for the Drug Related Group project during 201718 year.
New in-kind grant for Medicine Stock System was experiencing initial difficulties to spend funds.
Programme 4: Primary Health Care Services
Invoices were delayed for Ideal Clinic Realisation and Maintenance (ICRM) feedback and planning meetings that were conducted in provinces. Explanations of material variances
Per Programme<br>
slide60. 60 Expenditure per Economic Classification
2017/18<br>
slide61. 61 Goods and Services:
Delays in receiving the invoice for the renewal of the software license from the supplier has resulted in non-payment
Invoices were delayed for Ideal Clinic Realisation and Maintenance (CRM); feedback and planning meetings were conducted in provinces
Transfer and Subsidies:
Not all Non-Profit Institutions applied for funding
Payment for capital assets:
There was no expenditure for the Drug Related Group project during 2017/18 financial year Explanations of material variances
Per Economic Classification<br>
slide62. Conditional Grants Expenditure 2017/18 62<br>
slide63. Presentation covers Conditional Grants exp. as at 31 March 2018
Total CG spending is at 98.6% or R37.3 bn against total adjusted
budget of R 37.8 bn resulting in under spending of 1.4% or R516m
(compared to 99.0% or R33.9 bn spent same period last year).
However, major contributors to under spending are:
HFRG spending 94.1%
HPTDG, NTSG and HIV/AIDS spent 98.1%, 99.6% and 99.6%
respectively, thus their spending is within acceptable norm.
Rollover of R353m requested for unspent funds linked to committed
projects. Introduction 67<br>
slide64. Overview - Grants 68<br>
slide65. Health Professions Training Grant (01) 69<br>
slide66. Health Professions Training Grant (02) Overall spending is 98.1% in this financial year which is a decline from
prior year spending of 99.6%.
All provinces spent within the acceptable norm with the exception of MP and NC. The underspending is attributed to delays in delivery of equipment.
Rollovers have been requested and approved. 70<br>
slide67. National Tertiary Services Grant (01) 71<br>
slide68. National Tertiary Services Grant (02) Overall spending is 99.6% and shows an increase compared to last
financial year where the spending was at 98.3% and is within the
acceptable norm.
All provinces spent within the acceptable norm with the exception of MP,
NC & NW that spent below the acceptable norm due to:
delays in procurement of equipment.
delays in appointment of specialists and challenges in attracting
certain category of specialists.
Rollovers have been requested and approved. 72<br>
slide69. Comprehensive HIV/AIDS & TB (01) 69<br>
slide70. Comprehensive HIV/AIDS & TB (02) Overall spending is 99.6% and shows a slight decline from the previous
year spending of 99.8%.
All provinces spent within the acceptable norm
On unspent funds, rollovers were requested and approved. 70<br>
slide71. Health Facility Revitalisation Grant (01) 71<br>
slide72. Health Facility Revitalisation Grant (02) Overall spending is 94.1% and has decline from the previous year
spending of 94.7%.
Only three provinces EC, KZN & NC) spent within the acceptable norm; all other province underspent and their underspending is attributed to:
difficulty in attracting infrastructure technical skills (posts
advertised however applicants did not qualify),
Slow progress by contractors also caused by delays in Eskom connection
delays in conclusion of final accounts
late revision of the business plan – submitted during last quarter
delays in awarding of tenders by IA and implementation
However the rollovers have been requested and approved. 72<br>
slide73. National Health Insurance Indirect Grant (01) 73<br>
slide74. National Health Insurance Indirect Grant (02) NHI component – spending is within the acceptable norm and the under
spending is attributable to CCMDD commitments at year end however
payment has already been made in this financial year.
HFR Component - component underspent and this is attributed to invoice
that could not be processed at year end as they were received very late
for processing.
Ideal Clinic component – under spending due to delays in delivery of
equipment.
HPV component – the component spent 100% and grant has been
converted to direct grant as from 2018/19 financial year 74<br>
slide75. National Health Insurance Indirect Grant (03) Capitation funding was shifted to HP Contracting due to budgetary
pressures within the component.
HP Contracting overspent due to budgetary pressures. Department has scaled down on the numbers of HPs and the contracting process has been decentralized to provinces. There is no projected overspending in future and all accruals were settled.
Health Information Systems component
Health Patient Registrations System spent full budget.
Medicine Stock Survellence system underspent due to supply chain management challenges (migration from LOGIS to G-commerce for procurement of computer equipment). 75<br>
slide76. Rollovers - 2017/18 The following rollovers received by NDoH and recommended to National
Treasury and approval received.
The rollovers were recommended on the basis of:
Availability of Cash
Availability of invoices or commitment 76<br>
slide77. The End 77<br>