
The MOBILE Study doi:10.1001/jama.2021.7444 Scott























Description: The MOBILE Study doi:10.1001jama.2021.7444 Scott Stadler, PharmD Candidate Funding Conflict of interest All authors received grant funding from Dexcom to their institution for the conduct of the submitted study Dexcom representatives
Related Topics
Download Presentation
"The MOBILE Study doi:10.1001/jama.2021.7444 Scott" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
slide1. The MOBILE Study
doi:10.1001/jama.2021.7444 Scott Stadler,
PharmD Candidate<br>
slide2. Funding / Conflict of interest All authors received grant funding from Dexcom to their institution for the conduct of the submitted study
Dexcom representatives participated in development of the design of the trial, but were not involved in management, or analysis other than providing the process for the uploading of continuous glucose monitoring data; and were not involved in the preparation of the manuscript or the decision to submit the manuscript for publication.<br>
slide3. Background<br>
slide4. Continuous Glucose Monitors How do they work?
Continuous glucose monitoring (CGM) devices measure interstitial glucose via small sensors worn on the back of the upper arm or on the abdomen. Users can scan them using affiliated receivers or their smartphone to view their glucose readings.
Additionally, real-time CGM devices monitor as frequently as every 5 minutes and can alarm the user of dangerously low or high glucose levels<br>
slide5. Continuous Glucose Monitors How are they different from traditional monitors?
CGMs provide continuous data, whereas traditional blood glucose monitors give insight to only a snapshot in time.
Interstitial glucose levels positively correlate with blood glucose levels but can occasionally lag behind true blood glucose levels especially in instances where blood glucose is rapidly increasing or decreasing.<br>
slide6. Continuous Glucose Monitors Where are they used?
For patients with type 1 or type 2 diabetes using intensive insulin regimens, there is strong evidence for use of CGMs to lower/maintain A1c and reduce the incidence of severe hypoglycemia
Use of this technology in patients with type 2 diabetes using basal insulin without prandial insulin is not well studied. Roughly 20% of patients with type 2 diabetes in the United States fall within this category<br>
slide7. Methodology<br>
slide8. Study Design Type of study:
Multicenter, randomized, open-label, parallel-group trial
15 centers in the US participated
Duration: 8 months
The protocol and informed consent form were approved by a central IRB for 14 centers and a local board for 1 center.<br>
slide9. Outcomes Primary: HbA1c level at 8 months adjusted for the baseline value
Key secondary:
CGM-measured time in the target glucose range of 70 to 180 mg/dl
Change in CGM time-hyperglycemic, defined as >250 mg/dL
Mean glucose level at 8 months adjusted for the baseline value
Safety:
Severe hypoglycemia (defined as an event that required assistance from another person to administer carbohydrates or other resuscitative action)
Severe hyperglycemia including DKA and serious adverse events regardless of causality<br>
slide10. Interventions Participants in both arms were provided with a Bluetooth-enabled BGM and test strips. Participants in the CGM arm were provided with a Dexcom G6 CGM
The BGM group was instructed to test fasting and postprandial 1 to 3 times daily
The CGM group was instructed to perform BGM testing as needed, especially is CGM readings did not match symptoms
Follow up clinic visits for both treatment groups to review glucose data and self-titration of insulin occurred after 2 weeks and 1 and 8 months, with telephone visits at 2, 4, and 6 months. Glucose record data and management suggestions were sent to participant’s PCP
A1c was measured at 3 months and at 8 months<br>
slide11. Study population<br>
slide12. Study Design Method of randomization:
Patients were randomized with a computer-generated sequence to either the CGM or BGM group in a 2:1 ratio, using a permuted block design stratified by site.
117 participants were randomized to CGM and 59 participants were randomized to BGM<br>
slide14. Inclusion criteria Age > 30 years old
Type 2 diabetes
Comprehends written and spoken English
Using 1-2 injections of basal or intermediate acting insulin daily for at least 6 months prior to screening
HbA1c between 7.8-11.5% inclusive at enrollment (by site’s POC or local lab)
Assessment by clinician that patient is able and willing to wear a CGM device
No use of a personal real-time CGM within 3 months of study entry (may have used intermittent blinded CGM in the past)
Self-monitors blood glucose on average at least 3 times per week (self-reported) during the month prior to screening
Stable medication regimen (medication class) during the 3 months prior to screening
Has a smart phone compatible with CGM and BGM systems and is willing to utilize a study issued blood glucose meter
Has diabetes managed by a primary care physician or nurse practitioner/physician assistant<br>
slide15. Exclusion criteria Regular use of short acting insulin in the 3 months prior to entry visit or planning to initiate prandial insulin or short acting insulin
Pregnancy (as demonstrated by a positive test) at time of screening or planning to become pregnant during the study
Weight reduction medications, programs or surgery.
Concomitant disease or condition that may compromise patient safety including and not limited to severe mental illness, a diagnosed or suspected eating disorder or any uncontrolled long-term medical/ psychiatric condition that would interfere with study related tasks or visits, based on investigator judgment.
Known (or suspected) significant allergy to medical grade adhesives
Renal disease defined as estimated Glomerular Filtration Rate (eGFR) <30 mL/min/1.73 m2 , obtained within 4 months of screening visit
Anticipated acute uses of glucocorticoids (oral, injectable, or IV) that could affect glycemic control and impact HbA1c – such as frequent steroid bursts required for inflammatory arthritis or inflammatory bowel disease, recurrent lumbar epidural steroid injections, etc. (Long-term stable glucocorticoid doses are allowed, such as when used for the treatment of rheumatoid arthritis or Addison’s disease).
Acute conditions that could impact the stability of a HbA1c measurement such as GI blood loss, recent (with 3 months of entry visit) or anticipated red blood cell transfusion or erythropoietin administration.
Followed for their diabetes management by a study PI or sub-investigator
Diabetes (glucose) management in the prior 6 months (study entry) under the guidance of a diabetes specialist
Participation in another pharmaceutical or device trial at the time of enrollment or during the study<br>
slide16. Statistical Analysis<br>
slide17. Statistical Tests used The primary analysis was a treatment group comparison of HbA1c level at 8 months in a longitudinal mixed-effects linear model with baseline HbA1c as a fixed effect and clinical site as a random effect.
Statistical significance was defined as P< .05 for the primary analysis and for the 3 key secondary outcomes prespecified as part of a hierarchy with the primary outcome
Per-protocol analysis was used to restrict the analytic cohort by excluding the following:
Participants in the BGM Group performing blood glucose meter testing on average less than 1 time per day based on self-report over the full 8 months were excluded.
Participants in the CGM Group using CGM on less than 70% of days over the full 8 months or not using CGM on at least one day in month 8 were excluded
Participants missing 8-month visit (or completing the visit more than 30 days before or after the target date were excluded
Participants in the BGM Group who used an unblinded CGM at any point during the study phase were excluded<br>
slide18. results<br>
slide19. Outcomes The study was completed by 108 participants in the CGM group and 57 in the BGM group.
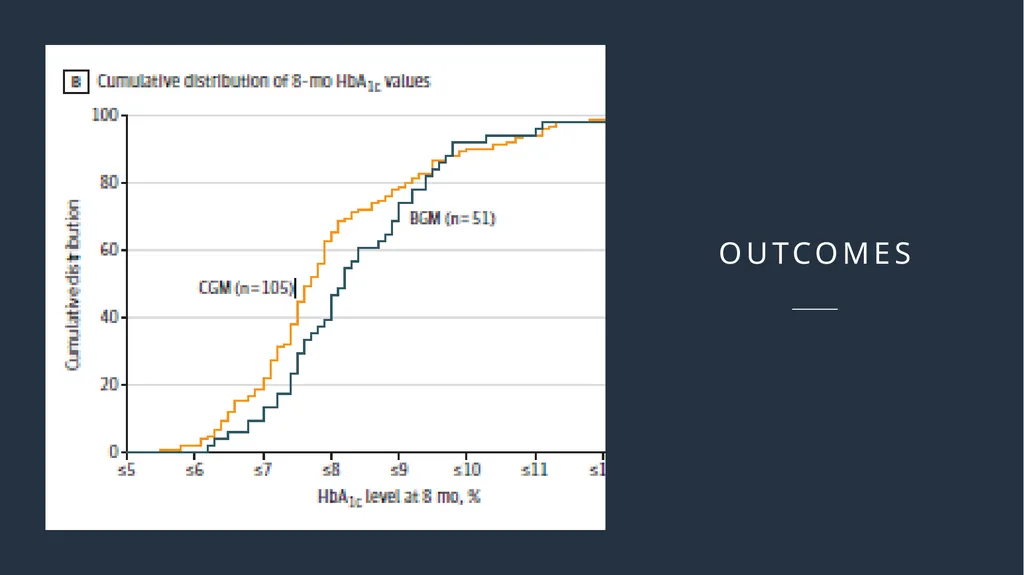
Primary: The mean HbA1c level, which was 9.1% in the CGM group and 9.0% in the BGM group at baseline, decreased to 8.0% vs 8.4%, respectively, at the 8-month primary outcome (adjusted difference in mean change in HbA1c level, −0.4%[95%CI, −0.8% to −0.1%]; P = .02
Key secondary:
The percent of time in range of 70-180 mg/dL, which was 40% in the CGM and BGM group at baseline, increased to 59% and 43%, respectively. P<.001
The percent of time >250 mg/dL, which was 26% in the CGM group and 25% in the BGM group at baseline, decreased to 11% in the CGM group and increased to 27% in the BGM group. P<.001
The mean glucose, which was 209 mg/dL in the CGM group and 206 mg/dL at baseline, deceased to 179 in the CGM group and remained 206 in the BGM group. P<.001<br>
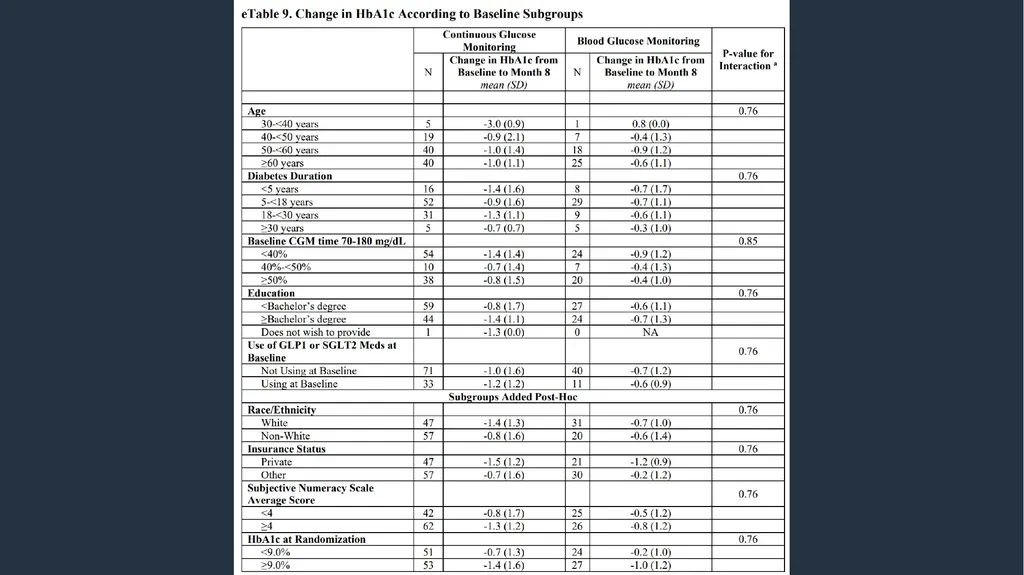
slide20. Outcomes Among participants with baseline HbA1c levels of 8.5% or greater, there was not a statistically significant treatment group difference in 8-month HbA1c level (P = .10)
There was no clinically or statistically significant difference in severe hypoglycemic or hyperglycemic events between groups<br>
slide21. Outcomes<br>
slide22. Authors’ Conclusions The authors concluded that patients with poorly controlled type 2 diabetes using basal insulin without prandial insulin saw significantly lower HbA1c levels at 8 months
Limitations discussed by authors:
Unsure whether glycemic improvement seen with CGM would be sustained after 8 months
Because of COVID-19, some participants were not able to receive an HbA1c at 8 months
The study participants had more contact with clinical staff than in most practice settings<br>
slide23. Discussion Interpretation of results
CGM appears to be an effective method to reduce A1c in patients with an A1c 8.5% or lower.
For patients with A1c >8.5%, there may be other more important problems to address first
Lack of need to test using BGM may make this technology stand out in the real world
Is the data compelling enough for insurance companies to cover CGM in this new subset of patients?
At GIM, the patients we manage and consider “uncontrolled” would fall within the groups that were not statistically different between treatment groups<br>
slide24. Resources Martens T, Beck RW, Bailey R, et al. Effect of Continuous Glucose Monitoring on Glycemic Control in Patients With Type 2 Diabetes Treated With Basal Insulin: A Randomized Clinical Trial. JAMA. 2021;325(22):2262–2272. doi:10.1001/jama.2021.7444
American Diabetes Association. 2021. Standards of Medical Care in Diabetes - 2021. Retrieved from http://care.diabetesjournal.org<br>
PharmD Candidate<br>
slide2. Funding / Conflict of interest All authors received grant funding from Dexcom to their institution for the conduct of the submitted study
Dexcom representatives participated in development of the design of the trial, but were not involved in management, or analysis other than providing the process for the uploading of continuous glucose monitoring data; and were not involved in the preparation of the manuscript or the decision to submit the manuscript for publication.<br>
slide3. Background<br>
slide4. Continuous Glucose Monitors How do they work?
Continuous glucose monitoring (CGM) devices measure interstitial glucose via small sensors worn on the back of the upper arm or on the abdomen. Users can scan them using affiliated receivers or their smartphone to view their glucose readings.
Additionally, real-time CGM devices monitor as frequently as every 5 minutes and can alarm the user of dangerously low or high glucose levels<br>
slide5. Continuous Glucose Monitors How are they different from traditional monitors?
CGMs provide continuous data, whereas traditional blood glucose monitors give insight to only a snapshot in time.
Interstitial glucose levels positively correlate with blood glucose levels but can occasionally lag behind true blood glucose levels especially in instances where blood glucose is rapidly increasing or decreasing.<br>
slide6. Continuous Glucose Monitors Where are they used?
For patients with type 1 or type 2 diabetes using intensive insulin regimens, there is strong evidence for use of CGMs to lower/maintain A1c and reduce the incidence of severe hypoglycemia
Use of this technology in patients with type 2 diabetes using basal insulin without prandial insulin is not well studied. Roughly 20% of patients with type 2 diabetes in the United States fall within this category<br>
slide7. Methodology<br>
slide8. Study Design Type of study:
Multicenter, randomized, open-label, parallel-group trial
15 centers in the US participated
Duration: 8 months
The protocol and informed consent form were approved by a central IRB for 14 centers and a local board for 1 center.<br>
slide9. Outcomes Primary: HbA1c level at 8 months adjusted for the baseline value
Key secondary:
CGM-measured time in the target glucose range of 70 to 180 mg/dl
Change in CGM time-hyperglycemic, defined as >250 mg/dL
Mean glucose level at 8 months adjusted for the baseline value
Safety:
Severe hypoglycemia (defined as an event that required assistance from another person to administer carbohydrates or other resuscitative action)
Severe hyperglycemia including DKA and serious adverse events regardless of causality<br>
slide10. Interventions Participants in both arms were provided with a Bluetooth-enabled BGM and test strips. Participants in the CGM arm were provided with a Dexcom G6 CGM
The BGM group was instructed to test fasting and postprandial 1 to 3 times daily
The CGM group was instructed to perform BGM testing as needed, especially is CGM readings did not match symptoms
Follow up clinic visits for both treatment groups to review glucose data and self-titration of insulin occurred after 2 weeks and 1 and 8 months, with telephone visits at 2, 4, and 6 months. Glucose record data and management suggestions were sent to participant’s PCP
A1c was measured at 3 months and at 8 months<br>
slide11. Study population<br>
slide12. Study Design Method of randomization:
Patients were randomized with a computer-generated sequence to either the CGM or BGM group in a 2:1 ratio, using a permuted block design stratified by site.
117 participants were randomized to CGM and 59 participants were randomized to BGM<br>
slide14. Inclusion criteria Age > 30 years old
Type 2 diabetes
Comprehends written and spoken English
Using 1-2 injections of basal or intermediate acting insulin daily for at least 6 months prior to screening
HbA1c between 7.8-11.5% inclusive at enrollment (by site’s POC or local lab)
Assessment by clinician that patient is able and willing to wear a CGM device
No use of a personal real-time CGM within 3 months of study entry (may have used intermittent blinded CGM in the past)
Self-monitors blood glucose on average at least 3 times per week (self-reported) during the month prior to screening
Stable medication regimen (medication class) during the 3 months prior to screening
Has a smart phone compatible with CGM and BGM systems and is willing to utilize a study issued blood glucose meter
Has diabetes managed by a primary care physician or nurse practitioner/physician assistant<br>
slide15. Exclusion criteria Regular use of short acting insulin in the 3 months prior to entry visit or planning to initiate prandial insulin or short acting insulin
Pregnancy (as demonstrated by a positive test) at time of screening or planning to become pregnant during the study
Weight reduction medications, programs or surgery.
Concomitant disease or condition that may compromise patient safety including and not limited to severe mental illness, a diagnosed or suspected eating disorder or any uncontrolled long-term medical/ psychiatric condition that would interfere with study related tasks or visits, based on investigator judgment.
Known (or suspected) significant allergy to medical grade adhesives
Renal disease defined as estimated Glomerular Filtration Rate (eGFR) <30 mL/min/1.73 m2 , obtained within 4 months of screening visit
Anticipated acute uses of glucocorticoids (oral, injectable, or IV) that could affect glycemic control and impact HbA1c – such as frequent steroid bursts required for inflammatory arthritis or inflammatory bowel disease, recurrent lumbar epidural steroid injections, etc. (Long-term stable glucocorticoid doses are allowed, such as when used for the treatment of rheumatoid arthritis or Addison’s disease).
Acute conditions that could impact the stability of a HbA1c measurement such as GI blood loss, recent (with 3 months of entry visit) or anticipated red blood cell transfusion or erythropoietin administration.
Followed for their diabetes management by a study PI or sub-investigator
Diabetes (glucose) management in the prior 6 months (study entry) under the guidance of a diabetes specialist
Participation in another pharmaceutical or device trial at the time of enrollment or during the study<br>
slide16. Statistical Analysis<br>
slide17. Statistical Tests used The primary analysis was a treatment group comparison of HbA1c level at 8 months in a longitudinal mixed-effects linear model with baseline HbA1c as a fixed effect and clinical site as a random effect.
Statistical significance was defined as P< .05 for the primary analysis and for the 3 key secondary outcomes prespecified as part of a hierarchy with the primary outcome
Per-protocol analysis was used to restrict the analytic cohort by excluding the following:
Participants in the BGM Group performing blood glucose meter testing on average less than 1 time per day based on self-report over the full 8 months were excluded.
Participants in the CGM Group using CGM on less than 70% of days over the full 8 months or not using CGM on at least one day in month 8 were excluded
Participants missing 8-month visit (or completing the visit more than 30 days before or after the target date were excluded
Participants in the BGM Group who used an unblinded CGM at any point during the study phase were excluded<br>
slide18. results<br>
slide19. Outcomes The study was completed by 108 participants in the CGM group and 57 in the BGM group.
Primary: The mean HbA1c level, which was 9.1% in the CGM group and 9.0% in the BGM group at baseline, decreased to 8.0% vs 8.4%, respectively, at the 8-month primary outcome (adjusted difference in mean change in HbA1c level, −0.4%[95%CI, −0.8% to −0.1%]; P = .02
Key secondary:
The percent of time in range of 70-180 mg/dL, which was 40% in the CGM and BGM group at baseline, increased to 59% and 43%, respectively. P<.001
The percent of time >250 mg/dL, which was 26% in the CGM group and 25% in the BGM group at baseline, decreased to 11% in the CGM group and increased to 27% in the BGM group. P<.001
The mean glucose, which was 209 mg/dL in the CGM group and 206 mg/dL at baseline, deceased to 179 in the CGM group and remained 206 in the BGM group. P<.001<br>
slide20. Outcomes Among participants with baseline HbA1c levels of 8.5% or greater, there was not a statistically significant treatment group difference in 8-month HbA1c level (P = .10)
There was no clinically or statistically significant difference in severe hypoglycemic or hyperglycemic events between groups<br>
slide21. Outcomes<br>
slide22. Authors’ Conclusions The authors concluded that patients with poorly controlled type 2 diabetes using basal insulin without prandial insulin saw significantly lower HbA1c levels at 8 months
Limitations discussed by authors:
Unsure whether glycemic improvement seen with CGM would be sustained after 8 months
Because of COVID-19, some participants were not able to receive an HbA1c at 8 months
The study participants had more contact with clinical staff than in most practice settings<br>
slide23. Discussion Interpretation of results
CGM appears to be an effective method to reduce A1c in patients with an A1c 8.5% or lower.
For patients with A1c >8.5%, there may be other more important problems to address first
Lack of need to test using BGM may make this technology stand out in the real world
Is the data compelling enough for insurance companies to cover CGM in this new subset of patients?
At GIM, the patients we manage and consider “uncontrolled” would fall within the groups that were not statistically different between treatment groups<br>
slide24. Resources Martens T, Beck RW, Bailey R, et al. Effect of Continuous Glucose Monitoring on Glycemic Control in Patients With Type 2 Diabetes Treated With Basal Insulin: A Randomized Clinical Trial. JAMA. 2021;325(22):2262–2272. doi:10.1001/jama.2021.7444
American Diabetes Association. 2021. Standards of Medical Care in Diabetes - 2021. Retrieved from http://care.diabetesjournal.org<br>