
Realigning DDS Clinical-Behavioral Supports Better
FD
Published · 40 slides · 0 views

1 / 1


































Description
Realigning DDS Clinical-Behavioral Supports Better Understanding PBS and ABA Peter Tolisano, Psy.D. ABPP Board Certified in Clinical Psychology Director of Psychological Services Connecticut Department of Developmental Services Vincent
Related Topics
Share
Embed code
Download this presentation From Below
"Realigning DDS Clinical-Behavioral Supports Better" is the property of its rightful owner. Permission is granted to download and print the materials on this website for personal, non-commercial use only, and to display it on your personal computer provided you do not modify the materials and that you retain all copyright notices contained in the materials. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
01
Realigning DDS Clinical-Behavioral Supports
Better Understanding PBS and ABA
Peter Tolisano, Psy.D. ABPP
Board Certified in Clinical Psychology
Director of Psychological Services
Connecticut Department of Developmental Services
Vincent Covino, Ph.D.
Director of Clinical Services, North Region
Connecticut Department of Developmental Services<br>
02
Realigning Clinical-Behavioral Supports Goals of Training:
1. Identify the similarities and differences that exist between the Positive Behavior Support and Applied Behavior Analysis.
2. Grasp the limitations of a Medical Model and coercive methods.
3. Appreciate the individual and systemic benefits of a Positive Behavior Support approach.
4. Better understand the key components of a comprehensive Positive Behavior Support plan.
5. Learn the updated DDS qualifying requirements and process for PBS versus ABA providers.<br>
03
3 Realigning Clinical-Behavioral Supports
In general, Positive Behavior Support (PBS) constitutes a distinct discipline and a different service delivery model from Applied Behavioral Analysis (ABA)
While the science of behavior underlies both PBS and ABA (e.g., functional assessment as a cornerstone), ABA is primarily guided by the behavioral research literature.
PBS, in addition to guidance from various research literatures, places an emphasis on cultural and social values, as well as supports the movement toward deinstitutionalization, normalization, and inclusion for individuals with developmental disabilities.
The attributes of PBS are consistent with the mission of the Department of Developmental Services (DDS) that aspires to partner with the individuals we support and their families, to support lifelong planning and to join with others to create and promote meaningful opportunities for individuals to fully participate as valued members of their communities.<br>
04
4 The Traditions of Applied Behavioral Analysis
An ABA program analyzes the interaction between purposeful behavior and a changeable environment, especially operant conditioning.
The strength of ABA is focusing a narrow lens on intervening and modifying a specific behavior through prescriptive techniques that are data-driven. That is, concentrating on what occurs directly before, during, and after a maladaptive behavior in order to form a functional hypothesis as to why the individual is behaving in a certain way.
ABA is developed by Board Certified Behavioral Analysts. This approach has been demonstrated as very effective for individuals diagnosed with an autism spectrum disorder.
Agencies and families should appreciate the strengths and limitations of ABA, especially the potential for over-applying the model in cases with more complex behavioral challenges.<br>
05
5 Why not rely on a Medical Model?
Maladaptive behaviors are conceptualized as a sign of an underlying disease or reflective of impairment, rather than serving a function.
It assumes that “abnormal” behavior is a symptom of the diagnosis. For example, “Joe acts out because he has an intellectual disability. That is just how he is.”
It is expert-driven with little input from the individual and family served.<br>
06
What are the Problems with
Consequence-Based Interventions? Ethical concerns (e.g., poor respect for rights and dignity)
Do not teach new replacement behaviors
Setting of points and the earning of levels are clinically contra-indicated
Even minor coercion can give rise to negative psychological effects, such as lowered self-esteem, feelings of frustration, and a sense of rejection.
Counterintuitively, when coercion is ineffective in changing behavior, people who favor it tend to use it even more!
George Sugai describes a “Cycle of Coercion” that suggests we all need to
understand our contribution in events and that when a behavior doesn’t
work tend to escalate.<br>
07
7 Why Use a Positive Behavioral Support Approach? Humanistic
Individual- and family-centered
Holistic (a comprehensive approach that views behaviors as goal-directed and interconnected with physiology, situational context, cultural variables, and psychological factors).
Evidence-Based (empirically supported through randomized and controlled research, incorporates clinical expertise and relevant findings from various disciplines, and the preferences of the individual-served)
Accountability
Sustainability<br>
08
8 Positive Behavior Support
Design and Evolution
PBS is an all-encompassing approach that emerged from the controversy surrounding the escalating use of aversive procedures and consequence-based interventions.
It blends values about the rights of persons with developmental disabilities with a practical science about behavioral change.
In reflection of its wide applicability, PBS has been espoused by national organizations (e.g., National Association of State Directors of Developmental Disability Services) and driven by federal mandates (e.g., Individuals with Disabilities Education Act) for use in school systems.<br>
09
9 Benefits of PBS
Individuals with intellectual and developmental disabilities often present with a complex array of needs that are manifested in one’s “behavior.” A global approach to assessment and interventions that is developed through broad education, diverse training, and a depth of experience is required.
PBS is a blending of knowledge and methods from multiple disciplines, such as biology, developmental psychology, behaviorism, systems theory, and trauma-informed care.
As a result, PBS integrates well with other clinical and collaborative supports, such as individual services (e.g., psychotherapy) and a multidisciplinary team process (e.g., nursing, psychology, psychiatry, occupational therapy).<br>
10
10 Implementation
Service agencies like DDS are often challenged by the limited supply of direct care staff needed to implement behavioral plans.
While ABA tends to require trained professionals to administer, PBS offers advantages in service delivery, which lend to its broad appeal. These include:
A relatively colloquial vocabulary
An emphasis on supports as opposed to technical interventions
Suitability for non-academically trained staff of varied backgrounds.
PBS can be used at an organizational and an individual level, as it looks beyond merely eliminating challenging behavior towards changing systems, improving environments, emphasizing prevention, and teaching adaptive skills.<br>
11
11<br>
12
Support for Positive Behavior
Support = Encouraging, increasing, and strengthening
Positive Behavior = desirable, adaptive, and prosocial
Versus
Non-Positive Behavior Support
Use of aversive, humiliating, or stigmatizing interventions Defining Positive Behavior Support<br>
Support = Encouraging, increasing, and strengthening
Positive Behavior = desirable, adaptive, and prosocial
Versus
Non-Positive Behavior Support
Use of aversive, humiliating, or stigmatizing interventions Defining Positive Behavior Support<br>
13
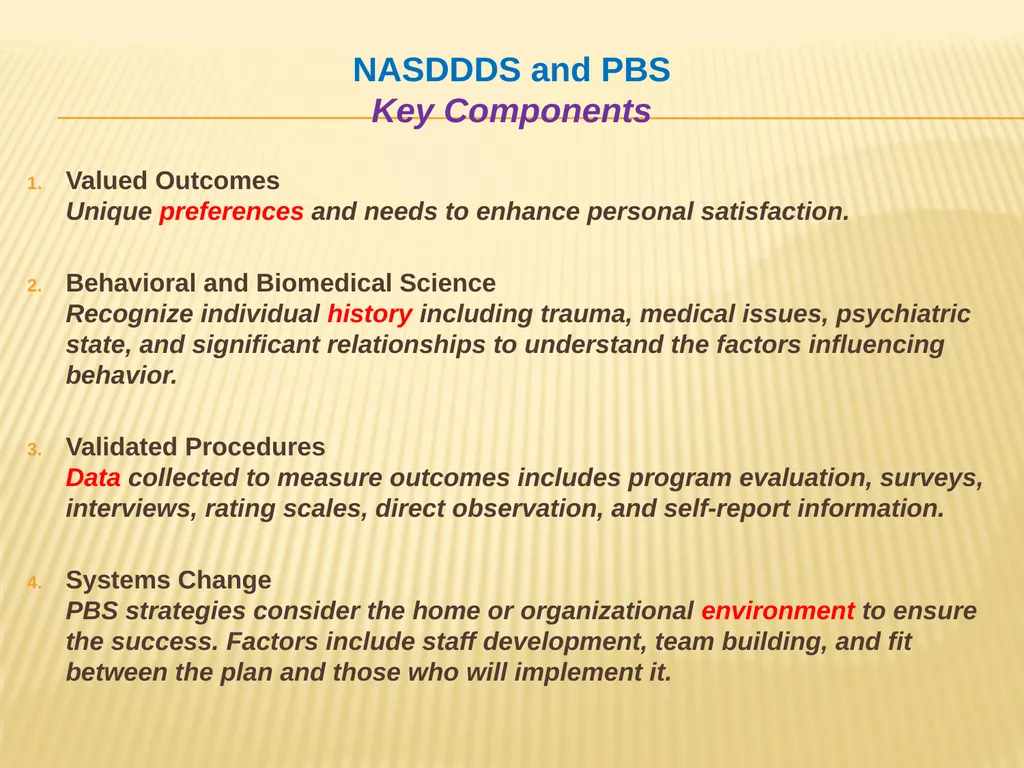
Valued Outcomes
Unique preferences and needs to enhance personal satisfaction.
Behavioral and Biomedical Science Recognize individual history including trauma, medical issues, psychiatric state, and significant relationships to understand the factors influencing behavior.
Validated Procedures Data collected to measure outcomes includes program evaluation, surveys, interviews, rating scales, direct observation, and self-report information.
Systems Change PBS strategies consider the home or organizational environment to ensure the success. Factors include staff development, team building, and fit between the plan and those who will implement it. NASDDDS and PBS
Key Components<br>
14
Positive Behavioral Supports Hallmarks and Strategies:
Lifespan perspective
Proactive teaching of expectations and acceptable behaviors
Building on existing appropriate behaviors
Monitoring problem behaviors
Data-driven decisions and evaluation of effectiveness
Intense efforts for support
Improving quality of life
Integrity with implementation and responsiveness 14P<br>
15
Practical Components of PBS Functional Assessment
Information gathering process
Comprehensive Interventions
Preventative techniques, intensive strategies, crisis plans
Lifestyle Enhancement
Person-centered planning
Team Approach
Collaboration to support the process<br>
Information gathering process
Comprehensive Interventions
Preventative techniques, intensive strategies, crisis plans
Lifestyle Enhancement
Person-centered planning
Team Approach
Collaboration to support the process<br>
16
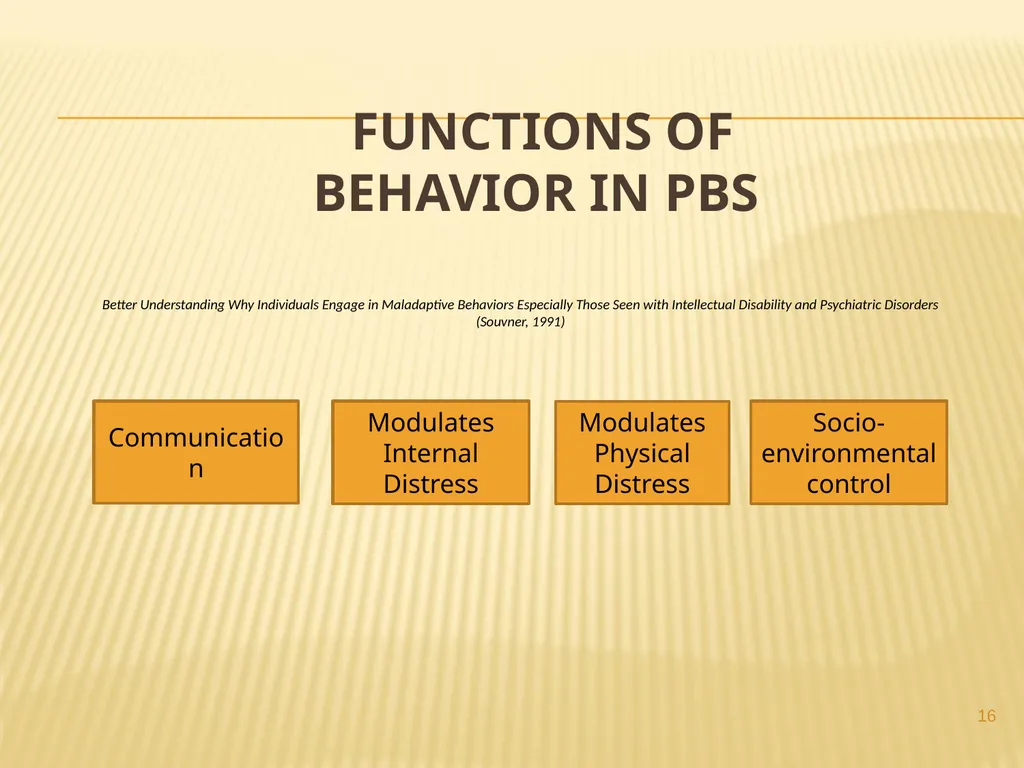
Better Understanding Why Individuals Engage in Maladaptive Behaviors Especially Those Seen with Intellectual Disability and Psychiatric Disorders
(Souvner, 1991) 16 Communication Modulates Internal Distress Modulates Physical Distress Socio-environmental control Functions of
Behavior IN PBS<br>
17
Four Main functions
of Behavior in ABA Attention(positive/negative)
Desire for attention from others, can include “power”
It is person specific=not event or location
Escape/Avoidance
From a person, task, environment, etc.
Behavior occurs in response to specific person, event, or requests to perform activity.
Sensory
Behavior feels good or meets a sensory need
Not person, event or location specific, but may occur more often when under stress.
Tangible
Desire for a specific item or activity
Behavior occurs when something has been denied; it is not person or event specific. 17<br>
18
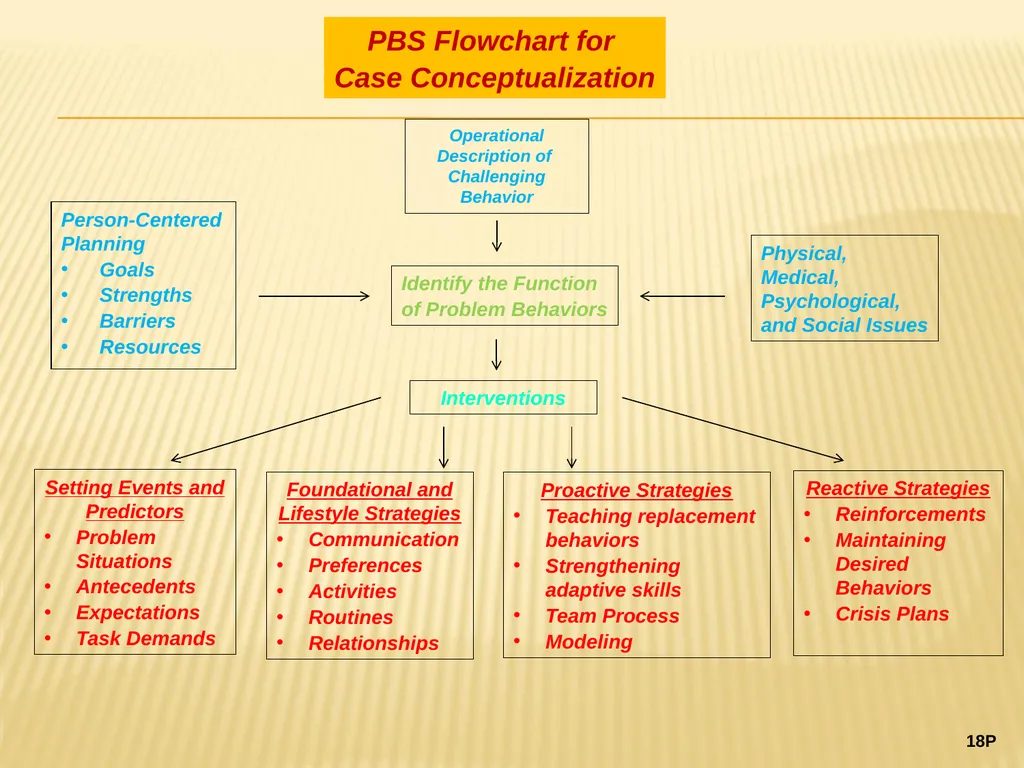
Operational Description of Challenging Behavior Person-Centered Planning
Goals
Strengths
Barriers
Resources Identify the Function
of Problem Behaviors Physical, Medical, Psychological, and Social Issues PBS Flowchart for
Case Conceptualization Proactive Strategies
Teaching replacement behaviors
Strengthening adaptive skills
Team Process
Modeling Foundational and Lifestyle Strategies
Communication
Preferences
Activities
Routines
Relationships Setting Events and Predictors
Problem Situations
Antecedents
Expectations
Task Demands Reactive Strategies
Reinforcements
Maintaining Desired Behaviors
Crisis Plans Interventions 18P<br>
19
Positive Behavior Support Serves
Multiple Aspects of an Individual
Person-Centered :
Respects self-determination (e.g., person-first language, individual strengths, informed consent)
Not a “cookbook” approach
Positive Changes in the Environment:
Identify ways to consistently support new skills across settings
Eliminate negative consequences, coercion, and restrictions
Collaborative:
Caregiver training for competency is key to effectiveness
Keep everyone involved as part of the interdisciplinary team (e.g., individual-served, family members, psychiatrist, occupational therapist, psychotherapist, job coach)
Feedback loops between direct care staff, caregivers, and team 19T<br>
20
Overarching Goal of Positive Behavior Support The aim is the presence of targeted adaptive and prosocial behaviors through teaching, not just the absence of challenging behavior. 20P<br>
21
21 Personal Background gathered from the records and collateral sources may be included to better understand the biopsychosocial history of the person-served:
Demographics
Achievements and delays in developmental milestones
Family relationships and dynamics
Trauma, abuse, and neglect history
Physical and medical conditions
Neurological impairments (e.g., seizure disorder)
Intellectual functioning (i.e., cognitive strengths and weaknesses)
Adaptive functioning (i.e., skills and deficits in meeting age-related and sociocultural standards in the conceptual, practical, and social domains)
Educational and vocational history
Review of the Relevant History:
Include pertinent information from the diagnostic profile and clinical formulations
Describe any salient risk factors (e.g., suicidality, substance abuse, maladaptive personality traits, psychosexual issues, legal involvement)
Discuss any recent changes in mental status, such symptoms of psychiatric illness
Response to psychotropic medications
Note current psychosocial stresses
Identify the goals and readiness to change of the person-served
Emphasize personal strengths (i.e., interests, preferences, skills, protective factors, and supports) A Comprehensive PBS Plan<br>
22
22 A Comprehensive PBS Plan Referral Questions:
Identify the reasons that prompted the development of the positive behavioral support plan. For example, describe the ways in which the behaviors of concern (e.g., aggression, refusals) interfere with performance, participation, and/or progress.
Rationale for the Interventions:
Describe the predisposing, precipitating, perpetuating, and protective factors that may influence the behavioral presentation. For example, low frustration tolerance and difficulties delaying gratification associated with severe intellectual disability often lead to impulsive behaviors.
Obtain a history of the successes/failures of previous interventions
What is the level of assistance that the person-served needs to learn and retain new information about their behavior (e.g., prompting, demonstrations, visual cues, verbal reminders, line of sight supervision)?<br>
23
23 A Comprehensive PBS Plan
Technical Aspects to a Functional Behavior Assessment Topography: A clear description of how each behavior of concern is performed that includes information about the frequency/rate, intensity, severity, and duration. The behaviors should be described in measurable and observable terms that everyone understands.
Setting Events and Vulnerabilities: Situations in the environment combined with the deficits of the person-served where the behavior of concern is most and least likely to occur.
Antecedents: The internal and/or external factors that occur before the behavior that might have triggered it. Consideration should be given to fast (immediate) versus slow (delayed) triggers. Categories of triggers include the following:
Physiological (physical issues)
Psychological (emotions, feelings or thought processes)
Social (situations involving other people)
Environmental (the surroundings)
Precursors: Noticeable changes in the body language of the person-served that came before the behavior of concern (e.g., pacing, pressured speech, rolling their eyes, and clenching their fists).
Maintaining Consequences: Events that occur after the behavior. How did the caregivers respond immediately after the behavior of concern occurred? Is there inadvertent reinforcement of the challenging behavior?<br>
24
24 Does the person-served understand the behavioral expectations for the situation?
Does he or she realize they are engaging in unacceptable behavior?
Is the problem behavior associated with certain environmental conditions? For example, who is present and what interactions take place prior to and immediately after the behavior?
What has worked in the past to help stabilize behavior versus what has not?
What was the individual thinking and feeling before the behavior of concern?
Is it within the individual’s ability to control the behavior?
Can the person-served identify acceptable behaviors to replace the maladaptive behavior?
Does the individual have the capacity, ability, and skills necessary to perform the new behavior?
What modifications to the environment that have been tried to reduce problem behaviors and support more adaptive behaviors? A Comprehensive PBS Plan
Develop a Functional Assessment to
“Anchor the Interventions” through Key Questions<br>
25
25 Identify the Behaviors of Concern to decrease or eliminate in the following hierarchy:
Behaviors that threaten health and safety, such as physical aggression, self-injury, property destruction, and refusals with medical care.
Behaviors that pose a barrier to participation in services, such as verbal outbursts and refusals.
Inappropriate behaviors that hinder adaptive and social functioning, such as poor compliance with hygiene and isolative behaviors.
Identify the Target Positive Behavior(s) to increase through teaching, shaping, and reinforcement:
Describe the adaptive and prosocial behaviors that will serve as replacements for behaviors of concern. For example, putting feelings into soft speech and polite words, rather than shouting to express frustration and disappointment. They should always have a direct “correspondence” to the behaviors of concern they are replacing.
Always be mindful that the overarching goal of positive behavior supports is the presence of targeted adaptive behaviors, especially an emphasis on the development of prosocial behaviors, rather than merely the absence of challenging behavior. A Comprehensive PBS Plan<br>
26
26 A Comprehensive PBS Plan Reactive Interventions:
Caregivers’ actions to restore calmness and maintain safety.
By definition, reactive strategies typically prescribe exactly when and how to intervene when a behavior of concern occurs.
They should only be used when necessary (5-10%), as their goal is to either cut short the behavior of concern, to minimize its effect, or to extinguish it entirely. A behavior support plan should never be entirely based on reactive strategies!
Reactive approaches include the following examples:
Active Listening
Empathic validation
Sensory modalities for soothing and relaxation
Gentle redirection
Limit setting
Strategic giving-in
One-to-one supervision in the household and/or community<br>
27
27 A Comprehensive PBS Plan Lifestyle Enhancements:
These are a hallmark of any PBS approach.
They are based on the individual plan of the person-served, such as participation in pleasurable activities, opportunities for choice and control, meaningful relationships, and inclusion in community activities.<br>
These are a hallmark of any PBS approach.
They are based on the individual plan of the person-served, such as participation in pleasurable activities, opportunities for choice and control, meaningful relationships, and inclusion in community activities.<br>
28
28 A Comprehensive PBS Plan
Data Collection:
Graphs are a tool to clearly organize and record data. They allow us to continuously evaluate treatment effects, as behavioral change is a dynamic process.
Before implementing interventions, baseline data should be collected for a period of time to ensure a representative sampling. This allows us to compare the intervention data to the baseline data to determine whether the treatment is effective.
The horizontal axis of a graph tracks the passage of time. The vertical axis usually displays dependent variables, such as the frequency of the behaviors.
Line graphs are usually preferable to bar graphs because they easily show trends across time. Repeated measures (i.e., more data points) lead to greater confidence in estimating behavioral patterns.
In addition to data points, significant changes in the course of treatment that may affect behavior can be reflected in the graphing. These interaction effects may include medication changes, emergent health issues, revisions in the behavioral strategies, and increased engagement in community services.<br>
29
Documentation and Training Requirements:
A variety of methods can be used to ensure fidelity to the behavioral support plan. These may include in-service trainings, periodic data reviews in team meetings, weekly clinical supervision, and ongoing consultations.
Criteria for Success and Determining Effectiveness:
Meaningful improvements in quality of life for the person-served, such as making better choices and demonstrating increased self-regulation over their emotions.
Strengthened use of their desired adaptive behaviors and better engagement in alternative coping skills.
Decreases in the frequency, intensity, and duration of challenging behavior.
Reduction in the reliance on crisis interventions by caregivers. A Comprehensive PBS Plan<br>
30
30 Sample ABA Plan<br>
31
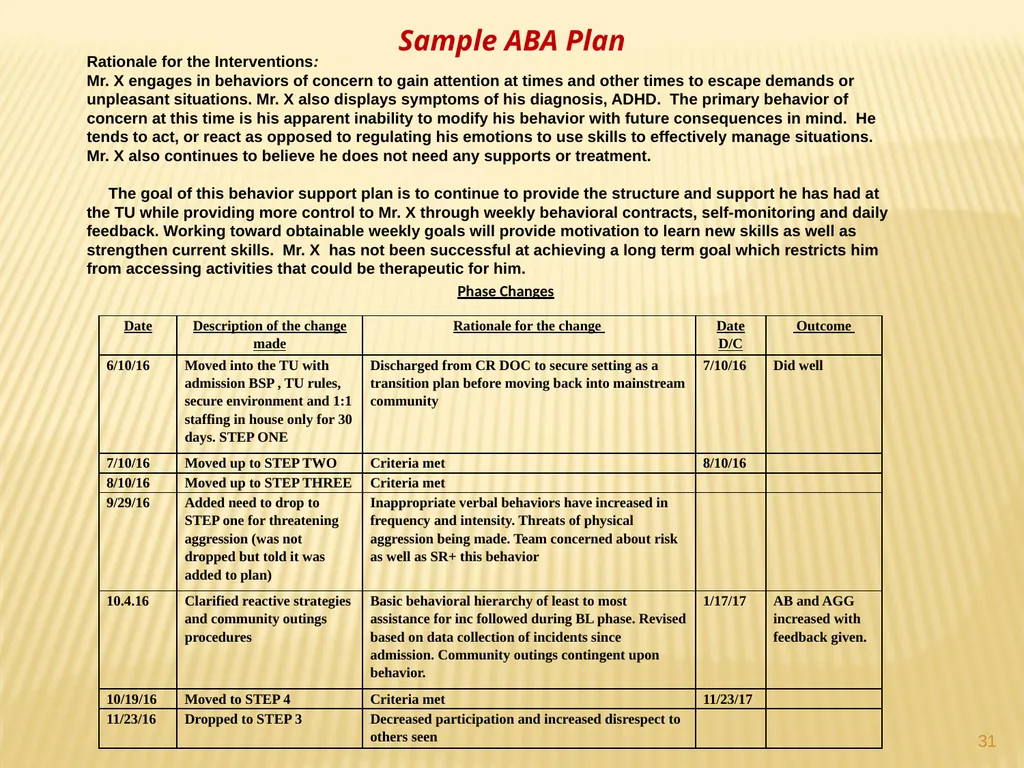
31 Rationale for the Interventions:
Mr. X engages in behaviors of concern to gain attention at times and other times to escape demands or unpleasant situations. Mr. X also displays symptoms of his diagnosis, ADHD. The primary behavior of concern at this time is his apparent inability to modify his behavior with future consequences in mind. He tends to act, or react as opposed to regulating his emotions to use skills to effectively manage situations. Mr. X also continues to believe he does not need any supports or treatment.
The goal of this behavior support plan is to continue to provide the structure and support he has had at the TU while providing more control to Mr. X through weekly behavioral contracts, self-monitoring and daily feedback. Working toward obtainable weekly goals will provide motivation to learn new skills as well as strengthen current skills. Mr. X has not been successful at achieving a long term goal which restricts him from accessing activities that could be therapeutic for him. Phase Changes Sample ABA Plan<br>
32
32 Name: _Mr. X
Behavioral Objective(s):
Given a structured daily schedule which outlines daily responsibilities, Mr. X will complete each task with assistance as needed to do so correctly with 90% independence for 6 consecutive months by 8/19.
Given instruction, direct support, and weekly group therapy meetings, Mr. X will demonstrate respect to himself and others and in all settings (as defined in BSP) with 90% success maintained for 6 consecutive months by 8/19.
Mr. X will demonstrate the ability to manage emotions by using skills as taught independently or with assistance as needed to decrease incidents of targeted behaviors by 10% of the annual average by 8/19.
Mr. X will maintain safe behavior (as measured by 0 incidents of fire setting) for 12 consecutive months by 8/19.
Target Positive Behavior(s) to increase:
Respect for Self – defined as completing personal care tasks as listed on daily schedule, taking prescribed medications, following healthy diet, participating in exercise weekly, using good hygiene skills (i.e. handwashing, etc.), attending medical and therapy appointments. Following Dr. orders and using skills learned to maintain emotional stability. Adhering to boundaries and limitations set to ensure health and safety.
Respect for others – defined as being kind and courteous to others, helping others when needed, working cooperatively with staff as needed, talking to others appropriately (refrain from insulting comments or teasing), sharing staff attention and time with housemates, using manners in the presences of others, and using skills learned to resolve conflicts with others as needed. Showing respect for authority figures and professionals
Respect for home– defined as keeping living area clean and neat, participating in household chores, using household appliances safety and correctly, picking up after himself in main living areas of the home, dispose of trash and recycle items, and avoid reckless behaviors that cause environmental damage
Respect for community – showing respect for others in the community (courteous, refrain from negative comments or insults), follows safety rules in community (pedestrian safety, move away from emergency situations), uses community resources appropriately (banks, stores, Medical facilities, recreational events) abiding by the laws of the community (no stealing, no fire setting, no harassing others).
Using skills to manage emotions – use of skills taught to self-regulate emotions to work toward identified goals as opposed to impulsively reacting negatively. Sample ABA Plan<br>
33
33 Proactive Interventions:
The design of the TU includes a Level system which provides a therapeutic approach including:
Teaching and strengthening Daily living skills
Individual instruction /
Individual and Group therapy
STEP Progression Plan
These are described in more detail in the Transitional Unit Behavioral Support Plan
Daily Responsibilities
Mr. X will have a Structured Daily Schedule of responsibilities and scheduled activities.
Staff will assist him as needed to complete tasks focusing on teaching how to do each task correctly to promote independence.
Social Praise will be given randomly throughout the day for completing each task.
Staff will score each task on his schedule as it is completed. 1= Mr. X completed the task independently (no prompting or assistance from staff). 2=Mr. X completed the task with prompting (a reminder to do it or prompts to do it correctly) or 0 =he was prompted but refused to do it. If a task is not needed to be done that day, score N/A.
Access to community outings will be contingent upon completion of daily responsibilities prior to the planned outing times.
Self –Monitoring
Mr. X will self-monitor by checking off daily responsibilities after completing them.
Mr. X will learn how to accurately self-monitor through an initial training and weekly review with the behaviorist
In addition, staff will prompt Mr. X how to score based on their scores and data collection with periodic checks throughout the week.
As Mr. X demonstrates accuracy in self-monitoring data collection, staff checks will be faded.
As Mr. X demonstrates mastery of his daily responsibilities and use of skills when needed, the need to document his own data will be faded.
The goal is to increase self-awareness of his own behavior and decrease dependency on staff prompting (which Mr. X finds aversive). Sample ABA Plan<br>
34
34 Targeted Behaviors of Concern:
Impulsive responses to emotions – immediate negative reaction to emotions as demonstrated by making statements that are defensive, provocative, oppositional, or threatening.
Opposes support (OS) – refusing to do what is asked, arguing about doing tasks, refusing support offered to complete tasks or learn skills. Not following rules, refusing to attend individual therapy or groups
Antagonistic Behavior (AB) – comments or actions made directed at someone that intentionally insults, offends, or agitates them. This typically includes making an accusation staff did/did not do something, comments made to or about other individuals for them to hear that provokes them.
Untrue Statements (US) – making statements that cannot be verified as true, Accusations about staff, Denies he has done things that he was seen doing or there is substantial evidence he has done
Agitation (AGG) – yelling, making derogatory statements, excessive demands to have needs/wants met immediately, verbally threating others, threats to harm himself, oppositional statements.
Historical Behaviors to monitor
aggression to others
environmental aggression
fire setting
Elopement
Stealing. Sample ABA Plan<br>
35
35 Prevention and Precursor Strategies
Mr. X has a history of setting fires. IT IS CRITICAL NO MATCHES OR LIGHTERS ARE LEFT UNATTENDED. Staff is NOT to bring any lighters or matches into the facility.
Keeping Mr. X focused on his long term goals and how he can achieve them is helpful in encouraging him to make good choices, use skills, avoid breaking rules or being disrespectful.
Use of skills to manage emotions that occur daily is critical. Mr. X needs a great deal of support and instruction to use skills, couching how to use skills and reinforcement for using them as needed.
Staff is included in the weekly skills training to learn, practice and review skills to be prepared to coach him as needed. Staff will assist Mr. X with skills homework throughout the week.
Whenever he initiates using a skill or uses a skill with prompting and support, praise him for doing so.
Upon seeing any signs of emotion dysregulation, remind Mr. X to focus on his skills before reacting to his emotions. Sample ABA Plan<br>
36
36 Reactive Procedures for targeted behaviors to decrease:
Impulsive Reaction to emotions:
Stop interacting with Mr. X to give him the chance to stop/correct his behavior. If he does not do so on his own and the behavior continues, Let Mr. X know he is being disrespectful (to himself or others) and remind him to use his skills.
If he stops, praise him for doing so. Allow him time to use skills to regulate his emotions before moving on.
If he doesn’t stop and behavior continues, ignore the behavior (meaning does not continue talking about it with him as this gives him the opportunity to argue with you). Tell Mr. X to let you know when he is ready; remind him you can help him use skills if needed.
Do not get into a verbal altercation with him. Simply walk away and give him space. Interact with the other guys to keep them from saying something to Chris.
Once he is cooperative again, return to assist him as needed to complete the task, resolve the conflict, etc. He may not be ready to talk about it yet and may prefer to just move on with a task. That is fine for now.
Document the behavior that happened by placing a checkmark on the behavior data sheet under the targeted behavior that occurred. Complete the data sheet for each incident that occurs.
Once Mr. X has completely calmed (absent of any targeted behaviors to decrease, able to talk/listen –defined as intensity level 3) and is focused again, remind him to complete his diary card to describe the incident that caused him to become emotional. Offer to help him if needed. Sample ABA Plan<br>
37
37 Data Collection and Team review:
Data will be collected for each task on his daily schedule and graphed as % independent (1)
Overall Rating of Respect will be tallied and graphed daily
Presence of each targeted behavior tallied and graphed daily as # per day.
# behavioral chain assigned will be tallied and graphed
The current STEP achieved will be graphed daily.
Significant incidents will be documented on ABC sheets or 255 if needed and reviewed weekly
Internal clinical reviews are done weekly to discuss concerns. Data will be reviewed weekly by the behaviorist and shared with the internal clinical team.
Quarterly behavior reports will be done and shared with the IDT members.
PRC and HRC reviews as determined necessary by DDS regulations
Documentation and Training Requirements
Staff training and development will be conducted by the behaviorist, and monitored by house supervisors, to ensure staff proficiency
Reliability checks to ensure the integrity of the program and need for further training will be done as determined necessary.
Ongoing consultation and data review will be done by the behaviorist and will occur monthly at minimum. Data reviews will be done with the clinical team to determine need for revisions Sample ABA Plan<br>
38
38 Maintenance, Generalization and Fading procedures
The need for staff intervention, intrusive interventions, and supervision will be monitored based on the data and faded as progress is made by systematically fading prompts to offer more independence and decreasing the LOS as criteria is met and progress is made. Changes to the intervention and level of supervision are made following policies and procedures of the TU as well as meeting criteria as defined in the BSP. Maintenance and generalization is addressed by implementing the procedures across staff and settings
Program Author/ Title Sample ABA Plan<br>
39
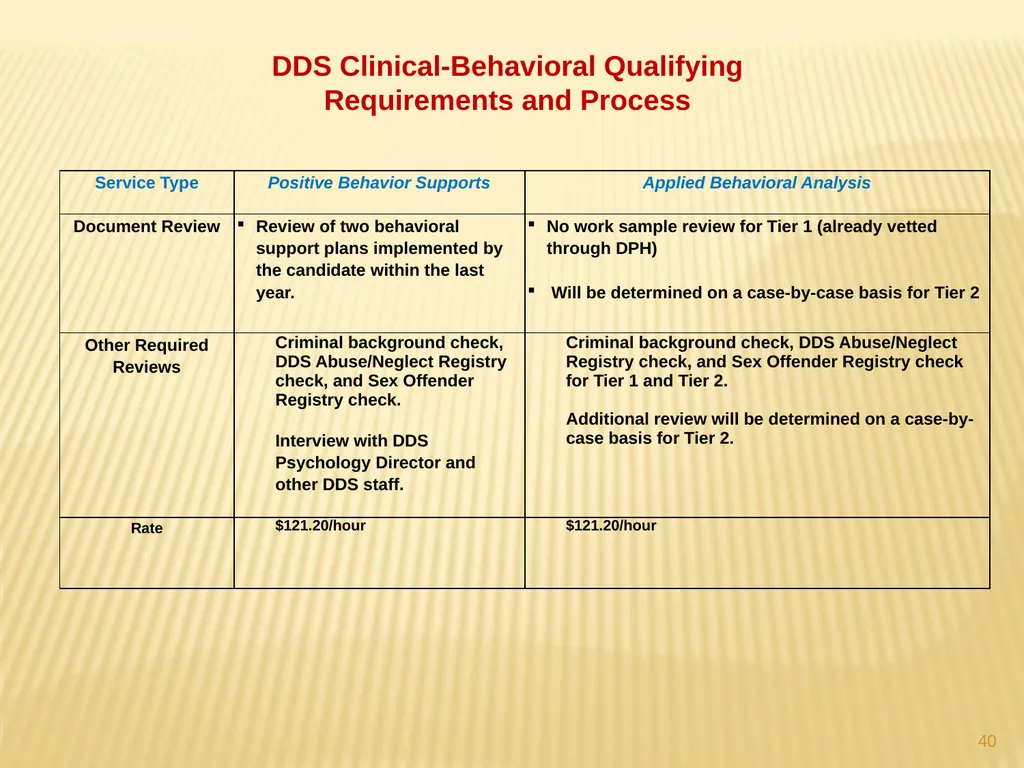
39 DDS Clinical-Behavioral Qualifying
Requirements and Process As of December 1, 2018, the qualification and authorization system
will be divided into two sub-types:<br>
Requirements and Process As of December 1, 2018, the qualification and authorization system
will be divided into two sub-types:<br>
40
40 DDS Clinical-Behavioral Qualifying Requirements and Process<br>